An overview of the Community Tool Box and frameworks for guiding, supporting and evaluating the work of community and system change.
admin
Building healthier cities and communities involves community members working together to transform the conditions and outcomes that matter to them. That work demands an array of competencies, such as community assessment, planning, mobilization, intervention, advocacy, evaluation, and communicating successful efforts. Supporting this local and global work requires widespread access to skills-building resources. This section describes a free, online resource for building healthier communities called the Community Tool Box.
What is the Community Tool Box?
Background
Our mission is to promote community health and development by connecting people, ideas, and resources.
We began this work in 1994, focused on developing practical information for community building that both professionals and community members could use in everyday practice -- for example, leadership skills, program evaluation, and writing a grant application. The emphasis was on these core competencies of community building, which can be applied across more specific issues and concerns, such as promoting child health, reducing violence, or creating job opportunities.
We developed a broad and evolving Table of Contents and started writing, one section at a time. Today, there are more than 340 sections online and more than 7,000 pages of text -- available across English, Spanish, Arabic, and Farsi, with translation coverage continuing to expand.
Audience
The audiences for this site include:
- People doing the work of community change and improvement (community leaders and members)
- People supporting it (intermediary organizations such as public agencies or university-based centers)
- People funding it (governmental institutions, foundations, and others)
Attributes
Building healthier communities is hard work, requiring frequent adjustments to emerging opportunities and barriers. To be a resource for community work, a "tool box" would exemplify the following attributes:
- Its content needs to be comprehensive. Since effective community members and practitioners need a variety of skills, sections of the Tool Box would have to reflect a broad array of core competencies (e.g., skills in conducting listening sessions, organizing focus groups, leading meetings, group facilitation, and recording).
- The information needs to be easily available on demand, and in particular readable, printable, downloadable, and accessible online from one location.
- The information must be useful, providing step-by-step guidance that the reader can apply directly in practice.
- The tone of the material should be friendly and supportive of users with varying levels of experience who may feel uncertain about what to do.
- Forums or other exchange mechanisms should be available to connect people who have relevant experience that can help facilitate applications and adjustments in diverse contexts and situations.
- An online resource should help reduce inequities, or certainly not increase them. By being widely available and free through the web, our tools may help reduce inequities in local capacity for community change and improvement.
- Since there is such high turnover among people and projects, the tools should help build capacity for continuous learning among current and future generations of those doing the work.
Conceptual framework for the core content
A conceptual framework or model for building healthier communities guides choices for core content in the Community Tool Box. Based on earlier conceptual models, this framework outlines a dynamic and iterative process with six phases, and related competencies, associated with facilitating community change and improvement:
- Understanding Community Context (e.g., assessing community assets and needs)
- Collaborative Planning (e.g., developing a vision, mission, objectives, strategies, and action plans)
- Developing Leadership and Enhancing Participation (e.g., building relationships, engaging participants)
- Community Action and Intervention (e.g., designing interventions, advocacy)
- Evaluating Community Initiatives (e.g., program evaluation, documentation of community and system change)
- Promoting and Sustaining the Initiative (e.g., social marketing, obtaining grants)
Both evidence-informed practice and practice-based and experiential knowledge inform choices for content development for the Community Tool Box. Ongoing research by members of the Tool Box team, and many others throughout the world, suggests key factors or components of successful efforts to bring about community change and improvement (e.g., leadership, having a clear and focused mission, and action planning).
Promising practices from this growing evidence base, and ongoing input from community leaders and practitioners, are used to focus content development on core competencies (e.g., building leadership skills, creating a vision and mission, and developing an action plan). Similarly, research and practice in behavioral instruction helped identify structural elements of the how-to sections or learning modules (i.e., what, why, how-to steps, etc.).
Framework for Building Healthier Communities: A Gateway to Illustrative Tools
Understanding Community Context
- Understanding and Describing the Community
- Developing a Plan for Assessing Local Needs and Resources
- Collecting Information About the Problem
- Analyzing Community Problems
- Analyzing Root Causes of Problems: The "But Why?" Technique
Collaborative Planning
- VMOSA (Vision, Mission, Objectives, Strategies, Action Plans): An Overview
- Proclaiming Your Dream: Developing Vision and Mission Statements
- Creating Objectives
- Developing Successful Strategies: Planning to Win
- Developing an Action Plan
- Identifying Strategies and Tactics for Reducing Risks
- Promoting Coordination, Cooperative Agreements, and Collaborative Agreements Among Agencies
- Developing Multi-sector Collaborations
Developing Leadership and Enhancing Participation
- Developing a Plan for Building Leadership
- Servant Leadership: Accepting and Maintaining the Call of Service
- Developing a Plan for Increasing Participation in Community Action
- Promoting Participation Among Diverse Groups
- Methods of Contacting Potential Participants
- Developing a Plan for Staff Hiring and Training
- Developing a Plan for Involving Volunteers
- Providing Supervision for Staff and Volunteers
- Conducting Effective Meetings
Community Action and Intervention
- Strategies for Community Change and Improvement: An Overview
- Designing Community Interventions
- Adapting Community Interventions for Different Cultures and Communities
- Developing a Plan for Advocacy
- Organizing Study Circles
- Registering Voters
- Organizing Public Demonstrations
Evaluating Community Initiatives
- Our Evaluation Model: Evaluating Comprehensive Community Initiatives
- A Framework for Program Evaluation: A Gateway to Tools
- Developing an Evaluation Plan
- Measuring Success: Evaluating Comprehensive Community Initiatives
- Gathering and Using Community-Level Indicators
Promoting and Sustaining the Initiative
- Understanding Social Marketing: Encouraging Adoption and Use of Valued Products and Practices
- Working with the Media
- Making Community Presentations
- Using Principles of Persuasion
- Creating a Website
- Achieving and Maintaining Quality Performance
- Developing a Plan for Financial Sustainability
- Strategies for Sustaining the Initiative
- Applying for a Grant: The General Approach
How do you get around the Tool Box?
Upon arrival at any desired section, the reader will find several choices:
Main Section -- the text of the section with these components: What (a clear description of the skill), Why (rationales or descriptions of consequences for using or not using the skill), When (the conditions under which the skill should or should not be used), and How (descriptions of the discrete behaviors that constitute desired performance). The Main Section also contains a Resources list that details sources of information, contacts, and related websites.
Examples -- specific real-world illustrations or stories of using the skill that reflect varied issues or concerns (e.g., substance use, child and youth development, urban community development) and places or contexts (e.g., urban, rural, or specific cultural communities).
Tools & Checklists -- Tools provide training and technical assistance materials such as exercises and handouts; Checklists provide prompts or brief phrases to help you remember important considerations and steps.
PowerPoint -- ready-to-use or adaptable summaries of the section that may be useful in providing training and technical assistance.
In addition, we use customized gateways or guided pathways to maximize efficient access to valued tools. One type of gateway uses promising models or frameworks (e.g., Community Health Improvement Process, A Framework for Program Evaluation, or Writing a Grant Proposal) to guide the reader to core competencies related to each phase and operation of the framework (e.g., forming a coalition, identifying stakeholders, documenting the problem). These frameworks help orient the community practitioner to recommended activities -- and related how-to information -- that can help support the local effort.
Another valued gateway is the Troubleshooting Guide. This access point starts with a list of commonly faced problems in the work of community change and improvement.
By selecting a particular problem situation (e.g., "There is not enough action to promote change."), the reader calls up a list of clarifying questions (e.g., "Does the group know the specific changes we want to see made?" or "Do we have enough members to carry out our actions?"). Should the answer to any question be "No," the user may follow links to retrieve related how-to information (e.g., "Developing an Action Plan," "Recruiting Members," "Recognizing Allies"). Since we may be more open to learning new skills when facing a challenge, the Troubleshooting Guide provides valuable user-tailored access to the tools.
Ways to Use the Community Tool Box
The Community Tool Box has been used for several specific purposes:
- For training and technical assistance. For example, many support organizations, including our University of Kansas Center for Community Health and Development, have used the tools in periodic workshops and ongoing consultation. They have been used to support a variety of community-based initiatives, including those addressing specific issues such as adolescent pregnancy or substance use, and broader issues such as child and youth development, public health, or urban community development.
- As readings and learning resources for in-person and online courses. For example, Community Tool Box materials can be used to create distributed learning communities among students, community members, and practitioners in different locations.
- To help build capacity of community-building initiatives. These resources support competency-building among large numbers of community members and practitioners engaged in this work. These tools are being used to support the community work of a wide range of people in diverse contexts throughout the world.
Entries in the Guestbook suggest that users span ages, roles, communities, countries, and continents. They include community members, leaders, and professionals working in such domains and disciplines as public health, child and youth development, environmental justice, education, mental health, social and human services, peer support and mutual aid, international development, policy advocacy, rural development, and urban community development.
Challenges, Strengths, and Future Prospects
Several prominent challenges must be addressed to enhance the utility of the Tool Box:
We need to continue to extend the breadth, depth, and generality of core content.
By partnering with others with technical and experiential knowledge, we hope to enhance the breadth of content topics, the depth of how-to information, examples, stories, and tools, and the generality of application across different issues (e.g., child health, violence), cultures and regions (e.g., Africa, the Middle East), languages (e.g., Portuguese, French), and contexts (e.g., urban, rural, global).
We need to enhance the interactivity of the Community Tool Box.
We seek to make greater use of online and other interactive communication tools to connect people with complementary knowledge and experience.
We seek widespread adoption and use of the tools and competencies in community practice.
Social marketing efforts include links from related sites, brochures and other materials where useful, email and other digital outreach to current and prospective users, and partnerships with state, national, and global initiatives for community health and development.
The Community Tool Box is an extraordinary resource for teaching and learning:
- It offers extensive information for supporting development of core competencies in building healthier communities.
- It allows input from the field about promising practices for community work. By linking with a growing local and global community of community leaders and practitioners, the Community Tool Box can help identify and communicate innovations emerging from the diverse but related work of community change and improvement.
- The Community Tool Box provides a powerful resource for sharing practical information that supports community work. By partnering and linking with state, national, and global networks, we can promote widespread adoption, adaptation, and use of tools for community transformation.
There are several future prospects for using communications technologies to help create a civic ecology -- an environment in which local people routinely work together to affect the conditions and outcomes that matter to them.
- This will demand a support infrastructure for expanding reach -- for making civic work easier and more rewarding for large numbers of people in many different communities. Digital communications and other emerging technologies -- including resources such as the Community Tool Box -- can be used to help build capacity for community change in the many local contexts that might benefit.
- Imagine a connected exchange network that brings together a diverse community of people engaged in transformational work. For example, online and other interactive spaces might connect people addressing different specific issues (e.g., stopping violence, improving childhood outcomes), perhaps helping reveal the underlying social determinants of related concerns. These spaces could connect people with diverse experience -- for example, people newer to and more experienced in the work, or people with different experiences of inequity and institutional influence. They could also help connect those who work in different places (e.g., urban neighborhoods and rural communities) and communities with different racial, ethnic, linguistic, and cultural backgrounds.
- Digital communications and emerging technologies can help connect people -- both locally (e.g., across neighborhoods and cultural communities in the same city) and globally (e.g., across communities in different states, provinces, or nations).
In summary
Building healthier cities and communities fits with global trends of self-determination and democracy building. The widespread and growing availability of online resources, such as the Community Tool Box, offers flexible and efficient means to support the expression of local concerns and innovations, connect people in common purpose, and share tools for amplifying local work. Such innovations can transcend distance in promoting civic participation and connections across communities of place and interest.
Imagine: broad, affordable access to tools for community building and transformation in homes, local libraries, faith communities, schools, community organizations, and public buildings. In this evolving civic ecology, we join together in common purpose across space and time -- furthering the work of democracy and reducing the inequities that hinder our pursuit of justice.
Contributor
Stephen B. Fawcett
Vincent T. Francisco
Jerry A. Shultz
Genevieve Nagy
Bill Berkowitz
Thomas J. Wolff
Resources
Print Resources
Holt, C.M., Fawcett, S.B., Schultz, J.A., Jones, J.,Berkowitz, B., Wolff, T., Francisco, V.T., Rabinowitz, P., (2013): Disseminating Online Tools for Building Capacity Among Community Practitioners, Journal of Prevention & Intervention in the Community, 41:3, 201-211. http://www.tandfonline.com/doi/abs/10.1080/10852352.2013.788349
Holt, C. M., Fawcett, S.B., Schultz, J. A., Berkowitz, B., Wolff, T. J., Francisco, V. T. (2013). Building Community Practice Competencies
Globally through the Community Tool Box. Global Journal of Community Psychology Practice, 4(4), 1-8. Retrieved from http://www.gjcpp.org/.
Fawcett, S., Francisco, V., Hyra, D., Paine, A., Schultz, J., Russos, S., Fisher, J. & Evensen, P. (2000). Building healthy communities. In A.Tarlov (Ed.), Society and population health reader: State and community applications. New York, NY: The New Press.
Fawcett, S., Francisco, V., Paine, A., & Schultz, J. (2000). Working together for healthier communities: A research-based memorandum of collaboration. Public Health Reports, (115), 174-179.
Fawcett, S.B., Francisco, V.T., Schultz, J.A., Berkowitz, B., Wolff, T.J., & Nagy, G. (2000). The Community Tool Box: A Web-based resource for building healthier communities. Public Health Reports, 115(2&3), 274-278
Fawcett, S., Schultz, J., Carson, V., Renault, V., Francisco, F. (2002). Using internet based tools to build capacity for community based participatory research and other efforts to promote community health and development. In M. Minkler and N. Wallerstein (Eds.), Community based participatory research for health (pp. 155-178). San Francisco: Jossey-Bass.
Fawcett. S.B., Schultz, J.A., Francisco, V.T., Berkowitz, B., Wolff, T., Rabinowitz, R.W., and Wydeven Olverius, R. (2008). Using Internet Technology for Capacity Development in Communities: The Case of the Community Tool Box. In J. Rothman, et al. (Eds.), Strategies of Community Intervention (7th ed.), Eddie Bowers Publishing.
I understand that the Community Tool Box is:
___an internet-based resource for community change and improvement
I have an understanding that the goal is to:
___promote community health and development by connecting people, ideas, and resources
I understand that the audience consists of:
___people doing work for community change
___people that support
___people that fund it
Contributor
Stephen B. Fawcett
Vincent T. Francisco
Jerry A. Shultz
Genevieve Nagy
Bill Berkowitz
Thomas J. Wolff

Most of us want the same things from our communities. We want them to be safe from violence and illness; we want neighborhoods that are alive and that work well. And we would all like to have people who care for us and whom we trust.
But how do we develop a community like that? Our belief is that communities are built when people work together on things that matter to them. In this section, we'll talk about what we mean by that, and explore our idea of how we can get there from here -- what might be called our "model of change" or "theory of practice."
We'll start this section with some definitions that will help ground the ideas we are trying to get across. Then, we'll look at the advantages of collaborative efforts: why we believe it makes sense for people to work together to solve problems they share.
Next, we'll look at key partners in community efforts, and then, we will describe the model of change that is the focus of this section. We'll supplement that model with principles and values that we believe should influence how community efforts unfold. Finally, we'll close with some broad recommendations for working together to help build healthier communities.
Definitions: Community, health, partnerships, capacity
By community, we mean a group of people who share a common place, experience, or interest. We often use this term for people who live in the same area: the same neighborhood, the same city or town, and even the same state or country.
People may also consider themselves part of a community with others who have had similar experiences. For example, people may see themselves as part of a:
- Racial or ethnic community (for example, the Black community, the Latino or Hispanic community)
- Religious community (for example, the Catholic community, the Hindu community, or the Muslim community)
- Community of people with disabilities (for example, people with visual disabilities, developmental disabilities, or mental health conditions)
Finally, a community may be formed of people interested in the same things. For example, we may talk about the business community, the labor community, or the child advocacy community.
Community health refers to the well-being of everyone in a community. It asks the question, "How healthy are all of the members of our community? Our children and adolescents? Older adults? People experiencing poverty?"
Collaborative partnerships are alliances to improve the health of a community. They encourage people to get together and make a difference. For example, an effort to improve education might involve school officials, youth, parents, teachers, business representatives, and nonprofit staff and volunteers. Because these partnerships bring people together from all parts of the community, their efforts are more likely to be successful.
Community capacity refers to the ability of community members to make a difference over time and across different issues. Capacity isn't a one-time thing; like learning to ride a bike, it's not something that disappears once you've experienced it. And like riding a bike, we get better the more we practice.
For example, if a community that develops a successful collaboration around substance use decides later that rates of childhood immunization aren't high enough in their community, they might also work effectively to improve those rates. By applying what they learned while developing the substance use coalition (for example, ways to recruit members or to work with the media), they should be able to do a good job and effectively improve immunization rates. A community has demonstrated strong community capacity when it can bring about community changes over time and across concerns.
The power of collaborative partnerships
Collaborative partnerships are a powerful way to improve our communities. To improve our communities, we must all work together to solve problems.
One reason for this is that issues that matter to local people, such as child health, academic success, or substance use, don't fit into neat categories. The things that make one issue likely to become a problem usually affect other things as well. Defining our problems as being connected to other issues (and people) helps us to see the many ways in which we are linked together.
For example, take the case of a mother and father who both hold down several low-wage jobs. They don't have much time for their children, and they may smoke cigarettes to cope with all of their stress. Their children are exposed to second-hand smoke and other health hazards, such as cockroaches and lead paint in their substandard housing.
What are the results? For the children, spending less time with their parents may hurt their early development. Exposure to hazards increases their risks for chronic disease such as asthma. As a whole, the situation makes it more difficult for the children to succeed at school. Finally, opportunities for stable, well-paying employment may be reduced for the parents, their children, and their children's children.
Who should be involved?
It's important that the collaboration is as inclusive as possible. This means individuals from different parts of the community -- for example, representatives from schools, businesses, and government. It also means representatives from different levels -- for example, representatives from the neighborhood, the county, the state or province, and even the broader region or nation.
Key partners in a broad collaboration should include:
- People most affected by the issue
- Local members of existing community partnerships
- Support organizations and those who work closely with people affected by the issue
- Local policymakers
- Grantmakers
- Governmental agencies
Let's look at each of these partners more closely.
State and community partnerships
The most obvious member in a collaborative effort will be the community or state partnerships themselves -- the groups of people who are working directly to change their communities. These groups, which are often nonprofit organizations, are found in almost any community. Examples include:
- The Kansas City Partnership for Children
- The Piscataway Substance Abuse Coalition
- The Durham Teen Pregnancy Prevention Project
- The Bronzeville Community Initiative
It's important to realize that while these organizations will be part of a larger collaboration with funders and support organizations, they are also collaborative arrangements in their own right. That's because collaborative partnerships link organizations drawn from different parts of the community. For example, a community partnership to promote child health might include representatives from:
- The media
- The business community
- Area schools
- Civic and community organizations
- Youth organizations
- Local government
- Health organizations
- The faith community
- Financial institutions
People from each of these areas will be able to promote child health in important, unique ways. By working together, a strong partnership will exist in the community.
Support and intermediary organizations
The second partner in a broad collaborative partnership is support and intermediary organizations. Some local, regional, and statewide organizations can provide technical assistance for community partnerships. These intermediary organizations can help community partnerships build on the "core competencies" that are necessary for working on community issues. For example, a university research center might give advice on such topics as community assessment, strategic planning, advocacy, leadership development, and evaluation.
Intermediary organizations can also help assess what the partnerships need and provide them with that support. For example, state and county health departments can assist community groups by developing health data systems that provide county-level data (for example, the percentage of children without recommended immunizations). They and other related support organizations can also offer other information useful for making decisions.
Grantmakers and governmental agencies
Finally, grantmakers and governmental agencies are also important members in these broad collaborative partnerships. That's because foundations and governmental agencies can help create the conditions for community partnerships to be successful. How do they do this? Certainly, by providing the financial resources needed by partnerships and intermediary organizations. This is the most obvious of the ways in which funders contribute. Many groups rely strongly, if not completely, on funding from grantmakers or the government to survive.
However, this important contribution is only one way in which grantmakers and governmental agencies can contribute to a collaborative partnership. They can also foster community work in the following ways:
- By giving a group some funding, funders may make additional funding more likely by adding to the group's credibility.
- Grantmakers can use requests for proposals (RFPs) as a way to bring groups together around a common purpose. And, in doing so, they can forge ties among different people working in the same community.
- Finally, grantmakers and governmental agencies can also help make outcomes matter by awarding additional funding if groups attain their objectives.
With an understanding of all of these parts, let's look at how these partners can work together to improve their communities.
How to build healthier communities: A model for community change
There are five basic parts to this model:
1) Community context and planning
2) Community action and intervention
3) Community and system change
4) Risk and protective factors and widespread behavior change
5) Improving more distant outcomes (the long-term goals)
Here are a couple of general ideas to keep in mind as we go through this model:
- This model is meant to be fluid and interactive. For example, an understanding of the community context and planning should guide community action, which should affect community and system change, and so on.
- This model is meant to be a continuous cycle. For example, improvement in more distant outcomes, such as reduced rates of violence, should lead to a renewed cycle of planning and action for these or other issues that matter to members of the community.
The bottom line? There isn't a day when community work ends. In a healthy community, working together for the good of the community is a constant part of everyone's lives.
With these ideas in mind, let's look at the individual parts of this logic model or theory of action.
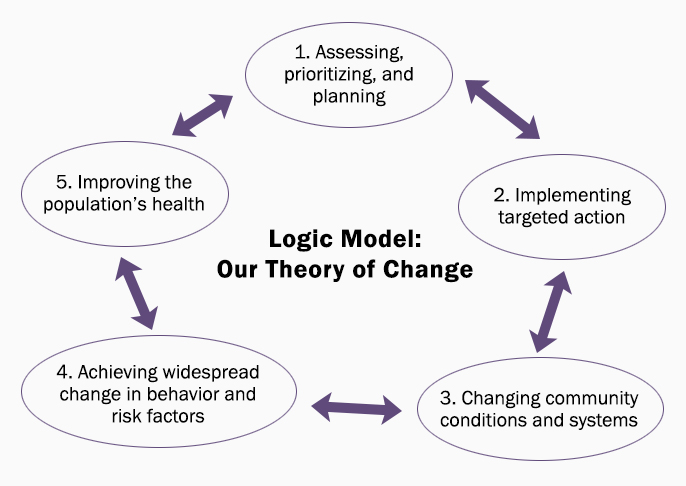
The Future of the Public's Health in the 21st Century. Institute of Medicine (US) Committee on Assuring the Health of the Public in the 21st Century. Washington (DC): National Academies Press (US); 2002.
1. Assessing, prioritizing, and planning
The first step is understanding the context, or the community conditions, in which people act. The context is influenced by many things, such as:
- People's hopes and expectations -- for example, the belief that things can change
- Challenges, especially poverty
- Strong and sustained leadership: a diverse team with vision, competence, and persistence
- Adequate financial resources
- Approval (or resistance) from the community or from those in authority when people attempt to change things
- The broader political and social context
Within this context, people may come together to identify issues that matter to them, such as transportation, job opportunities, affordable housing, or substance use prevention, to give just a few examples. They may gather and review community-level indicators to help understand markers for important measures in the community. For example, records of assaults at school are one community-level indicator of violence in the community; nighttime single-vehicle car crashes can be used as an indicator for substance use in a community.
Later in the life of the community group, these can serve as benchmarks for detecting whether or not they are making progress on their goals. For example, they can look at the level of violence and see if it has decreased since implementation of prevention strategies.
With an understanding of the context, the group can move forward with planning. Collaborative planning is a critical and ongoing task that brings together people and organizations with different experiences and resources. Together, they clarify or develop a vision, mission, objectives, strategies, and action steps for bringing about changes in the community.
2. Implementing targeted action
The planning process should be followed by taking action to implement the plan.
How can a community organization overcome any potential opposition? View this Troubleshooting Guide for different responses a group might make, depending on its particular situation.
3. Changing community conditions and systems
The goal of the action plan is to bring about community and system changes.
By community change, we mean developing a new program (or modifying an existing one), bringing about a change in policy, or adjusting a practice related to the group's mission.
Let's look at the following examples:
- A "safe ride" program giving free rides so people don't need to travel alone in unsafe areas after dark (a new program)
- Policy changes such as stronger penalties for people who commit crimes using a weapon (a change in policy)
- New employment practices that allow workers flexible time to be with children after school (a change in practice)
System changes are similar to community changes, but take place on a broader level. For example, a business might implement its family-supportive employment practices throughout its operations nationally.
Rockefeller Philanthropy Advisors defines systems change as, "a phrase used to explain an approach that targets the root causes of social issues instead of directly tackling the issue itself. It aims to alter or shift underlying structures such as policies, mindsets and power dynamics, which enable the system to function in a particular way."
4. Achieving widespread change in behavior and risk factors
When these community and system changes occur, they should, taken together, change the environment in which a person behaves. This is sometimes referred to as increasing protective factors and/or decreasing the risk factors of community members.
What are risk and protective factors? They are aspects of a person's environment or personal characteristics that make it more likely (risk factors) or less likely (protective factors) that a person will experience a given problem. Often, risk and protective factors can be considered flip sides of the same coin. For example, if drugs are readily available in your community, then easy accessibility is a risk factor. If they are very difficult to find, then limited availability is a protective factor. The intended effect of environmental change is widespread behavior change among large numbers of people in the community.
5. Improving the population's health
Improvements in more distant outcomes, such as reducing violence or increasing employment rates and family incomes, are the ultimate goals of collaborative partnerships.
As we discussed earlier in this section, data on community-level indicators can help you determine just how much progress you have made toward your goals. Information to see if efforts are working in different areas can be organized together in an annual community "report card." This can let people throughout the community know how things are going, including information on community-level indicators, important community changes, and success stories.
Before we go on, it may be helpful to look again at this process as a whole. Remember, this process is an interactive and continuous cycle.
- The community context affects the organization's planning
- Guided by ongoing planning, the group generates community action and implements interventions
- Community action brings about community and system changes
- These community and system changes, taken together, decrease risk factors and enhance protective factors
- This environmental change should affect the behavior of a large number of people in a positive manner
- This widespread behavior change should affect community-level indicators of improvement
Factors affecting the work of community partnerships
In all the different parts of our lives, some things work, and others don't. Why is that? Think for a moment about a school. Students have the same basic framework to work within; each grade has learning objectives, for example. Still, some students and schools succeed more than others. What causes that difference?
It's probably a combination of things -- support at home, a good teacher, and good (or not so good) materials to use. Quite simply, within a framework that almost all students have, different events often mean the difference between success and failure.
In the last few paragraphs, you have seen what we believe to be a workable model for building healthier communities. But like that school, what you've read is just a framework. And different events that happen within the framework make it more or less likely that a community group will succeed.
For improving the health and development of a community, we have found seven features that seem to be very important in determining whether a community effort is successful. In our research, each of the following "factors" has been related to the rate of community change. We'll look at them one by one.
Targeted mission
Having a targeted mission is one of the most important factors in whether or not a community group is effective.
A mission statement is your organization's statement of purpose; it tells what the organization is going to do and why.
For example, an organization's mission might be: "Our mission is to decrease pregnancies among adolescents and sexually transmitted infections in Dade County through a community-wide effort which will provide education and support to young people and their families."
Action planning
Action planning means identifying specific changes in the community or broader system, and action steps to bring them about. During action planning, community partnerships identify:
- The community or system changes (new or altered programs, policies, and practices) to be sought
- The actions that will bring about desired community or system changes
- Who will take those actions
- When they will be done
- What resources are needed to get the job done
When partnerships develop a plan of action, they are more successful in bringing about community change and improvement.
Changes in leadership
Involving competent leaders with a clear vision helps change to occur more rapidly. Such leaders see community partnerships as a way to mobilize the community, draw out people's strengths, and celebrate members' accomplishments. These leaders are likely to head effective collaborative partnerships.
The downside of this, of course, is that when such leaders leave an organization, the group's accomplishments often suffer. Finding a way to ease transitions and develop leadership within the group is an important factor in having groups that have long, successful lives.
Resources for community mobilizers
One thing that is clear is the need for people who act as catalysts -- community mobilizers who will really get things going in the community. They are the ones who will start the ball rolling on the actions that the group decides to take. By hiring or recruiting community mobilizers, groups consistently make more changes happen.
Documentation and feedback
To know whether a community group's efforts are making a difference, it is important that the group documents efforts and results. Such information about the group's accomplishments should be used to improve the group's ongoing efforts.
Documentation should occur for intermediate outcomes, such as community and system changes. Tracking these changes, as well as the group's longer-term goals, can help collaborative partnerships understand, celebrate, and improve their overall efforts.
Technical assistance
Good leaders work to attract competent people with skills that complement those of other people in the organization. By doing so, team members grow and become stronger in their work.
Outside help, which may take the form of technical assistance, can be a breath of fresh air for your organization. That's because the core competencies necessary for community organizations often transcend the variety of targeted missions and specialties people work in. For example, action planning will be important to community work on environmental advocacy, child maltreatment prevention, mental health, or almost any other community issue.
The goal of technical assistance should always be the same: to build the community's ability to take care of the things that matter to its members. This website is an example of this kind of assistance. The Community Tool Box contains more than 340 sections that can support technical assistance efforts.
Making outcomes matter
Finally, grantmakers and governmental agencies can help those they support by clearly stating and rewarding desired results. For example, a foundation in Kansas (U.S.A.) announced that continued funding would be based on evidence of progress. The result was that the amount of community change increased dramatically. This same grantmaker now uses bonus grants to encourage progress.
Possibilities for rewarding results include:
- Providing bonus grants for groups that accomplish important objectives
- Awarding outcome dividends -- that is, giving communities funds for reinvestment that they have effectively saved through prevention efforts
Ten recommendations for promoting community health and development
Throughout this section, we have talked about the three groups who are the important players in collaborative partnerships: local members of state and community partnerships, support organizations, and grantmakers and governmental agencies.
Much of the decision-making and work must happen within the communities themselves. However, all of these groups can work together and help create conditions under which it is more likely that community efforts will be successful. Based on the model we discussed above, we propose ten specific recommendations to assist people who are trying to change their communities for the better.
1. Working with community partnerships, grantmakers and governmental agencies should develop a social marketing plan to promote involvement in community work.
- The marketing plan should help encourage community members to see working together to solve public problems as an important part of their daily lives.
- The messages should counter the idea that the community can't solve its own problems.
- The plan should focus on encouraging community involvement.
- Messages for different members of the community should be delivered in different ways. For example, messages to teenagers should be delivered differently than messages to older adults.
- The plan should include a way to communicate the good things going on. Success stories and profiles of people who have done meaningful work should be shared with the community.
- The social marketing campaign should use different methods of communication to reach the greatest number of people. For example, it might use posters, online messages, and editorials in the local newspaper, to give just a few examples.
2. Develop partnerships where people can work together to improve their community.
- Grant funds should be directed toward broad community partnerships. By having a broad partnership, the community will have a structure that is strong enough to make a real impact on different community problems.
- Partnerships should involve both people with decision-making power and those most affected by the issue.
- Many different ways in which people can be a part of the partnership should be provided.
- Grantmakers should try to invest in the same place and permit work across the normal boundaries. For example, it's often the case that one group in the community will receive a grant to prevent substance use, another will receive a grant to improve education, and so on. We suggest grantmakers work together to offer larger grants to community partnerships that can work on several of these interrelated issues at the same time.
3. Provide information to help focus efforts on issues with the greatest effect on community health and development.
- Collaborative partnerships should develop objectives based on two things: the level of community problems (i.e., the statistics) and what members of the community find important.
- Support organizations should develop a model of change (such as the one outlined in this section) to help guide community work.
4. Support action planning to improve the community.
- Planning should begin early and never stop. Annual action planning retreats can renew the group's efforts and be supplemented by regular adjustments.
- When something works, its use should be widely promoted. For example, a "bag it" program that allows young people to call in orders for contraceptives and have them discreetly wrapped in a paper bag might increase contraceptive use substantially among young people at increased risk of unintended pregnancy in a small community. If that proves to be the case, that program should be promoted in newsletters and through word of mouth, so that similar organizations can do the same thing. It's important to remember, though, that programs often need to be adapted to fit local conditions.
- The focus of action planning should be on transforming the environment to make behaviors that promote health and development more likely to occur.
- By gathering pertinent information about risk and protective factors, partners in the collaborative effort can better focus their efforts on new programs, policies, or practices that will cause positive changes in the environment.
- Some of the community changes should try to reach the whole community; others should be targeted toward people who are at greater risk.
5. Provide investments in collaborative partnerships that are large enough and last long enough to make a difference.
- Fund community partnerships long enough to make a difference (for example, for 5 to 10 years).
- Provide resources to hire community mobilizers to act as catalysts in the community.
- Many larger system changes your organization will work for can take a long time to occur. Be sure to develop and celebrate "small wins" -- milestones that will regularly reward everyone's efforts. This will help keep spirits up as you work to reach your goals.
- Promote the sustainability of successful community partnerships. Groups that have demonstrated their value should be supported through continuing efforts by funding partners.
6. Use a variety of methods to build capacity for doing community work.
- Offer many opportunities for people involved in community work to meet and learn from each other.
- Use online and distance education to give people the opportunity to learn with others doing similar work in different places.
- Use the web to distribute "how-to" information for developing the core competencies of community work.
- Link newer community partnerships with those that are more experienced, and connect established leaders with newer generations of leadership.
7. Document the process of community and system change to improve community work.
- Leaders of initiatives should work with representatives from support organizations to develop meaningful ways to present and use data on community and system change.
- Honor organizations and individuals that bring about significant changes in their communities.
- Use data on community and system change to make adjustments in the group's action plan.
- Researchers should examine trends in community and system change to identify the factors that might affect community change.
- Use an annual state-of-the-partnership report to encourage accountability of members of community partnerships.
8. Make outcomes matter.
- Establish and report on intermediate and more distant outcomes -- such as high rates of important community and system changes for community-determined goals.
- Make renewal of community investments (for example, the continuation of a grant) conditional on evidence of progress by the group.
- Award bonus grants to encourage progress and outstanding accomplishments.
- Award outcome dividends to reward improvements in the bottom line. For example, if a community has fewer pregnancies among adolescents because of the efforts of a local coalition, give the coalition some of the money saved by the state through reduced related costs, such as hospital expenses and public assistance for adolescent parents and their children.
9. Develop collaborative partnerships to increase the support for people working to improve their communities.
- Develop broad collaborative partnerships among diverse organizations that broadly represent the community. Members of the partnership should share the risks, resources, and responsibilities for community improvement.
- Employers should modify their structures to support involvement in public problem solving. For example, organizations might have a flextime policy that allows employees to volunteer in their community.
- Community partnerships, intermediary and support organizations, and grantmakers and governmental agencies should act as catalysts for change. They can do this by:
- Convening people around health and development concerns;
- Forging relationships among people who can help address community issues; and
- Helping get resources that few communities could access by themselves.
10. Future research should help understand and improve the factors that affect community health and development.
- Examine whether and how reducing poverty and improving education affect community-level indicators of health and development.
- Examine the conditions under which community and system change are associated with improvements in long-term goals.
- Let people know what works -- what are promising practices for building healthier communities. This can be done through a variety of different media, such as print and broadcast media, professional associations, and the web.
In Summary
A healthy community is a form of living democracy: people working together to address what matters to them. As community members, we have a responsibility to help shape the basic conditions that affect our lives. In transforming communities together, we are guided by shared values and principles that bind us in common purpose.
Building healthier communities blends the local and the universal, the particular and broader contexts. Such efforts are grounded locally: the family, the neighborhood, and other familiar communities. To be effective, however, we must also bring diverse groups of people and organizations together to transform the broader conditions that affect local work. This requires courage, doubt, and faith: the courage to trust those outside our immediate experience, the doubt to question what is, and the faith to believe that together, we will make a difference.
The work of building healthier communities takes time: our time, that of our children, and that of our children's children. A Jewish proverb counsels: "You are not bound to finish the work, but neither are you free to give it up." In our emerging ties across place and time, we join others in an attempt to create environments worthy of all our children.
Contributor
Stephen B. Fawcett
Resources
Online Resources
Building Healthy Communities (article*)
Building Multisectoral Partnerships for Population Health and Health Equity (article*)
Emerging Action Principles for Designing and Planning Community Change is from Community Science and shares what science and practice have taught us about strengthening community.
A Framework for Community Mobilization to Promote Healthy Youth Development (article*)
The Future of the Public's Health in the 21st Century from the Institute of Medicine (US) Committee on Assuring the Health of the Public in the 21st Century. Washington (DC): National Academies Press (US); 2002.
An Introduction to Policy, Systems, and Environmental (PSE) Change is an article from Community Commons that explains how PSE change strategies aim to make healthier choices more practical and accessible for all community members by transforming the environments where people live, work, worship, learn, and play.
The Journey of Changing Systems by Co-Impact is an interactive learning platform designed to guide organizations through the complex process of systems change.
The Lead Local organization focuses on building community power to drive structural changes and promote health equity, providing research, resources, and practical strategies to support communities in transforming local systems and conditions. Their Leading Locally: A Community Power-Building Approach to Structural Change report (pdf) explores how community power-building efforts across 16 diverse places in the United States can drive structural changes to advance equity, emphasizing strategies like grassroots organizing, policy advocacy, and coalition building to transform local conditions and systems. Their Story of Place: Community Power and Healthy Communities report (pdf) discusses how building community power can transform systems to advance health equity, emphasizing the role of local context, structural reforms, and inclusive decision-making to shape healthier communities.
The Power of Collaborative Solutions - Six Principles and Effective Tools for Building Healthy Communities, by Tom Wolff
The Water of Systems Change, created by FSG, helps organizations and funders look closely at the underlying issues that keep social problems in place. This framework supports changemakers as they work to improve systems both inside and outside their organizations, aiming to create greater equity and impact.
Why Community Power is Fundamental to Advancing Racial and Health Equity is the first commentary in a three-part series from Lead Local that explores how community power building can drive health and racial equity more effectively than traditional engagement. It details practical examples of power-building campaigns and emphasizes the crucial role of external actors (e.g. researchers) in supporting these movements.
Why the future belongs to community research is a video from TedX Talks, featuring Ronald Harvey. In his speech, he describes the role of community psychology in treating addiction.
Work Group on Health Promotion and Community Development. (March, 1998). Community Tool Box, Chapter 8: Developing a Strategic Plan
* For more publications from the Center for Community Health and Development, please visit our Publications page.
Print Resources
This Community Tool Box section is an edited version of the following invited paper (and book chapter):
Fawcett, S. B., Francisco, V. T., Hyra, S., Paine-Andrews, A., Schultz, J., Russos, S., Fisher, J., & Evensen, P. (1998). Building Healthy Communities. Invited Address to the Kansas Conference on Health and Its Determinants. Sponsored by the Kansas Health Institute and the Kansas Health Foundation. Wichita, KS.
To appear in:
Tarlov, A., & Peter R. St. (Eds.) Society and Population Health. New York, NY: New Press.
The references cited in the above paper are as follows:
References:
Aguirre, M. (1996). Community-based approaches for the prevention of alcohol,tobacco, and other drug use. Annual Review of Public Health, 17, 337-358.
Altman, D., Balcazar, F., Fawcett, S., Seekins, T., & Young, J. (1994). Public health advocacy: Creating community change to improve health. Palo Alto, CA: Stanford Center for Research in Disease Prevention.
Tarlov, A., & Peter, R. St. (Eds.) Society and Population Health. New York, NY: New Press.
Barker, R. (1968). Ecological psychology. Stanford, CA: Stanford University Press.
Bernstein, J., & Michel, L. (1997). Has income inequality stopped growing? Monthly Labor Review, 120 (12), 3-16.
Brofenbrenner, U., McClelland, P., Wethington, E., Moen, P., & Ceci, S. J. (1996). The state of Americans: This generation and the next. New York, NY: The Free Press.
Carroll, J. (1997). Neighborhoods and citizenship. Lecture at the Boston Public Library, Boston, Massachusetts. Broadcast by C-SPAN television network. November 15, 1997.
Citrin, T. (1998). Topics for our times: Public health--community or commodity? Reflections on Healthy Communities. American Journal of Public Health, 88(3), 351-352.
Fawcett, S. B., Francisco, V. T., Hyra, D. S., Paine-Andrews, A., Schultz, J. A ., Russos, S., Fisher, J.L., & Evensen, P. (1998). Building Healthy Communities. Invited Address to the Kansas Conference on Health and Its Determinants. Sponsored by the Kansas Health Institute and the Kansas Health Foundation. Wichita, KS.
Fawcett, S.(1991). Some values guiding community research and action. Journal of Applied Behavior Analysis, 24, 621-636.
Fawcett, S. (1999). Some lessons on community organization and change. In Rothman, J. (Ed.), Reflections on community organization: Enduring themes and critical issues. (pp. 314-334). Itasca, IL:F.E. Peacock Publishers.
Fawcett, S., Paine, A., Francisco, V., Schultz, J., Richter, K ., Lewis, R., Williams, E., Harris, K., Berkley, J., Fisher, J., & Lopez, C. (1995 ). Using empowerment theory to support community initiatives for health and development. American Journal of Community Psychology, 23(5), 667-697.
Fawcett, S., Lewis, R., Paine, A., Francisco, V., Richter, K., Williams, E. , & Copple, B. (1997). Evaluating community coalitions for the prevention of substance abuse: The case of Project Freedom. Health Education and Behavior, 24(6), 812-828.
Fawcett, S., Paine, A., Francisco, V., Schultz, J., Richter, K., Berkley, J., Fisher, J., Lewis, R., Lopez, C., Russos, S., Williams, E., Harris, K., & Evenson, P. Evaluating community initiatives for health and development. In I. Rootman, McQueen, D. etal. (Eds.) Evaluating health promotion approaches. Copenhagen, Denmark: Work Health Organization-- Europe.
Feinstein, J. (1993). The relationship between socioeconomic status and health: A review of the literature. Milbank Quarterly, 71, 279-322.
Francisco, V., Paine, A., & Fawcett, S. (1993). A methodology for monitoring and evaluating community coalitions. Health Education Research: Theory and Practice, 8(3), 403-416.
Fukuyama, F. (1995). Trust: The social virtues and the creation of prosperity. New York, NY: The Free Press.
Goodman, R., Speers, M., McLeroy, K., Fawcett, S., Kegler, M., Parker, E., Smith, S., Sterling, T., & Wallerstein, N. (1998). An initial attempt at identifying and defining the dimensions of community capacity to provide a basis for measurement. Health Education and Behavior.
Green, L., & Kreuter, M. (1991). Health promotion planning: An educational and environmental approach, 2nd ed. Mountain View, CA: Mayfield.
Hawkins, D. & Catalano, R. (1992). Communities that care. San Francisco, CA: Jossey-Bass.
Herrnstein, R., & Murray, C. (1994). The bell curve: Intelligence and class in American life. New York, NY: Free Press.
Himmelman, A.T. (1992). Communities working collaboratively for a change. (Monograph available from the author, 1406 West Lake, Suite 209, Minneapolis, MN 55408).
Institute of Medicine. (1988). The future of public health. Washington, D.C.: National Academy Press.
Institute of Medicine. (1997). Committee on Using Performance Monitoring to Improve Community Health: Durch, J., Bailey, L., & Stoto, M. (Eds). Improving health in the community: A role for performance monitoring. Washington, DC: National Academy Press.
Kaplan, G., Pamuk, E., Lynch, J., Cohen, R., & Balfour, J. (1996). Income inequality and mortality in the United States. British Medical Journal, 312, 999-1003.
Kawachi, I., Kennedy, B., Lochner, K., & Prothrow-Stith, D. (1997). Social capital, income inequality, and mortality. American Journal of Public Health, 87(9), 1484-1490.
Kehrer, B., & Wolin, C. (1979). Impact of income maintenance on low birthweight: Evidence from the Gary experiment. Journal of Human Resources, 14 , 435-462.
Kretzman, J., & McKnight, J. (1993). Building communities from the inside out: A path toward finding and mobilizing a community's assets. Chicago: ACTA Publications.
Lappe, F., & DuBois, P. (1994). The quickening of America: Rebuilding our nation, remaking our lives. San Francisco, CA: Jossey-Bass.
Marmot, M., Smith, G., Stansfield, S., Patel, C., North, F., Head, J., White, I., Brunner, E., & Feeney, A. (1991). Health inequality among British civil servants: The Whitehall II study. The Lancet, 337 (8), 1387-1393.
Orfield, M. (1997). Metropolitics: A regional agenda for community and stability. Washington, DC: Brookings Institution Press.
Paine, A., Vincent, M. , Fawcett, S., Campuzano, M., Harris, K., Lewis, R., Williams, E., & Fisher, J. (1996). Replicating a community-based initiative for the prevention of adolescent pregnancy: From South Carolina to Kansas. Family and Community Health, 19(1), 14-30.
Putnam, R. (1995). Bowling alone: America's declining social capital. Journal of Democracy, 6(1), 64-78.
Putnam, R. (1993). Making democracy work. Princeton, NJ: Princeton University Press.
Raudenbusch, S. (1997). Toward a science of ecological assessment: A model for the systematic social observation of neighborhoods. Unpublished paper presented at the annual meeting of the American Society of Criminology, San Diego, November, 1997.
Rothman, J. (Ed.) (1999). Reflections on community organization: Enduring themes and critical issues. Itasca, IL: F.E. Peacock Publishers.
Ryan, W. (1971). Blaming the victim. New York, NY: Vintage Books.
Schorr, L. (1997). Common purpose: Strengthening families and neighborhoods to rebuild America. New York, NY: Anchor Books, Doubleday.
Sclove, R. (1995). Democracy and technology. New York, NY: Guilford Press.
Walzer, M. (1998). Pluralism and social democracy. Dissent, Winter issue, 47-53.
World Health Organization. (1987). Ottawa charter for health promotion. Health Promotion, 1-4, iii-v.
Wilson, W. (1996). When work disappears: The world of the new urban poor. New York, NY: Knopf.
Wilkinson, R. (1996). Unhealthy societies: The afflictions of inequality. London, England: Routledge.
Yin, R. (1988). Case study research: Design and methods. Newbury Park, CA: Sage.
___You understand what constitutes a community.
___You understand what a collaborative partnership is and how powerful it can be.
___You know what community capacity is.
___You know that the key partners in a broad collaboration should include:
- Local members of community partnerships
- Support organizations
- Grantmakers and governmental agencies
___You understand the context in which people in the community act.
___You have decided to move forward with collaborative planning in order to bring people and organizations with different experiences and resources together.
___A mission statement that tells what your organization is going to do and why has been established.
___Through action planning, specific changes in the community have been identified and related action steps have been taken to bring them about.
___A strong leader for the organization is in place.
___You have community mobilizers who have started the ball rolling on actions that your group has decided to take.
___The groups efforts and results have been documented to know whether a difference is being made.
___You understand the ten recommendations for promoting community health and development.
Contributor
Phil Rabinowitz
Example 1: Healthy Communities: A Parable of Two Paths
In the early 1920's, the people of Prairie Center and Sunflower enjoyed a rich community life. There were strong ties among neighbors. People supported each other in many informal ways; through churches, in conversations at the local cafe, and on front porches. Adults cared for each other's children. When Billy or Maria did something wrong, their parents were sure to hear about it. People trusted each other to look out for them.
Gradually life changed in the two communities. Growth from nearby urban areas added people with limited ties to the community. Local zoning laws and regional planning separated the places where people worked from where they lived. Roads now cut through established neighborhoods, making it necessary to take the car to places people used to walk.
Individuals and families made new choices about how to use their time. Rather than visit neighbors, people stayed at home and watched television. Increasingly, both adults worked outside the home; often at several low-paying jobs to meet family needs. As a result, there were fewer adults to watch what kids were doing. All these individual choices and constraints added up: community folks had less contact with their neighbors, with their children, and with each other's children.
In Prairie Center, things changed gradually -- and so did the way local people addressed their problems. As drug use and violence increased in the 1980's and 1990's, the local media blamed on youth and their parents. Following advice from outside experts, the county jail was expanded at considerable cost. This left less public money for education and health. Those who could afford it sent their children to private schools. Those who could went out of town for health care. Poor people suffered the most; sharp cuts in public assistance could not be made up by local churches and charities.
People still cared deeply about their own children and family, but the sense was that each person and family should take care of themselves. Many people were increasingly distrustful of "them." "Them" was understood to mean everyone outside the family.
The people of Sunflower took a different approach. A tragedy in the late 1980's -- the deaths of two children in a drug-related incident really got people's attention. They began a process of community renewal. They started a dialogue about what really mattered in the community, and about what values they shared. They identified a common purpose: to create a caring place for all of the community's children.
The people of Sunflower began to work together in new ways. They formed action teams that cut across the usual boundaries. They included both the powerful and those people, such as youth and low-income families, who were seen by some as the problem. Now a diverse group of citizens, public officials, clergy, service providers, and business people joined hands. They worked to transform schools, businesses, health and service organizations, the faith community, and other valued assets. They established benchmarks for success:
- All kids succeeding in school
- Less drug and alcohol use
- Fewer teen pregnancies
- Fewer children living in poverty
- Adults employed in decent jobs
They coordinated all of their efforts in what they called the "Sunflower Partnership."
Gradually, people started to notice a difference with the unfolding of community changes, both large and small, in Sunflower. Several major businesses allowed flextime for their employees so they could help children. The school district expanded the hours of neighborhood schools, creating safe places for children after school. The faith community collected donations to care for others. City government officials approved new guidelines for tax abatements that rewarded businesses for creating better paying jobs for the unemployed and working poor.
Taken together, all of these changes improved community life. Gradually, the differences could be seen. They also produced results: kids did better in school, fewer kids got in trouble, the neighborhoods were safer, and children and adults were more successful. There was more to be done, of course, but people could see that they were making progress.
Contributor
Stephen B. Fawcett
Tool 1: Principles, assumptions, and values that guide the work of building healthy communities
- Community health improvement involves the population as a whole, not merely individuals at risk for specific physical, mental, or social conditions.
- Community health requires changes in both the behaviors of large numbers of individuals and the conditions or social determinants that affect health and development.
- A healthy community is a local product with priority issues and strategies best determined by those most affected by the concern.
- Freedom and justice require reducing income disparities to promote optimal health and development for all.
- Since health and development outcomes are caused by multiple factors, single interventions are likely to be insufficient.
- The conditions that affect a particular health or development concern are often interconnected with those affecting other concerns.
- Since the behaviors that affect health and development occur among a variety of people in an array of contexts, community improvement requires engagement of diverse groups through different parts of the community.
- Statewide and community partnerships, support organizations, and grantmakers are catalysts for change: they attempt to convene important parties, broker relationships, and leverage needed resources.
- The aim of support organizations is to build capacity to address what matters to people over time and across concerns.
- Community health and development involves interdependent relationships among multiple parties in which none can function fully without the cooperation of others.
Tool 2: Using this model of change--"Building capacity for community change"
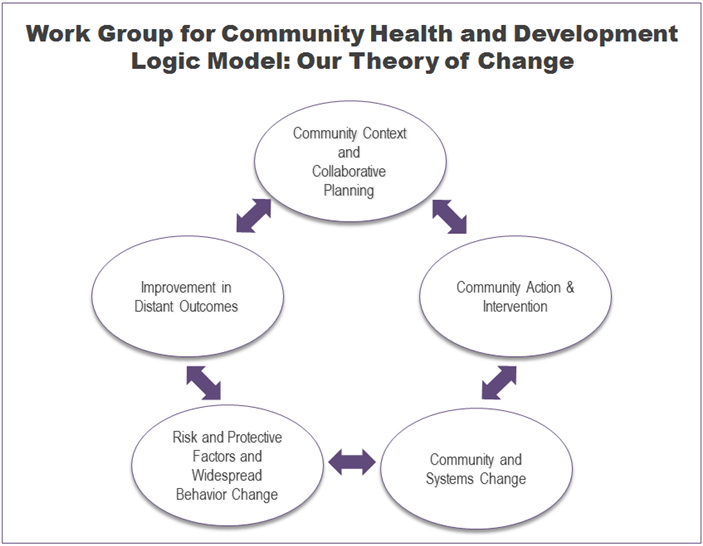
1. Community Context and Planning
The first step in the process is understanding the context in which people act. By the context, we mean people's experiences, their dreams for a better life, and what makes them do what they do.
With an understanding of the context, the group can move forward with planning. Collaborative planning is a critical and ongoing task of a successful organization. It brings together people and organizations with different experiences and resources. Together, they clarify or develop the group's vision, mission, objectives, strategies, and action steps. In doing so, they can bring about changes in the community.
2. Community Action and Intervention
The planning process should be followed by action--going out and doing what was outlined. Sometimes, there is serious resistance to efforts that will need to be overcome.
3. Community and System Change
The goal of planning and action is to bring about community and system changes. Bringing about these changes is an important step towards achieving your organizational goals. By community change, we mean developing a new program (or modifying and existing one), bringing about a change in policy, or adjusting a practice related to the group's mission. system changes are similar to community changes, but take place on a broader level.
4. Risk and Protective Factors and Widespread Behavior Change
Our belief is that when these community and system changes occur, they should, taken together, change the environment in which a person behaves. This is sometimes referred to as increasing protective factors and/or decreasing the risk factors that community members face.
Risk and protective factors are aspects of a person's environment or personal features that make it more likely (risk factors) or less likely (protective factors) that she will develop a given problem. Often, risk and protective factors can be considered flip sides of the same coin. The intended effect of environmental change is widespread behavior change.
5. Improve More Distant Outcomes
Improvements in more distant outcomes, such as reducing violence or increasing employment rates and family incomes, are the ultimate goals of collaborative partnerships. By reducing the risk factors (and enhancing the protective factors) for the issue you are trying to address, you will affect the bottom line. Data on community-level indicators can help you determine just how much progress you have made towards your ultimate goals.
Contributor
Stephen B. Fawcett
File Upload

Throughout the world, people and organizations come together to address issues that matter to them. For example, some community partnerships have formed to reduce substance use disorders, pregnancies among adolescents, or violence. Other community-based efforts attempt to lower risks for HIV, cardiovascular diseases, or injuries. Alliances among community members have also focused on promoting urban economic development, access to decent housing, and quality education.
These initiatives try to improve the quality of life for everyone in a community. Often, they do this in two ways. Initiatives use universal approaches -- that is, they try to reach everyone who could possibly be affected by the concern. They also use targeted approaches, which try to affect conditions for people who are at greater risk for the problem. Through these two approaches, initiatives try to change people's behavior, such as using illicit drugs, being physically active, or caring for children. They also might go deeper and try to change the conditions, such as the availability of drugs or access to childcare, under which these behaviors occur.
Community health promotion is a process that includes many things at many levels. For example, efforts use multiple strategies, such as providing information about the problem or improving people's access to assistance. They also operate at multiple levels, including individuals, families, and organizations, and through a variety of community sectors, such as schools, businesses, and faith-based organizations. All of this works together to make small but widespread changes in the health of the community. The goal is to promote healthy behaviors by making them easier to do and more likely to meet with positive reinforcement.
There are a lot of different models that describe how to best promote community health and development. Some of the more popular models include the Healthy Cities/Healthy Communities Model, the PRECEDE/PROCEED model, and the Planned Approach to Community Health [PATCH]. Similarly, our University of Kansas (U.S.A.) Center for Community Health and Development's model of Building Capacity for Community Change is outlined elsewhere. While how things should be done differs in each model, the basic goal of these and other community approaches is the same. They aim to increase opportunities for community members to work together to improve their quality of life.
Evaluating the effectiveness of community-based initiatives presents some special challenges. Community initiatives are often evaluated using research methods borrowed from clinical trials and other researcher-controlled techniques. While these methods work very well in the fields for which they were developed, they're not necessarily a "good fit" for evaluating community work. It's like trying to put a square peg into a round hole -- with a lot of work, you might be able to do it, but it will never be as smooth as you want.
Ideas about community evaluation have their roots in several different models and traditions. These include:
- Action anthropology, which refers to the use of research to support community empowerment and self-determination.
- Qualitative research, which highlights the value of experience and context as important parts of understanding an effort. That is, it looks at more than statistics alone.
- Community-based participatory research (CBPR), which uses dialogue among community and scientific partners to produce knowledge and guide the actions taken by a group or community.
- Empowerment evaluation, which aims to assess the effort's worth while strengthening the community's desire and ability to understand and improve its own work.
These and other types of research actively involve community members in designing and conducting the evaluation. They all have two primary goals: understanding what is going on, and strengthening communities' ability to address their own concerns. What is different between these methods is the various balances they strike between these two ends.
In this section, we'll look at models, methods, and applications of community evaluation in understanding and improving comprehensive community initiatives. We'll start with a look at some of the reasons why community groups should evaluate their efforts. Then, we'll describe some of the major challenges to evaluation. We'll also describe a model of community initiatives as catalysts for change. Then, we'll discuss some principles, assumptions, and values that guide community evaluation and outline a "logic model" for our KU Center for Community Health and Development's system of evaluation. We'll also make some specific recommendations to practitioners and policymakers about how these issues can be addressed. Finally, we'll end with a discussion examining some of the broad issues and opportunities in community evaluation.
Why evaluate?
There are many good reasons for a community group to evaluate its efforts. When done properly, evaluation can improve efforts to promote health and development at any level -- from a small local nonprofit group to a statewide or even national effort. Evaluation offers the following advantages for groups of almost any size:
- Collecting information about how things are done and the results helps us understand how community initiatives develop, offering lessons other groups can benefit from.
- Providing ongoing feedback can improve community work by encouraging continuous adjustments of programs, policies, and other interventions.
- By involving community members, people whose perspectives have been underrepresented may gain greater opportunities to understand and improve local efforts.
- Finally, evaluation can help hold groups accountable to the community and to the grantmakers who provide funding. It can also help hold grantmakers accountable to the communities that they serve.
Challenges to community participatory evaluation
Although there are a lot of advantages to evaluating community efforts, that doesn't mean it's an easy thing to do. There are some serious challenges that make it difficult to do a meaningful evaluation of community work. They are:
- The causes of many community problems, such as substance use or violence, aren't fully understood. Without a better understanding of the causes, it's hard to decide what needs to be done and whether the work has been successful.
- Some of the more important things to evaluate, such as the ability of the group to successfully accomplish its goals or the quality of life of community members, can be very difficult to measure.
- Community initiatives are very complex. They include doing many things at multiple levels with many different people. Because of this, it can be daunting to describe what's been done thoroughly enough for another community to try to do the same thing.
- For some community issues, such as child maltreatment or domestic violence, it can be difficult to develop valid ways to determine whether efforts are working. Because of this, evaluating effectiveness can be challenging.
- For many issues, it takes a long time to move the bottom line. For example, if a group is trying to reduce HIV in the community, they may not know whether they have affected the number of new infections for years. Therefore, it's necessary to identify markers along the path -- measures of intermediate outcomes, such as changes in the community or system, which give community members an idea of whether or not they are going in the right direction.
- It's very hard to estimate how strong a community-driven intervention is -- will it make a large impact, or just a ripple? Evaluators will need to collect precise information on what happened, who it happened to, and for how long the intervention occurred.
- Information collected on individuals can't always be generalized to reach a conclusion about the community as a whole.
- Because there aren't always suitable experimental designs or fitting comparisons -- for example, it's hard to say that two towns are exactly alike -- it is not always possible to say that the results were really because of the community initiative and not because of something else that was going on.
- Because community initiatives change with time and circumstances, what they do gets modified as well. Since they are adaptable and constantly changing, it can be difficult to assess the generality of effects and decide whether a given program works broadly or worked in one particular circumstance.
- People see things differently. Evaluators, especially those in the field of participatory evaluation, must be attentive to differing perspectives when interviewing different people about the same event.
- To evaluate a community initiative fully and well takes a lot of time and work. For an already overburdened organization, it may not be feasible to do all of this properly.
- As we discussed above, there are two primary goals of evaluation: understanding what is going on and strengthening communities' ability to address their own concerns. It can be very difficult to attain both of these goals at the same time. Often, one may seem to take priority over the other.
Despite the challenges that evaluation poses, our belief is that it is a very worthwhile pursuit. In order to minimize these challenges, the KU Center for Community Health and Development has developed a model and some principles that may provide guidance for people trying to evaluate the work done in their community.
A model: Community initiatives as catalysts for change
Although different community groups have different missions, many of them use the same logic model or framework: that of a community initiative as a catalyst for change. This type of community initiative tries to transform specific parts of the community. They change programs, policies, and practices to make healthy behaviors more likely for large numbers of people.
Below, we offer a model of what occurs in a comprehensive community initiative and its results.
- Supporting collaborative planning
- Documenting community implementation, action, and change
- Assessing community adaptation, institutionalization, and capacity
- Evaluating more distal outcomes
- Promoting dissemination
This model is nonlinear -- that is, community partnerships don't just do one thing at a time. Instead, they take part in many interrelated activities that occur simultaneously. A new initiative to reduce the risks for violence involving young people, for example, may be refining its action plan while pursuing relatively easy changes in the community, such as posting billboards that warn people about the consequences of gang-related violence.
The components of the model are also interrelated -- that is, they can't be taken separately. They are all part of the same puzzle. For example, collaborative planning should decide what needs to happen in the community. That, in turn, should guide community action and change. Important community actions may be adapted to fit local conditions, and then kept going through policy changes, public funding, or other means of institutionalization.
Also important in this model is the idea that success breeds success. If a community is able to successfully bring about changes, its capacity to create even more community changes related to the group's mission should improve. This, in turn, may affect more distal outcomes -- the long-term goals the group is working for. Finally, successful comprehensive initiatives or their components (e.g., public awareness efforts, programs, or policies) may be picked up and adapted by other communities addressing similar concerns.
The goals and expectations of community initiatives vary. A community may have a single, narrowly defined mission, such as increasing children's immunizations against disease. It may also have much broader goals that involve several different objectives. For example, members of an initiative may wish to work on two problems, such as reducing child maltreatment and domestic violence, which share common risk and protective factors.
Some communities have a relatively free hand in deciding what to do. Other partnerships may be required by grantmakers to use well-established strategies or interventions. Some initiatives try hybrid approaches that combine the use of these established methods with the role of a catalyst. They do this by implementing core components, such as sexuality education and peer support for preventing pregnancies among adolescents, along with developing new community changes, such as enhancing access to contraceptives, that are related to the group's desired outcomes.
Different initiatives will modify programs to make them work well in their community. For example, different groups might want to develop supervised alternative activities for young people to make their participation in risky behavior, such as unprotected sexual activity or substance use, less likely. However, different communities may start any one of a variety of interventions, such as expanding recreational opportunities, offering summer jobs, or developing community gardens.
Adapting interventions to fit community needs has several advantages. First of all, it creates an approach that "belongs" to community members -- it's something they are proud of, that they feel they created -- it's really theirs. Second, because it has been modified to fit the community's needs, the program or policy is more likely to remain in existence. Finally, through changing interventions to fit local needs, community members improve their ability to address their own concerns.
If a comprehensive community initiative (or a program or policy that is part of it) proves to be successful over a long period, it may be used as an example that other communities can follow. For example, comprehensive interventions for reducing risks for cardiovascular diseases, or specific parts of the intervention such as increasing access to lower-fat foods, might be held up as examples for other groups. Leaders of nonprofit organizations need to know what works, what makes it work, and what doesn't work. That way, local efforts can learn from other community-based projects and demonstrations, and adopt some of what experience and research suggest are the "best practices" in the field.
Principles, assumptions, and values of community evaluation
When we look at the process of supporting and evaluating community initiatives, we need to look at what our ideas are based on. The following principles, assumptions, and values serve as the foundation for these processes. You'll notice that they reflect the challenges of addressing both of the major aims of evaluation: understanding community initiatives while strengthening the community's ability to address its concerns.
Principles, Assumptions, and Values of Community Evaluation
Community initiatives often function as catalysts for change in which community members and organizations work together to improve the quality of life.
Community initiatives are complex and ever-changing, and they must be analyzed on multiple levels.
Community initiatives help launch interventions that are planned and implemented by community members.
Community evaluation must understand and reflect the issue, and the context in which it is happening.
Community evaluation should involve people from throughout the community.
Community evaluation information should be linked to questions of importance to key stakeholders.
Community evaluation should strengthen community members' ability to understand what's going on, improve practices, and increase self-determination.
Community evaluation should begin early and be ongoing.
Community evaluation results, if positive, should be used to help sustain and promote widespread adoption of the community initiative and/or its components.
Community evaluation should be coupled with technical assistance to provide comprehensive support.
Community initiatives engage community members and organizations as catalysts for change: they transform community conditions to improve quality of life. Community evaluation is based on the premise that community initiatives are very complex. To be effective, they need many levels of intervention. Researchers try to understand the issue, the history of the initiative, and the community in which it operates. Ideally, local initiatives are planned and implemented with the involvement of many community members, including those from diverse backgrounds. Because of this, community evaluation is a participatory process involving a lot of collaboration and negotiation among many different people.
Evaluation should take place from the beginning of an initiative. That way, it can offer ongoing information and feedback to better understand and improve the initiative. Evaluation priorities -- that is, what to evaluate -- should be based on what's of most importance to community members, grantmakers, and the field.
If done properly, evaluation results should actually help sustain and renew the community initiative. The information gathered in evaluation can be used to obtain resources such as grant money, show how to improve, and offer an opportunity to celebrate accomplishments. If the initiative seems to be effective, information from community evaluation can be used to promote its widespread adoption. Finally, evaluation should be coupled with technical assistance to provide a complete support system for the initiative. Evaluation without support can actually hurt the initiative. It can be seen as criticism, and leave members of the group frustrated and unsure of what to do next.
Logic model for community evaluation
The figure below describes the logic model for the KU Center for Community Health and Development's Community Evaluation System. A logic model is simply a way of thinking about something in a rational order -- one thought naturally follows another, and you build on ideas as you go. It has its roots in the catalyst model we described above, and tries to show the ideal situation -- what might occur in a fully implemented community evaluation.
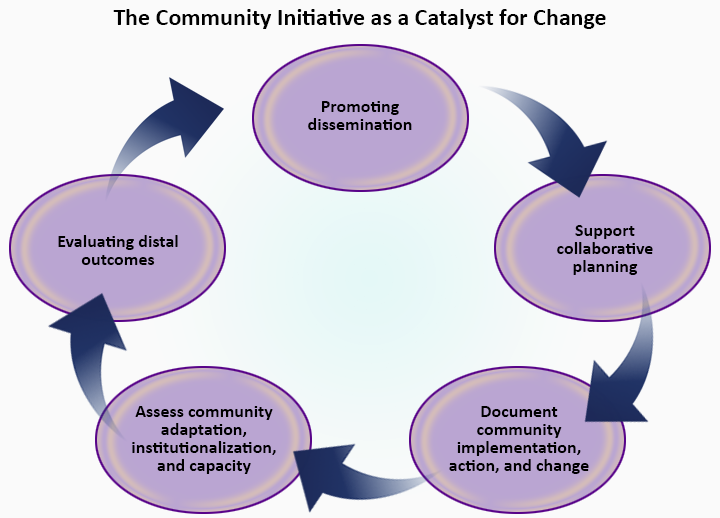
Initiative phases and evaluation activities
Our ideas about evaluation and support for community initiatives are based on the model of community initiatives as catalysts for change we described earlier. The five parts are:
- Supporting collaborative planning
- Documenting community implementation, action, and change
- Assessing community adaptation, institutionalization, and capacity
- Evaluating more distal outcomes
- Promoting dissemination
Supporting collaborative planning
Agenda setting -- that is, deciding what issues and options should be acted upon -- is one of the most important things a community initiative can do. Agendas shape the choice of which issues should be addressed. The topics for the agenda might be decided on by using assessment tools, such as gathering information about community concerns. Media advocacy -- understanding how to use the media to effectively get the word out -- may also assist agenda-building efforts.
Supporting collaborative planning, when done comprehensively, will include all of the following:
- Involving many people in planning efforts, including those from diverse backgrounds
- Clarifying the group's vision, mission, objectives, and strategies
- Developing an action plan that identifies specific community changes to be sought (and later documented) throughout the community
- Identifying local concerns and gathering information about them
- Identifying local resources that can help solve the problem
Documenting community implementation, action, and change
Community evaluation documents what gets done by community initiatives, and lets all of the members of the initiative know about these changes. That way, community members can improve on what they have done. This includes documentation of:
- Local efforts and accomplishments
- Community and system changes: changes in programs, policies, and practices that are related to the mission
- How things got done
- How many changes occurred in the community and where they happened (this is also known as intermediate outcomes)
Assessing community adaptation, institutionalization, and capacity
Community evaluators also look at how the interventions get changed, and whether or not these adjustments to fit the community actually work. They also determine if efforts to sustain the initiative are effective. Finally, evaluators try to measure whether efforts to improve the community's capacity to address current and future issues have been effective.
Evaluating more distal outcomes
Of course, the ultimate goal of most community initiatives is to move the bottom line -- to have fewer people acquire HIV or experience violence, to give two examples. To see if this has happened, community evaluators use quantitative methods. One such method is the use of behavioral surveys. For example, a project to prevent pregnancies among adolescents might survey students about reported abstinence or unprotected sexual activity. Another quantitative method is finding archival records of outcomes. For example, the project above might use estimated rates of pregnancies among adolescents from the health department.
They also use qualitative methods, such as interviews with participants, to better understand the meaning and value of efforts. Used together, quantitative and qualitative information weave a rich tapestry of understanding around the initiative's efforts, and offer a solid understanding of the community-level outcomes. They are much more powerful together than either could be alone.
Unfortunately, it usually takes so long to see if the initiative has really moved the bottom line that this information isn't useful for making the day-to-day improvements initiatives need. This is why we recommend documenting intermediate outcomes such as changes in the community or broader system. Measuring community changes -- new or modified programs, policies, or practices -- assists in detecting patterns to see if the initiative is helping to create a healthier environment.
Promoting dissemination
Finally, evaluators help community initiatives spread the word about effectiveness to important audiences, such as community boards and grantmakers. Evaluators help provide and interpret data about what works, what makes it work, and what doesn't work. Ways to get the word out may include presentations, professional articles, workshops and training, handbooks, media reports, and online communication.
So, how does all of this work together? To give a quick recap:
Identifying local concerns helps communities decide on and develop strategies and tactics. These, in turn, may guide implementation of interventions, actions, and changes. Important parts may be adapted to work better in the local community, and important changes may be sustained. This should improve the community's ability to address current and future issues. It may also help attain the initiative's long-term goals, and at the same time improve researchers' understanding of how to get things done. This may help promote adoption of the entire initiative or its more effective components by other communities. All of these steps may influence each other and help decide what the community will do next.
Recommendations for practitioners and policymakers
Research and experience in the field provide us with recommendations for community evaluation. These 34 specific recommendations are grouped into categories that follow the five phases of the catalyst and logic models:
- Supporting collaborative planning
- Documenting community implementation, action, and change
- Assessing community adaptation, institutionalization, and capacity
- Evaluating more distal outcomes
- Promoting dissemination
These recommendations are directed to a wide audience that includes both practitioners, especially members of community initiatives, and policymakers, including elected and appointed officials and grantmakers.
Recommendations for Supporting Collaborative Planning
- Policymakers should support, and practitioners assist, community members in identifying local concerns and collecting information that documents these problems.
- Policymakers should support, and practitioners assist, community members in strategic planning. This includes identifying a vision and developing a mission, objectives, strategies, and action steps.
- Practitioners should develop and share information regarding factors that put people at risk for, or protect them against, local concerns.
- Practitioners should use community members' knowledge of what's going on and build on this understanding by assisting with the interpretation and analysis of available information.
- Practitioners and policymakers should involve community members in developing an evaluation plan for the initiative.
- Practitioners should develop a "give and take" relationship with members of community initiatives. That is, they can provide technical assistance and resources for the initiative, and in turn ask for information and data.
- Information should be shared among practitioners, community members, and other key stakeholders.
Recommendations for Documenting and Supporting Community Implementation, Action, and Change
- Practitioners and policymakers should help community members choose interventions and prioritize goals using local and expert knowledge of what is important and what is feasible.
- Practitioners and policymakers should encourage community initiatives to be a catalyst for change. They should focus their efforts on transforming the environment (i.e., by changing programs, policies, and practices), rather than focusing only on individual behavior.
- Practitioners should highlight the products of planning, such as forming committees or completing grant applications, rather than focusing only on the process it took to do it (e.g., how much time was spent or the number of meetings that took place).
- Practitioners should provide technical support and constructive feedback to help the initiative understand and do what works in their community.
- Practitioners should evaluate progress made in moving the "bottom line," or indicators of population-level outcomes.
- Practitioners should also evaluate and share information about the process with community members. For example, they might look at and explain the amount of media coverage, number of community members and organizations participating, resources generated, and services provided.
- Policymakers should request, and practitioners provide, a way to measure changes in the community, such as knowing how many new or modified programs, policies, or practices the group has brought about. These data on community and system change will help show how the environment is changing to improve community health and development.
Recommendations for Assessing and Supporting Community Adaptations, Institutionalization, and Capacity
- Policymakers should allow, and practitioners support, the reinvention or adaptation of interventions to be more effective in the local community.
- Practitioners should collect information on what happens and what makes it happen to see if the group's work is effective.
- Policymakers should encourage community groups to look at things over the long haul. This means helping with long-range planning, providing training, and gradually reducing funding over time. For example, a grant may give the most money in the first year, less money in year two, and even less in year three. This might allow the initiative to have the initial support it needs and then prompt the group to look for more sustainable funding. All of this should help to promote the institutionalization of the initiative.
- Practitioners should conduct periodic assessments to see how many of the group's community or system changes have been sustained. This helps determine the level of institutionalization of the initiative.
- Practitioners should collect information on rates of community change over time and across concerns -- that is, changes that occurred in the community for different missions, such as substance use and child maltreatment. High rates of change over time and across different areas of local concern provide an indication of "community capacity."
- Practitioners should collect and share information on community members who become "community champions" -- that is, who do great things for the initiative and the community as a whole.
- Policymakers should request, and practitioners should provide, regular reports on what's happening.
- Practitioners should provide feedback on how and where community changes have occurred to help understand and improve efforts to address community issues.
- Policymakers should provide grant funding that improves the ability of a diverse team of leaders to successfully carry out the initiative. For example, they might provide training on grant writing or leadership development.
Recommendations for Evaluating and Influencing More Distal Outcomes
- Practitioners should record what people report has happened related to risk and protective factors and compare this information with relevant statistical evidence about behavior and population-level outcomes.
- Practitioners should study how "health promoting" the environment is and how it changes over time. This may include studying rates of community or system changes and their relationship to changes in the bottom line.
- Practitioners should develop consistent, practical methods for collecting information on relevant behavior and related outcomes in a comparison community. (A comparison community is one similar to that you are studying, but in which no systematic intervention occurs.) For example, if you are conducting a comprehensive initiative in an urban neighborhood, you might use another nearby urban neighborhood as a comparison.
- Policymakers should encourage, and practitioners support, community members and outside experts to evaluate the importance of the initiative's achievements. This can help increase accountability to community members and other stakeholders.
- Practitioners should use qualitative methods to improve understanding of what gets done and how it happens. These methods might include interviews with participants about barriers, resources, and lessons they have learned about the work.
- Policymakers should provide funding that is based on showing positive results. For example, annual renewal of grants might be based on evidence of high rates of community or system change; bonuses could be given for groups that have done outstanding work; and outcome dividends could be provided for those showing improvement in community-level outcomes.
- Practitioners should share information on what has happened, why and how it happened, and the resulting changes in the community. This should be shared early and regularly with a broad cross section of people, including staff, community members, board members, and grantmakers.
- Practitioners should collaborate with initiative members to develop meaningful ways to present evaluation data to key stakeholders.
Recommendations for Promoting Dissemination
- Practitioners, community members, and staff should present data at local, state, national, and international venues to create a larger audience for their efforts.
- Practitioners and policymakers should share information about effective programs and encourage other communities to adopt or adapt them.
- Policymakers and practitioners should use methods such as newspapers, storytelling, and online communication to get the word out about successful interventions, promising practices, and lessons they have learned.
In Summary
Community evaluation offers two overarching benefits. First, it helps us better understand the community initiative, and second, it improves the community's ability to address issues that matter to local people. This evaluation perspective joins the traditional research purpose of determining worth with ideas of empowerment.
In community evaluation, community members, grantmakers, and evaluators work together to pick the best strategies for the community. The specific mix chosen is determined by several things: the issue to be addressed, the interests and needs of those involved, the resources available for the evaluation, and what the initiative is doing. The evaluation is designed very carefully to answer the following: How well does this help us understand and contribute to our ability to improve our community?
For example, an injury prevention initiative might work with the local clinic to assess risk behavior with surveys and determine how many deaths and injuries occurred that were related to violence, motor vehicle crashes, or other causes. Evaluation might be very different for a child welfare initiative, however, which might find it too expensive to observe parents and children interacting or may not be able to afford a behavioral survey. Instead, it might collect information on the number of children living below the poverty level or other measures of children's well-being.
Ideally, community evaluation is an early and central part of the initiative's support system. At the beginning, it helps the group decide on goals and strategies. Later, the evaluation team can document the community's progress toward its goals.
Communities often have a local support system, which might include things such as financial resources or service networks, that help make it possible for the initiative to make a difference in the community. Community evaluation can help communities recognize their own abilities to bring about change, and then to act on that knowledge. The community is in a partnership with the evaluation team, with both working together to understand and improve the initiative.
Communities identify and mobilize existing resources to bring about changes, and members also help document them. By documenting these community or system changes, community evaluation can prompt community members and leadership to discover where change is, and should be, occurring.
When communities are not making things happen, however, the role of the community evaluation team may shift to making the initiative accountable for its actions. When not much happens over a long period, for example, evaluation information can be used to encourage leaders of the initiative to change what's going on. In extreme cases, community initiatives may be encouraged to change the leadership of the initiative. Finally, renewal of funding -- and bonuses and dividends -- can be based on evidence of progress, with intermediate and longer-term outcomes.
Detecting community capacity -- the community's ability to improve things that matter to local people -- is a particularly important challenge for community evaluation. For example, an initiative trying to prevent substance use that causes many important community changes over a long period, and that then really moves the bottom line, might be said to have greater community capacity than a community whose changes didn't stick. If members of the same initiative later take on a new concern such as preventing violence involving young people and do so effectively, we might be further convinced of improved community capacity.
Successful community partnerships develop, adopt, or adapt interventions and promising practices that will work in their community. How interventions are adapted and implemented becomes almost as important for researchers as what happened as a result of the intervention.
Relationships between researchers and communities seem to be changing. This may reflect a shift in traditional modes of research and practice. In the late 1980s, community-based grantmaking emerged as a new, or rediscovered, way to distribute resources. It awards grants to communities to address their concerns themselves instead of relying only on research scientists to design and implement interventions. Earlier researcher-controlled approaches often did not address all of the goals of community initiatives -- improving understanding, capacity, and self-determination. Concerns about these approaches helped bring about the community-based approaches to evaluation discussed in this section.
The community evaluation system described in this chapter gives a framework and a logic model for examining and improving community initiatives. The methods include providing support, documentation, and feedback. We believe that this approach to evaluation can help local people make a positive difference in their communities.
Contributor
Stephen B. Fawcett
Resources
Online Resource
Collie-Akers, V., Fawcett, S., Schultz, J., Carson, V., Cyprus, J., & Pierle, J.E. (2007). Analyzing a community-based coalition's efforts to reduce health disparities and the risk for chronic disease in Kansas City, Missouri. Preventing Chronic Disease.
Are You Ready to Evaluate Your Coalition? (PDF) prompts 15 questions to help the group decide whether your coalition is ready to evaluate itself and its work.
Chapter 10: Empowerment in the "Introduction to Community Psychology" addressed the different levels of empowerment, how to contribute to power redistribution, and ways to take action to make changes in communities.
The Community Schools Evaluation Toolkit is designed to help community schools evaluate their efforts so that they are able to learn from their successes, identify current challenges, and eventually allow them to plan for future efforts.
An Evaluation Toolkit for The Community Mapping Program (PDF) is part of the Place-based Education Evaluation Collaborative (PEEC), a unique partnership of organizations whose aim is to strengthen and deepen the practice and evaluation of place-based education initiatives. Prepared by Program Evaluation and Educational Research Associates.
Print Resources
This section is an edited version of the following article: Evaluating Community Initiatives for Health and Development, by Stephen B. Fawcett, Ph.D., Adrienne Paine-Andrews, Ph.D., Vincent T. Francisco, Ph.D., Jerry Schultz, Ph.D., Kimber P. Richter, M.P.H., Jannette Berkley Patton, M.A., Jacqueline L. Fisher, M.P.H., Rhonda K. Lewis, Ph.D., M.P.H., Christine M. Lopez, Stergios Russos, M.P.H., Ella L. Williams, M.Ed., Kari J. Harris, M.S., and Paul Evensen. In I. Rootman, D. McQueen, et al. (Eds.) (2001). Evaluation in health promotion: principles and perspectives. (Pp. 241-269). Copenhagen, Denmark: World Health Organization - Europe.
Ashton, J., Grey, P., & Barnard, K. (1986). Healthy cities: WHO's new public health initiative. Health Promotion International, I, 55-60.
Baum, F. (1995). Researching public health: Behind the qualitative-quantitative debate. Social Science and Medicine, 55(4), 459-468.
Bracht, N., (Eds.). (1990). Health promotion at the community level. Newbury Park, CA: Sage Publications.
Connell, J., Kabisch, A., Schorr, L., & Weiss, C. (Eds.), (1995). New approaches to evaluating community initiatives. Washington, DC: The Aspen Institute.
Fawcett, S., Paine A., Francisco, F., Schultz, J., Richter, P., Berkley, L., Fisher, J., Lewis, R., Lopez, C., Russos, S., Williams, E., Harris, K., & Evensen. P., Evaluating Community Initiatives for Health and Development. In I. Rootman, et al. (Eds.) (2001). Evaluation in health promotion: principles and perspectives. (Pp. 241-269). Copenhagen, Denmark: World Health Organization - Europe.
Fawcett, S., Boothroyd, R., & Schultz, J. (2004). Understanding and improving the work of community health and development. In J. Burgos and E. Ribes (Eds.), Theory, basic and applied research, and technological applications in behavioral science. Guadalajara, Mexico: Universidad de Guadalajara.
Fawcett, S., Lewis, R., Paine, A., Francisco, V., Richter, K., Williams, E., & Copple, B. (1997). Evaluating community coalitions for the prevention of substance abuse: The case of Project Freedom. Health Education & Behavior, 24 (6), 812-828.
Fawcett, S., Paine, A., Francisco, V., Schultz, J., Richter, K., Lewis, R., Williams, L. Harris, K., Berkley, J., Lopez, C., & Fisher, J.. (1996). Empowering community health initiatives through evaluation. In Fetterman, M., Kafterian, S., & Wandersman, A. (Eds.), Empowerment evaluation: Knowledge and tools for self-assessment & accountability, 161-187. Thousand Oaks, CA: Sage Publications.
Fawcett, S., & Schultz, J. (2008). Using the Community Tool Box's online documentation system to support participatory evaluation of community health initiatives. In M. Minkler and N. Wallerstein (Eds.). Community-based participatory research for health. San Francisco: Jossey-Bass.
Fawcett, S., Schultz, J., Carson, V., Renault, V., & Francisco, V.. (2003). Using Internet-based tools to build capacity for community-based participatory research and other efforts to promote community health and development. In M. Minkiler and n. Wallerstein (Eds.), Community-based participatory research for health. (Pp. 155-178). San Francisco: Jossey-Bass.
Fawcett, S., Sterling, T., Paine, A., Harris, K., Francisco, V.., Richter, K., Lewis, R., & Schmid, T. (1995). Evaluating community efforts to prevent cardiovascular diseases. Atlanta, GA: Centers for Disease Control and Prevention, National Center for Chronic Disease Prevention and Health Promotion.
Fawcett, S., Suarez, Y., Balcazar, F., White, G., Paine, A., Blanchard, K., & Embree, M. (1994). Conducting intervention research: The design and development process. In Rothma, J., Thomas, J. (Eds.), Intervention research : Design and development for human service, 25-54. New York, NY: Haworth.
Francisco, V., Paine, A., & Fawcett, S. (1993). A methodology for monitoring and evaluating community health coalitions. Health Education Research: Theory and Practice, 8, 403-416.
Green, L., & Kreuter, M. (1991). Health promotion planning: An educational and environmental approach, 2nd ed. Mountain View, CA: Mayfield.
Joint Commission on Standards for Educational Evaluation. (1994). The Program Evaluation Standards. Thousand Oaks: Sage.
Koepsell, T., Wagner, E., Cheadle, A., Patrick, D., Martin, D., Diehr, P., & Perrin, E. (1992). Selected methodological issues in evaluating community -based health promotion and disease prevention programs. Annual Review of Public Health, 13, 31-57.
Mittlemark, M., Hunt, M., Heath, G., & Schmid, T. (1993). Realistic outcomes : Lessons from community-based research and demonstration programs for the prevention of cardiovascular diseases. Journal of Public Policy, 14, 437-462.
Paine, A., Fisher, J., Berkely, J., Fawcett, S., Williams, E, Lewis, R., & Harris, K. (2002). Analyzing the contribution for community change to population health outcomes in an adolescent pregnancy prevention initiative. Health Education & Behavior, 29(2), 183-193.
Parcel, G., Perry, C., & Taylor, W. (1990). Beyond demonstration: Diffusion of health promotion innovations. In N. Bracht, (Ed.), Health Promotion at the Community Level. Newbury Park, CA: Sage Publications.
Rogers, E. (1995). Diffusion of innovations. New York, NY: Free Press.
Thompson, J., Fawcett S., & Schultz, J. (2008). A framework to promote community mobilization for health youth development. American Journal of Preventative Medicine, 34 (3S), S72-S81.
Windsor, R., Baranowski, T., Clark, N., & Cutter G. (1984). Evaluating program effectiveness. Evaluation of health promotion and education programs, 126-170. Palo Alto, CA: Mayfield Publishing Company.
World Health 2007 Jul.Organization. (1987). Ottawa charter for health promotion. Health Promotion, 1-4, iii-v.
___You know the difference between universal approaches and targeted approaches to initiatives.
___You have incorporated multiple strategies, multiple levels, and multiple community sectors in your community effort.
___You understand that the goal of community health promotion is to increase opportunities for community members to collaborate to improve their quality of life.
___You have attempted to implement your evaluation at the same time as your initiative.
You know the two goals of an evaluation:
___To understand what is going on.
___To empower communities to take care of their own problems.
___You understand the advantages evaluations offer.
___You have analyzed the challenges your community and your initiative/evaluation may face.
___You have poised your community to function as a catalyst for change.
___You know the five steps of the comprehensive community initiative.
- Collaborative planning
- Community implementation, action, and change
- Community adaptation, institutionalization, and capacity
- More distal outcomes
- Dissemination
You know what to incorporate in each of these steps:
___Supporting collaborative planning-you have set your agenda and included all of the following:
- Ideas from people of diverse backgrounds
- Clarification of your visions, missions, objectives, and strategies
- Development an action plan
- Identification of local resources to help you solve
___Documenting community implementation, action, and change you have documented:
- Local efforts/accomplishments
- Changes in programs/policies/practices
- How things have been accomplished
___Assessing community adaptation, institutionalization, and capacity: you have:
- Looked at how the intervention has been changed
- Analyzed whether or not the efforts to sustain the initiative have been effective
- Measured to see if your efforts to address the issue have been effective
___Evaluating more distal outcomes: you have:
- Used both quantitative and qualitative methods to evaluate your successes
- Documented the intermediate outcomes
___Promoting dissemination: you have worked to spread word about the effectiveness of your comprehensive community initiative.
___You have analyzed, understood, and applied the 34 recommendations for practitioners and policy makers.
Evaluating community health initiatives in Kansas (U.S.A.)
This example talks about a composite case study that draws on work with several community health initiatives in Kansas with which our Center for Community Health and Development at the University of Kansas had evaluation and support responsibilities. Their missions included preventing teen pregnancy, preventing teen substance use, reducing risks for cardiovascular diseases and some cancers, and promoting health in rural communities. All of the initiatives had the aim of improving community members' abilities to better their quality of life.
Background and context
A variety of communities participated in these initiatives with grant support from the Kansas Health Foundation. Initiatives were located in urban areas, communities with military bases and prisons, and rural communities.
In each community, the local partnership attempted to be a catalyst for change. The initiatives involved community members in deciding how to change programs, policies, and practices to address local concerns. Task forces and action committees developed the initiatives' action plans.
Who was involved?
Participants in these initiatives included community members, service providers, community leaders, youth, and parents. They involved people affected by the problem and community leaders who had the ability to bring about changes. Members included targets of change, such as youth or elected officials whose actions (or inaction) contributed to the problem, and agents of change, such as religious leaders or peers, who could contribute to the solution. Other players included members of the steering committees and staff of the initiatives; program officers representing the grantmaker; and evaluation and support staff of the Center for Community Health and Development at the University of Kansas.
Stakeholder interests for the evaluation included understanding whether the efforts were having an effect and using this information to improve the initiative and its projects. Major stakeholders posed several questions to be addressed by the community evaluation:
- Is the initiative making a difference?
- Is the initiative serving as a catalyst for change?
- How is the initiative distributing its efforts?
- What makes a difference in how well the initiative functions?
The evaluation system used different measurement tools to address these and other questions.
Implementation of the model
Here, we'll look at how the catalyst and logic models we described in the section played out in these communities in Kansas.
Supporting collaborative planning
In the rural health initiative, our KU Center for Community Health and Development collaborated with rural communities in using concerns surveys, listening sessions or town meetings, and statistical information relevant to local concerns.
First, the concerns survey allowed community members to rate the importance of different health issues, such as teen drug abuse or water quality, and to say how well they thought each of these issues was being addressed in their community. Data were summarized to highlight major strengths and relative problems in the community. The issues chosen by each community varied, and included promoting good health among older adults, preventing substance use, and preventing teen pregnancy.
Second, the KU Center for Community Health and Development helped community members conduct listening sessions. In these informal focus groups, members of the community came together to define issues, identify barriers and resources, and brainstorm solutions. Third, statistical information was obtained by the Center for Community Health and Development to determine if what community members perceived as problems were confirmed by statistical records.
The Center's supported action planning by community members. Staff helped each community initiative to form a vision, create a mission, set objectives, and develop strategies and action steps. It's important to recognize that achieving consensus on what to do in the face of many problems and without always having all of the necessary information (or resources) involves artistry. Conflicts may arise when what people care about isn't supported by available "hard" data. For example, community members may feel strongly about working to end child violence in the community, even if statistics show that many other problems occur more often.
People throughout the community were encouraged to participate so that changes could be brought about throughout the community. The Center developed practical guides to support action planning for teen substance use, teen pregnancy, youth violence, chronic disease, child abuse and neglect, and health promotion for older adults.
Documenting community implementation, action, and change
The KU Center for Community Health and Development worked with members of the initiatives to document the changes in the community that were facilitated by each community partnership. Ratings of importance and feasibility by community members and outside "experts" helped inform members of the initiative about the importance of discrete community changes. Graphs and regular reports of accomplishments were used to inform stakeholders about the progress on intermediate outcomes. The Center also helped develop ways to get the word out about the initiative's accomplishments, and provided information about how to incorporate such information in status reports and future grant applications.
Implementation of initiatives was also documented. For example, with the teen pregnancy prevention initiatives, sexuality education was tracked using teacher reports and records. The Center also worked with the initiatives to determine if particular changes brought about by the initiatives were effective in reducing risks for the problem. For example, researchers and members of one initiative studied whether adjustments in physical education requirements improved the physical fitness of school children.
Assessing community adaptation, institutionalization, and capacity
The KU Center for Community Health and Development helped make necessary adjustments to important parts of the initiative. For example, communities working to prevent teen pregnancy adapted specific elements of an approach first implemented in South Carolina. To provide support and education' communities implemented a variety of different programs, including male-to-male support groups, abstinence clubs, and social events. Institutionalization was examined by looking at whether new programs, policies, and practices were still in place some months after they began. Community capacity was studied by looking at the pattern of community changes over time.
Evaluating more distal outcomes
The KU Center for Community Health and Development obtained information from behavioral surveys and archival records to help determine if changes in the environment were associated with corresponding changes in the bottom line. For example, the initiatives working to prevent teen substance use used school surveys to determine youths' reported use of alcohol, tobacco, and other drugs. The Center also gathered data on outcomes such as the rate of teen pregnancy. Finally, staff examined possible relationships between rates of community change and changes in the bottom line to help determine if the initiative had a real impact on its long-term goals.
Promoting dissemination
Center for Community Health and Development staff used local and national presentations, journal articles, and book chapters to get the word out about what works, what makes things work, and what doesn't appear to work. Staff also prepared handbooks for guiding action planning and community evaluation, and conducted workshops and training sessions. Finally, the Center team helped develop this website -- The Community Tool Box -- to share information about promising practices for improving our communities.
Contributor
Stephen B. Fawcett
Adrienne Paine-Andrews
Vincent T. Francisco
Jerry Schultz
Kimber P. Richter
Jannette Berkley Patton
Jacqueline L. Fisher
Rhonda K. Lewis
Christine M. Lopez
Stergios Russos
Ella L. Williams
Kari J. Harris
Paul Evensen
Tools: Logic Model - Evaluating Comprehensive Community Initiatives
1. Supporting Collaborative Planning
Collaborative planning is a critical and ongoing task of a successful organization. It brings together people and organizations with different experiences and resources. Together, they clarify or develop the group's vision, mission, objectives, strategies, and action steps. In doing so, they can bring about changes in the community.
Support activities related to collaborative planning include the following:
A. Assess local concerns and assets
- Conducting Public Forums and Listening Sessions
- Analyzing Community Problems
- Conducting Focus Groups
- Conducting Needs Assessment Surveys
- Identifying Community Assets and Resources
- Conducting Concerns Surveys
- Conducting Interviews
- Rating Community Goals
B. Obtain data on behavior and community-level indicators
- Collecting Information About the Problem
- Developing Baseline Measures of Behavior
- Gathering and Using Community-Level Indicators
C. Facilitate setting vision, mission, objectives, and strategies
D. Help develop the action plan
2. Documenting Community Implementation, Action, and Change
Community evaluation documents what gets done by community initiatives, and lets all of the members of the initiative know about these changes. That way, community members can improve on what they have done. Community implementation, action, and change include the following related documentation activities. After each activity, relevant Community Tool Box sections are listed.
A. Monitor and provide feedback on community action and change
B. Monitor and provide feedback on implementation of key components
3. Assessing Community Adaptation, Institutionalization, and Capacity
Community evaluators also look at how the interventions are changed, and whether or not these adjustments fit the community actually work. They also determine if efforts to sustain the initiative are effective. Finally, evaluators try to measure if efforts to improve the community's capacity to address current (and future) issues have been effective. Related Community Tool Box sections include:
- Adapting Community Interventions for Different Cultures and Communities
- Planning for Long-Term Institutionalization
- Our Model of Practice: Building Capacity for Community and System Change
4. Evaluating More Distal Outcomes
Of course, the ultimate goal of most community initiatives is to move the bottom line --to have fewer people contract HIV/AIDS or be victims of violence, to give two examples. To see if this has happened, community evaluators use quantitative methods. One such method is the use of behavioral surveys. For example, a teen pregnancy prevention project might survey students about reported abstinence or unprotected sexual activity. Another quantitative method is finding archival records of community-level indicators of outcomes. For example, the project above might use estimated rates of teen pregnancy for the city or county available from the health department.
They also use qualitative methods, such as interviews with participants, to better understand the meaning and value of efforts. Used together, quantitative and qualitative information weave a rich tapestry of understanding around the initiative's efforts. They are much more powerful together than either could be alone. Evaluating more distal outcomes include the following related activities. After each activity, relevant Community Tool Box sections are listed.
A. Assess community-level outcom
- Reaching your Goals: The Goal Attainment Report
- Behavioral Surveys
- Gathering and Using Community-Level Indicators
B. Collect ongoing qualitative information
- Obtaining Feedback from Constituents: What Changes are Important and Feasible
- Rating Member Satisfaction
- Constituent Survey of Outcomes: Ratings of Importance
- Conducting Interviews with Key Participants to Analyze Critical Events
5. Promoting Dissemination
Finally, evaluators help community initiatives spread the word about effectiveness to important audiences, such as community boards and grantmakers. Evaluators help provide and interpret data about what works, what makes it work, and what doesn't work. Ways to get the word out may include presentations, professional articles, workshops and training, handbooks, media reports and on the Internet.
Information on the active dissemination of the initiative and its components can be found in the following related Community Tool Box sections:
- What do we mean by values, principles, and assumptions?
- Core values of the Community Tool Box
- Core principles of the Community Tool Box
- Assumptions of the Community Tool Box
The work of community health and development is both science and art. On the one hand, it grows from the lessons of experience learned by community activists and professionals trying to create systems, programs, interventions, and policies that improve the lives and health of everyone in communities. On the other hand, it stems from the passion for social justice, equity, and fairness that leads people to work to create healthy communities where all people, regardless of their backgrounds or circumstances, have what they need.
The commitment to community doesn’t arise out of nowhere. It comes from and is guided by values, principles, and assumptions that spring from our backgrounds and cultures, from our experiences, and from our conscious decisions about what is right. These values, principles, and assumptions shape our vision of the world as it should be, and motivate us to try to make it so.
The purpose of this chapter is to provide a framework for the chapters that follow.
What do we mean by values, principles, and assumptions?
The terms values, principles, and assumptions are sometimes used as if they all mean the same thing – the underlying truths on which we base our dealings with the world. In fact, although they are all “truths” to some extent, they are different in meaning and substance. Although we realize how similar they are, we’ll try to consider each of the three. Understanding the difference can help us sort out when we’re operating on facts or well-examined experience, when we’re applying moral or ethical rules or judgments, and when we’re responding to emotion or bias or unexamined “knowledge” that may not be accurate.
All of these – facts and experience, morality, ethics, bias, emotion, “common knowledge” – can be legitimate reasons for action in some circumstances. (It’s hardly logical to be non-violent in the face of racist police armed with clubs and vicious dogs; the moral imperative for those in the Civil Rights Movement was more important than facts and experience in that situation.) The importance of knowing the difference is understanding your own motivation, and acting accordingly.
Values
Values are our guidelines for living and behavior. Each of us has a set of deeply held beliefs about how the world should be. For some people, that set of beliefs is largely shaped by a religion, a culture, a peer group, or society at large. For others, it has been arrived at through careful thought and reflection on experience, and is unique. For most of us, it is probably a combination of the two. Values often concern the core issues of our lives: personal relationships, morality, gender and social roles, race, social class, and the organization of society, to name just a few.
Principles
Principles are the fundamental scientific, logical, or moral/ethical “truths” arising from experience, knowledge, and values on which we base our actions and thinking. In the case of the Community Tool Box team, they are the underpinning of our understanding of community health and development, the truths that shape both our reasons for doing the work and the work itself.
Scientific and logical principles are derived from experience and experiment, from knowledge (which itself comes from experience and experiment on the part of someone else), from logical analysis, and/or from theory. They are as objective – as free of bias, untested assumptions, etc., and as firmly based on provable fact or reasoned analysis – as they can be, and are considered true until proven otherwise. They include the physical and other laws by which the universe operates, and their extensions into the sphere of human action. (If you run into a tree at 70 miles an hour, you’ll probably be seriously injured or killed. If you drive your car when you’re drunk, you don’t have much judgment or control, making it much more likely that you’ll hit that tree at 70 miles an hour. Principle: Don’t drive drunk.)
Scientific and logical principles are typified by such statements as “For every action there is an equal and opposite reaction” (Newton’s Third Law of Motion). Such principles are either verifiable by observation – a cannonball shooting out of a cannon drives the cannon itself back in the opposite direction, consistent with Newton’s Third Law – or are supported by all the evidence available – thousands of dinosaur fossils, various chemical and geological dating systems – and are “theories” only in the sense that they can’t be fully proven because of the impossibility of traveling back in time or across interstellar space.
Moral and ethical principles are where values come in. These principles grow out of deeply held beliefs and values, and are often the principles upon which community work is founded. Devotion to democratic process, to equity and fair distribution of resources, to a reasonable quality of life for everyone, to the sacredness of life, to the obligation of people to help one another – these all come not from logic or scientific experiment, but from a value system that puts a high priority on human dignity and relationships.
One of the clearest statements of moral/ethical principle is that of the American Declaration of Independence, written by Thomas Jefferson (with Benjamin Franklin’s help) in 1776: “We hold these truths to be self-evident: that all men are created equal; that they are endowed by their Creator with certain unalienable rights; that among these are life, liberty, and the pursuit of happiness…”
This statement is actually a good demonstration of how values and principles form a loop, with principles based on values. Jefferson and Franklin may have held these “truths” to be self-evident (i.e., so obvious that they don’t have to be explained or supported), but the certainty of the American founding fathers had to do with their values, not with any scientific proof that they were right.
At the same time, people may hold the same principles, but interpret them through different value systems. Two individuals may both believe, for instance, that all humans are created equal. For one, this may mean that they have a duty to try to gain equity for all. For the other, it may mean that since everyone starts out equal, anyone who doesn’t achieve or do well is at fault for their failure, and therefore deserves no help or respect.
Even scientific principles are, in some sense, based on values. The use of the scientific method, the adherence to empirical evidence (i.e., evidence actually observed or experienced), the willingness to believe the evidence even when it conflicts with religious or cultural assumptions – these are all characteristics of a value system that puts a high priority on logical and scientific thinking.
Some people subscribe to different values, which place much more importance on religious or cultural traditions than on the work of science.
Assumptions
Assumptions are the next level of truths, the ones we feel we can take for granted, given the principles we have accepted. If we accept, for instance, that life is an “unalienable right” – a right of every human being that cannot be taken away – then we will usually assume that killing another person is wrong, or at least that we don’t have the right to do it.
Assumptions are often unexamined. They are the facts or beliefs that we don’t question, because we “know” they’re accurate, even though they may not be. Most of us have been in situations where we’ve had to face the consequences of our incorrect assumptions.
It is nevertheless true that we all bring assumptions to what we do, and the Community Tool Box team is no exception. We hope our assumptions are based on carefully thought-out principles, however, and try to reevaluate them to make sure we aren’t operating on false premises.
What follows are some of the core values, principles, and assumptions on which the Community Tool Box is based. The lists are not meant to be comprehensive, and are not necessarily in order of priority.
Core values of the Community Tool Box
We’ll start with values, because, as we’ve explained, they’re usually the basis for the work we do. Our values are a reflection of the way each of us sees and addresses the world.
Although values can and do change as people grow and learn, there are some basic values that most people hold: the need to protect and preserve human life, for instance, or the responsibility of adults to care for children. These and a number of other values are held by the majority of people in most societies, and are often the foundation of laws and social norms.
Here are some of the values behind the Community Tool Box:
Everyone has a right to a decent quality of life. This is a core value for most people involved in community health and development. The Ottawa Charter for Health Promotion, a policy statement issued by the World Health Organization-sponsored First International Conference on Health Promotion (Ottawa, Canada, 1986), embodies this value. It states that the prerequisites for health in a community are peace, shelter, enough food, adequate income to support individuals and families, a stable ecosystem, sustainable resources, social justice, and equity.
Everyone is worthy of respect and equal consideration. Treating people with respect and consideration doesn’t mean you can’t disagree with them, or even fight against what they’re trying to do. Rather, it means that you should approach them as equals who think they’re right, rather than labeling or treating them as evil or stupid.
Any community work or research should have the ultimate aim of being useful in improving people’s lives, particularly the lives of those with the greatest needs and/or least power. There’s no point to research or action in health and community work unless it contributes to the quality of life in the community and/or the world. Knowledge is hugely important, but it doesn’t matter much if you don’t do anything with it.
Due to the inherent biases we all have, some understood and some we may not be aware of, it is essential for us to continually increase awareness of our biases and to ensure they do not contradict the higher-order values previously discussed, such as ensuring all people are respected.
Fairness demands that everyone affected by research or by an issue – all stakeholders – should have the opportunity for either direct participation or representation in planning, implementing, and analyzing the resulting research or intervention. Community work, in whatever field, should be about creating new situations with the people affected, not about doing things for or to them.
This work isn’t about power, but about the public good. Therefore, power and leadership, to the extent that it doesn’t entirely compromise the purpose of the work, should be shared as much as possible.
Core principles of the Community Tool Box
Principles, as we’ve described, are the essential truths on which we base our work. They’re different from values, in that values are a reflection of what we deeply believe and feel: principles are a reflection of what we think. Although the reasoning behind them may – and usually does – grow out of our value system, they are generally practical, and aimed not at guiding our overall thinking and behavior, but at putting them – and our values – to work in the real world.
“Fair” doesn’t mean that everyone gets the same thing; it means that everyone gets what they need. This implies that equity involves making sure that those with less have enough for their needs, and aren’t ignored or exploited by those with more money or power.
Community work is far more likely to be successful if it involves all stakeholders from the very beginning. This is the principle that derives from the value concerning the fairness of involving everyone affected by an issue. It’s stated as a principle because it is a practical statement: planning, intervention, and evaluation all simply go better if there is input and participation by everyone involved. This participatory process results in more ideas, more widespread support, the possibility of avoiding errors because of ignorance of community history or past performance, and ownership of the resulting action by everyone affected.
Leadership from within the community should be encouraged and nurtured. Positive community change is more likely to occur, and more likely to continue, if it is built from within. The leaders for this work should come from the community, because they know the community so well, because they have the credibility that community membership brings, and because they have so much interest in success. It is also a matter of fairness – it is only right that people should have control over their own futures. For outsiders to impose solutions and leadership may be effective in the short term, but it hinders the community’s ability to develop and evolve.
Community work takes careful planning at every stage of the process. Assessment and issue identification, strategic planning, implementation, evaluation, and maintenance of effort all have greater chances of success with collaborative planning. This principle is reflected in the large number of sections that discuss planning.
Evaluation is absolutely necessary, and useful in many ways, although probably most useful as a tool for improving your effort. It can show where changes are needed, pinpoint problems and strengths, suggest additional action, and provide accountability. A formative evaluation – one that carefully examines the process and content of your effort, compares it to what was supposed to occur, and analyzes the results of what you did in light of how you could improve on it – can tell you whether parts of the process or the goals need to be changed in order for the effort to become more effective. A summative evaluation – one that simply decides whether you did well or not, essentially focusing only on accountability – is far less helpful. A summative evaluation can often stop an effort in its tracks, when all it needs to become successful is a relatively minor change in execution.
Outcomes matter. While fingerpointing and handwringing over failures to meet goals may not be particularly helpful, it’s important to remember the reason you’re doing this work in the first place. You should be constantly doing your best both to adapt your effort for greater effectiveness and to keep your ultimate goal in sight.
Time is of the essence. Always allow enough time for things to happen, both in your planning and in your implementation. That means factoring in how long it actually takes to get an effort or program started:
- Recruiting a participatory planning team
- Developing a plan
- Getting the people, the space, the equipment and materials, and whatever else is needed in place
- Finding funding or other resources
- Carrying out the actual work
- Designing, implementing, and analyzing an evaluation
- Making the changes suggested by the evaluation, and then doing it all again
Allowing enough time also means allowing time in your effort for the desired results to occur. In some public health programs, for instance, it may take years to know whether a particular method of prevention has been truly successful. Even in many programs that policymakers see as quick fixes, results may not be forthcoming as fast as they’d like. Programming in the time to get the job done can be frustrating, but it’s crucial to success.
Legislators may see an employment training program as a simple matter of people who are unemployed learning a particular skill – similar to taking a course for a set number of weeks. But policymakers often don’t realize that not only do different people learn at different rates, but that some participants may never have held a job, and may not understand the basics of working effectively with supervisors and coworkers, or even of getting to work on time every day. Teaching all the basics in addition to the job skill in question may take a great deal longer than policymakers intend, but will be more effective in the long run.
Don’t bite off more than you can chew. Aim high, but be honest with yourself and others about what you can actually do, and how much time it will take.
Make sure that your funding and other resources are adequate for what you’re trying to do. Trying to carry out a project without the resources you need is a recipe for failure. It makes far more sense to scale back your intentions, or to allow more time to get what you need, than to go into an effort ill-equipped to carry it off.
Community action should take place at the level and time to make it most effective. The level of community action refers to where the action is aimed. You may be planning action to benefit a particular group, but your effort might be more effective if aimed at policymakers, or at some other group or individual whose actions affect the group you’re concerned with.
By the same token, your effort should occur at the best time for it to have the desired effect. This may mean coordinating it with regular legislative procedures (the issuing of a state budget, for instance), with a particular season (timing a fundraising effort for families experiencing homelessness to coincide with the winter holidays), with a similar national or international effort (e.g., National Literacy Day), or with current events as they develop. (You’d want to campaign to save an open space when its possible development first came to light, so as to give your effort enough time to rally public opinion and get the facts out.
If you wait till the bulldozers are already pushing down trees, it’s too late.)
Community intervention should be replicable and sustainable. For an intervention to be “replicable,” it has to be able to be repeated successfully in other places and/or with other participants. The basic elements of the intervention should be effective – perhaps with some adaptation to a different community or population – anywhere, and you should be able to explain exactly how it works, so that someone else can set it up and run it in another situation. That means you have to understand the intervention’s elements clearly, and know what it is that makes it successful. Since the formula often involves a combination of theory, philosophy, interpersonal approaches, politics, and methods, you have to pay careful attention to, document, and evaluate what you’re doing if you want someone else to be able to do it as well.
For an intervention to be sustainable, you have to be able to continue to operate it for the long term. That includes not only carrying on the work effectively, but also finding the financial and other resources necessary to keep it going, building community support, providing ongoing training for both new and continuing staff, and constantly evaluating and trying to improve what you’re doing.
That leads to the next principle:
Community work is never done. Whatever your work involves – whether a community intervention, an advocacy campaign, a one-time community action to accomplish a particular goal, the founding of an organization, or the establishment of a self-sustaining community initiative – your task isn’t done when you’ve reached your initial goal. If you don’t work to maintain what you’ve done, or assure that others are doing so, it will fall apart. To really bring about change in a community, you have to keep at it indefinitely.
Don’t lose sight of your vision, your principles, and your values in the struggle to get things done. It’s often tempting to take any funding that’s available, or to change what you’re doing in order to be eligible for resources. Sometimes, it might seem that altering your purpose will make it more palatable and less controversial, and will make your life easier. When these possibilities arise, it’s crucial to review what your vision, mission, and ultimate goals are. If these need to change because of changes in circumstances or community needs, then they should. But if the motivation for change conflicts with your values or your vision – or the reason you’re doing the work in the first place – it has to be rejected. The integrity of your cause and your organization is worth far more, and will contribute far more to your effort, than any short-term financial or public relations gain.
The real goal of community work is positive social change. The ideal, in most cases, is to improve the quality of life for a particular group, or for everyone, in the community. This often means changing some fundamental aspects of the way the community thinks or functions – its attitude toward domestic violence, for instance, its commitment to education or to environmental preservation, its consumption of alcohol or unhealthy food, or its concept of social justice. If you can help the community change its attitudes and behaviors in positive ways, it will become a better place for everyone to live.
Core assumptions of the Community Tool Box
As we’ve explained, assumptions are the ideas we take for granted. They’re not the same as values, because they often stem from logical – or what we believe is logical – reasoning, rather than from deeply held beliefs. They differ from principles in that they don’t usually form the basis of our thinking and action, but guide how we respond to our principles.
It’s almost impossible to list all our assumptions, simply because we’re not aware of many of them. They’re so deeply ingrained in our thinking, we don’t even realize that they’re assumptions: they seem like truths. With that in mind, we’ll try to list some of the most important assumptions behind the work of the Community Tool Box.
Just about everyone wants what’s best for the community. People may disagree both on the definition of what’s best, and on how to get there, but their goal is usually similar: to live in a community that’s as good as it can be in as many ways as possible. If we start with that assumption, it becomes easier to establish common ground, and to begin to work together. Demonizing those we disagree with is easy and often satisfying, but it leads nowhere. Assuming instead that others want many of the same things we do can lead to cooperation on some issues, and can at least start a dialogue on others. That’s far better, both practically and otherwise, than two factions stuck in opposition, with no chance for movement.
Once people understand others’ circumstances, they’re usually willing to help. In the quest for equity in a community, we often come up against attitudes that seem mean and unfeeling. In many cases, however, these attitudes are the result of people in different circumstances having little contact with one another. If you have little experience with people receiving public assistance, it can be easy to make assumptions about their circumstances or willingness to work. Learning more about the realities people may face -- including limited income, barriers to employment, lack of access to childcare, transportation challenges, or difficulty obtaining affordable health care -- can provide a fuller understanding of their experiences and make it more difficult to view them through stereotypes.
If people are treated with respect, they usually respond the same way. Whether you’re dealing with participants in an intervention, with people who hold differing perspectives, or with allies, treat them as you’d wish to be treated. The Golden Rule is generally a good guideline, not only morally and ethically, but practically.
Coalitions, partnerships, and collaborations are built one relationship at a time. It may be relatively easy to bring a number of people and groups together around an issue, but getting them to stay and work together is another matter. The relationships that they build with one another are the glue that can make that happen.
Tip O’Neill, former Speaker of the U.S. House of Representatives, used to say that all politics was local. What he really meant was that all politics was personal, that alliances are built relationship by relationship. That’s as true for community activists as it is for members of Congress.
People have to believe something is possible before they’ll work to make it happen. This is the reason that a shared vision is so important in community work, but it also holds true on the individual level. Students, for instance, have to believe they can learn before they’ll put in the concentration and effort needed to do so. If they become too discouraged, the task looks impossible, and it’s easier to give up than to risk continual failure.
An individual or community has to be able to imagine the future in order to make it happen. If there’s no belief in the possibility of change, there’s likely to be no change.
People working together are better off and more successful than people working alone. They’ll have more ideas, develop more capacity to get things done, and feed off one another’s energy in order to keep the effort moving. If it’s possible, concerted action is almost always more effective in the long run than one person or organization going it alone.
The world isn’t perfect; this work is necessary to create positive social change and make it a better place for everyone.
In summary
Underlying every section of the Community Tool Box are the values, principles, and assumptions that the Tool Box team uses to guide its work. These have to do largely with the fundamental dignity and worth of all people; the ability of – and necessity for – communities to solve their own problems and produce their own leaders; the ethical and practical necessities of health and community work; and the need for positive social change.
This section is meant to help Tool Box users understand the perspective of the Community Tool Box, and perhaps make clearer some of what’s presented there. It’s also meant to help users think about their own values, principles, and assumptions, to make them conscious, to examine them, and to continue to hold them up to scrutiny as they do this often difficult and incredibly important work.
Resources
Print Resource
Fawcett, S. Some Values Guiding Community Research and Action. Journal of Applied Behavior Analysis, 24, no.4 (1991), pp.624-636.
What do we mean by values, principles, and assumptions?
___Values are the deeply held beliefs about how the world should be that provide our guidelines for living and behavior.
___Principles are the fundamental scientific, logical, or moral/ethical “truths,” arising from experience, knowledge, and (often) values, on which we base our actions and thinking.
___Assumptions are the next level of truths, the ones we feel we can take for granted, given the principles we have accepted.
Core values of the Community Tool Box
___Everyone in a community has a right to a decent quality of life.
___Everyone is worthy of respect and equal consideration.
___Any community work or research should have the ultimate aim of being useful in improving people’s lives, particularly the lives of those most in need and/or least powerful.
___Racism and bias – because of religion, class, gender, sexual orientation, ethnic background, disability, etc. – have no place in a civil society.
___Fairness demands that everyone affected by research or by an issue – all stakeholders – should have the opportunity for either direct participation or representation in planning, implementing, and analyzing the resulting research or intervention.
___This work isn’t about power or turf, but about the public good.
Core principles of the Community Tool Box
___“Fair” doesn’t mean that everyone gets the same thing; it means that everyone gets what she needs.
___Community work is far more likely to be successful if it involves all stakeholders from the very beginning.
___Leadership from within the community should be encouraged and nurtured.
___Community work takes careful planning at every stage of the process.
___Evaluation is absolutely necessary, and useful in many ways, although probably most useful as a tool for improving your effort.
___Outcomes matter.
___Time is of the essence.
___Don’t bite off more than you can chew.
___Make sure that your funding and other resources are adequate for what you’re trying to do.
___Community action should take place at the level and time to make it most effective.
___Community intervention should be replicable and sustainable.
___Community work is never done.
___Don’t lose sight of your vision, your principles, and your values in the struggle to get things done.
___The real goal of community work is positive social change.
Assumptions of the Community Tool Box
___Just about everyone wants what’s best for the community.
___Once people understand others’ circumstances, they’re usually willing to help.
___If people are treated with respect, they usually respond the same way.
___Coalitions, partnerships, and collaborations are built one relationship at a time.
___People have to believe something is possible before they’ll work to make it happen.
___People working together are better off and more successful than people working alone.
___The world isn’t perfect; this work is necessary to create positive social change and make it a better place for everyone.
Contributor
Phil Rabinowitz
To improve our communities -- to make them places where all people are healthy, safe, and cared for -- takes a lot of work. As community organizers, we know all too well that we can't do it alone. The ability to partner effectively with others is absolutely essential to doing what we like to call "the work" of building healthy communities.
However, these partnerships don't materialize out of thin air. And once they do occur, the players involved aren't always sure of their roles, or how those roles can come together in a manner that meets everyone's needs and interests. In short, there's often a knowledge gap, even when everyone wants to work together for the same outcomes.
In this section, we'll try to address that gap. We outline a modest proposal for how three key groups -- community partnerships, support and intermediary organizations, and grantmakers -- might work together to make the most of everyone's investments in the work.
We'll start with a brief look at why we focus on community (and systems) change and what we believe are seven key elements in effective community work. This understanding, although laid out elsewhere in the Community Tool Box, forms the basis for later ideas in this section. Then, we will explain who the key players in community work are, and follow up with an understanding of how they can best work together to make the most of everyone's efforts.
Our hope is that, when adapted in local dialogue, this model "memorandum of collaboration" will help guide future community investments.
A focus on community (and systems) change
When we talk about building healthier communities, we mean the process of people working together to address what matters to them -- whether that is reducing violence, revitalizing an urban neighborhood, or promoting child health. Civic engagement is promoted among all of the members of the community. By community, we mean people who share a common place, such as a rural community or urban neighborhood, or experience, including being an adolescent or a member of an underrepresented racial or ethnic group.
To address what matters to community members, we need to change the conditions in which we live, with the hope that changing those conditions will change people's behavior and more distant outcomes. For example, a community organization might make it more difficult for adolescents to buy cigarettes, with the hope that those changes will result in fewer adolescents smoking, and fewer related deaths.
We believe that collaborative partnerships should focus on environmental changes -- bringing about those community and systems changes that modify local conditions. That's because we believe these changes are an intermediate outcome in the long process of community health improvement. Community and systems changes fall into one of three categories, all of which should relate back to community-determined goals:
- New or modified programs -- for example, after-school programs or prevention services
- New or modified policies -- for example, higher fines for selling products that cannot legally be sold to minors or family-friendly policies in businesses
- New or modified practices -- for example, improved access to health services or increased opportunities for academic participation in schools
What makes it work: Seven key factors in community change
Our research and experience -- and that of many others -- suggests that there are seven essential ingredients that contribute to community change.
- Clear vision and mission -- those initiatives with a clear and specific focus, such as increasing rates of childhood immunization or lowering the rate of unemployment, bring about much higher rates of change than broad "healthy communities" efforts which lack a targeted mission and objectives. The vision and mission may reflect a continuum of outcomes, including:
- Specific issues (e.g., pregnancies among adolescents),
- Broader interrelated concerns (e.g., youth development), and/or
- More fundamental social determinants of health and development (e.g., children experiencing poverty).
- Action planning -- Identifying specific community changes (that is, new or modified programs, policies, and practices) to be sought may be the single most important practice that can be implemented. The action plan should be quite precise, specifying with whom, by whom, how, and by when each action step should be carried out.
- Leadership -- A change in leadership can dramatically affect the rate of change brought about by a community group. The loss of strong leadership can be particularly difficult for an organization.
- Resources for community mobilizers -- Hiring community mobilizers or organizers can aid in following up on action plans. It can be very difficult to maintain an organization without some paid staff. Paid organizers can help fan the flames and keep the level of excitement about the organization and its goals at a consistently high level.
- Documentation and feedback on the changes brought about by the organization -- It's also very important that people keep a record of what they have done and how they have done it. Having this history can be an invaluable guide for the organization's work. Looking regularly (at least quarterly) at what the group has done, how quickly it has occurred, and outside events that affect the group's work has been shown to spur groups on to even greater heights.
- Technical assistance -- Outside help with specific actions, such as action planning or securing resources, is also a way to support a group's efforts to transform its community.
- Making outcomes matter -- Finally, grantmakers also have the ability to increase rates of community and systems change through offering incentives or disincentives to their grantees. For example, the annual renewal of multi-year awards or the offering of bonus grants could be based on evidence of progress or accomplishment by the community group.
Who is involved?
Transforming the conditions that affect community health and development requires a broad collaborative partnership among key players. Three distinct groups emerge as playing vital, interdependent roles:
- State and community partnerships
- Support and intermediary organizations
- Grantmakers
State and community partnerships -- those doing the work of community and systems change -- link together people and organizations that have the same goals. For example, a community partnership for universal access to health care might bring together representatives from health care with representatives of groups that have historically faced barriers to access. Together, they might work to make changes throughout the community that would affect access for all. Specific changes might be made in local community-based organizations, health organizations, businesses, schools, the government, financial institutions, and the faith community -- all with the overall goal of access to health care for all.
Support and intermediary organizations -- such as university-based research centers and community-based organizations, help community partners develop the skills they need to be effective. Often, these groups concentrate on improving community members' understanding of the core competencies necessary to do this work. Examples of these competencies include community assessment, strategic planning, community action and advocacy, community evaluation, and securing resources to sustain the effort.
Grantmakers -- help create conditions for success by using requests for proposals to bring people together for a common purpose, such as reducing domestic violence or improving arts education for children. They can also broker connections among groups working in the same community or on the same issue. Finally, they can leverage funding and resources through relationships with other grantmakers and help make outcomes matter.
A proposed "Memorandum of Collaboration"
Our question in this section is, how can these three groups work together most effectively? What are the roles and responsibilities of each that, taken together, will help make our communities healthier places to live?
We'll look again at each of the seven key elements for effective community work that we discussed above, offering timelines and specific roles that partners can assume. These roles and responsibilities are summarized in a table under the Tools tab.
Refining and targeting the partnership's vision, mission, and objectives
How long? This step should take approximately four to six months.
- Community partnership: The community partnership is responsible for selecting a workable (i.e., fairly modest) number of broad goals, such as improving nutrition among students, reducing crime and violence, or increasing the rate of immunization. By specifying these goals, the group can better define and focus their work.
- Support organizations: Support organizations can assist the community partnerships in developing a broad-based vision, and then in framing their objectives in a manner that is both specific and workable. For example, if the community group is interested in education but does not have a specific idea about what should be done, a support organization might suggest the following goal statement:
By 20XX, the graduation rate for youth entering local high schools will increase by 40%. Support organizations will also work with the community partnership to identify community-level indicators that are most likely to give an accurate and sensitive picture of how effective the partnership's efforts have been.
- Grantmakers: Grantmakers can help applicants find the funders who are most appropriate for their work. They can also offer longer-term grants (for example, at least several years) so that grantees can have the long-term support they need to really make a difference. Finally, grantmakers can offer investments that look holistically at the community and its situation.
Developing an action plan for bringing about community and systems change related to community-determined goals for health and development
How long? This step takes approximately six to eight months for the original development, and will then be ongoing through the life of the initiative.
- Community partnership: Building on earlier efforts, collaborating partners should identify specific changes to be brought about. These changes in programs, policies, and practices will be sought throughout the community (for example, in schools, government, business, health and human service organizations, the faith community, and so on). Specific action plans that complement one another should be developed for each objective the community partnership has chosen.
It's very important that the planning process is inclusive, involving people who have significant influence in the community (for example, elected officials), as well as the people who are most affected by the concern (such as residents of neighborhoods with limited economic resources). Finally, it is often helpful to organize members in working committees for each specific objective, such as creating a Task Force on Substance Use. This coordinates and focuses efforts so they will have the greatest possible impact.
- Support organizations: Support organizations can assist with action planning by suggesting possible actions, and making members of community partnerships aware of "best practices" (successful actions taken by other community groups) for each objective. They can also be very helpful in supporting the early stages of action planning. For example, they might organize and run planning retreats for the community group.
- Grantmakers: Grantmakers can help community groups get in touch with other organizations with special expertise in specific goal areas. For example, if one of the goals a grantee has is to promote caring relationships for children, the grantmaker might get the group in touch with another of their grantees doing similar work in another community or state. Grantmakers can also assist in bringing about broader changes, such as implementing more effective grantmaking practices; or helping change regional planning policies that concentrate poverty in a few urban neighborhoods. These "systems changes" can work to improve the conditions under which community improvement efforts occur.
Developing and supporting leadership within communities
How long? This is an ongoing task.
- Community partnership: Members of the partnership can enhance and support existing leadership through mechanisms such as meetings and retreats. They will also seek to develop new generations of leaders by creating opportunities for new leadership to develop, through mentoring newer leaders, and by supporting local young people in leadership roles.
- Support organizations: Support organizations can use direct personal assistance, support groups, and print and online resources to support local leadership in their efforts. They can also help to develop formal (e.g. courses) and informal learning communities (e.g., support networks).
- Grantmakers: Grantmakers can support partners in acquiring additional resources for leadership development. Using traditional face-to-face gatherings and communications technologies such as video conferencing and online forums, grantmakers can help community partnerships connect leaders to each other across distance and topic area. They can also connect them to additional resources to support their work.
Documenting the process of community change and improvement, and using feedback to improve and celebrate efforts
How long? This is an ongoing task that should occur on a monthly basis.
- Community partnership: Using a documentation and evaluation system, members of the partnership will gather information on changes facilitated by the partnership. They will also assist in obtaining other information to help understand and be accountable for their work, including success stories and community-level indicators related to their objectives.
Finally, they will review data on intermediate outcomes (community and systems change) at least quarterly, and data on more distant outcomes (community-level indicators) at least annually. This will help guide improvements and promote the celebration of accomplishments.
- Support organizations: Support organizations can facilitate a conversation about what are important markers of success. They will establish and maintain a system for documenting community and systems changes. Finally, they will help local documenters in clarifying and interpreting information, and in communicating important news to funders and the broader community.
- Grantmakers: Grantmakers can request and accept information on progress made by the community group for its grant status reports and grant applications. To maximize efficiency, they should work with other grantmakers and organizations to encourage acceptance of the same data for different reports the community group will be responsible for. If needed, they can help secure access to data on community-level indicators. Grantmakers can also help document their own contributions to local efforts (such as facilitating systems changes or brokering access to resources).
Securing and providing technical assistance for local groups' efforts
How long? This is an ongoing task.
- Community partnership: Members of the partnership should look for help from organizations with specialized knowledge, such as those which specialize in an issue that the partnership is interested in (for example, HIV prevention or child maltreatment). In addition, the partnerships should develop their own capacity to provide technical assistance, such as in action planning or documentation, for other communities working on similar issues.
- Support organizations: Support organizations can provide technical assistance to community partnerships in implementing and documenting their work. This might include providing training materials and/or workshops in skills such as community assessment, action planning, leadership development, and evaluation.
- Grantmakers: Grantmakers can help fund support organizations, and they can also foster relationships between support organizations and the community partnerships that might benefit from their help.
Securing and providing financial resources for work in local communities
How long? We recommend an initial ten-year commitment that is potentially renewable; further, we suggest multi-year grants with their renewal based on evidence of progress.
- Community partnership: As appropriate, partners will hire and support community organizers responsible for helping bring about the community and systems changes identified in the group's action plan. In applications for grant funding, the partners should provide evidence of the need for (and value of) community investment. This includes using quantitative information on community and systems change and improvement through community-level indicators, and qualitative information such as success stories.
- Support organizations: Support organizations can assist local documenters in analyzing, interpreting, and communicating data for use in grant status reports and "progress to date" sections of grant applications. This and related qualitative information such as success stories can be used to help leverage resources as the community's accomplishments are communicated to prospective funders.
- Grantmakers: Grantmakers can facilitate the development of grant proposals that support a long-term, comprehensive community change and improvement effort. Grantmakers can also help the community partnership make necessary connections with other funders to help generate the resources needed for the effort. This is particularly important because often, effective community work takes a substantial amount of money and other resources -- quite possibly, more than a single grantmaker is willing or able to invest.
Making outcomes matter in working with local communities
How long? This is an ongoing task.
- Community partnership: The partnership should agree to submit annual status reports that include information on evidence of community and systems change as well as progress towards affecting the bottom line. To be fully accountable, they should agree to share evidence of accomplishments (and needed changes) with funders and the broader community.
- Support organizations: Support organizations should assist the community partnership in documenting, analyzing, and communicating data on the process of community change and improvement for grant status reports.
- Grantmakers: Grantmakers can require annual grant status reports that include evidence of progress. To maximize accountability to the community and to grantmakers, grantmakers can try to "make outcomes matter" in three ways.
First, annual renewal of multi-year awards can be based on the evidence of progress. Initially, progress should be judged largely on community involvement and on the rate and kind of community and systems change facilitated by the community partnership. In later years, improvement on community-level indicators will serve as additional evidence of success.
Second, bonus grants (up to one-third of the grant award) may be earned for outstanding accomplishments, such as high rates of changes on issues that are important to community members. For example, the community might show a markedly decreased rate of pregnancies among adolescents that can be traced back to the partnership's efforts.
Third, outcome dividends could be made available to enhance accountability for longer-term community-level outcomes, such as a lowered rate of substance use or improved school performance. The "outcome dividend" is a cash bonus that is calculated based on cost-benefit estimates associated with improvements. The outcome dividend will be deposited in a local "Community Trust Account" and reinvested by the community partnership for work on community-determined goals.
In summary
Community health -- the well-being of the people who share a common place or experience -- requires changes in both the behaviors of large numbers of individuals and in the conditions that affect their health. Although community members are best positioned to determine their concerns and strategies, other partners can help with technical support, and in obtaining financial and other needed resources. In this section, we recommend adjusting the related roles and responsibilities of community partnerships, support organizations, and grantmakers. The aim is to build the capacity of community members to address what matters to them. Our hope is that these ideas for a new "social contract" will stimulate dialogue and enhance collaboration among those committed to building healthier communities.
Contributor
Stephen B.Fawcett
Vincent T. Francisco
Adrienne Paine-Andrews
Jerry Schultz
Resources
Online Resources
The Community Health Assessment and Group Evaluation (CHANGE) Tool is a community health assessment and planning resource that helps local organizations identify health priorities, collect data, and develop action plans to create healthier environments. It supports evidence-based improvements in areas such as nutrition, physical activity, chronic disease prevention, and tobacco control.
Emerging Action Principles for Designing and Planning Community Change is from Community Science and shares what science and practice have taught us about strengthening community.
The Healthy Community Checklist consists of a 40-item quick assessment of a community’s health environment related to promoting and supporting physical activity, healthy eating and weight, as well as tobacco-free lifestyles.
Independent Sector provides an excellent example of creating partnerships. It is a national coalition of foundations, corporate giving programs, and nonprofit organizations that joined together to strengthen the nonprofit sector. It sponsors initiatives and highlights research and policy news related to advancing the public good.
Tobacco-Related and Other Chronic Diseases Community Assessment is a Community Assessment tool designed for Healthy Community counties and their community health advisory councils. This process creates a foundation to guide the rest of the Healthy Communities process and identifies priorities for county work plans.
Print Resources
This Community Tool Box section is an adaptation of the following:
Fawcett, S., Francisco, V., Paine, A., & Schultz, J. (1999). Working Together for Healthier Communities: A Research-Based Memorandum of Collaboration. Public Health Reports, Supplement on Healthy Cities/Healthy Communities. Publisher: Place.
This report is based on lessons learned with an array of partners in communities, support organizations, and grantmaking institutions. For a summary of this work, see:
Fawcett, S. B., Francisco, V. T., Hyra, D., Paine-Andrews, A., Schultz, J. A., & Russos, S., et al. (2000). Building healthy communities. In A. Tarlov & R. St. Peter (Eds.), The society and population health reader: A state and community perspective (pp. 75-93). New York: New Press.
Fawcett, S., Lewis, R., Paine, A., Francisco, V.., Richter, K., Williams, E., & Copple, B. (1997). Evaluating community coalitions for the prevention of substance abuse: The case of Project Freedom. Health Education and Behavior, 24 (6), 812-828.
Fawcett, S.B., Paine-Andrews, A., Fancisco, V.T., Schultz, J.A., Richter, K.P, Berkley-Patton, J., Fisher, J., Lewis, R.K., Lopez, C.M., Russos, S., Williams, E.L., Harris, K.J., & Evensen, P. (2001). Evaluating community initiatives for health and development. In I. Rootman, D. McQueen, et al. (Eds.), Evaluating health promotion approaches. (pp. 241-277). Copenhagen, Denmark: World Health Organization - Europe.
Fawcett, S., Sterling, T., Paine, A., Harris, K., Francisco, V., Richter, K., Lewis, R., & Schmid, T. (1995). Evaluating community efforts to prevent cardiovascular diseases. Atlanta, GA: U. S. Centers for Disease Control and Prevention, National Center for Chronic Disease Prevention and Health Promotion.
Francisco, V., Paine, A., & Fawcett, S. (1993). A methodology for monitoring and evaluating community coalitions. Health Education Research: Theory and Practice, 8 (3), 403-416.
___You know that building healthier communities means the process of people working together to address issues that matter to them.
___You understand the differences between the three types of community change.
___You can list the 7 key components of community change.
- Clear vision and mission
- Action planning
- Leadership
- Resources for community organizers
- Documentation and feedback
- Technical assistance
- Making outcomes matter
___You can distinguish between state and community partnerships, support and intermediary organizations, and funders using your knowledge of their characteristics and functions.
___You have developed a timeline based on the steps in collaboration.
Contributor
Stephen B.Fawcett
Vincent T.Francisco
Adrienne Paine-Andrews
Jerry Schultz
Tool #1: Working Together - Roles and Responsibilities in Community Work
| Partner Task | Community Parnership | Support Organizations | Funders |
|---|---|---|---|
| Develop the vision, mission and objectives |
Develop a vision Select broad purpose and goals |
Frame their objectives; identify community-level indicators |
Help applicants find appropriate funders Offer long term support Offer less categorical, and most holistic investments |
| Develop an action plan |
Identify specific changes Develop an inclusive planning process Organize committees for each objective |
Suggest action steps Make partnerships aware of "promising practices" Support early stages of action planning |
Help community groups get in touch with others in the field Assist in bringing about broader changes |
| Develop and support leadership |
Enhance and support leadership Develop new leaders |
Skill training using personal assistance, support groups and resources | Acquire resources for leadership development |
| Document and feedback |
Gather information on changes Obtain other information Review data |
Establish and maintain a system of documentation focused on tracking intermediate outcomes related to the mission |
Request information on progress made Work with other grantmakers to accept the same data Document their own contributions |
| Secure and provide technical assistance |
Look for help from organizations with specialized knowledge Develop their own technical assistance capacity |
Provide assistance in implementing and documenting their work Provide training materials and/or workshops |
Fund support organizations Foster relationships between support organizations and community partnerships |
| Secure and provide financial resources | Provide quantitative and qualitative information on community investments | Assist documenters in analyzing, interpreting and communicating the data |
Request long-term, comprehensive proposals Broker connections with other funders |
| Make outcomes matter | Submit to an annual status report | Assist documenters in analyzing, interpreting, and communicating data |
Renewal based on evidence of progress Bonus grants Outcome dividends |
Tool #2: Strategic Partnership Development
Strategic Partnership Development: Achieving Collaborative Advantage in Public Health by the Kansas Health Institute. This toolkit helps public health leaders build strong partnerships by offering practical tools to overcome challenges and leverage the benefits of collaboration.
Contributor
Stephen B.Fawcett
Vincent T.Francisco
Adrienne Paine-Andrews
Jerry Schultz

What is community organization?
Community organization is the process of people coming together to address issues that matter to them. Community members developing plans for how the city can be a place where all its children do well. Neighbors joining in protests to stop drugs and violence in their community. Members of faith communities working together to build affordable housing. These are all examples of community organization efforts.
What are the types of communities that organize?
Community organization can happen in the variety of contexts that define "community."
Shared place
People come together who share a common geographic place such as a neighborhood, city, or town. For example, local residents might come together to address neighborhood concerns such as safety, housing, or basic services. Problem solving through community-based organizations (CBOs), neighborhood associations, and tenants' organizations are common forms of place-based practice.
Shared experience
Community organizing also occurs among people who share an experience, such as a shared workplace or shared experience with disabilities or health disparities. Those who share a common identity may organize around issues, such as discrimination, that are barriers to achieving common goals.
Shared interest
Organizing frequently occurs among those who have concerns about the same issues such as jobs, housing, child well-being, or education.
What are some models of practice in community organization?
Should community organization be about collaboration among people sharing common interests or confrontation with those in power? This is a false dichotomy that ignores the context of the work. Several models of practice emerged in various contexts of community organization work (Rothman, 1995).
Social planning
Social planning uses information and analysis to address substantive community issues such as education, child development, or environmental health. For example, planning councils or task forces engage (usually) professionals in setting goals and objectives, coordinating efforts, and reviewing goal attainment.
Social planning might occur in a context of either consensus or conflict about goals and means. For example, information about high rates of pregnancies among adolescents, and factors that contribute to them, may help communities focus on the goal of preventing pregnancies among adolescents, and even decisions about using controversial means such as sexuality education and enhanced access to contraceptives. Use of social planning helps build agreement on common results.
Social action
Social action involves efforts to increase the power and resources of people experiencing economic barriers or limited access to power. For example, advocacy organizations, such as those for disability rights or tobacco control, often use social action approaches. They might arrange disruptive events -- including lawsuits, sit-ins, or boycotts -- to draw attention and focus to their concerns by those in power.
Organizers create events, such as a protest or strike, that those in positions of power (such as employers) can avoid or stop by coming to an agreement. For example, people with disabilities might stop picketing a business when it modifies policies that discriminate against people with disabilities. Or, a tobacco company might avoid a lawsuit by tobacco control advocates by eliminating advertising directed at minors. Social action tactics are used in lots of situations involving conflicting interests and imbalance in power; they usually take place when conventional negotiations aren't working.
Locality development
Locality development is another way to get people to work together. It is the process of reaching group consensus about common concerns and collaborating in problem solving. For example, local residents in urban neighborhoods or rural communities may cooperate in defining local issues, such as access to job opportunities or better education, and in taking action to address the concerns.
Community partnerships or coalitions
There are many hybrid models that combine elements of the three approaches. For example, community partnerships or coalitions combine elements of social planning and locality development when people who share common concerns, such as child well-being or substance use, come together to address them. The goal of many coalitions is to change community conditions -- specific programs, policies, and practices -- that protect against or reduce risk for these concerns. These models, and their variations, may be implemented at local, state, regional, and even broader levels.
What are some lessons learned about community organization and change?
The following summaries come from lessons learned from various experiences with community organization practice. The lessons are organized by broad topics related to the work of community organization and change.
The lessons come through experience within:
- Understanding (and affecting) community context
- Community planning
- Community action and mobilization
- Understanding (and addressing) opposition and resistance
- Intervention and maintenance of efforts
- Promoting community change
- Influencing systems (or broader) change
- Achieving community-level improvements
Understanding (and affecting) community context
High-profile commissions and reports create conditions for experimentation and optimism about public problem solving.
For example, during the 1960s, the U.S. President's Commission on Juvenile Delinquency helped spawn innovative efforts such as those of Mobilization for Youth in New York City. Similarly, in the early 1990s, a national-level task force on infant mortality helped launch a multi-site demonstration program known as Healthy Start. High-profile studies such as this help set the public agenda by highlighting what should be addressed and how. Prominent reports frame the dominant explanations for societal problems. For example, a report could focus attention on poverty as a "root cause" of many societal problems or infant mortality as a pressing issue. It might also feature a promising alternative solution, such as equal access to health care or legal assistance, as an innovative way to address social problems.
You might need to use more than one model of community organization practice to fit the variety of contexts in which community work is done.
For example, social planning or locality development strategies may fit a context of consensus about common purpose such as working together to reduce violence. By contrast, the strategy of social action, with its disruptive activity and related conflict, may be more appropriate in a context of conflicting interests, such as organizing for decent wages or safe conditions in the workplace.
Cross-cutting issues are good contexts for community organization practice.
Some community issues, for example, neighborhood safety or substance use, affect the majority of people who share a common place. They also offer a solid basis around which a critical mass of local people can work together. When community organization efforts involve people from diverse backgrounds of income and power -- such as educational or public health improvements that affect people across social class -- substantive change is a lot more likely to happen.
Community organization can't always be separated from politics or controversy.
Consider the case of people coming together in a rural community to address issues of toxic waste and environmental pollution. Public debate may focus on both the economic interests of affected businesses, and the health concerns of local residents. It's typical that when two parties are on opposite sides of an issue, neither will get everything they want. Inevitably, a resolution is going to involve politics: the art of reconciling or balancing competing interests.
People experiencing poverty can make substantial gains (or losses) during periods of tumultuous change, and related realignment of political parties.
Would there have been a Civil Rights Act of 1964 without rioting and a realignment of the Democratic Party? Political parties want to avoid mass protest or any unorganized behavior if it's at all possible, by changing (or appearing to change) policies, programs, and practices related to voiced concerns. Since mass protest is something those in power try to avoid, it's an important means by which people experiencing poverty -- with otherwise limited resources -- can achieve power and influence.
Strategies used in community organization should match the times.
In times of turmoil, organizing protests and strikes by the people affected by the issues can yield maximum gains. By contrast, in the long times between periods of disruptive actions, community organization might use less conflict-oriented approaches, such as locality development or collaborative partnerships, to define and pursue common purposes.
Mass protest and grassroots community organization can work together.
When public protests and other forms of disruption increase, so do the grassroots organizations that address prevailing issues. For example, protests regarding pro-life (anti-abortion) interests were associated with increases in local organizations supporting this and other related causes. When public concern declines, so does organizing at the grassroots. Although protest nourishes organization, the reverse does not hold. Organization doesn't produce protest -- it may even retard it (as when agencies may avoid controversy to protect their funding).
Community organizations form when people are ready to be organized.
Although organizations may exist to promote interest in an issue, such as child hunger, little will happen until a significant number of people care about the issue and feel that their actions can make a difference. A big challenge is figuring out when your issue matters to enough people who share a common place or experience, so they can be organized around the issue.
Institutions that want to avoid conflict and controversy may be a difficult base for community organization work.
Consider the case of a school-community initiative to prevent pregnancies among adolescents or HIV. Although schools are well positioned to deliver information and health services to young people, school officials often oppose providing sexuality education or enhanced access to contraceptives for those who choose to be sexually active. So, human service agencies and educational institutions that rely on public funding may be bad choices for lead agencies in community organization efforts that are likely to draw opposition.
Community planning
Societal and community problems are evidence that institutions are not functioning for people.
Much of the framing of societal problems in the 1980s and 1990s focused on the personal attributes of those immediately affected. For example, stated "causes" of high rates of youth crime may highlight the values and behavior of young people and their families such as "poor anger control" or "bad parenting." Such analyses rarely emphasize the contribution of broader environmental conditions, such as availability of jobs or chronic stresses associated with low income, and the institutions responsible for them. In addition to individual responsibility, public institutions -- such as schools, business, religious organizations, and government -- should be held accountable for widespread problems in living.
It's essential to set realistic goals for community organization efforts.
Community-based initiatives often overpromise, particularly with grantmakers. Setting unrealistic objectives -- for example, to reduce academic (school) failure by 50 percent in the next two years -- sets the group up for perceived failure. Organizations should carefully assess the feasibility of their proposed aims.
If we set only modest goals, we will probably achieve less.
Although goals ought to be achievable, they should also be challenging. Objectives can be overly modest. For example, an overly modest goal might be to reduce rates of school failure (now at 80 percent) by 10 percent within three years. Insufficiently challenging objectives may not bring forth the necessary effort, resources, and degree of change needed to address the community's concern.
Social planning can engage experts (and local people) in helping address societal problems, particularly when there is consensus on the issue.
We can advance locally valued purposes by engaging technical experts and local people in defining problems and solutions. Outside experts, such as university-based researchers or public officials, can assist local people in obtaining and interpreting data, facilitating the process of setting priorities, and identifying promising alternatives. But planning can go beyond the traditional roles of facilitating coordination and communication among agencies to identifying environmental conditions to be changed.
Locality development or self-help efforts can also assist in addressing community issues.
Local people have the experiential knowledge to come together to define local issues, such as neighborhood safety or jobs, and take action in addressing them. Such self-help efforts have their roots in the settlement house movement in urban neighborhoods. They are guided by respect for the autonomy of local people to decide (and act on) what matters to them.
Local control can hinder collaboration at broader levels of planning.
Planning at higher levels than the neighborhood, city, or town may be necessary to address the broader conditions that affect community organization efforts. For example, the growing concentration of poverty in the urban core, a result of regional planning decisions and other broader policies, is a structural issue that affects community development efforts within urban neighborhoods. Although it's desirable for community building, strong local control may hinder the broader planning and coordination necessary to address local issues.
Community action and mobilization
Each individual has the capacity for self-determination, self-help, and improvement.
A basic assumption of community organization is that people most affected by local concerns, including those labeled as "clients" of agency services, can do something about them. This "strengths" perspective highlights people's assets and abilities, not their deficits and limitations. While it acknowledges personal and community competence, it also recognizes the importance of environmental supports and barriers that affect engagement in community life. For self-determination efforts to be successful, we must create opportunities for working together, and increase the positive consequences of community action.
You can't do it by yourself.
Addressing what matters to local people -- good health, education, and jobs, for example -- is beyond any one of us. The idea of "ecology" -- interactions among organisms and the environment -- helps us see community action as occurring within a web of relationships. Community life is enhanced when individual strengths are joined in common purpose -- an expression of the principle of interdependence. We are interconnected: each of us has a responsibility to make this a world good for all of us.
Strong leaders are present in even communities with very limited economic resources.
Authentic leaders -- those who enable constituents to see higher possibilities, and pursue them together -- are among us. Yet, they may not always be acknowledged by those in authority. When doing community organizing in public housing in communities facing economic barriers, I found that a simple question helped in "discovering" local leaders: "Who do children go to when they are hurt and an adult isn't home?" Such questions help us discover the "servant leaders" among us: those who "lead" by addressing the interests of their "followers."
Community practitioners should never get used to the terrible conditions they see in their community work.
Those doing community work, particularly in communities with limited economic resources, are exposed to horrible things: children in uncaring and unhealthy environments; adults without adequate food, clothing, and shelter; and other conditions essential for a decent life. Practitioners should avoid becoming desensitized about how they feel about what they see and hear. Disclosing experiences and feelings to colleagues is one way to help support each other. Community activists must also decide how to use those feelings -- such as anger about conditions in which some people live -- to energize and sustain their work.
People's beliefs and values enable them to stay committed.
To make a difference, those doing community work must be in it for the long haul. People's values, such as fairness or respect for the dignity of others, help sustain their efforts. For instance, a personal or family history of discrimination -- a common experience for many people from underrepresented racial and ethnic groups -- may incline us to embrace the value of social justice and to work for equality of opportunity.
The work of community organization is like that of a "secular church."
Faith communities and religious institutions help shape our beliefs about what is right and good, such as our responsibility to care for others. Community-based organizations, such as a coalition addressing homelessness or tenants' rights organization, call us to serve the common good -- things beyond ourselves. As such, they enable us to devote our lives to higher purposes, while working in this world.
Community practitioners have few opportunities to reflect on the work.
Those doing the work of community building are often consumed by its demands. For example, leaders and staff of community-based organizations rarely take time to consider the lessons learned about community action, barriers and resources, or other features of their work. Personal reflection journals and periodic group retreats help leaders and groups to reflect on and review the initial purposes and recent directions of their organizations. As such, they promote "praxis" -- the joining of understanding (theory) and action (practice).
Responding to events and opportunities to build community often takes us beyond what we know.
Community practice is largely an art form. Effective intervention is shaped more by trial and error than by tested general statements about the conditions under which specified interventions (the independent variable) affect desired behavior and outcomes (the dependent variables). Yet, attention to the conditions that matter to local people -- crime, substance use, and poverty, for example -- cannot wait for the findings of research trials. We must be decisive in the face of uncertainty, even when the scientific evidence for a chosen course of action is inadequate.
Understanding (and addressing) opposition and resistance
Societal problems sometimes serve the interests of those in power.
For example, a regulatory policy that permits environmental polluters to go unpunished serves the economic interests of businesses that pollute, and those elected and appointed officials who may benefit from campaign contributions or bribes. Similarly, the existence of drugs and violence may indirectly benefit elected officials since they often gain public support when they rant against perpetrators of drugs and violence. When those in authority oppose community action efforts (or ignore appeals for substantive intervention), there may be a disconnect between the public interest (common good) and the private interests of those with disproportionate influence.
Racial and ethnic tension and controversies have disrupted and destroyed many community organization efforts.
Race and ethnic differences matter in this work. For instance, most African Americans share a common history of discrimination based on race, such as being followed more closely in a store or being ignored by cabs in a city. When you are part of an underrepresented racial or ethnic group, people may assume they can think and speak for you, even if they have given no evidence that they care about you. Accordingly, understandable distrust of the "other" (the dominant culture) may breed conflict that disrupts reciprocity and collaboration among people of different races and cultures.
Social action tactics, such as disruptive protest, have many detractors.
Participating in (or supporting) protest can be dangerous, especially for those who remain in the community. For example, following a school boycott launched by residents of a public housing community facing economic barriers, it was my friend Myrtle Carter, a mother receiving public assistance and visible leader, who was subjected to police harassment. She was arrested and jailed for a minor parking violation while we outside organizers who were also part of the effort experienced only small inconveniences. Activists using protest tactics should expect those in power to retaliate, even by establishing criminal penalties for particularly effective disruptive actions such as strikes.
Less in-your-face social action approaches can produce a strong political base from which to make change.
For example, the Industrial Areas Foundation (IAF) appeared to be relatively effective in attracting support (and avoiding opposition) for their causes. Consistent with the "I Ching" and other traditions of Eastern philosophy, less direct or forceful actions may be less likely to beget opposition and adverse reaction.
Opposition and resistance may come in many forms.
An analysis of the advocacy literature suggests different ways in which change efforts might be blunted. These include deflecting attention from the issue, delaying a response, denying the problem or request, discounting the problem or the group, deceiving the public, dividing and conquering the organization, appeasing leadership with short-term gains, discrediting group members, or destroying the group with slur campaigns through the media. Skilled practitioners can help group members recognize (and avoid or counteract) sources and modes of opposition.
Community organizations may respond to opposition with appropriate counteractions.
Consider the case of local public assistance officials (the opposition) who discount claims of a disability rights group that people with disabilities are being denied assistance unfairly. To counteract this opposition, disability advocates might document the number and kinds of cases denied, and use media advocacy about the consequences of denying eligibility to arouse public concern. Depending on the nature and form of opposition, appropriate counteractions may include reframing the issues, turning negatives into positives, going public with tactics being used against the group, concentrating the organization's strength where the opposition is weaker, and knowing when to negotiate.
Opposition to change may be like an onion.
Advocates should expect multiple layers of opposition and resistance to community and system change. For example, community organizations working for better schools may face resistance initially from school board officials; later, from local principals; and still later, from teachers. Peel off one layer, and another form of resistance or opposition may be there to protect vested interests.
Intervention and maintenance of efforts
The strategy of community organization should fit the situation.
The broad and specific means of intervention should match the ends, and the context. For example, social planning -- using technical information often with the guidance of outside experts -- may assist in defining goals when people share common interests. Similarly, locality development -- featuring self-help efforts of local people -- may be appropriate for reducing a particular problem, such as substance use or neighborhood safety, around which there is widespread agreement. In contrast, social action -- with its disruptive tactics and related conflict -- may be needed in contexts of opposing interests such as in reducing discrimination or disparities in income or power.
Using multiple strategies usually has an advantage over any single strategy.
Some initiatives -- for instance, a campaign for school reform -- get stuck using one preferred means of action, such as collaborative planning or disruptive tactics, even when the goals or conditions shift. By invoking only one strategy, the organization's actions may be easier to ignore and the benefits of complementary approaches may go untapped. For example, the threat of disruptive tactics (social action) may make support for self-help efforts (locality development) more likely. Flexibility in strategy, and use of multiple means, may enhance community efforts and outcomes.
Being in two cultures promotes creativity.
Some community practitioners operate in more than one system of influence. For example, those who combine research and practice must respect the influences of both academic disciplines and members of community-based organizations. Being open to different audiences helps integrate disparate ideas, discover novel solutions, and transform practice.
The work of community organization takes time, and follow-through.
Mobilizing people for action requires substantial time and effort. Making the calls and personal contacts to bring about a change in school policy, for example, cannot be done solely by volunteers. The stimulation and coordination of community work, like any other valued work, should be paid for. Without salaries for community mobilizers or organizers, follow-through on planned actions is rare.
External support may be both a necessity and a trap for community organizations.
Community organization efforts seldom are maintained without external resources. Yet, financial support usually has strings attached. For example, accepting money from foundations or the government may restrict advocacy efforts. Although often a necessity, outside resources may come at the price of compromising the group's goals or available means of action.
Community organizations often fade away.
When the issue that a community organization was formed around begins to fade, so may the organization. For example, a taxpayer rights organization may dissolve when its goal of blocking a particular public expenditure, such as a school bond issue, is resolved. Organizations that endure after the issue subsides may lose members unless they reinvent themselves to address other emerging issues.
Organizations need small wins.
"Small wins" are shorter-term, controllable opportunities that can make a tangible difference. For example, a good neighborhood organizer might work for improved trash pickup or more streetlights to provide (literally) visible benefits of group action. Without the small victories, community organizations won't retain current members -- or attract new ones.
Promoting community change
The central ideal of community organization practice is service.
Practitioners' interests should always be lower on the list than the interests of the people served. Yet, when disciplines, such as social welfare or public health, market training for "professionals" in the work of community organization, they risk creating professions in which the practitioners benefit more than the people served. Professions that certify people -- and not promising practices or demonstrably effective methods -- may emphasize the interests of professionals (or guild interests), and not those experiencing the problems.
Community organization must go beyond the process of bringing people together.
For some practitioners, dialogue among representatives of different groups is a sufficient "outcome" of community development efforts. Yet, local people who come together to address what matters to them are usually interested in going beyond talk, and on to action and achieving results. Community organization efforts should bring about tangible benefits such as community change, problem solving, and furthering social justice.
The primary need is not for individuals to adjust to their world, but for environments to change so people can attain their goals.
Much framing of societal problems focuses on the deficits of those most affected. For example, prominent labels for causes of academic failure might include "poor motivation" (of young people) or "poor monitoring" (by parents). Alternatively, analyses of academic failure might address such environmental conditions as "few opportunities to do academic work" (in schools) and "limited opportunities for employment" (following school). Community health and well-being are private and public matters, calling for both individual and social responsibility.
Community-based organizations can function as catalysts for change.
Effective community organizations transform the environment: they alter programs, policies, and practices related to the group's mission. For example, a disability rights organization might modify policies regarding employment discrimination against people with disabilities or establish new job training programs that accommodate people with different disabilities. In their role as catalysts for change, community organizations convene others, broker relationships, and leverage resources for shared purposes.
Influencing systems (or broader) change
The level(s) of intervention should reflect the multiple levels that contribute to the problem.
Consider the typical interventions for most societal problems. For example, job training to address unemployment or drug awareness programs to counter substance use are typical of initiatives trying to change the behavior of those with limited power who are closest to the "problem," for instance, adults with lower incomes (unemployment) or young people (substance use).
When used alone, service programs and targeted interventions for adults or young people at increased risk may deflect attention away from more root causes, such as poverty and the conditions of opportunity that affect behavior at a variety of levels. Resolution of many societal issues, such as crime or unemployment, requires changes in decisions made by corporate and political decisionmakers at levels higher than the local community.
Systems change does not occur simply by reporting felt needs to appointed or elected officials.
For those with higher economic or political status, simply expressing a concern may have influence on decisions that affect them. A variety of traditional means is available to such groups as a way of exerting influence; they include petitioning, lobbying, influencing the media, supporting political candidates, and voting in large numbers. These means are largely unavailable to those most affected by many societal problems, however, such as children and people experiencing poverty. Marginalized groups lack the resources to exert influence in conventional ways.
The great power of social movements is in communicating a different vision of the world.
Marginalized groups use the drama of protest -- and the conflict it provokes -- to display realities not widely regarded as important. For example, the media may cover a strike and related protests by farm workers or coal miners, and the violence it often evokes from owners, the police, or others in power. Media coverage helps convey the story of the conditions faced by the protesters, and the unfairness of the action (or inaction) of businesses or institutions that are targeted. The dramatic nature of protest and related conflict can help politicize voters who, through enhanced public support of the positions of marginalized groups, can exert influence on those in power.
Community organizations should seek changes within their power to manage.
Since ignoring is likely and retaliation is possible, small organizations with limited power should avoid seeking fundamental changes in the system. For example, a single grassroots organization in a neighborhood with limited economic resources may not be positioned to effect systems changes such as altering the priorities of grantmakers who support work in the community. But, small and scrappy organizations may succeed in bringing about community change when their bulkier counterparts do not.
Community and broader systems change can be brought about through collaboration.
Collaboration involves alliances among groups that share risks, resources, and responsibilities to achieve their common interests. For example, local community-based organizations interested in the well-being of children can link with each other to create local programs (e.g., mentoring), policies (e.g., flextime to be with children after school) and practices (e.g., adults caring for children not their own).
Additionally, broader partnerships with grantmakers, government agencies, and business councils can affect the conditions in which change occurs at the community level. An example is altering grantmaking programs to support collaborative work or promoting child-friendly business policies through industrial revenue bonds or new corporate policies. Collaborative partnerships help bring about community and system change when they link local people to resources and institutions at the multiple levels in which change should occur to address common interests.
Achieving community-level improvements
Societal problems often recur.
Consider the problem of gang violence that occurred after World War II and recurred in the 1990s. Broad social conditions -- wide income disparities, weak social ties, and related mistrust of others -- appear to affect the likelihood of societal problems such as increased death rates, infant mortality, and perhaps violence involving young people. Improvements achieved in one era may need to be reestablished by future generations that must again transform the environmental conditions that support the recurrence of societal problems.
Most community efforts "chip" away at the problem.
The majority of community interventions do not match the scale of the problem. For example, a community effort may prepare 10 people who are unemployed to compete for only one available job, or may create 100 jobs in a community with thousands of people who are unemployed. We often make small changes in a context that remains unchanged.
Real change is rare.
Significant improvements in community-level outcomes are highly unusual -- such as cases of reducing rates of pregnancies among adolescents or academic failure by 50 percent or more. Yet, in requests for grants, community-based organizations often promise (and grantmakers expect) statements of objectives that indicate significant improvements as a result of only modest investments over a short time. We should not perpetuate myths about what most interventions can actually accomplish.
Development of community leadership may be a positive byproduct of even a "failed" community effort.
Although an initiative may not produce statistically significant changes in community benchmarks or indicators, it may develop new leaders or build capacity to address new issues in the future. For instance, a public health initiative that produces only modest reductions in rates of pregnancies among adolescents may develop the capacity to produce changes that matter, such as four years later when the group switches its efforts from pregnancies among adolescents to child well-being.
Community documentation and evaluation must help us see what is actually achieved by community initiatives, including evidence of intermediate outcomes (e.g., community and system change) and other indicators of success or "failure" (i.e., community capacity over time and across issues).
Optimal health and development for all people may be beyond the capacity of what communities can achieve, but not beyond what they should seek.
Most community-based efforts, such as those to create healthy environments for all our children, will fall short of their objectives. Yet, justice requires that we create conditions in which all people can make the most of their different individual strengths and circumstances. Support for community initiatives should be guided by what we must do for current and future generations, not by what limited gains we have made in the past.
In Summary
The fundamental purpose of community organization -- to help discover and enable people's shared goals -- is informed by values, knowledge, and experience. This section outlined lessons learned from the experiences of an earlier generation of community organization practitioners (each with an average of over 40 years of experience). The insights were organized under broad themes of community organization practice.
Community organization often has a bottom-up or grassroots quality: people with relatively little power coming together at the local level to address issues that matter to them. For example, grassroots efforts may involve planning by members of a neighborhood association, protests by a tenants' organization, or self-help efforts of families facing economic barriers to build local housing.
Yet, community organization may also function as a top-down strategy, such as when elected or appointed officials -- or others in power -- join allies in advancing policies or resource allocations that serve their interests. Bottom-up and top-down approaches to community organization may work in conflict, such as when appointed officials conspire to make voter registration of emerging underrepresented groups more difficult. Top-down and bottom-up efforts may also work in concert, as when grassroots mobilization, such as letter writing or public demonstrations, helps support policy changes advanced by cooperative elected or appointed officials working at broader levels.
Community organization strategies may be used to serve -- or hinder -- the values and aims of particular interest groups. Consider the issue of abortion: those organizing under the pro-choice banner may use protest tactics to advance policies and practices that further individual freedom (a woman's "right" to choose whether to have an abortion). Alternatively, those working on the pro-life side may organize to seek changes consistent with the value of security and survival (an unborn child's "right" to life). Depending on our values and interests, we may support or denounce the use of similar disruptive tactics by proponents or those who hold opposing perspectives on the issue.
What is the relationship between personal values and qualities -- and the experiences and environments that shaped them -- and the work of community organization and change? Personal background, such as a basic spirituality or a history of discrimination associated with underrepresented racial or ethnic group status, can predispose a practitioner to support particular values, such as social justice or equality, consistent with the work of community organization.
What qualities and behaviors of community organizers, such as respect for others and willingness to listen, help bring people together? Many of these attributes and behaviors -- including clarity of vision, capacity to support and encourage, and tolerance of ambiguity -- are similar to those of other leaders.
How do we cultivate such natural leaders, and nurture and support their work in bringing people together? Further research may help clarify the relationship between personal qualities and behaviors, such as those of the "servant" or "servant leader," the broader environment that nurtures or hinders them, and the outcomes of community organization efforts.
Finally, leadership in community work may begin with a few good questions:
- What is desired now, in this place, by these people?
- What is success?
- Under what conditions is improvement possible?
- How can we establish and sustain conditions for effective community problem solving over time and across concerns?
- How would we know it?
Imagine a "living democracy" -- large numbers of people, in many different communities, engaged in dialogue about shared concerns and collective action toward improvement. Perhaps these lessons -- inspired by reflections of an earlier generation of community organization practitioners -- can help us better understand and improve the essential work of democracy: people coming together to address issues that matter to them.
Contributor
Stephen B. Fawcett
Resources
Resources
Online Resources
Chapter 5: Theories in the "Introduction to Community Psychology" explains the role of theory in Community Psychology, the main foundational theories in the field, and how community psychologists use theory in their work.
Chapter 15: Community Organizing, Partnerships, and Coalitions in the "Introduction to Community Psychology" describes how and why communities organize, bottom-up and top-down approaches to community organizing, and the cycle of organizing.
The Lead Local organization focuses on building community power to drive structural changes and promote health equity, providing research, resources, and practical strategies to support communities in transforming local systems and conditions. Their Leading Locally: A Community Power-Building Approach to Structural Change report (pdf) explores how community power-building efforts across 16 diverse places in the United States can drive structural changes to advance equity, emphasizing strategies like grassroots organizing, policy advocacy, and coalition building to transform local conditions and systems. Their Story of Place: Community Power and Healthy Communities report (pdf) discusses how building community power can transform systems to advance health equity, emphasizing the role of local context, structural reforms, and inclusive decision-making to shape healthier communities.
Theory In Community Organization: People Have the Power! is a downloadable PowerPoint presentation that elaborates about theory in community organization.
Why Community Power is Fundamental to Advancing Racial and Health Equity is the first commentary in a three-part series from Lead Local that explores how community power building can drive health and racial equity more effectively than traditional engagement. It details practical examples of power-building campaigns and emphasizes the crucial role of external actors (e.g. researchers) in supporting these movements.
Print Resources
Adler, M. (1981). Six great ideas: truth, goodness, beauty, liberty, equality, justice: ideas we judge by, ideas we act on. New York, NY: Macmillan.
Alinsky, S. (1969). Reveille for radicals. Chicago: University of Chicago Press.
Altman, D., Balcazar, F., Fawcett, S. B., Seekins, T., & Young, J. (1994 ). Public health advocacy: Creating community change to improve health. Palo Alto, CA: Stanford Center for Research in Disease Prevention.
Balcazar, F., Seekins, T., Fawcett, S., & Hopkins, B. (1990). Empowering people with physical disabilities through advocacy skills train. American Journal of Community Psychology, 18, 281-295.
Bracht, N. (Ed.) (1990). Health promotion at the community level. Newbury Park, CA: Sage Publications.
Brager, G. & Specht, H. (1973). Community organizing. New York, NY: Columbia University Press.
Branch, T. (1988). Parting the waters: America in the King years 1954-63. New York, NY: Simon and Schuster.
Brown, M. (2006). Building powerful community organizations: A personal guide to creating groups that can solve problems and change the world. Arlington, MA: Long Haul Press.
Cobb, R., & Elder, C. (1972). Participation in American politics: The dynamics of agenda-building. Baltimore: The Johns Hopkins University Press.
Cook, T. & Campbell, D. (1979). Quasi-experimentation: Design and analysis issues for field settings. Chicago: Rand McNally.
Cox, F., Erlich, J., Rothman, J., & Tropman, J. (1987). Strategies of community organization: Macro practice. (4th ed.). Itasca, IL: F. E. Peacock Publishers, Inc.
Cuoto, R. (1990). Promoting health at the grass roots. Health Affairs, 9, 145-151.
Dass, R. & Gorman, P. (1985). How can I help? Stories and reflections on service. New York, NY: Alfred A. Knopf.
Dunham, A. (1963). Some principles of community development. International Review of Community Development, 11, 141-151.
Fawcett, S. (1991). Some values guiding community research and action. Journal of Applied Behavior Analysis, 24, 621-636.
Fawcett, S., Lewis, R., Paine, A., Francisco, V., Richter, K., Williams, E., & Copple, B. Evaluating community coalitions for the prevention of substance abuse: The case of Project Freedom. Health Education and Behavior.
Fawcett, S., Paine, A., Francisco, V., Vliet, M. (1993). Promoting health through community development. Promoting Health and Mental Health in Children, Youth, and Families (pp. 233-255). D. S. Glenwick & L. A. Jason (Eds.). New York, NY: Springer Publishing Company.
Fawcett, S., Paine, A., Francisco, V., Schultz, J., Richter, K., Lewis, R., Williams, E., Harris, K., Berkley, J., Fisher, J., & Lopez, C. (1995). Using empowerment theory in collaborative partnerships for community health and development. American Journal of Community Psychology, 23, 677 -697.
Fawcett, S., Paine, A., Francisco, V., Schultz, J., Richter, K., Berkley, J., Patton, J., Fisher, J., Lewis, R., Lopez, C., Russos, S., Williams, E., Harris, K., & Evensen, P. Evaluating community initiatives for health and development. In I. Rootman, D. McQueen, et al. (Eds.) Evaluating health promotion approaches. Copenhagen, Denmark: World Health Organization - Europe.
Fawcett, S., Seekins, T., & Silber, L. (1988). Low-income voter registration: A small-scale evaluation of an agency-based registration strategy. American Journal of Community Psychology, 16, 751-758.
Fawcett, S. (1999). Some lessons on community organization and change. In J. Rothman (Ed.). Reflections on Community Organization: Enduring Themes and Critical Issues. Itasca, Illinois: F. E. Peacock Publishers.
Fisher, R. (1987). Community organizing in historical perspective: A typology. In F. M. Cox, J. L. Erlich, J. Rothman, and J. E. Tropman. (pp. 387-397). Strategies of Community Intervention: Macro Practice. (4th ed.). Itasca, IL: F. E. Peacock Publishers, Inc.
Gardner, J. (1990) On leadership. New York, NY: Free Press.
Gaventa, J. (1980). Power and powerlessness: Quiescence and rebellion in an Appalachian valley. Chicago: University of Illinois Press.
Greenleaf, R. (1997). Servant leadership. New York, NY: Paulist Press.
Heifetz, R. (1994). Leadership without easy answers. Cambridge, MA: Belnap Press of Harvard University Press.
Himmelman, A. (1992). Communities working collaboratively for a change. (Monograph available from the author, 1406 West Lake, Suite 209, Minneapolis, MN 55408)
Jargowsky, P. (1997). Poverty and place: Ghettos, barrios, and the American city. New York, NY: Russell Sage Foundation.
Kingdon, J. (1995). (2nd Ed.). Agendas, alternatives, and public policies. Boston: Little, Brown.
Lappe, F. & Dubois, P. (1994). The quickening of America. San Francisco: Jossey-Bass.
Mathews, R.. & Fawcett, S. (1984). Building the capacities of job candidates through behavioral instruction. Journal of Community Psychology, 12, 123 -129.
Morris, A.. (1984). The origins of the civil rights movement. New York, NY: The Free Press.
Newstetter, W. (1947). The social intergroup work process. In Proceedings of the National Conference of Social Work. (pp. 205-217). New York, NY: Columbia University Press.
Paine, A., Francisco, V., & Fawcett, S. (1994). Assessing community health concerns and implementing a microgrants program for self-help initiatives. American Journal of Public Health, 84(2), 316-318.
Paine, A., Fawcett, S., Richter, K., Berkley J., Williams, E., & Lopez, C. Community coalitions to prevent adolescent substance abuse: The case of the "Project Freedom" replication initiative. Journal of Prevention and Intervention in the Community.
Paine, A., Harris, K., Fawcett, S., Richter, K., Lewis, R., Francisco, V., Johnston, J., Coen, S. Evaluating a statewide partnership for reducing risks for chronic diseases. Journal of Community Health.
Paine, A., Vincent, M., Fawcett, S., Campuzano, M., Harris, K., Lewis, R., Williams, E., & Fisher, J. (1996). Replicating a community initiative for preventing adolescent pregnancy: From South Carolina to Kansas. Family and Community Health, 19(1), 14-30.
Perlman, R. & Gurin, A. (1972). Community organization and social planning. New York, NY: John Wiley.
Piven, F. & Cloward, R. (1977). Poor people's movements: Why they succeed, how they fail. New York, NY Random House.
Rappaport, J., Swift, C., & Hess, R. (Eds.). (1984). Studies in empowerment: Steps toward understanding and action. New York, NY: Haworth.
Ross, M. (1955). Community organization: Theory and principles. New York, NY: Harper and Brothers.
Rothman, J. (Ed.). (1999). Reflections on community organization: Enduring themes and critical issues. Itasca, Illinois: F.E. Peacock Publishers.
Rothman, J., & Tropman, J. (1987). Models of community organization and macro practice perspectives: Their mixing and phasing. In Cox, F., Erlich, J., Rothman, J., & Tropman, E. (Eds.), Strategies of community organization: Macro practice (4th ed.) (pp. 3-26). Itasca, IL: F.E. Peacock Publishers.
Schriner, K., Fawcett, S. (1988). A community concerns method for local agenda setting. Journal of the Community Development Society, 19, 108-118.
Seekins, T. & Fawcett, S. (1987). Effects of a poverty clients' agenda on resource allocations by community decisionmakers. American Journal of Community Psychology, 15, 305-320.
Seekins, T., Maynard, S., & Fawcett, S. (1987). Understanding the policy process: Preventing and coping with community problems. Prevention in Human Services, 5 (2), 65-89.
Stull, D., & Schensul, J. (1987). Collaborative research and social change: Applied anthropology in action. Boulder, CO: Westview.
Suarez de Balcazar, Y., Bradford, B., & Fawcett, S. (1988). Common concerns of disabled Americans: Issues and options. Social Policy, 19 (2), 29-35.
Tax, S. (1952). Action anthropology. American Indigena, 12, 103-106.
Watzlawick, P., Weakland, J. H., & Fisch, R. (1974). Change: Principles of problem formation and problem resolution. New York, NY: Norton.
Weick, K. E. (1984). Small wins: Redefining the scale of social problems. American Psychologist, 39, 40-49.
Wilkinson, R. G. (1996). Unhealthy societies: The afflictions of inequality. London: Routledge.
World Health Organization. (1986). The Ottawa charter for health promotion. Health Promotion, 1, iii-v.
Yin, R. (1988). Case study research: Design and methods. Newbury Park, CA: Sage.
Zald, M. (1987). Organizations: Organizations as polities: An analysis of community organization agencies. In Cox, F., Erlich, J., Rothman, J., & Tropman, E. (pp. 243-254). Strategies of community organization: Macro practice. (4th ed.). Itasca, IL: F. E. Peacock Publishers, Inc.
You understand that success in community organization comes through experience with:
___Understanding (and affecting) community context
Practitioners must be able to both understand and create the conditions under which community organization efforts have the best chance for success.
___Community planning
Community planners need to help people agree on common goals and means for addressing them.
___Community action and mobilization
Community leaders and members must commit to act with and learn from each other in this hard work.
___Understanding (and addressing) opposition and resistance
To be effective, community activists must be able to defeat and counteract the efforts of those with different interests.
___Intervention and maintenance of efforts
Community practitioners must be able to implement multiple strategies and sustain local efforts.
___Promoting community change
Community leaders and members must be able to change programs, policies, and practices related to shared goals.
___Influencing systems (or broader) change
To enhance chances of success, community practitioners try to change the conditions under which local communities seek improvement.
___Achieving community-level improvements
To make broader indicators of success, community members must build leadership and affect change that is large enough and long enough to make a difference.
You know the characteristics that can define a "community"
___Shared geographic location
___Similar experiences
___Shared goal
You know the types of community organizations that can work together
___Neighborhoods
___Union Workers
___Farmers
___Religious Groups
___Ethnic Groups
___Elderly
___Disabled
You know the key points for community organization
___Plan
___Set goals and objectives
___Get assistance from within the community
___Take action
___Always follow-up and maintain
Contributor
Stephen B. Fawcett
Example: Tireless 'Ms. Jessie' Cultivates Next Generation of Neighborhood Leaders

Jessie Jefferson, 79, is developing a new generation of neighborhood leaders as a consultant and community organizer for a host of neighborhoods: Town Fork Creek, Oak Park, Vineyard, South Roundtop, Seven Oaks, Blue Valley, McCoy, Washington Wheatley, and Independence Plaza.
And she fights for them, arguing for commitments from city department heads and council members to carve out financial support for these neighborhood associations so they can do the work of preserving and growing community power. Read more.
Tool #1 Supporting the Work of Community Organization and Change
Understanding (and affecting) community context
Practitioners must be able to both understand and create the conditions under which community organization efforts have the best chance for success.
See these related sections of the Community Tool Box:
Community planning
Community planners need to help people agree on common goals and means for addressing them.
See these related sections of the Community Tool Box:
- Coalition Building
- Developing a Strategic Plan
- Developing an Organizational Structure, Staff, and Volunteers
- Facilitating the Problem-solving Process
- Participatory Approaches to Planning Community Interventions
- Identifying Strategies and Tactics for Reducing Risks
Community action and mobilization
Community leaders and members must commit to act with and learn from each other in this hard work.
See these related sections of the Community Tool Box:
- Understanding Broad Strategies for Improving Health and Community Development Issues
- Training for Conflict Resolution
- Promoting Coordination, Cooperative Agreements, and Collaborative Agreements Among Agencies
- Recognizing Allies
- Communicating Information to Funders for Support and Accountability
Understanding (and addressing) opposition and resistance
To be effective, community activists must be able to defeat and counteract the efforts of those with different interests.
See these related sections of the Community Tool Box:
- Identifying Opponents
- Encouraging Involvement of Potential Opponents as Well as Allies
- Overview of Opposition Attacks
- How to Respond to Opposition Attacks
Intervention and maintenance of efforts
Community practitioners must be able to implement multiple strategies and sustain local efforts.
See these related sections of the Community Tool Box:
- Developing Multisector Collaborations
- Some Methods for Evaluating Comprehensive Community Initiatives
- Maintaining Quality Performance
Promoting community change
Community leaders and members must be able to change programs, policies, and practices related to shared goals.
See these related sections of the Community Tool Box:
Our Model of Change conceptual pieces
- Communications to Promote Interest
- Encouraging Involvement in Community Work
- Understanding Social Marketing: Learning to Change People's Behavior
- Conducting a Social Marketing Campaign
Influencing systems (or broader) change
To enhance chances of success, community practitioners try to change the conditions under which local communities seek improvement.
See these related sections of the Community Tool Box:
- Conducting a Direct Action Campaign
- Media Advocacy
- Providing Feedback to Improve a Community Initiative
Achieving community-level improvements
To make broader indicators of success, community members must build leadership and affect change that is large enough and long enough to make a difference.
See these related sections of the Community Tool Box:
Contributor
Stephen B. Fawcett
-
What is action planning?
-
How does action planning help a community?
-
Why is action planning important?
-
When should you create an action plan?
-
What are the components of an action plan framework?
Have you had the motivation to mobilize your community to address a problem that affects the local population, but just not known how to begin? You might wonder: “How do I investigate the problem?”, “Whom do I involve in the strategies to address the problem?”, “How do I successfully facilitate a group of diverse representatives from a community to reach consensus about a common vision and the actions that will turn ideas into results?”
This tool has the answers to these and other important questions. It will prepare you to lead your community in action planning.
What is action planning?
The overall goal of action planning is to increase your community’s ability to work together to affect conditions and outcomes that matter to its residents—and to do so both over time and across issues of interest.
As your community works towards a broad vision of health for all, creating supportive conditions for change requires comprehensive efforts among diverse sectors of the community. These include health organizations, faith communities, schools, and businesses. Representatives of each sector come together to form a community coalition. Your community coalition can strive to influence systems changes—programs, policies, and practices that can enhance the community’s capacity to be a healthy environment.
A community coalition initiates its work by generating an action plan.
An action plan outlines what should happen to achieve the vision for a healthy community. Desirable changes and proposed activities (action steps), timelines, and assignment of accountability provide a detailed roadmap for collaborators to follow.
How does action planning help a community?
Regardless of the complexity of the problem at hand within your community, action planning helps you:
- Understand the community’s perception of both the issue at hand and its potential solutions
- Ensure inclusive and integrated participation across community sectors in the planning process
- Build consensus on what can and should be done based on the community’s unique assets and needs
- Specify concrete ways in which members of the community coalition can take action
The list above describes how an action plan helps a community’s sectors and residents within those sectors work together to achieve a common vision. This tool will address each item and provide guidance for your action planning work that lies ahead.
Why is action planning important?
Proper planning of any initiative is critical for yielding the best results or outcomes possible. An action plan, while a significant investment of time and energy, can be an effective tool that grounds all collaborators with a common purpose. Developing an action plan is a critical first step toward ensuring project success.
An action plan ensures that:
- No detail is overlooked
- Proposed action steps are feasible and/or realistic
- Collaborators follow through with their commitments
- Measurable activities are documented and evaluated
Overall, action planning is important because it provides a reference point with a detailed timeline and assignment of accountability for accomplishing tasks along the path to making a difference.
Research findings of the Center for Community Health and Development suggest that there are a number of factors that appear to have a positive effect on rates of community and system change—and one of those includes action planning:
- Analyzing Information About the Problem, Goals, and Factors Affecting Them
- Establishing Your Group's Vision and Mission
- Defining Organizational Structure and Operating Mechanisms
- Developing a Framework or Model of Change
- Developing and Using Strategic and Action Plans
- Arranging for Community Mobilizers
- Developing Leadership
- Implementing Effective Interventions
- Assuring Technical Assistance
- Documenting Progress and Using Feedback
- Making Outcomes Matter
- Sustaining the Work
When should you create an action plan?
Ideally, you should develop an action plan within the first six to twelve months of the start of an initiative or organization. Once an action plan is generated, it should be revisited frequently (e.g., as often as monthly but at least annually) so it can be modified to meet the changing needs of your community.
What are the components of an action plan framework?
While some issues may be universal (for example, mental health issues), each community will have different assets and barriers for improving conditions for its residents. Therefore, each community’s intervention strategy for influencing programs, policies, and practices will be unique. However, a series of steps—a framework—helps guide the process of community action and change within the context of a community’s unique needs.
If you approach the action planning process as a manageable series of steps, you can take charge and help your community coalition work through each one with confidence.
Determine what people and sectors of the community to involve
As you begin your action planning process, you will need to accomplish three things:
- Document the problem or issue with information and statistics
- Learn more about your community
- Involve community members
How do you go about accomplishing these steps?
Listen to the community about issues and options. Conduct focus groups and public forums to obtain information about perceived issues and solutions within the community.
The key pieces of information you should gather in each listening session or focus group include:
- The perceived problem or issue
- Perceived barriers or resistance to addressing the issue
- Resources for change
- Recommended solutions and alternatives
- Current and past initiatives to address the problem or issue
Gather data to document the problem. In addition to hearing the community perspective on problems or goals related to the issue at hand, it is important to document the issue using existing information sources.
- "What are the issues related to the problem/topic in your community?"
- "What are the consequences of these issues?"
- "Who is affected?"
- "How are they affected?"
- "Are these issues of widespread concern?"
While the information that you collect can answer the questions above, remember that it will also play a key role in helping you determine how effective your group was in addressing the problem. You will use these baseline data—data that document the extent of the problem prior to implementation of your initiative—for comparison with data that document the extent of the problem after implementation of your initiative.
Listed below are helpful data sources that you may want to investigate. Keep in mind that not all of them will be relevant to your particular issue or problem.
- State or county health department data
- State social services department data
- Hospital admission and discharge records
- Police records
- Chamber of commerce data
- Nonprofit service agency data
- School district data
- Information from your local reference librarian
- Data from specialized local, statewide, or national organizations
Also see federal data sources such as:
- The U.S. Centers for Disease Control and Prevention’s National Notifiable Diseases Surveillance System data
- National Center for Health Statistics data
- Census data
- Maternal and Child Health Bureau, HRSA, Title V Block Grant Information System
Become aware of local resources and past and current efforts: If current efforts targeting your issue exist, think of ways in which they can become more effective via support, advocacy, or other means. Consider the following:
- Do current efforts have a parallel vision?
- How many people are they serving?
- Do the services and programs meet local needs?
Particularly if pre-existing initiatives had a similar mission and failed, seek to understand why and apply those lessons learned to your action planning. You might gain valuable insight by talking with the agency or group with the failed initiative.
Involve key officials and grassroots leaders in a planning group: While you may easily identify key officials, service providers, or representatives from relevant agencies, extend the boundaries of your planning coalition to be as inclusive as possible. Remember that your planning group should reflect the diversity of the local community.
Your group might use interviews with both key officials and key grassroots leaders to answer the following questions:
- Who can make things happen on this issue?
- What individuals are in a position to create (or block!) change?
- What contacts within the initiative would be most successful in getting those key officials to become involved?
- What neighborhoods and ethnic and cultural communities are particularly affected by this issue?
- What individuals and groups make things happen in these neighborhoods?
- What contacts within the initiative would be most successful in involving members of these neighborhoods?
Convene a planning group
Once you identify and include interested participants for the planning group, publicize planning sessions to ensure that they are open to all group members. As facilitator, you should extend additional courtesies to planning group members, such as starting and ending meetings on time, using an agenda, and covering items in as little time as possible. Other responsibilities that you might have as a facilitator include:
Managing conflict. The richness of diverse views represented within your planning group may also lead to conflict among members. Group leaders may need to elevate discussions to a higher level on which there may be a basis for agreement. Leaders can also remind group members of the shared vision as a means of fostering discussion on common ground.
The Centers for Disease Control and Prevention's (CDC) Planned Approach to Community Health (PATCH) documentation includes suggestions for reaching consensus in group meetings:
- Avoid the “one best way” attitude, and opt for that which reflects the best collective judgment of the group
- Avoid “either/or” thinking; often the best solution combines several approaches
- A majority vote may not always be the best solution. When participants give and take, several viewpoints can be combined.
- Healthy conflict may actually help participants reach a consensus; do not end conflict prematurely.
- Problems are best solved when all participants try to communicate and listen.
Conflict resolution is the process of settling disagreements among group members. The CDC recommends trying one of four approaches to resolve conflicts about goals, plans, activities, or procedures:
- Avoidance: While this can be a temporary solution, particularly if a conflict does not seem important enough to discuss, be sure to reassess the problem at a later date.
- Accommodation: Use tact and discretion to ask participants to yield or conform to the positions of others.
- Compromise: When a consensus cannot be reached, compromise may be the only solution. With compromise, everyone both wins and gives up something.
- Collaboration: While this may be the best approach, reserve it for issues of greatest importance. Collaboration requires all group members to acknowledge the conflict, consider many possible solutions and the consequences of each, and select the alternatives that best meet the needs of the group.
Creating a supportive context for planning and action. Several aspects of your community group can influence the element of support in the planning environment. They are: leadership, size and structure, organization, and diversity and integration.
- Leadership – Although a single person may accept overall responsibility, effective organizations usually have a number of leaders who work with constituents to fulfill the group’s mission. Leaders should have a clear vision and the capacity for listening and relating to others in the group.
- Size and Structure – A maximum group size of 15 is recommended. If this seems prohibitive given the number of people interested in participation, you can also structure smaller groups such as “task forces” for specific functions within the action plan.
- Organization – If your planning group or surrounding community is particularly large, you may want to allocate work to subcommittees for each sector of the community to be involved (e.g., health organizations, businesses, schools). If your planning group or surrounding community is relatively small, the group might work as a whole to accomplish action planning.
- Diversity and Integration – Include all types of participants: people in positions of authority, grassroots leaders, and local residents with experience.
Offering ongoing encouragement. Throughout the planning process, let group members know when they are doing a good job. Positive feedback is very important—especially when people are volunteering their time and energy.
If you find it challenging or intimidating to facilitate planning sessions in which diverse ideas and opinions are expressed, try applying some of the information below to your situation. Having a “plan” for effective facilitation will help you yield the most positive outcomes and best ideas from your planning meetings.
Tips for Group Facilitation
The Centers for Disease Control and Prevention’s (CDC) Planned Approach to Community Health (PATCH) documentation offers the following suggestions for facilitating meetings:
- Create an environment conducive to communication by seating participants around small tables or in semicircles.
- Make participation an expectation; ask questions frequently and use open-ended questions to encourage thought and participation.
- Create opportunities for participants to work in teams.
- Give small assignments in advance, and ask participants to come to meetings prepared to share their work.
- Encourage participants to evaluate the group’s working dynamic and offer solutions for improving interaction if needed.
- Talk with quiet participants during breaks, and help them express their ideas and share their thoughts with the group.
- Use flip charts, presentation slides, or shared digital displays to record comments, but face participants while writing or ask someone else to do it.
- Suggest the “next step” if a meeting seems to be stagnating.
- Walk around to gain attention, but look directly at participants.
- Expect to make some mistakes! Acknowledge them, correct them, and move on.
Lead brainstorming sessions. Brainstorming is a problem-solving technique that encourages all members of a group to contribute ideas. You may find this technique of idea generation particularly helpful in the early phases of action planning. There are three common approaches to brainstorming:
- Freewheeling: Participants randomly call out suggestions, which are then recorded on a flip chart. Some group members may dominate in this setting.
- Round robin: Each member is called upon for a suggestion in turn, and ideas are recorded on a flip chart. This is a more organized approach and prevents domination of the session by only a few individuals.
- Slip: Each member submits anonymous suggestions on a slip of paper, and ideas are then recorded on a flip chart.
CDC suggests that a group facilitator follow these guidelines for a brainstorming meeting:
- Explain all rules at the beginning of the session. Those are:
- No critical remarks allowed; evaluation comes later
- Give the thought only; explanation comes later
- Give only one idea at a time
- Adding to or improving on someone else’s idea is appropriate
- Give all participants a chance to share ideas.
- Ask one or two people to record ideas.
- Keep a lively tempo to the process.
- Praise the quantity versus quality of ideas.
Convening and facilitating a planning group for a common vision, mission, or purpose can be challenging yet rewarding. Participation of diverse individuals can require skilled facilitation. However, you can successfully facilitate a group meeting by applying the guidelines presented above. The more meetings you lead throughout the action planning process, the more confident you will become!
Develop an action plan to address proposed changes
Your planning meetings, brainstorming sessions, and other group discussions will yield an extensive compilation of great ideas (and maybe some that are not so great!).
What do you do with all of that information? How do you sort through the pile of rocks to find the gems?
First, you will need to distill the many ideas and voices into a common vision and mission. Next, you will need to refine the relevant ideas into objectives with corresponding strategies and actions.
As you distill the large number of ideas into a common vision, the VMOSA process (vision, mission, objectives, strategies, and action) will help your planning group develop a blueprint for moving from dreams to actions to positive outcomes for your community. VMOSA gives both direction and structure to your initiative. The five components of VMOSA should be completed in the order in which they are presented here.
Vision
Your planning group needs a vision statement to serve as a unifying statement for your effort, help communicate your goals and attract participants, remind participants of the desired outcome, and guide important decisions. The vision statement should be a few short phrases or a sentence. Catchy phrases such as "Healthy teens," "Safe streets, safe neighborhoods," and "Education for all" illustrate the common characteristics of a vision statement.
Craft a vision statement that is:
- Understood and shared by members of the community
- Broad enough to include a diverse variety of perspectives
- Inspiring and uplifting
- Easy to communicate
Mission
Your planning group’s mission statement will be more specific than the vision. As the next step in the action planning process, it expresses the "what and how" of your effort, describing what your group is going to do to make your vision a reality. An example of a mission statement: "Our mission is to develop a safe and healthy neighborhood through collaborative planning, community action, and policy advocacy."
While your vision statement inspires people to dream, your mission statement should inspire them to action.
Create your mission statement to be:
- Concise
- Outcome-oriented
- Inclusive
Objectives
Objectives are the specific, measurable steps that will help you achieve your mission. Develop objectives that are SMART+C: specific, measurable, achievable (eventually), relevant to your mission, and timed (with a date for completion). The +C reminds you to add another important quality to your goals: make them challenging!
Strategies
Strategies explain how your group will reach its objectives.
Broad strategies for change include:
- Advocacy
- Coalition building
- Community development
- Education
- Networking
- Policy or legislative change.
The big picture
Charting a logical pathway for community and system change: A key question to ask as your group formulates strategies is, “What combination of changes in programs, policies, and practices are necessary to make a difference with the mission of promoting health for all?” Your group will want to take inventory of potential community and system changes for addressing the problem or issue of interest. To do this, sort your “inventory” of ideas and objectives generated via the planning group into five specific strategy categories:
- Providing information and enhancing skills
- Altering incentives and disincentives
- Modifying access, barriers, and opportunities
- Enhancing services and support
- Modifying policies and practices
To facilitate the process of thinking about how ideas fit most logically together, you may want to draft a one-page flowchart that forms pathways leading logically to widespread behavior change and elimination or reduction of the problem to be addressed. You might want to think of this flowchart as a way to double-check for any gaps that may remain despite your extensive planning and discussion up to this point. Furthermore, as you look at the pathways and linkages along the way to change, the visual representation may prompt you to think of potential resources and barriers for accomplishing objectives. These noted resources and barriers will be applied to the development of action steps—the last piece of your action plan (to be discussed in the next section).
Determining strategies within your community’s context
Once your planning group has a clear vision and mission and has chosen community and system changes to be sought, you will have the foundation for making informed decisions regarding types of strategies to implement. The information below is a guide to talking through the development of strategies as they relate to the priorities and desired changes in the context of your community.
When developing strategies to accompany your objectives, consider the following factors:
- Population levels to be affected
- Universal versus targeted outreach
- Personal and environmental factors
- Which community sectors can benefit from and contribute to efforts
- Behavioral strategies to be used.
The levels to be targeted (individuals vs. families and kinship groups vs. organizations and sectors vs. broader systems).
Whether the strategy will be universal (e.g., include all of those who may be at risk or may benefit) or targeted (e.g., targets those who may be at greater risk for the problem):
- Universal example: providing age-appropriate information to men in the community about prostate cancer screening.
- Targeted example: providing additional prostate cancer screening information to men with a family history of prostate cancer.
The personal and environmental factors to be addressed by the initiative:
- Personal factors: knowledge, beliefs, skills, education and training, experience, cultural norms and practices, socioeconomic status, cognitive or physical abilities, gender, age.
- Environmental factors: social support, available resources and services, barriers (including financial, physical, and communication), social approval, policies, environmental hazards, living conditions, poverty.
- People or groups experiencing the issue - those who may be at particular risk for the issue and those whose actions (or inaction) contribute to the problem.
- People or groups who can contribute to change - those who may be in a position to (and have a responsibility to) contribute to the solution or initiative (includes people or groups experiencing the issue)
- Community sectors through which people or groups who can contribute to change can be reached or involved
The behavior change strategies to be used. Approaches may include:
- Providing information and enhancing skills - Delivery of information or training through media, courses, workshops, webinars, or other modes.
- Enhancing services and supports - Increasing, improving, or expanding assistance or social or technical supports related to the identified goal(s). This could include expanding or changing components or offerings such as mental health or social services, or expanding hours or adding new locations.
- Modifying access, barriers, and opportunities - Changes in the environment (e.g., changes in office hours, reduced entry fees, changes to the built environment such as trails or lighting) that reduce barriers and improve access.
- Changing consequences - Changing the incentives or disincentives for outcomes. This might include public recognition or tax breaks. This might also take the form of implementation of policies that call for consequences to actions, such as a tax on certain products.
- Modifying policies and broader systems - Changing existing policies or regulations at the organizational or governmental level to promote desired behaviors/outcomes. This might take the form of written regulations or organizational policies.
For each strategy, consider what programs, policies, and/or practices should be created or modified. Make a list, keeping in mind how they work together to address the problem or goal. And finally, review your planning group’s strategies for:
- Consistency with the overall vision, mission, and objectives
- Fit with the resources and opportunities available
- Anticipated resistance and barriers and how they can be minimized
- Whether those who are affected will actually be reached
- Whether those who can contribute will be involved
Building consensus on proposed strategies for change
Once you think that the strategies are finalized and in place, you will want to build consensus on proposed changes within your planning group. Keeping in mind the fact that multiple sectors of the community are represented in the planning group, you should complete two types of review:
- Review proposed changes for each sector
- Taken together, do these proposed changes maximize this sector’s contribution to the mission?
- What other changes in programs, policies, or practices could or should be made in this sector?
- Review proposed changes for all sectors taken together
- Would all changes, taken together, be sufficient to reduce the problem?
- What other changes in programs, policies, or practices could or should be made within the community or system?
- Furthermore, to help attract and preserve commitments on behalf of the sectors represented in your planning group, you should build consensus on the changes to be sought by asking:
- “Is this proposed change important to the mission?”
- “Is this proposed change feasible?”
You can even put these two questions into a survey format and create a table for planning group members to respond to. Before administering the survey, set criteria for which sought changes will be kept or eliminated with a ranking score system.
You can see below that a sample ranking system ranging from ‘1’ for “Not at All [Important or Feasible]” to ‘5’ for “Very [Important or Feasible]” has been used. We suggest that you set criteria of an average value of 3 or higher for a proposed change to be retained.
| Proposed Change | How important is it to... | How feasible is it to... |
|---|---|---|
| 1 - 2 - 3 - 4 - 5 | 1 - 2 - 3 - 4 - 5 | |
| 1 - 2 - 3 - 4 - 5 | 1 - 2 - 3 - 4 - 5 | |
| 1 - 2 - 3 - 4 - 5 | 1 - 2 - 3 - 4 - 5 |
How do you calculate the average ranking score using a scale like the one in the table above?
Example:
For a proposed change, 20 planning group members select one of the score values in their response. Of those, you have:
- 10 responding “3”
- 4 responding “2”
- 6 responding “4”
Given the suggested criteria of an average ranking of 3 or higher, will you keep or toss the proposed change?
Step 1. 10(3) + 4(2) + 6(4) = 62
Step 2. 62 / 20 responses = an average ranking of 3.1
Step 3. Based on the scoring criteria, you determine to keep the proposed change since the overall consensus via the survey is 3.1.
What is most important about the process demonstrated above is that each group member participates in the consensus vote on each proposed change. And when you are finished, your community will be armed with a targeted action plan that has the approval of all community sector representatives.
The Grande Finale – The Complete Action Plan!
By now, you have come a long way in your action planning process. You have gathered information, involved key community members, outlined a vision, mission, objectives, and developed appropriate strategies for your community. In this final step of action plan development, you will specify in detail who will do what, by when, to make what changes happen. The action plan will also note the resources needed, potential barriers or resistance, and collaborators or communication lines that need to be active. You can rely on this plan to know what actions you should take day by day.
Action Step Criteria
Your action plan will consist of numerous action steps needed to bring about change in the community. Each action step should outline:
- What actions or changes will occur
- Who will carry out those changes
- By when the changes will take place, and for how long
- What resources are needed to carry out proposed changes
- Communication (who should know what?)
Drafting Action Steps
Action steps are similar to well-written objectives in their structure and content, but include some additional information. First, let’s start by looking at how to draft a strong objective. Then, we will take it one step further and write a comparable action step. You may already be working from objectives in a funded grant proposal. If that is the case, you have a time-saving, solid foundation for your action steps.
The best action steps have several characteristics in common with well-written objectives. Those parallel characteristics are:
- Specific. That is, they tell how much (e.g., 40%) of what is to be achieved (e.g., what behavior of whom or what outcome) by when (e.g., by 20XX)?
- Measurable. Information concerning the objective can be collected, detected, or obtained from records (at least potentially).
- Achievable. Not only are the objectives themselves possible, it is likely that your organization will be able to pull them off.
- Relevant to the mission. Your organization has a clear understanding of how these objectives fit in with the overall vision and mission of the group.
- Timed. Your organization has developed a timeline (a portion of which is made clear in the objectives) by which they will be achieved.
- Challenging. They stretch the group to set its aims on significant improvements that are important to members of the community.
Example: Your community is working to establish on-site childcare for community health clinic clients by the year 20XX. Based on the desired systems change, here is a sample action statement: “By June 20XX, all necessary regulatory permits will be obtained.”
Now, let’s take this information and generate a complete action step. In addition to the criteria for well-written objectives, action steps address resources needed, anticipated barriers, and a communication plan. Now we will complete the five action step criteria (what, who, by when, what resources, and communication) using the sample, “By June 20XX...”
Criteria 1: What actions or changes will occur?
All necessary regulatory permits will be obtained for the on-site provision of childcare for health clinic clients.
Criteria 2: Who will carry out those changes?
Danelda Jackson and Tom Glinn, staff of the community health clinic
Criteria 3: By when will the changes take place, and for how long?
June 20XX, in order to open the following year. They will be renewed annually after that.
Criteria 4: What resources are needed to carry out the proposed changes? (For example, resources may be material, financial, or time-related).
Contractors
What potential barriers might affect this action step? Barriers to success might include:
- Faltering commitment on behalf of collaborators
- Key individuals or groups opposing efforts
- Lack of sustained interest in the initiative at the community level
- Simultaneous events such as an economic downturn or parallel or competing initiatives
- City staff may resist providing a permit because it may appear to intensify the use of the clinic site.
Criteria 5: Communication (who should be informed about these actions?)
Clinic staff, clients, and community residents should be made aware of the availability of on-site childcare at the clinic.
Note: You may find it most helpful to set up a template for a table in a word processing program so you can efficiently record each action step generated by your planning group. The table below has been filled in with the criteria and sample information listed above.
| Action Step | Action | By Whom | By When | Resources/Support Needed | Potential Barriers/Resistance | Communication |
|---|---|---|---|---|---|---|
| By June 20XX, all necessary regulatory permits will be obtained. | All necessary regulatory permits will be obtained from the childcare licensing agency, city government, etc. | Danelda Jackson and Tom Glinn, clinic staff | June 20XX in order to open the following year | Contractors | City staff may resist providing a permit because it may appear to intensify the use of the clinic site. | Clinic staff, clients, and community residents should be made aware of the availability of on-site childcare at the clinic. |
Review your action plan for completeness
Once the planning process is complete, be sure to obtain review and approval of the final action plan from all group members.
Assess the action plan for:
- Comprehensiveness
- Clarity
- Feasibility
- Timeliness
- Flexibility
Remember that the action plan will be revisited from time to time for modifications, as a community’s needs change. However, ultimately, this “blueprint for action” will be used over time, across sectors of the community, and across issues of interest. Therefore, strive to make it a powerful tool for community change.
Follow Through
Your completed action plan may contain many action steps. And while you will have mapped those out carefully along a timeline, you will probably have action steps that should occur simultaneously. Furthermore, you may sense a need to prioritize the order in which you execute action steps that are supposed to take place in the first six months of your initiative.
You may find it easier to determine that ordering or prioritization strategy if you ask the following questions:
- Which changes are the most important or key to the initiative's objectives?
- Which changes would inspire and encourage participants and build credibility within the community?
- Which changes need to be completed before others can? For example, some changes may require other changes and relationships to be established.
- Which changes are easier or quicker? Could completing them give the planning group’s members a sense of success?
Part of following through with proposed action steps will be the task of maintaining collaborator commitment and interest. An invaluable approach to fostering this working relationship is communication: communication about timelines, upcoming planning meetings, progress, results, intermediate feedback, etc.
Communicate progress
Communication is paramount to continued support and commitment within all sectors of the community. Continue to hold planning group meetings and additional public forum meetings, making sure to publicize these appropriately via local newspapers, email lists, etc. Communicate with all relevant audiences, and let them know how their feedback was used to modify the action plan when relevant. You may want to refer back to the “communication” column of your action step table to make sure that you have corresponded with all people who need to know about the status of a particular action step.
It is best to include a communication plan in your action plan, and regularly share information about progress and outcomes relevant to the initiative. And the best means of having sound information to report is an evaluation plan.
Document progress
After you have worked so hard to plan and implement action steps, your community group will most certainly want a means of measuring progress towards the vision. It is important to evaluate your initiative toward that end.
The purpose of evaluation is to document and measure the completion or success of action steps. From your action planning group’s perspective:
- Evaluation may help you clarify action steps so they are measurable.
- Documentation and evaluation help you continually refine your program. Remember—an action plan is an ever-changing blueprint that can be modified according to community needs. If evaluation of action steps reveals successes, failures, or other lessons learned, that information should be applied to future planning cycles or revision of the overall action plan.
- Evaluation data provide information about the relative costs and effort for tasks so activity and budget adjustments can be made as needed.
It is important to include evaluation components as you develop your action plan rather than waiting until you implement it. Be sure that your action plan details how information will be collected, analyzed, and communicated. Because the action plan will be implemented over a long period of time, you may want to document intermediate accomplishments on a monthly basis. Such cumulative records help you identify trends in rates of community and system change over a number of years.
Celebrate progress and revisit/renew the action plan
Even the most effective initiatives can benefit from reflection on their accomplishments. Therefore, you should review your action plan as frequently as needed, but at least annually. Arrange for ongoing review and discussion of group progress and proposed changes in the action plan. And, when new and important changes occur (e.g., a long-awaited policy change by a major employer), celebrate them.
Overall, focus on “small wins” versus creating “the perfect program.” This approach will:
- Reward outcomes versus actions
- Provide multiple opportunities for celebration
- Allow coalition partners to work together by asking each other to do their part while not demanding that everyone be locked into a single course of action
- Provide a sensitive measure of progress that can be monitored periodically to support improvement and accountability
Throughout evaluation of progress, celebration of progress, and renewal of the action plan as the community environment changes over time, maintain this key perspective:
Your community coalition is a catalyst for change, helping to bring about a series of community and system changes related to the mission, rather than simply the delivery of a single program or service. While evaluation has its place in all initiatives, try to focus more on contribution rather than attribution as your community implements its action plan.
In summary
Action planning includes:
- Convening a planning group in your community that consists of:
- Key officials
- Grassroots leaders
- Representatives of key sectors
- Representatives from all parts of the community, including diverse ethnic, cultural, and socioeconomic groups
- Listening to the community
- Documenting problems that affect healthy youth development
- Identifying risk and protective factors
- Developing a framework for action
- Becoming aware of local resources and efforts
- Refining your group's vision, mission, objectives, and strategies
- Refining your group's choice of targets and people or groups who can contribute to change
- Determining what community sectors should be involved in the solution
- Developing a tentative list of changes to be sought in each sector
- Building consensus on proposed changes
- Outlining action steps for proposed changes
- Documenting progress on bringing about community and system changes
- Renewing your group's efforts along the way
When you complete these activities, celebrate (for now) You have developed a blueprint for action.
Regardless of the complexity of the problem at hand within your community, action planning helps you:
- Understand the community’s perception of both the issue at hand and its potential solutions.
- Ensure inclusive and integrated participation across community sectors in the planning process.
- Build consensus on what can and should be done based on the community’s unique assets and needs.
- Specify concrete ways in which members of the community coalition can take action.
Myles Horton, the late founder of the Highlander Center, talked about "making the road by walking." The work of transforming communities and systems to promote healthy youth development will be made by joining with local people who care enough to make needed changes. As we do this important work, we realize that we walk the path of those before us. And, eventually, with those who will carry on this cause after we are gone.
Contributor
Sarah Pfau
Resources
Online Resources
Concerns Report Handbook: Planning for Community Health
Preventing Adolescent Substance Abuse: An Action Planning Guide for Community-Based Initiatives
Preventing Adolescent Pregnancy: An Action Planning Guide for Community-Based Initiatives
Preventing Youth Violence: An Action Planning Guide for Community-Based Initiatives
Preventing Child Abuse and Neglect: An Action Planning Guide for Community-Based Initiatives
Promoting Child Well-Being: An Action Planning Guide for Community-Based Initiatives
Promoting Health for All: Improving Access and Eliminating Disparities in Community Health
Promoting Healthy Living and Preventing Chronic Disease: An Action Planning Guide for Communities
Reducing Risk for Chronic Disease: An Action Planning Guide for Community-Based Initiatives
Youth Development: An Action Planning Guide for Community-Based Initiatives
Print Resources
Fawcett, S., Carson, V., Collie, V., Bremby, R., & Raymer, K. (May 2000). Promoting Health for All: An Action Planning Guide for Improving Access and Eliminating Disparities in Community Health. KU Work Group on Health Promotion & Community Development, Lawrence, Kansas.
Francisco, V., Holt, C., Swenson, J., & Fawcett, S. (November 2002). Youth Development: An Action Planning Guide for Community-Based Initiatives. KU Work Group on Health Promotion & Community Development, Lawrence, Kansas.
Puddy, R., Fawcett, S., & Francisco, V. (July 2002). Promoting Child Well-Being: An Action Planning Guide for Community-Based Initiatives. KU Work Group on Health Promotion & Community Development, Lawrence, Kansas.
Tarlov, A., & St. Peter, R. (2000). The Society and Population Health Reader: A State and Community Perspective. New York: The New Press. Chapter Four: Fawcett, S., Francisco, V., Hyra, D., Paine-Andrews, A., Shultz, J., Russos, S., Fisher, J., & Evensen, P. Building Healthy Communities.
U.S. Department of Health and Human Services. Planned Approach to Community Health: Guide for the Local Coordinator. Atlanta, GA: U.S. Department of Health and Human Services, Centers for Disease Control and Prevention, National Center for Chronic Disease Prevention and Health Promotion.
___You understand what action planning is.
___You understand why action planning is important, and how it can help your community address a health issue or problem.
___You have reviewed the eight broad components of an action plan.
___You have guidelines for facilitating group meetings, including: resolving conflict, offering encouragement, consensus building, and leading brainstorming sessions.
___You understand how to draft clear and effective vision, mission, objective, and strategy statements.
___You have reviewed guidelines for developing, categorizing, and prioritizing strategies within the context of your community.
___You have reviewed guidelines for developing action steps that address the “what”, “who”, “when”, “resources”, and “communication” aspects of action plan activities.
___You understand the importance and relevance of evaluation within the action planning process.
___You understand why it is important to view your community planning group’s role as that of a “catalyst for change” versus a means of creating the ‘perfect program’, and that small wins should be acknowledged and celebrated.
___You understand that the action planning process is a “blue print for action” that is ever changing, and therefore requires maintenance of collaborative working relationships via communication, feedback, and action plan renewal over time.
Contributor
Sarah Plau
Tool: Determine the importance of proposed changes
| Proposed Change | How important is it to... | How feasible is it to ... |
Tool: Determine action steps
Action Plan for [Community or Initiative Name]
Goal Area:____________________________________________________
Strategy: __________________________________________________________________________________________________
|
Action Steps |
By Whom |
By When |
Resources and Support |
Communications |
|
|
What needs to be done? |
Who will take actions? |
By what date will the action be done? |
Resources Available |
Resources Needed (financial, human, political, other) |
Who should be informed about these actions? |
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|

The internet can function as an invaluable resource in community health and development. In this section, you will learn how to use online tools to gather and distribute information, communicate effectively with others, and gain support and credibility in conducting community projects.
What do we mean by using online tools to promote community health and development?
The internet provides access to an enormous storehouse of information and knowledge, as well as a global communication network. With a computer or smartphone, you can post on social media or send a message and reach people across the globe. You can also work collaboratively with someone you may never meet in person, read an article on almost any subject, or search the contents of some of the world's largest libraries.
You can also find a huge array of false or misleading information. It's important to be aware of the reliability of the source of any information you get online. If you have any question about it, check the information with other sources before you assume that it's accurate. Even reliable sites -- major news organizations or universities, for instance -- make mistakes from time to time. The difference is that reliable sources generally correct themselves when they find an error, while less reliable sources may intentionally persist in error or simply may not bother to change their information once it's posted.
University libraries and other research institutions provide useful guidance for evaluating the credibility of online information. When using information you find online, consider the reliability of the source and verify questionable information with other credible sources.
There are different kinds of online tools you might use, and different purposes you might use them for:
To learn how to do the work. The Community Tool Box is an example, but there are many others that can provide guidance as you plan your work, start a coalition, raise money, gain participation, etc.
To gather information . This obviously includes a broad range of possibilities -- not only websites, but also online forums, digital publications, library catalogs, databases, and other online resources. Some of the most common types of information you might be seeking:
- Demographics (age, gender, race, ethnicity, income, etc.). The most common source of this data in the U.S. is the Census Bureau, but much may also be found on state, county, municipal, and federal and state government agency and department websites. Equivalent data for Canada can be found through Statistics Canada and provincial and ministry websites.
- Laws and regulations. Laws can be found on a number of websites for both the U.S. and Canada. These include U.S. state laws; Uniform Commercial Code, U.S. federal laws, and the General Laws of Canada. Regulations of municipal, county, state, and federal agencies can generally be found on agency websites.
- Funders and funding opportunities. A well-defined web search will turn up the names of foundations that are interested in your issue, and their websites will tell you whether you're a good candidate for funding by them or not. State and other government agency websites will also give information about what they fund, how much is available, and usually include copies of current Requests for Proposals (RFPs). The websites of state and national coalitions and organizations may also have funding information or opportunities.
- Best practices. Many U.S. and Canadian state/provincial and national government agencies (e.g., the U.S. National Institutes of Health) have on their websites lists and descriptions of successful programs and approaches (sometimes called "best practices," sometimes identified as successes or effective programs). Professional organizations, coalitions devoted to your issue, and organizations that run successful programs are all likely to have online information about best practices.
- New methods, ideas, theory, or research in the field. Academic papers and journal articles, online discussions, and digital versions of newspapers, journals, and other media may all make this kind of information available online, or at least tell you where you can find it. Online publications may also include contact information for the author or another expert so that you can discuss the ideas more fully.
- Information to use for education or other program purposes. Biographical data, historical facts, scientific principles or formulas, and the text of important historical or government documents (the U.S. Constitution, for example).
To communicate with others. The internet allows you to communicate with people from all over the world in a short time through email, video conferencing, social media, messaging platforms, and other online tools. Among the reasons you might want to do so are:
- To share and discuss information and advice on your work, or on political or social factors affecting it, in online forums, discussion groups, and other spaces.
- To communicate directly with colleagues, participants, funders, collaborators, and others. You might also use email or other digital communication to ask members or supporters for contributions; advertise programs or events; discuss individual cases or situations with others involved; ask questions of colleagues or experts; or organize and engage in advocacy.
- To use a website or other online platform to get your message out, advertise your services, and post messages and other important material for participants, members, board members, staff, and others.
To distribute educational or informational material to participants . Many university courses use the Community Tool Box as text, for instance, or send students directly to the Community Tool Box site for course reading.
To conduct business . Nonprofit and grassroots organizations, like many individuals, use the internet to find and contact suppliers; comparison shop; order materials, equipment, and supplies; pay bills; advertise positions; and sell or publicize services and products.
To engage in advocacy . Online tools can be invaluable to an advocacy effort. Email, websites, social media, online groups, and other communication tools allow an advocacy group to organize, mobilize members for action, contact policymakers, conduct advocacy research, and educate a constituency, as well as the general public, about an issue.
Why use online tools to promote community health and development?
First, the scope: the internet is truly international and crosses geographic borders. Mobile and satellite technologies have extended opportunities for internet access to places where traditional infrastructure may be limited. This means that people in widely separated places may be able to access information and communicate with one another in ways that were once difficult or impossible. Such reach can be misused, but it can also create tremendous opportunities for economic, social, political, intellectual, and human development.
There are, of course, important limitations. Access to devices, reliable connectivity, and affordable internet service remains uneven, particularly in communities and countries with limited economic resources. People may have access through schools, libraries, community organizations, government programs, or other channels, but access remains a significant issue for many people.
Literacy and language can also create barriers. People who have limited literacy or who do not read languages commonly used in online materials may not be able to take full advantage of available information. Translation can help, but the volume of online material makes complete translation difficult.
That said, billions of people can benefit directly from internet access, and many others can benefit indirectly from information and resources that are shared through it.
Second, the internet can be a highly participatory medium. Access to a great deal of online information is free, and people who can get online may find information, communicate their ideas, connect with others, and participate in discussions that once would have been difficult to access.
Furthermore, the nature of the medium makes it possible for a message to be transmitted to someone anywhere in the world, or for that same message to reach thousands or even millions of people in a very short time. Online communication can reduce many physical barriers of time and distance and can create opportunities for people who otherwise might never encounter one another to exchange ideas. At the same time, differences in access and influence remain, and not everyone participates online on equal terms.
Governments in some countries monitor or limit internet use for political reasons. Restrictions can include blocking websites or services, monitoring online activity, or limiting access to parts of the internet. These restrictions can affect people's ability to communicate and obtain information freely.
Given these characteristics of the internet -- its enormous reach and its ability to connect people -- there are a number of reasons why online tools have enormous potential for health and community development.
- They broaden access to knowledge and information -- including for people who may not have ready access to libraries, universities, or other traditional sources of information. Thus, they can build capacity for people to work out solutions to their concerns.
- They make it possible for people to change their lives and communities themselves , without having to depend entirely on outside experts to solve problems for them.
- They can help distribute access to knowledge and information more equitably throughout societies. If knowledge is power -- and the one certainly has a lot to do with the other -- then access to knowledge and accurate information can help people participate more fully in decisions that affect them.
- They can help combat ignorance and misinformation, as well as disinformation (false information deliberately spread by governments, corporations, institutions, individuals, or other entities in order to influence others or protect their own interests).
- They make it easier for people to understand how they can effect social change , and therefore to be more willing to attempt it.
- They give people models to follow. This is true in several senses: online tools can help people discover best practices and processes that are likely to work in their communities. They can, by exposing people to a range of possibilities, change their goals and sense of the possible. And they can present individual role models -- either people with whom internet users might establish direct contact, or profiles of people like themselves who have been able to accomplish good things. Many websites of NGOs and development organizations -- Oxfam America comes to mind -- profile people who have made a difference in their communities.
- They put people concerned with health and community development in touch with one another, so they can support one another and spread their own knowledge and experience farther.
- They increase the ease and effectiveness of advocacy, particularly for community members whose perspectives have been underrepresented. As discussed above, online tools can mobilize and instruct people in action, provide information on issues, and facilitate strategic planning for policy change.
- They can ease access to elected and appointed officials. Many officials maintain websites, email addresses, online contact forms, or other digital channels through which they can be contacted.
- They can help to ensure the accountability of those officials and of oversight bodies. Proceedings of governmental and legislative sessions and hearings, legislators' voting records, political contributions, and a great deal of other information relating to official accountability are available online, as well as information about public-records laws such as the U.S. Freedom of Information Act.
- They can shorten response time to community emergencies or to addressing community needs. Online communication can mobilize volunteers, supplies, funding, and information to respond to disasters or address community issues. The international response to the 2004 Indian Ocean tsunami, for example, demonstrated the potential reach of online communication and fundraising.
- They encourage and facilitate collaboration among individuals and organizations at all levels. Online tools make it easier for individuals and organizations to work together, especially if they are geographically separated. A collaborative funding proposal, for instance, can be worked on by many different people without requiring everyone to be in the same place.
Who might use online tools to do health and community work?
The short -- and accurate -- answer here is everyone. The internet is particularly useful for those who want to reach out to many people in a short time.
Some examples:
- Professionals and professional organizations use online forums, websites, and other communication tools to discuss issues, conduct advocacy, plan and organize conferences (including virtual conferences), and collaborate on research and other work.
- Grassroots and community-based organizations use online tools to inform the community about their services, communicate with one another, search for best practices, seek and apply for funding, and keep current on political situations that affect them.
- Larger nonprofits and initiatives use online tools to publicize their issues, highlight their challenges and successes, and raise money.
Oxfam America's response to the 2004 Indian Ocean tsunami illustrated the potential reach of online fundraising. The organization experienced a rapid surge in donations following the disaster, demonstrating how online tools can help organizations reach large numbers of supporters quickly.
- Community activists use online tools for organizing and for researching their issues.
- Political activists use online tools to mobilize for or against candidates and issues they care about.
- Participants in and people served by health and community service organizations and initiatives use online tools to communicate, learn about political and social issues that affect their organizations, and practice advocacy, such as contacting legislators.
- Students in disciplines related to health and community services use sites like the Community Tool Box to learn about their fields, find practicum and job opportunities, and communicate with others with similar interests.
- Community members with an interest in a topic or issue, like parents concerned about alcohol use among adolescents, can use online tools to learn more about it and make connections with others with similar interests.
When might you use online tools?
There are times when online tools are particularly helpful.
- When you want to build the community's capacity to solve its own problems. A site like the Community Tool Box can help community activists, grassroots groups, and interested community members gain the skills, knowledge, and confidence necessary to create locally developed solutions to community problems, and to do the long-term work of social change that leads to better lives for everyone.
- When you're starting a program, initiative, or other effort with little information. The vast information resources available on the web can help you assess your community's needs, learn about your issue, find best practices, determine what's worked elsewhere, etc.
- When you need to communicate with a large number of people (and decide or embark on an action) quickly. Email, websites, social media, messaging platforms, or online groups make it possible to communicate with and mobilize large numbers of people quickly.
- When you need to learn about or understand laws or regulations. Whether it's a matter of checking on the amount of lobbying your tax-exempt organization may legally engage in, or on the environmental obligations of that smoke-belching factory on the edge of town, much of this information can be found online.
- When you need information for a grant proposal or other funding possibility. Statistics, the history of your issue, and information about what a funder has previously supported may all be helpful, and much of it can be found online.
- When you want to get your own message out, or set up a place where everyone involved in your organization, effort, or issue can communicate. You can accomplish both goals by creating a website or online community space that includes discussion or communication features. You, or someone else who's qualified, might serve as a moderator or expert in the field in order to answer questions and guide discussion in productive directions.
The logic behind the Community Tool Box as an online tool for the promotion of health and community development:
Since 1995, the University of Kansas Center for Community Health and Development has been building the Community Tool Box as a free, online resource for health and community development. In order to create as nearly complete a resource as possible, the Tool Box team first tried to understand the building blocks of health and community work. What do you have to know and do first, and where do you have to go from there, in health and community work, in order to foster change that will lead to an improvement in the quality of community members' lives?
We came up with a framework for health and community work that includes five components:
- Understanding the context of the work and collaborative planning
- Community action and intervention
- Community and system change
- Widespread behavior change and improvement in population-level outcomes
- Sustaining the effort
Each of these five components is in turn split into a number of core competencies (a total of 16 in all) that further define each component and divide the work into manageable elements. We'll look at each of the five components and its core competencies separately, but first, we'll call attention to three basic assumptions -- guiding principles -- that run through the Community Tool Box.
- An organization's vision, mission, and philosophy should all be consistent with one another. Any effort -- whether an intervention or service, a push for change in behavior or policy, an advocacy campaign, or a protest against current or planned action -- must have a clear vision, a mission that supports that vision, and a philosophical base that reflects the vision and mission. The vision, mission, and philosophy should guide every decision the organization makes, from what funding to pursue to how staff and participants are treated to relationships with other organizations and the community.
-
Almost any effort will benefit from a participatory process. Such a process involves all stakeholders -- particularly those who are the focus of your work -- in the planning and implementation of anything that affects them. That often means providing the information they need to understand clearly the possibilities and limitations of the effort you're embarking on so they can make informed decisions.
There might be various levels of involvement, from consultation to full partnership.
There are two excellent reasons for employing a participatory process:
- It's respectful and fair. It's arrogant and disrespectful, as well as patently unfair, to make decisions for other people without consulting them, no matter how well-meaning those decisions may be.
- It's more effective. You're far more likely to be successful if people buy into and feel ownership of a plan, a program, an initiative, an intervention, or a policy than if they feel it's been imposed on them.
There are, realistically, times when a participatory process simply isn't possible. Time may be too much of the essence -- people's lives may be at stake, as in an emergency relief effort or a military operation. In other situations, some people may be unwilling to consider the possibility that other ideas or positions might be legitimate. In those circumstances, a participatory process may not be the best approach.
Servant leadership and collaborative leadership both assume the leadership of a participatory process.
- Ethics are important. This not only means adhering to the professional ethics of your field, if that's relevant, but behaving as you would have others behave toward you. As an organization and as an individual, you should treat others with respect and fairness, and acknowledge their work and contributions. You should never abuse whatever power you have, and should instead use it to further your cause and your work. An ethical stance should carry over into your dealings with participants; collaborators and other organizations and institutions; staff, board members, and others within your organization; funders, contributors, and members; policymakers; and the community.
The components of health and community development, and their respective core competencies
Understanding context and collaborative planning
The context of a health or community issue encompasses the history, culture, character, and economic, social, and political makeup of the community itself; the nature of the issue and its relevance to and frequency in the community or population in question; the culture, size, attitudes, and other characteristics of the population of focus; and the people involved in all these areas, and their relationships to one another.
Six core competencies, or fundamental abilities, contribute to the work of understanding context and collaborative planning:
- Creating and maintaining coalitions and collaborative partnerships is a way to engage a variety of sectors, such as government agencies and faith communities, in a common purpose; to hear the concerns and needs of all sectors; and to gather a broad range of ideas and perspectives.
- Assessing community needs and resources, such as the need for more accessible health services or the presence of grassroots advocacy groups, grounds the work in what is locally important and available.
- Analyzing community-identified problems and goals with community partners helps pinpoint the personal and group factors -- knowledge and skills, or history of care or discrimination -- and environmental factors -- access and barriers, support and resources, broader policies -- that may affect the current problem and future prospects for goal attainment.
- Developing a framework or model of change helps define how the community intends to go from the current situation, such as low rates of childhood immunization, to sustained improvements in population-level outcomes.
- Developing strategic and action plans sets the blueprint for getting from a community's vision (Healthy Youth Program) to improvements in population-level outcomes (changes in rates of pregnancies among adolescents or substance use disorders).
- Building leadership helps ensure that the community itself can continue to generate a team of people to develop and sustain relationships and transform conditions necessary for community change.
Community action and intervention. Once you've engaged in community assessment and used the results to formulate a plan, you have to take action in order to effect change. Action plans should flow from the overall strategy you've come up with, and should be aimed at producing the outcomes that a collaborative planning process has identified as important. Your action should, to the extent possible, involve all sectors of the community, and encompass the diversity of the community. To these ends, three core competencies fall under this component of health and community development:
- Developing an intervention involves selecting and using intervention components based on an analysis of contributing factors and available resources. For example, a comprehensive intervention to increase childhood immunization might include such elements as providing information and enhancing skills (educating parents about how vaccination works and what it protects children from); modifying access, barriers, and opportunities (expanded outreach, provision of transportation); and modifying policies (offering vaccinations as part of other clinic visits).
- Increasing participation and membership brings in the voices of those who have the most experience of the issue (young people, people from underrepresented language communities), but who may face barriers to involvement, as well as involving as many sectors of the community as possible. All of this increases the sense of ownership of any action by those involved.
- Enhancing cultural competence makes it possible for people of diverse backgrounds to work together, and to understand and respect one another's cultural beliefs and practices. Such understanding and respect increases community coherence, and aids efforts to improve the quality of life for everyone in the community. Cultural competence, through improved communication and recognition of others' abilities, also contributes to the attainment of such other competencies as building community leadership and developing strategic and action plans.
Community and system change. Bringing about permanent change in a community entails more than simply creating and running an intervention. The intervention may have an immediate effect on the issue you're concerned with, but that's rarely enough. In order to bring about permanent change, you often have to change both the systems that affect it -- e.g., policies, funding mechanisms, education, etc. -- and the community itself -- attitudes, social customs...the things that people take for granted. In order to make these kinds of changes, you may have to take a multi-pronged approach, working with several sectors of the community at once. Three core competencies help in this endeavor:
- Advocating for change. Advocacy can range from trying to convince a local merchant not to sell tobacco to minors to organizing a national campaign against a proposed military action. It may target individuals, corporations, institutions, legislators or other public officials, or be aimed directly at public opinion through use of the media. Effective advocacy takes an orchestrated effort that pulls in as many people as possible, takes into account and counters opposition, and uses a variety of strategies and tactics.
- Influencing policy development. Both formal and informal policies may need to be rethought in order to bring about long-term change. Creating a safer environment for children, for instance, may involve a restructuring of drug laws (allowing for more prevention education, and more emphasis on treatment as opposed to imprisonment); a change in workplace policies (on-site or subsidized childcare, flexible schedules, etc.); expanded nutrition education and food programs; more structured activities for children and young people in the community; community policing strategies; etc. Changing those policies may require a combination of direct legislative advocacy, working with the business community, conducting a media campaign, and negotiating with community agencies and officials.
- Evaluating the initiative. Evaluation makes it possible to see (and enhance) the effects of your work over time, and to understand their impact on indirectly related community indicators of change. Not only does it enable you to make changes that reflect ongoing changes in the population and that respond to what you've learned, but it shows you to what extent you're addressing community and system change. Thus, an evaluation of an initiative to reduce smoking among people who are pregnant that showed a significant number of participants quitting during pregnancy might be related to a subsequent decrease in the expected number of infants with low birth weight.
Widespread behavior change and improvement in population-level outcomes. How do we affect the behavior of enough people in enough places to improve overall outcomes? Changing population-level outcomes requires changing the behaviors of large numbers of people. In order to accomplish this, states, communities, and organizations may employ social marketing efforts that include promotional messages, and that incorporate environmental changes that make the desired behaviors easier and more rewarding. To increase civic engagement, a campaign might include media messages that emphasize the beneficial consequences of community participation, easier access to voting (through simplified registration, more neighborhood polling places, free transportation to the polls, etc.), and greater opportunities for public participation in policy processes. One core competency supports this component:
- Implementing a social marketing campaign. Social marketing applies the techniques of commercial marketing to social goals, "selling" behavior change in much the same way that manufacturers sell products. Social marketing surveys potential "customers" -- those whose behavior needs to change -- segments the market (decides whom to appeal to and how), carefully crafts and places messages to speak to the intended audience, maximizes benefit and minimizes cost to the customer, supports change, and continually evaluates and readjusts the campaign to make it as effective as possible.
Sustaining the effort. As the Community Tool Box continually emphasizes, the work of health and community development is never really done. Once an intervention is launched, it has to be maintained over time for as long as it's needed. Real community change -- change that involves system and attitude changes, policy change, etc. -- may take years or decades. Even once it's accomplished, it still needs to be maintained if you don't want to lose ground. Both the work and the funding have to continue, or you'll never reach your ultimate goal of an improvement in the lives of community members. The final three core competencies are aimed at keeping it all going indefinitely, or for as long as is necessary.
- Applying for grants. As much as we might wish things were otherwise, money is necessary for almost any health or community effort. Understanding where to look for both public and private funding, and how to write a successful grant proposal, are essential skills for any organization that wants to do community work.
- Improving organizational management and development. If you're going to sustain your work over a long period, your organization has to be well-managed and structured for the long haul. There are different models you can choose from, but regardless of which you use, you have to be able to pay bills and staff on time, deliver services effectively, recruit participants, deal with internal and external problems, use your assets well, work with other organizations, and develop systems that make it easy to get things done. In short, you have to be able to manage work, staff, external relationships, and money as efficiently and gracefully as possible.
- Sustaining the work or initiative. All too often, funding from a particular source is time-limited. People -- founders and key staff members of organizations -- come and go, creating shifts in organizational patterns and gaps in organizational memory. Communities change, requiring changes in services or goals. New research pushes the work in an unexpected direction. Despite these disruptions, the organization and its work have to continue if you want to effect real change. You have to find ways to keep going -- to replace lost funding, to institutionalize your work in the community, to continue to hire people who'll do an excellent job, and to respond to changes in the population or the community. Sustaining the effort becomes part of your work at a certain point, and will remain so throughout the life of the organization.
We believe that the Community Tool Box is the most comprehensive capacity-building tool available online, both in the breadth of its vision and in the sheer volume of the information it provides. However, as we've discussed in this section, there are countless other tools of various types available online, and many of them provide information or services that the Community Tool Box doesn't. Explore the CTB, but explore other options as well, especially if you're looking for specific information -- census data, methods of doing your work, research results, etc.
Much of the early public internet was shaped by ideals of cooperation and broad access to information. In that spirit, our goal is not to compete with other websites, but rather to help your organization become the best and most effective practitioner of health and community development possible. If we all work together, and use online tools well, we can help make the world a better place, one community at a time.
In summary
The internet is a vast source of information and expertise, where community builders can find instruction, data, connections to others with similar concerns, funding possibilities, and much else they need to engage in their work. Online tools for health and community development -- websites like the Community Tool Box that provide information and instruction; university sites; government sites; newspaper and other media sites; online encyclopedias and databases; email groups; online forums; and other tools that allow communication among community builders -- can all contribute mightily toward doing the work. They can transcend geographical boundaries and make it possible for communities to find information and develop their own answers to problems, while recognizing that access to online resources is not universal.
The Community Tool Box is an online resource that aims to build the capacity of community-based and grassroots groups and organizations to act effectively on health and community issues, and to bring about positive social change in their communities. To this end, we have identified five basic components of health and community work, each with its own core competencies, and have organized accordingly:
Understanding the context of the work and collaborative planning
- Creating and maintaining coalitions
- Assessing community resources
- Analyzing community-identified problems and goals
- Developing a framework or model of change
- Developing strategic and action plans
- Building leadership
Community action and intervention
- Developing an intervention
- Increasing participation and membership
- Enhancing cultural competence
Community and system change
- Advocating for change
- Influencing policy development
- Evaluating the initiative
Widespread behavior change and improvement in population-level outcomes
- Implementing a social marketing campaign
Sustaining the effort
- Applying for grants
- Improving organizational management and development
- Sustaining the work or initiative
The Community Tool Box is, we believe, the most comprehensive capacity-building tool online, with thousands of pages of how-to information for health and community activists. But it's not the only valuable or useful online tool. There are thousands of sites that might be helpful, providing additional information or expertise that the Community Tool Box doesn't. The internet is one of the most powerful communication media and sources of information ever developed; if health and community builders take full advantage of it, we can change the world...for the better.
Contributor
Phil Rabinowitz
Resources
Online Resources
The list below, although fairly long, is hardly comprehensive. It's simply meant to give a taste of what's available. For every site listed, there are probably thousands more that could be found with similar or better information. For each U.S. government site, for instance, there is likely to be an equivalent site for most other western governments, at the very least. Use search engines, links, and your ingenuity, and there's almost no limit to what you can find.
The Canadian Encyclopedia - all about Canada, in French and English
Centers for Disease Control and Prevention - Information on a variety of topics related to disease and epidemiology, prevention techniques and programs, best practices, etc.
"Criteria to Evaluate the Credibility of WWW Resources"
Equal Employment Opportunity Commission - The agency of the United States Government that enforces the federal employment discrimination laws.
It's All About the Base: A Guide to Building a Grassroots Organizing Program
Legal Information Institute of Cornell Law School. Links to the statutes of all states, listed by topic and by state. You can find any US state law here - a tremendous resource.
The Library of Congress. An enormous reservoir of information, which contains the texts of pending and newly-passed bills and laws, as well as a great deal of other information useful to political activists. The LOC site also includes American Memory, which contains the full texts of the Constitution, the Declaration of Independence, and many other American historical documents.
The Medline Plus Medical Encyclopedia, from the U.S. National Library of Medicine and the National Institutes of Health.
The National Institutes of Health - The website often lists best practices or describes successful programs and efforts.
Oxfam America, an international development organization whose website often profiles "local heroes" - ordinary people who accomplish extraordinary things for their communities.
"Ten C's for Evaluating Internet Sources," from the library of the University of Wisconsin at Eau Claire.
The text of the Uniform Commercial Code, from the Legal Information Institute at Cornell.
Links to state statutes that correspond to the articles of the Uniform Commercial Code.
U.S. Bureau of Labor Statistics
U.S. Census Bureau - Census data for all areas of the U.S., including demographics, economic data, education, housing, etc.
The U.S. Department of Agriculture - Information on agriculture, rural development, food products, land use, the environment, etc.
U.S. Department of Health and Human Services
U.S. Department of Education - Information on government policy.
U.S. Department of Labor - Labor laws and regulations.
U.S. Department of Justice - Civil rights, immigration, the federal court system, etc.
U.S. Department of State - Foreign policy.
U.S. Environmental Protection Agency - Information on environmental topics, and on government environmental policy and initiatives, as well as EPA regulations.
U.S. Food and Drug Administration - Information on drugs and foods, warnings and safety alerts, FDA policy and regulations, etc.
U.S. government grant site - Information on grant availability, guidelines, applications and application procedures, etc.
U.S. House of Representatives - Connections to all Congresspersons and their websites, information on legislation, schedules, committees, links, and more.
U.S. Occupational Safety and Health Administration - Workplace safety regulations.
The text of the Uniform Commercial Code, from the Legal Information Institute at Cornell.
Links to state statutes that correspond to the articles of the Uniform Commercial Code.
The U.S. Senate - Senate rules, voting records and contact information for all Senators, glossary of terms, etc.
Wikipedia, a user-generated on-line encyclopedia.
Print Resources
Fawcett, S., Schultz, J., Carson L,, Renault, A,, Francisco, V. (2003) Using Internet Based Tools to Build Capacity for Community Based Participatory Research and Other Efforts to Promote Community Health and Development. In Minkler, M., N. Wallerstein (Eds), Community Based Participatory Research for Health, (pp. 155-178). San Francisco: Jossey-Bass.
Schlein, M. (2004) Find It Online: The complete guide to online research (4th ed.). Tempe, AZ: Facts on Demand Press.
What do we mean by using Internet-based tools to promote community health and development?
You use Internet based tools:
___To learn how to do the work.
___To gather information.
___To communicate with others.
___To distribute educational or other information to participants.
___To conduct business.
___To engage in advocacy.
Why use Internet-based tools to promote community health and development?
___They give access to knowledge and information to everyone.
___They make it possible for people to change their lives and communities themselves.
___They help to distribute power and control more equitably throughout societies.
___They help to combat ignorance and misinformation (as well as disinformation - the intentional lies that governments, corporations, institutions, and other entities sometimes tell in order to keep control or to protect their own self-interest).
___They make it easier for people to understand how they can effect social change, and therefore to be more willing to attempt it.
___They give people models to follow.
___They put people concerned with health and community development in touch with one another.
___They increase the ease and effectiveness of advocacy, particularly for those who might otherwise have no voice.
___They can ease access to elected and appointed officials.
___They can help to assure the accountability of those officials and of oversight bodies.
___They can shorten response time to community emergencies or to addressing community needs.
___They encourage and facilitate collaboration among individuals and organizations at all levels.
Who should use Internet-based tools to promote community health and development?
___Professionals and professional organizations.
___Grass roots and community-based organizations.
___Larger nonprofits and initiatives.
___Community activists.
___Political activists.
___Participants in and beneficiaries of health and community service organizations and initiatives.
___Students in disciplines related to health and community services.
When should you use Internet-based tools to promote community health and development?
___When you want to build the community's capacity to solve its own problems.
___When you're starting a program, initiative, or other effort with little information.
___When you need to communicate with a large number of people (and decide or embark on an action) quickly.
___When you need to learn about or understand laws or regulations.
___When you need information for a grant proposal or other funding possibility.
___When you want to get your own message out, or set up a place where everyone involved in your organization or effort or issue can communicate.
The logic behind the Community Tool Box as an Internet-based tool for the promotion of health and community development.
Guiding principles:
___An organization's vision, mission, and philosophy should all be consistent with one another.
___Almost any effort will benefit from a participatory process.
___Ethics are important.
Components of health and community development, with their respective core competencies:
___Understanding the context of the work and collaborative planning
- Creating and maintaining coalitions
- Assessing community resources
- Analyzing community-identified problems and goals
- Developing a framework or model of change
- Developing strategic and action plans
- Building leadership
___Community action and intervention
- Developing an intervention
- Increasing participation and membership
- Enhancing cultural competency
___Community and system change
- Advocating for change
- Influencing policy development
- Evaluating the initiative
___Widespread behavior change and improvement in population-level outcomes
- Implementing a social marketing campaign
___Sustaining the effort
- Applying for grants
- Improving organizational management and development
Contributor
Phil Rabinowitz
Katherine Fulton: You Are the Future of Philanthropy
In this 12 minute lecture, Katherine Fulton, president of the Monitor Institute, describes how philanthropy has evolved by utilizing the internet to grow, connect, and improve.

Experienced community builders know that involving stakeholders -- the people directly connected to and affected by their projects -- in their work is tremendously important. It gives them the information they need to design, and to adjust or change, what they do to best meet the needs of the community and of the particular populations that an intervention or initiative is meant to benefit. This is particularly true in relation to evaluation.
As we have previously discussed, community-based participatory research can be employed in describing the community, assessing community issues and needs, finding and choosing best practices, and/or evaluation. We consider the topic of participatory evaluation important enough to give it a section of its own, and to show how it fits into the larger participatory research picture.
It's a good idea to build stakeholder participation into a project from the beginning. One of the best ways to choose the proper direction for your work is to involve stakeholders in identifying real community needs and the ways in which a project will have the greatest impact. One of the best ways to find out what kinds of effects your work is having on the people it's aimed at is to include people receiving or affected by information, services, or advocacy on your evaluation team.
Often, you can see most clearly what's actually happening through the eyes of those directly involved in it -- participants, staff, and others who are involved in taking part in and carrying out a program, initiative, or other project. Previously, we have discussed how you can involve those people in conducting research on the community and choosing issues to address and directions to go in. This section is about how you can involve them in the whole scope of the project, including its evaluation, and how that's likely to benefit the project's final outcomes.
What is participatory evaluation?
When most people think of evaluation, they think of something that happens at the end of a project -- that looks at the project after it's over and decides whether it was any good or not. Evaluation actually needs to be an integral part of any project from the beginning. Participatory evaluation involves all the stakeholders in a project -- those directly affected by it or by carrying it out -- in contributing to the understanding of it, and in applying that understanding to the improvement of the work.
Participatory evaluation, as we shall see, isn't simply a matter of asking stakeholders to take part. Involving everyone affected changes the whole nature of a project from something done for a group of people or a community to a partnership among participants, community members, and those implementing the project. Rather than people with less influence over decisions affecting them being acted upon, participants become copilots of a project, helping make sure that their real needs and those of the community are recognized and addressed. Professional evaluators, project staff, project participants, and other community members all become colleagues in an effort to improve the community's quality of life.
This approach to planning and evaluation isn't possible without mutual trust and respect. These have to develop over time, but that development is made more probable by starting out with an understanding of local culture and customs -- whether you're working in a lower-resource setting or in an American urban neighborhood. Respecting individuals and the knowledge and skills they have will go a long way toward promoting long-term trust and involvement.
The other necessary aspect of any participatory process is appropriate training for everyone involved. Some stakeholders may not even be aware that project research takes place; others may have no idea how to work alongside people from different backgrounds; and still others may not know what to do with evaluation results once they have them. We'll discuss all of these issues -- stakeholder involvement, establishing trust, and training -- as the section progresses.
The real purpose of an evaluation is not just to find out what happened, but to use the information to make the project better. In order to accomplish this, evaluation should include examining at least three areas:
- Process. The process of a project includes the planning and logistical activities needed to set up and run it. Did we do a proper assessment beforehand so we would know what the real needs were? Did we use the results of the assessment to identify and respond to those needs in the design of the project? Did we set up and run the project within the timelines and other structures that we intended? Did we involve the people we intended to? Did we have or get the resources we expected? Were staff and others trained and prepared to do the work? Did we have the community support we expected? Did we record what we did accurately and on time? Did we monitor and evaluate as we intended?
- Implementation. Project implementation is the actual work of running it. Did we do what we intended? Did we serve or affect the number of people we proposed to? Did we use the methods we set out to use? Was the level of our activity what we intended (e.g., did we provide the number of hours of service we intended to)? Did we reach the population(s) we aimed at? What exactly did we provide or do? Did we make intentional or unintentional changes, and why?
- Outcomes. The project's outcomes are its results -- what actually happened as a consequence of the project's existence. Did our work have the effects we hoped for? Did it have other, unforeseen effects? Were they positive or negative (or neither)? Do we know why we got the results we did? What can we change, and how, to make our work more effective?
Many who write about participatory evaluation combine the first two of these areas into process evaluation, and add a third -- impact evaluation -- in addition to outcome evaluation. Impact evaluation looks at the long-term results of a project, whether the project continues or does its work and ends.
Rural development projects in lower-resource settings, for example, often exist simply to pass on specific skills to local people, who are expected to then both practice those skills and teach them to others. Once people have learned the skills -- perhaps particular cultivation techniques or water purification -- the project ends. If, in five or ten years, an impact evaluation shows that the skills the project taught are not only still being practiced, but have spread, then the project's impact was both long-term and positive.
In order for these areas to be covered properly, evaluation has to start at the very beginning of the project, with assessment and planning. In a participatory evaluation, stakeholders should be involved in:
- Naming and framing the problem or goal to be addressed
- Developing a theory of practice (process, logic model) for how to achieve success
- Identifying the questions to ask about the project and the best ways to ask them -- these questions will identify what the project means to do, and therefore what should be evaluated
What's the real goal, for instance, of a program to introduce healthier foods in school lunches? It could be simply to convince children to eat more fruits, vegetables, and whole grains. It could be to get them to eat less junk food. It could be to encourage weight loss among children for whom excess weight is a health concern. It could simply be to educate them about healthy eating, and to persuade them to be more adventurous eaters. The evaluation questions you ask both reflect and determine your goals for the program. If you don't measure changes in weight, for instance, then clearly that's not what you're aiming at. If you only look at an increase in children's consumption of healthy foods, you're not examining whether their overall eating patterns have changed. Is increased consumption of healthy foods still beneficial if other eating habits remain the same? You answer that question by what you choose to examine.
- Collecting information about the project
- Making sense of that information
- Deciding what to celebrate, and what to adjust or change, based on information from the evaluation
Why would (and why wouldn't) you use participatory evaluation?
Why would you use participatory evaluation? The short answer is that it's often the most effective way to find out what you need to know, both at the beginning of and throughout the course of a project. In addition, it carries benefits for both individual participants and the community that other methods don't.
Some of the major advantages of participatory evaluation:
- It gives you a better perspective on both the initial needs of the people the project is intended to benefit and on its ultimate effects. If stakeholders, including project participants, are involved from the beginning in determining what needs to be evaluated and why -- not to mention what the focus of the project needs to be -- you're much more likely to aim your work in the right direction, to correctly determine whether your project is effective or not, and to understand how to change it to make it more so.
- It can get you information you wouldn't get otherwise. When project direction and evaluation depend, at least in part, on information from people in the community, that information will often be more forthcoming if it's asked for by someone familiar. Community members interviewing their friends and neighbors may get information that an outside person wouldn't be offered.
- It tells you what worked and what didn't from the perspective of those most directly involved -- participants and staff. Those implementing the project and those who are directly affected by it are often well positioned to sort out the effective from the ineffective.
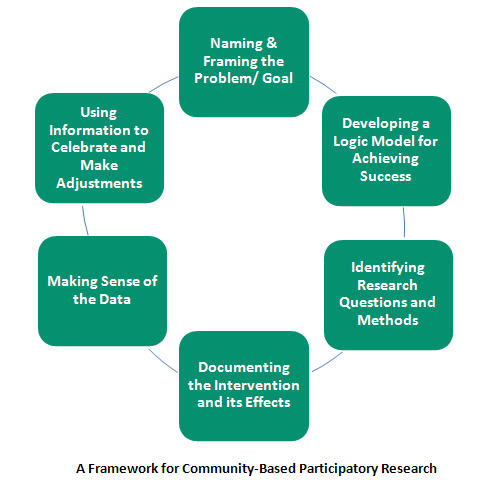
- It can tell you why something does or doesn't work. Participants are often able to explain exactly why they didn't respond to a particular technique or approach, thus giving you a better chance to adjust it properly.
- It results in a more effective project. For the reasons just described, you're much more apt to start out in the right direction, and to know when you need to change direction if you haven't. The consequence is a project that addresses the appropriate issues in the appropriate way, and accomplishes what it sets out to do.
- It empowers stakeholders. Participatory evaluation gives people who are often not consulted -- particularly line staff and participants -- the chance to be full partners in determining the direction and effectiveness of a project.
- It creates opportunities for perspectives that are often not included to be heard. Some project participants may have lower incomes or limited access to formal education and may have had fewer opportunities to influence decisions affecting them. By involving them from the beginning in project evaluation, you help ensure that their perspectives are included and that they have meaningful opportunities to speak for themselves.
- It teaches skills that can be used in employment and other areas of life. In addition to the development of basic skills and specific research capabilities, participatory evaluation encourages critical thinking, collaboration, problem-solving, independent action, meeting deadlines...all skills valued by employers, and useful in family life, education, civic participation, and other areas.
- It can strengthen self-confidence and self-esteem. This can include project participants and others who, because of circumstance, may have had few opportunities for their knowledge, abilities, or contributions to be recognized. The opportunity to engage in a meaningful and challenging activity, and to be treated as a colleague by professionals, can make a significant difference.
- It demonstrates ways in which people can take more control of decisions affecting their lives. Working with professionals and others to complete a complex task with real-world consequences can show people how they can take action to influence people and events.
- It encourages stakeholder ownership of the project. If those involved feel the project is theirs, rather than something imposed on them by others, they'll work hard both in implementing it and in conducting a thorough and informative evaluation in order to improve it.
- It can spark creativity in everyone involved. For those who've never been involved in anything similar, a participatory evaluation can be a revelation, opening doors to a whole new way of thinking and looking at the world. To those who have taken part in evaluation before, the opportunity to exchange ideas with people who may have new ways of looking at the familiar can lead to a fresh perspective on what may have seemed to be a settled issue.
- It encourages working collaboratively. For participatory evaluation to work well, it has to be viewed by everyone involved as a collaboration, where each participant brings specific tools and skills to the effort, and everyone is valued for what they can contribute. Collaboration of this sort not only leads to many of the advantages described above, but also fosters a more collaborative spirit for the future as well, leading to other successful community projects.
- It fits into a larger participatory effort. When community assessment and the planning of a project have been a collaboration among project participants, staff, and community members, it only makes sense to include evaluation in the overall plan, and to approach it in the same way as the rest of the project. In order to conduct a good evaluation, its planning should be part of the overall planning of the project. Furthermore, participatory process generally matches well with the philosophy of community-based or grassroots groups or organizations.
With all these positive aspects, participatory evaluation carries some negative ones as well. Whether its disadvantages outweigh its advantages depends on your circumstances, but whether you decide to engage in it or not, it's important to understand what kinds of drawbacks it might have.
The significant disadvantages of participatory evaluation include:
- It takes more time than a conventional process. Because there are so many people with different perspectives involved, a number of whom have never taken part in planning or evaluation before, everything takes longer than if a professional evaluator or a team familiar with evaluation simply set up and conducted everything. Decision-making involves a great deal of discussion, gathering people together may be difficult, evaluators need to be trained, etc.
- It takes the establishment of trust among all participants in the process. If you're starting something new (or, all too often, even if the project is ongoing), differences in social class, culture, and experience may divide groups of stakeholders. These can lead to snags and slowdowns until they're addressed, which won't happen overnight. It will take time and a good deal of conscious effort before all stakeholders feel comfortable and confident that their needs and culture are being addressed.
- You have to make sure that everyone's involved, not just "leaders" of various groups. All too often, "participatory" means the participation of an already-existing power structure. Most leaders are actually that -- people who are concerned with the best interests of the group, and whom others trust to represent them and steer them in the direction that best reflects those interests. Sometimes, however, people who hold leadership positions may not represent the full range of perspectives within a community.
By involving only leaders of a population or community, you run the risk of losing -- or never gaining -- the confidence and perspective of the rest of the population, which may distrust a particular leader or may simply see themselves shut out of the process. They may see the participatory evaluation as a function of authority and be uninterested in taking part in it. Working to recruit other community members as well as leaders may be an important step for the credibility of the process. But it's a lot of work and may be difficult.
- You have to train people to understand evaluation and how the participatory process works, as well as teaching them basic research skills. There are really a number of potential disadvantages here. The obvious one is that of time, which we've already raised -- training takes time to prepare, time to implement, and time to sink in. Another is the question of what kind of training participants will respond to. Still another concerns recruitment -- will people be willing to put in the time necessary to prepare them for the process, let alone the time for the process itself?
- You have to get buy-in and commitment from participants. Given what evaluators will have to do, they need to be committed to the process, and to feel ownership of it. You have to structure both the training and the process itself to bring about this commitment.
- People's lives -- illness, childcare and relationship problems, agricultural work, etc. -- may cause delays or get in the way of the evaluation. People facing economic hardship may have less flexibility when unexpected demands arise. A sick child, relationship difficulties, or too many days of rain in a row during an important agricultural period may disrupt someone's ability to participate on a given day, or at all. If you're working with a rural community that depends heavily on agriculture, for instance, an unexpected change in weather can derail the process temporarily or, in some cases, permanently.
- You may have to be creative about how you get, record, and report information. If some of the participants in an evaluation have limited literacy, or if participants speak a number of different languages (English, Spanish, and Lao, for instance), a way to record information will have to be found that everyone can understand, and that can, in turn, be understood by others outside the group.
- Funders and policymakers may not understand or believe in participatory evaluation. At worst, this can lose you your funding, or the opportunity to apply for funding. At best, you'll have to spend a good deal of time and effort convincing funders and policymakers that participatory evaluation is a good idea, and obtaining their support for your effort.
Some of these disadvantages could also be seen as advantages: the training people receive blends in with their development of new skills that can be transferred to other areas of life, for instance; coming up with creative ways to express ideas benefits everyone; once funders and policymakers are persuaded of the benefits of participatory process and participatory evaluation, they may encourage others to employ it as well. Nonetheless, all of these potential negatives take time, which can be crucial. If it's absolutely necessary that things happen quickly (which is true not nearly as often as most of us think it is), participatory evaluation is probably not the way to go.
When might you use participatory evaluation?
So when do you use participatory evaluation? Some of the reasons you might decide it's the best choice for your purposes:
- When you're already committed to a participatory process for your project. Evaluation planning can be included and collaboratively designed as part of the overall project plan.
- When you have the time, or when results are more important than time. As should be obvious from the last part of this section, one of the biggest drawbacks to participatory evaluation is the time it takes. If time isn't what's most important, you can gain the advantages of a participatory evaluation without having to compensate for many of the disadvantages.
- When you can convince funders that it's a good idea. Funders may specify that they want an outside evaluation, or they may simply be uncertain about the value of participatory evaluation. In either case, you may have some persuading to do in order to be able to use a participatory process. If you can get their support, however, funders may value the fact that participatory evaluation can have added benefits in the form of empowerment and transferable skills.
- When there may be issues in the community or population that outside evaluators (or program providers, for that matter) aren't likely to be aware of. Political, social, and interpersonal factors in the community can shape the results of an evaluation, and without an understanding of those factors and their history, evaluators may have no idea that what they're finding out is being influenced in any way. Evaluators who are part of the community can help sort out the influence of these factors, and thus end up with a more accurate evaluation.
- When you need information that it will be difficult for anyone outside the community or population to get. When you know that members of the community or population in question are unwilling to speak freely to anyone from outside, participatory evaluation is a way to increase the chances that you'll get the information you need.
- When part of the goal of the project is to empower participants and help them develop transferable skills. Here, the participatory evaluation, as it should in any case, becomes a part of the project itself and its goals.
- When you want to bring the community or population together. In addition to fostering a collaborative spirit, as we've mentioned, a participatory evaluation can create opportunities for people who normally have little contact to work together and get to know one another. This familiarity can then carry over into other aspects of community life, and even change the social character of the community over the long term.
Who should be involved in participatory evaluation?
We've referred continually to stakeholders -- the people who are directly affected by the project being evaluated. Who are the stakeholders? That varies from project to project, depending on the focus, the funding, the intended outcomes, etc. There are a number of groups that are generally involved, however:
- Participants or people intended to benefit. These are the people whom the project is meant to benefit. That may be a specific group (people with a certain medical condition, for instance), a particular population (recent immigrants from Southeast Asia, residents of a particular area), or a whole community. They may be actively receiving a service (e.g., employment training) or may simply stand to benefit from what the project is doing (violence prevention in a given neighborhood). These are usually the people with the greatest stake in the project's success, and often those with the least experience with evaluation.
- Project line staff and/or volunteers. The people who actually do the work of carrying out the project. They may be professionals, people with specific skills, or community volunteers. They may work directly with project participants as mentors, teachers, or health care providers; or they may advocate for immigrant rights, identify open space to be preserved, or answer the phone and prepare mailings. Whoever they are, they often know more about what they're doing than anyone else, and their lives can be affected by the project as much as those of participants.
- Administrators. The people who coordinate the project or specific aspects of it. Like line staff and volunteers, they know a lot about what's going on, and they're intimately involved with the project every day.
- Outside evaluators, if they're involved. In many cases, outside evaluators are hired to run participatory evaluations. The need for their involvement is obvious.
- Community officials. You may need the support of community leaders, or you may simply want to give them and other participants the opportunity to get to know one another in a context that might lead to better understanding of community needs.
- Others whose lives are affected by the project. The definition of this group varies greatly from project to project. In general, it refers to people whose jobs or other aspects of their lives will be changed either by the functioning of the project itself, or by its outcomes.
An example would be landowners whose potential use of their land would be affected by an environmental initiative or a neighborhood plan.
How do you conduct a participatory evaluation?
Participatory evaluation encompasses elements of designing the project as well as evaluating it. What you evaluate depends on what you want to know and what you're trying to do. Identifying the actual evaluation questions sets the course of the project just as surely as a standardized testing program guides teaching. When these questions come out of an assessment in which stakeholders are involved, the evaluation is one phase of a community-based participatory research process.
A participatory evaluation really has two stages: One comprises finding and training stakeholders to act as participant evaluators. The second -- some of which may take place before or during the first stage -- encompasses the planning and implementation of the project and its evaluation, and includes six steps:
- Naming and framing the issue
- Developing a theory of practice to address it
- Deciding what questions to ask, and how to ask them to get the information you need
- Collecting information
- Analyzing the information you've collected
- Using the information to celebrate what worked, and to adjust and improve the project
We'll examine both of these stages in detail.
Finding and training stakeholders to act as participant evaluators
Unfortunately, this stage isn't simply a matter of announcing a participatory evaluation and then sitting back while people beat down the doors to be part of it. In fact, it may be one of the more difficult aspects of conducting a participatory evaluation.
Here's where the trust building we discussed earlier comes into play. The population you're working with may be distrustful of outsiders, or may be used to promises of involvement that turn out to be hollow or simply ignored. They may be used to being ignored in general, and/or offered services and programs that don't speak to their real needs. If you haven't already built a relationship to the point where people are willing to believe that you'll follow through on what you say, now is the time to do it. It may take some time and effort -- you may have to prove that you'll still be there in six months -- but it's worth it. You're much more likely to have a successful project, let alone a successful evaluation, if you have a relationship of mutual trust and respect.
But let's assume you have that step out of the way, and that you've established good relationships in the community and among the population you're working with, as well as with staff of the project. Let's assume as well that these people know very little, if anything, about participatory evaluation. That means they'll need training in order to be effective.
If, in fact, your evaluation is part of a larger participatory effort, the question arises as to whether to simply employ the same team that did assessments and/or planned the project, perhaps with some additions, as evaluators. That course of action has both pluses and minuses. The team is already assembled, has developed a method of working together, has some training in research methods, etc., so that they can hit the ground running -- obviously a plus.
The fact that they have a big stake in seeing the project be successful can work either way: they may interpret their findings in the best possible light, or even ignore negative information; or they may be eager to see exactly where and how to adjust the work to make it go better.Another issue is burnout. Evaluation will mean more time in addition to what an assessment and planning team has already put in. While some may be more than willing to continue, many may be ready for a break (or may be moving on to another phase of their lives). If the possibility of assembling a new team exists, it will give those who've had enough the chance to gracefully withdraw.
How you handle this question will depend on the attitudes of those involved, how many people you actually have to draw on (if the recruitment of the initial team was really difficult, you may not have a lot of choices), and what people committed to.
Recruit participant evaluators
There are many ways to accomplish this. In some situations, it makes the most sense to put out a general call for volunteers; in others, to approach specific individuals who are likely -- because of their commitment to the project or to the population -- to be willing. Alternatively, you might approach community leaders or stakeholders to suggest possible evaluators.
Some basic guidelines for recruitment include:
- Use communication channels and styles that reach the people you're aiming at
- Make your message as clear as possible
- Use plain language and/or whatever other language(s) the population uses
- Put your message where the audience is
- Approach potential participants individually where possible -- if you can find people they know to recruit them, all the better
- Explain what people may gain from participation
- Be clear that they're being asked because they already have qualities that are important for participation
- Encourage people, but also be honest about the amount and extent of what needs to be done
- Work out with participants what they're willing and able to do
- Try to arrange support -- childcare, for example -- to make participation easier
- Ask people you've recruited to recommend -- or recruit -- others
In general, it's important for potential participant evaluators -- particularly those whose connection to the project isn't related to their employment -- to understand the commitment involved. An evaluation is likely to last a year, unless the project is considerably shorter than that, and while you might expect and plan for some dropouts, most of the team needs to be available for that long.
In order to make that commitment easier, discuss with participants what kinds of support they'll need in order to fulfill their commitment -- childcare and transportation, for instance -- and try to find ways to provide it. Arrange meetings at times and places that are easiest for them (and keep the number of meetings to a minimum). For participants who are paid project staff, the evaluation should be considered part of their regular work, so that it isn't an extra, unpaid burden that they feel they can't refuse.
Be careful to try to put together a team that's a cross-section of the stakeholder population. As we've already discussed, if you recruit only "leaders" from among the participant population, for instance, you may create resentment in the rest of the group, fail to get a full perspective of the thinking or perceptions of that group, and defeat the purpose of the participatory nature of the evaluation as well. Even if the leaders are good representatives of the group, you may want to broaden your recruitment in the hopes of developing more community leadership and creating opportunities for people whose perspectives may not always be heard.
Train participant evaluators
Participants, depending on their backgrounds, may need training in a number of areas. They may have very little experience in attending and taking part in meetings, for instance, and may need to start there. They may benefit from an introduction to the idea of participatory evaluation and how it works. And they'll almost certainly need some training in data gathering and analysis.
How training gets carried out will vary with the needs and schedules of participants and the project. It may take place in small chunks over a relatively long period of time -- weeks or months -- might happen all at once in the course of a weekend retreat, or might be some combination. There's no right or wrong way here. The first option will probably make it possible for more people to take part; the second allows for people to get to know one another and bond as a team, and a combination might allow for both.
By the same token, there are many training methods, any or all of which might be useful with a particular group. Training in meeting skills -- knowing when and how to contribute and respond, following discussion, etc. -- may best be accomplished through mentoring, rather than instruction. Interviewing skills may best be learned through roleplaying and other experiential techniques. Some training -- how to approach local people, for example -- might best come from participants themselves.
Some of the areas in which training might be necessary:
- The participatory evaluation process. How participatory evaluation works, its goals, the roles people may play in the process, what to expect.
- Meeting skills. Following discussion, listening skills, handling disagreement or conflict, contributing and responding appropriately, general ground rules and etiquette, etc.
- Interviewing. Putting people at ease, body language and tone of voice, asking open-ended and follow-up questions, recording what people say and other important information, handling interruptions and distractions, group interviews.
- Observation. Direct vs. participant observation, choosing appropriate times and places to observe, relevant information to include, recording observations.
- Recording information and reporting it to the group. What interviewees and those observed say and do, the nonverbal messages they send, who they are (age, situation, etc.), what the conditions were, the date and time, and any other factors that influenced the interview or observation.
For people for whom writing isn't comfortable, where writing isn't feasible, or where language is a barrier, there should be alternative recording and reporting methods. Drawings, maps, diagrams, audio recordings, videos, or other imaginative ways of remembering exactly what was said or observed can be substituted, depending on the situation. In interviews, if audio or video recording is going to be used, it's important to get the interviewee's permission first -- before the interviewer shows up with the equipment, so that there are no misunderstandings.
Planning and implementing the project and its evaluation. There's an assumption here that all phases of a project will be participatory, so that not only its evaluation, but its planning and the assessment that leads to it also involve stakeholders (not necessarily the same ones who act as evaluators). If stakeholders haven't been involved from the beginning, they don't have the deep understanding of the purposes and structure of a project that they'd have of one they've helped form. The evaluation that results, therefore, is likely to be less perceptive -- and therefore less valuable -- than one of a project they've been involved in from the start.
Naming and framing the problem or goal to be addressed. Identifying what you're evaluating defines what the project is meant to address and accomplish. Community representatives and stakeholders, all those with something to gain or lose, work together to develop a shared vision and mission. By collecting information about community concerns and identifying available assets, communities can understand which issues to focus a project on.
Naming a problem or goal refers to identifying the issue that needs to be addressed. Framing it has to do with the way we look at it. If violence involving young people is conceived of as strictly a law enforcement problem, for instance, that framing implies specific ways of solving it: stricter laws, stricter enforcement, zero tolerance for violence, etc. If it's framed as a combination of a number of issues -- availability of handguns, unemployment and substance use among young people, social issues that lead to the formation of gangs, alienation and hopelessness in particular populations, poverty, etc. -- then solutions may include employment and recreation programs, mentoring, substance use treatment, etc., as well as law enforcement. The more we know about a problem, and the more different perspectives we can include in our thinking about it, the more accurately we can frame it, and the more likely we are to come up with an effective solution.
Developing a theory of practice to address the problem. How do you conduct a community effort so that it has a good chance of solving the problem at hand? Many communities and organizations answer this question by throwing uncoordinated programs at the problem, or by assuming a certain approach (law enforcement, as in our example, for instance) will take care of it. In fact, you have to have a plan for creating, implementing, evaluating, adjusting, and maintaining a solution if you want it to work.
Whatever you call this plan -- a theory of practice, a logic model, or simply an approach or process -- it should be logical, consistent, consider all the areas that need to be coordinated in order for it to work, and give you an overall guideline and a list of steps to follow in order to carry it out.
Once you've identified an issue, for instance, one possible theory of practice might be:
- Form a coalition of organizations, agencies, and community members concerned with the problem.
- Recruit and train a participatory research team which includes representatives of all stakeholder groups.
- The team collects both statistical and qualitative, firsthand information about the problem, and identifies community assets that might help in addressing it.
- Use the information you have to design a solution that takes into account the problem's complexity and context.
This might be a single program or initiative, or a coordinated, community-wide effort involving several organizations, the media, and individuals. If it's closer to the latter, that's part of the complexity you have to take into account. Coordination has to be part of your solution, as do ways to get around the bureaucratic roadblocks that might occur and methods to find the financial and personnel resources you need.
- Implement the solution.
- Carry out monitoring and evaluation that will give you ongoing feedback about how well you're meeting objectives, and what you should change to improve your solution.
- Use the information from the evaluation to adjust and improve the solution.
- Go back to #2 and do as much of it again as you need to until the problem is solved, or -- more likely, since many community problems never actually disappear -- indefinitely in order to maintain and increase your gains.
Deciding what evaluation questions to ask, and how to ask them to get the information you need. As we've discussed, choosing the evaluation questions essentially guides the work. What you're really choosing here is what you're going to pay attention to. There could be significant results from your project that you're never aware of, because you didn't look for them -- you didn't ask the questions to which those results would have been the answers. That's why it's so important to select questions carefully: they'll determine what you find.
Framing the problem is one element here -- putting it in context, looking at it from all sides, stepping back from your own assumptions and biases to get a clearer and broader view of it. Another is envisioning the outcomes you want, and thinking about what needs to change, and how, in order to reach them.
Framing is important in this activity as well. If you want simply to reduce violence involving young people, stricter laws and enforcement might seem like a reasonable solution, assuming you're willing to stick with them forever; if you want not only to reduce or eliminate that violence, but to change the climate that fosters it (i.e., long-term social change), the solution becomes much broader and requires, as we pointed out above, much more than law enforcement. And a broader solution means more, and more complex, evaluation questions.
In the first case, evaluation questions might be limited to some variation of: "Were there more arrests and convictions of young people for violent crimes in the time period studied, as compared to the last period for which there were records before the new solution was put in place?" "Did young people convicted of violent offenses receive harsher sentences than before?" "Was there a reduction in violent incidents involving young people?"
Looking at the broader picture, in addition to some of those questions, there might be questions about counseling programs for young people who committed offenses to change their attitudes and help ease their transition back into the community, substance use treatment, control of handgun sales, changing community attitudes, etc.
Collecting information. This is the largest part, at least in time and effort, of implementing an evaluation. Various evaluators, depending on the information needed, may conduct any or all of the following:
- Research into census or other public records, as well as news archives, library collections, online sources, etc.
- Individual and/or group interviews
- Focus groups
- Community information-sharing sessions
- Surveys
- Direct or participant observation
In some cases -- particularly among populations with limited access to formal education in lower-resource settings -- evaluators may have to find creative ways to draw out information. In some cultures, maps, drawings, representations ("If this rock is the headman's house..."), or even storytelling may be more revealing than the answers to straightforward questions.
Analyzing the information you've collected. Once you've collected all the information you need, the next step is to make sense of it. What do the numbers mean? What do people's stories and opinions tell you about the project? Did you carry out the process you'd planned? If not, did it make a difference, positive or negative?
In some cases, these questions are relatively easy to answer. If there were particular objectives for serving people, or for participants' accomplishments, you can quickly find out whether they were met or not. (We set out to serve 75 people, and we actually served 82. We anticipated that 50 would complete the program, and 61 actually completed.)
In other cases, it's much harder to tell what your information means. What if approximately half of interviewees say the project was helpful to them, and the other half say the opposite? A result like that may leave you doing some detective work. (Is there any ethnic, racial, geographic, or cultural pattern as to who is positive and who is negative? Whom did each group work with? Where did they experience the project, and how? Did members of each group have specific things in common?)
While collecting the information requires the most work and time, analyzing it is perhaps the most important step in conducting an evaluation. Your analysis tells you what you need to know in order to improve your project, and also gives you the evidence you need to make a case for continued funding and community support. It's important that it be done well, and that it make sense of odd results like that directly above. Here's where good training and good guidance in using critical thinking and other techniques come in.
In general, information-gathering and analysis should cover the three areas we discussed early in the section: process, implementation, and outcomes. The purpose here is both to provide information for improving the project and to provide accountability to funders and the community.
- Process. This concerns the logistics of the project. Was there good coordination and communication? Was the planning process participatory? Was the original timeline for each stage of the project -- outreach, assessment, planning, implementation, evaluation -- realistic? Were you able to find or hire the right people? Did you find adequate funding and other resources? Was the space appropriate? Did members of the planning and evaluation teams work well together? Did the people responsible do what they were expected to do? Did unexpected leaders emerge (in the planning group, for instance)?
- Implementation. Did you do what you set out to do -- reach the number of people you expected to, use the methods you intended, provide the amount and kind of service or activity that you planned for? This part of the evaluation is not meant to assess effectiveness, but only whether the project was carried out as planned -- i.e., what you actually did, rather than what you accomplished as a result. That comes next.
- Outcomes. What were the results of what you did? Did what you hoped for take place? If it did, how do you know it was a result of what you did, as opposed to some other factor(s)? Were there unexpected results? Were they negative or positive? Why did this all happen?
Using the information to celebrate what worked, and to adjust and improve the project. While accountability is important -- if the project has no effect at all, for example, it's just wasted effort -- the real thrust of a good evaluation is formative. That means it's meant to provide information that can help to continue to form the project, reshape it to make it better. As a result, the overall questions when looking at process, implementation, and outcomes are: What worked well? What didn't? What changes would improve the project?
Answering these questions requires further analysis, but should allow you to improve the project considerably. In addition to dropping or changing and adjusting those elements of the project that didn't work well, don't neglect those that were successful. Nothing's perfect; even effective approaches can be made better.
Don't forget to celebrate your successes. Celebration recognizes the hard work of everyone involved, and the value of your effort. It creates community support, and strengthens the commitment of those involved. Perhaps most important, it makes clear that people working together can improve the quality of life in the community.
There's a final element to participatory research and evaluation that can't be ignored. Once you've started a project and made it successful, you have to maintain it. The participatory research and evaluation has to continue -- perhaps not with the same team(s), but with teams representative of all stakeholders. Conditions change, and projects have to adapt. Research into those conditions and continued evaluation of your work will keep that work fresh and effective.
If your project is successful, you may think your work is done. Think again -- community problems are only solved as long as the solutions are actively practiced. The moment you turn your back, the conditions you worked so hard to change can start to return to what existed before. The work -- supported by participatory research and evaluation -- has to go on indefinitely to maintain and increase the gains you've made.
In Summary
Participatory evaluation is a part of participatory research. It involves stakeholders in a community project in setting evaluation criteria for it, collecting and analyzing data, and using the information gained to adjust and improve the project.
Participatory process brings in the all-important multiple perspectives of those most directly affected by the project, who are also most likely to be connected to community history and culture. The information and insights they contribute can be crucial to a project's effectiveness. In addition, their involvement encourages community buy-in, and can result in important gains in skills, knowledge, self-confidence, and self-esteem for participant evaluators. All in all, participatory evaluation can create benefits for both the project and the people involved.
Conducting a participatory evaluation involves several steps:
- Recruiting and training a stakeholder evaluation team
- Naming and framing the problem
- Developing a theory of practice to guide the process of the work
- Asking the right evaluation questions
- Collecting information
- Analyzing information
- Using the information to celebrate and adjust your work
The final step, as with so many of the community-building strategies and actions described in the Community Tool Box, is to keep at it. Participatory research in general, and participatory evaluation in particular, has to continue as long as the work continues, in order to keep track of community needs and conditions, and to keep adjusting the project to make it more responsive and effective. And the work often has to continue indefinitely in order to maintain progress and avoid sliding back into the conditions or attitudes that made the project necessary in the first place.
Contributor
Phil Rabinowitz
Resources
Online Resources
Facilitator's Guide for Participatory Evaluation with Young People, by Barry Checkoway and Katie Richards-Schuster, is a publication from the Program for Youth and Community of the University of Michigan School of Social Work.
Guide to Project Evaluation: A Participatory Approach. From Health Canada, the Public Health Agency of Canada
Issue Topic: Democratic Evaluation from The Evaluation Exchange, vol. 1, No. 3/4, Fall, 1995, Harvard Family Research Project.
"Participatory Evaluation: How It Can Enhance Effectiveness and Credibility of Nonprofit Work" by Susan Saegert, Lymari Benitez, Efrat Eizenberg, Tsai-shiou Hsieh, and Mike Lamb, CUNY Graduate Center, from The Nonprofit Quarterly, 11, 1, Spring 2004.
A Participatory Evaluation Model for Healthier Communities: Developing Indicators for New Mexico. This model helps community coalitions to take an active role in developing evaluations of their programs.
Participatory Methods is a website that provides resources to generate ideas and action for inclusive development and social change.
Community-Based Public Health Policy & Practice Issue #5 explains and elaborates more in-depth information about Participatory Evaluation.
The Research for Organizing toolkit is designed for organizations and individuals that want to use participatory action research (PAR) to support their work towards social justice. PAR helps us to analyze and document the problems that we see in our communities; allows us to generate data and evidence that strengthens our social justice work and ensures that we are the experts about the issues that face our communities. In this toolkit you will find case studies, workshops, worksheets and templates that you can download and tailor to meet your needs
Useful Tools for Engaging Young People in Participatory Evaluation is a PDF toolkit from UNICEF.
Who Are the Question Makers? A Participatory Evaluation Handbook is a resource from the Office of Evaluation and Strategic Planning of the United Nations Development Programme.
What is participatory evaluation?
___Participatory evaluation is an evaluation that involves all the stakeholders in a project - those directly affected by it or by carrying it out - in every phase of evaluating it, and in applying the results of that evaluation to the improvement of the work.
Why would (and why wouldn't) you use participatory evaluation?
Advantages:
___It gives you a better perspective on both the initial needs of the project's beneficiaries, and on its ultimate effects.
___It can get you information you wouldn't get otherwise.
___It tells you what worked and what didn't from the perspective of those most directly involved - beneficiaries and staff.
___It can tell you why something does or doesn't work.
___It results in a more effective project.
___It empowers stakeholders.
___It can provide a voice for those who are often not heard.
___It teaches skills that can be used in employment and other areas of life.
___It bolsters self-confidence and self-esteem in those who may have little of either.
___It demonstrates to people ways in which they can take more control of their lives.
___It encourages stakeholder ownership of the project.
___It can spark creativity in everyone involved.
___It encourages working collaboratively.
___It fits into a larger participatory effort.
Disadvantages:
___It takes more time than conventional process.
___It takes the establishment of trust among all participants in the process.
___You have to make sure that everyone's involved, not just "leaders" of various groups.
___You have to train people to understand evaluation and how the participatory process works, as well as teaching them basic research skills.
___You have to get buy-in and commitment from participants.
___People's lives - illness, child care and relationship problems, getting the crops in, etc. - may cause delays or get in the way oftheevaluation
___You may have to be creative about how you get, record, and report information.
___Funders and policy makers may not understand or believe in participatory evaluation.
When would you use participatory evaluation?
___When you're already committed to a participatory process for your project.
___When you have the time, or when results are more important than time.
___When you can convince funders that it's a good idea.
___When there may be issues in the community or population that outside evaluators (or program providers, for that matter) aren't likely to be aware of.
___When you need information that it will be difficult for anyone outside the community or population to get.
___When part of the goal of the project is to empower participants and help them develop transferable skills.
___When you want to bring the community or population together.
Who should be involved in participatory evaluation?
All stakeholders, including:
___Participants or beneficiaries.
___Project line staff and/or volunteers.
___Administrators.
___Outside evaluators, if they're involved.
___Community officials.
___Others whose lives are affected by the project.
Tool: Team Data Collection - How to Do It Well
This is a summary of responses from e-listserves ARLIST-L (Action Research) and CBPR (Community-Based Participatory Research) to an inquiry posted by Michelle Garred in November 2007. We have included her initial e-mail, and then added the summarized reponses to each of her questions.
From: Michelle Garred
Subject: Team data collection: how to do it well?
Dear colleagues,
I am working on an action research project aimed at field-testing a new method for community-based peacebuilding, in cooperation with a partner agency in the Philippines. Within the agency, there is an established core team assigned to this project, and we collaborate in the research design, data collection, data analysis and dissemination of results. The project has two distinct outcomes: A) a practitioner-focused lessons learned publication to be published by the partner agency and B) my Ph.D. thesis.
Much of our data collection will be conducted by a team, rather than the more traditional approach of data collection by an individual researcher. I am wrestling with some questions about how to do this well.
Among the many questions are:
- What are the methodological advantages of team data collection? What are the pitfalls that we should avoid?
- How can we design the written question protocols, the note-taking templates, and the note-taking processes in ways that maximize the depth and consistency of data?
- How can I encourage and assist my partners in note-taking, when written documentation is not their preferred or strongest skill?
- In my Ph.D. thesis, what might be an acceptable proportion of data collected by team versus data collected directly by me?
- How would you cite team interviews in a Ph.D. thesis?
- What are the key resources I should review?
What are the methodological advantages of team data collection? What are the pitfalls that we should avoid?
Advantages:
- Data collection - Interview more participants / increase sample size, thus presumably increasing reliability and validity of the data while reducing time and cost to do the study.
- Data analysis - Diversity within the research team can enrich interpretation and lead to fresh perspectives.
Pitfalls:
- More personalities and activities to coordinate means more opportunities for things to go wrong.
- Quality assurance: possibility of inconsistencies in question interpretation; possibility of inadequate, erroneous, or extraneous data.
- Team motivation may requirement payment and/or incentive, and full support of the team’s supervisor.
Pitfalls can be addressed through training:
- Need for consistent, systematic training of data collectors.
- Lead researcher conduct pilot interviews first, to get a handle on how to better train the team.
- Conduct interviewing practice sessions before beginning actual interviews.
- During practice, use some standardized interviewees for training purposes and set a high inter-rater reliability for interviewers to make sure they have demonstrated proper technique before you let them loose on your subject population.
- Make sure all interviewers know how to ask delving follow-up questions to elicit clarity of meaning, depth, examples, etc.
- Ensure interviewing ground rules are clear. For example, what follow-up comments may an interviewer add to help an interviewee understand the question? What words may be used and/or not used?
- Demonstrated skills before graduation from training phase
And through regular team meetings:
- Meet periodically throughout the data collection period. This will help to identify any difficulties, and refine your process as you go along.
- Have regular – daily at first if necessary – debriefing, trouble-shooting meetings with all the data collectors, so all can learn from each others’ problems and solutions.
- Regular quality assurance meetings. Since these are partners and not hired data collectors, you will have to train them in a collaborative and diplomatic way. Group review of the data collected each day or each week may help, serving both for QA and as a support group.
- If not together on site, consider on-line conferencing.
How can we design the written question protocols, the note-taking templates, and the note-taking processes in ways that maximize the depth and consistency of data?
Keep in mind that we will have a team of 5 people conducting semi-structured interviews and we will probably not use audio recording.
- Conduct some preliminary focus groups to clarify the questions and problems. Have the interviewers sit in and/or help with the focus groups as part of their training and debrief with them afterwards.
- Use the focus group data to develop some checklists/checkboxes for anticipated responses so that you can have at least some quantitative data.
- Develop the interview guide together with the interview team. It is possible to use a participatory process such as “card storming” to build team consensus on the questions to be asked. Here's one example of a card storming.
- If possible, use two-person data collector teams with the second person taking notes and listening/looking for any problems.
How can I encourage and assist my partners in note-taking, when written documentation is not their preferred or strongest skill?
Again, this can be addressed through team training and regular meetings . . .
- Show the trainee interviewers how it’s done right, but also how it’s done badly. They need to see both the model behavior and also what mistakes to avoid.
- Find a way to illustrate to them how faulty memories of interview material can be, and how difficult it is to analyze interview data when there is little depth of content.
- Revisit this issue during regular team meetings during the data collection phase.
And through wise design of the note-taking protocols:
- Ensure the written interview protocol has space for note-taking in answer to each question, and also for noting unprompted comments from the interviewee.
- Additionally, you might have team members write up a brief summary within 24 hours of completing the interview.
- Focus the note-taking on direct recall of interviewee’s words. Interviewers should strive not to conduct implicit analysis at this point. Reserve analysis for a separate follow-up step.
In my Ph.D. thesis, what might be an acceptable proportion of data collected by team versus data collected directly by me?
I understand that team data collection is common in action research, but less common in a Ph.D. thesis. It would help me to hear some different opinions on this issue.
- For quantitative data, one might set a quota of random 10% of data reviewed for QA.
- I would suggest doing as many as you possibly can, up to the average done by the team, so you can know what they’re experience really is.
- As long as you are directing the study, I wouldn’t have a problem with a sharing of the data collection; however, you would need to be integrally involved in all aspects of the study, particularly coding and analysis.
- Ortrun Zuber-Skerritt and Chad Perry suggest that you distinguish between the field research (where others are involved) and the thesis research, which is your reflection on the field research.
- Zuber-Skerritt, Ortrun, and Perry, Chad (2002) Action research within organisations and university thesis writing. The Learning Organization, 9(4), 171-179.
How would you cite team interviews in a Ph.D. thesis?
- In table format within the document.
- I assume the interview data and individual interviewer will be de-identified in the thesis itself, even if you know who said what in your field notes and quality assurance activities.
- I think I would explain in the body of the text just how the study was carried out, including the qualifications of the team members. Since they are part of the Human as Instrument section, their backgrounds and experience as researchers would need to be shared to instill a sense of trust on the part of the reader for the qualifications of the data collectors.
- When referencing, check APA, but I think it would involve citing interviews in the text by noting the date of the interview, then citing APA style in the bibliography.
- Consider in advance whether you will use the participants' real names or pseudonyms.
Key resources
- See Madeline Church's doctoral thesis, Creating an Uncompromised place to belong - why do I find myself in networks? from the living theory section of Action Research.
- The following paper describes some of the advantages of using a particular form of team-based qualitative research interviews. You may find it useful: Driedger, S. Michelle; Gallois, Cindy; Sanders, Carrie; and Santesso, Nancy (2006). "Finding common ground in team-based qualitative research using the convergent interviewing method." Qualitative Health Research, 16(8), 1145-1157.
- There's a detailed critique in the following book chapter: Rao, Sally, and Perry, Chad (2006). Convergent interviewing: a starting methodology for enterprise research program. In Hine, Damian, and Carson, David, eds., Innovative methodologies in enterprise research, 86-99. Cheltenham, UK: Edward Elgar.
- A good reference is Clifford Geertz's 1973 book, The Interpretation of Cultures. The questions you are asking are actually much deeper and more philosophical than the operational issues you asked about. You are basically working within anthropological practices and rules about fieldnotes and fieldwork rather than traditional interviews like we do in psychology.

What is a logic model?
A logic model presents a picture of how your effort or initiative is supposed to work. It explains why your strategy is a good solution to the problem at hand. Effective logic models make an explicit, often visual, statement of the activities that will bring about change and the results you expect to see for the community and its people. A logic model keeps participants in the effort moving in the same direction by providing a common language and point of reference.
More than an observer's tool, logic models become part of the work itself. They energize and rally support for an initiative by declaring precisely what you're trying to accomplish and how.
In this section, the term logic model is used as a generic label for the many ways of displaying how change unfolds.
Some other names include:
- roadmap, conceptual map, or pathways map
- mental model
- blueprint for change
- framework for action or program framework
- program theory or program hypothesis
- theoretical underpinning or rationale
- causal chain or chain of causation
- theory of change or model of change
Each mapping or modeling technique uses a slightly different approach, but they all rest on a foundation of logic -- specifically, the logic of how change happens. By whatever name you call it, a logic model supports the work of health promotion and community development by charting the course of community transformation as it evolves.
A word about logic
The word "logic" has many definitions. As a branch of philosophy, scholars devote entire careers to its practice. As a structured method of reasoning, mathematicians depend on it for proofs. In the world of computing, computers operate according to programmed logic.
There is, however, another meaning that lies closer to the heart of community change: the logic of how things work. Consider, for example, the logic of rush-hour traffic. No one plans it. No one controls it. Yet, through experience and awareness of recurrent patterns, we comprehend it, and, in many cases, can successfully avoid its problems (by carpooling, taking alternative routes, etc.).
Logic in this sense refers to "the relationship between elements and between an element and the whole." All of us have a great capacity to see patterns in complex phenomena. We see systems at work and find within them an inner logic, a set of rules or relationships that govern behavior. Working alone, we can usually discern the logic of a simple system. And by working in teams, persistently over time if necessary, we can often make sense of even very complex systems.
On the flip side, we can also project logic into the future. With an understanding of context and knowledge about cause and effect, we can construct logical theories of change, hypotheses about how things will unfold either on their own or under the influence of planned interventions. Like all predictions, these hypotheses are only as good as their underlying logic. Magical assumptions, poor reasoning, and fuzzy thinking increase the chances that despite our efforts, the future will turn out differently than we expect or hope. On the other hand, some events that seem unexpected to the uninitiated will not be a surprise to long-time residents and careful observers.
The challenge for a logic modeler is to find and accurately represent the wisdom of those who know best how community change happens.
The logic in logic modeling
Like a roadmap, a logic model shows the route traveled (or steps taken) to reach a certain destination. A detailed model indicates precisely how each activity will lead to desired changes. Alternatively, a broader plan sketches out the chosen routes and how far you will go. This roadmap aspect of a logic model reveals what causes what, and in what order. At various points on the map, you may need to stop and review your progress and make any necessary adjustments.
A logic model also expresses the thinking behind an initiative's plan. It explains why the program ought to work, why it can succeed where other attempts have failed. This is the "program theory" or "rationale" aspect of a logic model. By defining the problem or opportunity and showing how intervention activities will respond to it, a logic model makes the program planners' assumptions explicit.
The form that a logic model takes is flexible and does not have to be linear (unless your program's logic is itself linear). Flowcharts, maps, or tables are the most common formats. It is also possible to use a network, concept map, or web to describe the relationships among more complex program components. Models can even be built around cultural symbols that describe transformation, such as the Indigenous medicine wheel, if the stakeholders feel it is appropriate.
See the "Generic Model for Disease/Injury Control and Prevention" in the Examples section for an illustration of how the same information can be presented in a linear or nonlinear format.
Whatever form you choose, a logic model ought to provide direction and clarity by presenting the big picture of change along with certain important details. Let's illustrate the typical components of a logic model, using as an example a mentoring program in a community where the high school dropout rate is very high. We'll call this program "On Track."
- Purpose, or mission. What motivates the need for change? This can also be expressed as the problems or opportunities that the program is addressing. (For On Track, the community focused its efforts on the mission of enhancing healthy youth development to improve the high school dropout rate.)
- Context, or conditions. What is the climate in which change will take place? (How will new policies and programs for On Track be aligned with existing ones? What trends compete with the effort to engage young people in positive activities? What is the political and economic climate for investing in youth development?)
- Inputs, or resources or infrastructure. What raw materials will be used to conduct the effort or initiative? (In On Track, these include the coordinator and volunteers in the mentoring program, agreements with participating school districts, and the endorsement of parent groups and community agencies.) Inputs can also include constraints on the program, such as regulations or funding gaps, which are barriers to your objectives.
- Activities, or interventions. What will the initiative do with its resources to direct the course of change? (In our example, the program will train volunteer mentors and refer young people who might benefit from a mentor.) Your intervention, and thus your logic model, should be guided by a clear analysis of risk and protective factors.
- Outputs. What evidence is there that the activities were performed as planned? (Indicators might include the number of mentors trained and young people referred, and the frequency, type, duration, and intensity of mentoring contacts.)
- Effects, or results, consequences, outcomes, or impacts. What kinds of changes came about as a direct or indirect effect of the activities? (Two examples are bonding between adult mentors and young people and increased self-esteem among young people.)
Putting these elements together graphically gives the following basic structure for a logic model. The arrows between the boxes indicate that review and adjustment are an ongoing process -- both in enacting the initiative and developing the model.
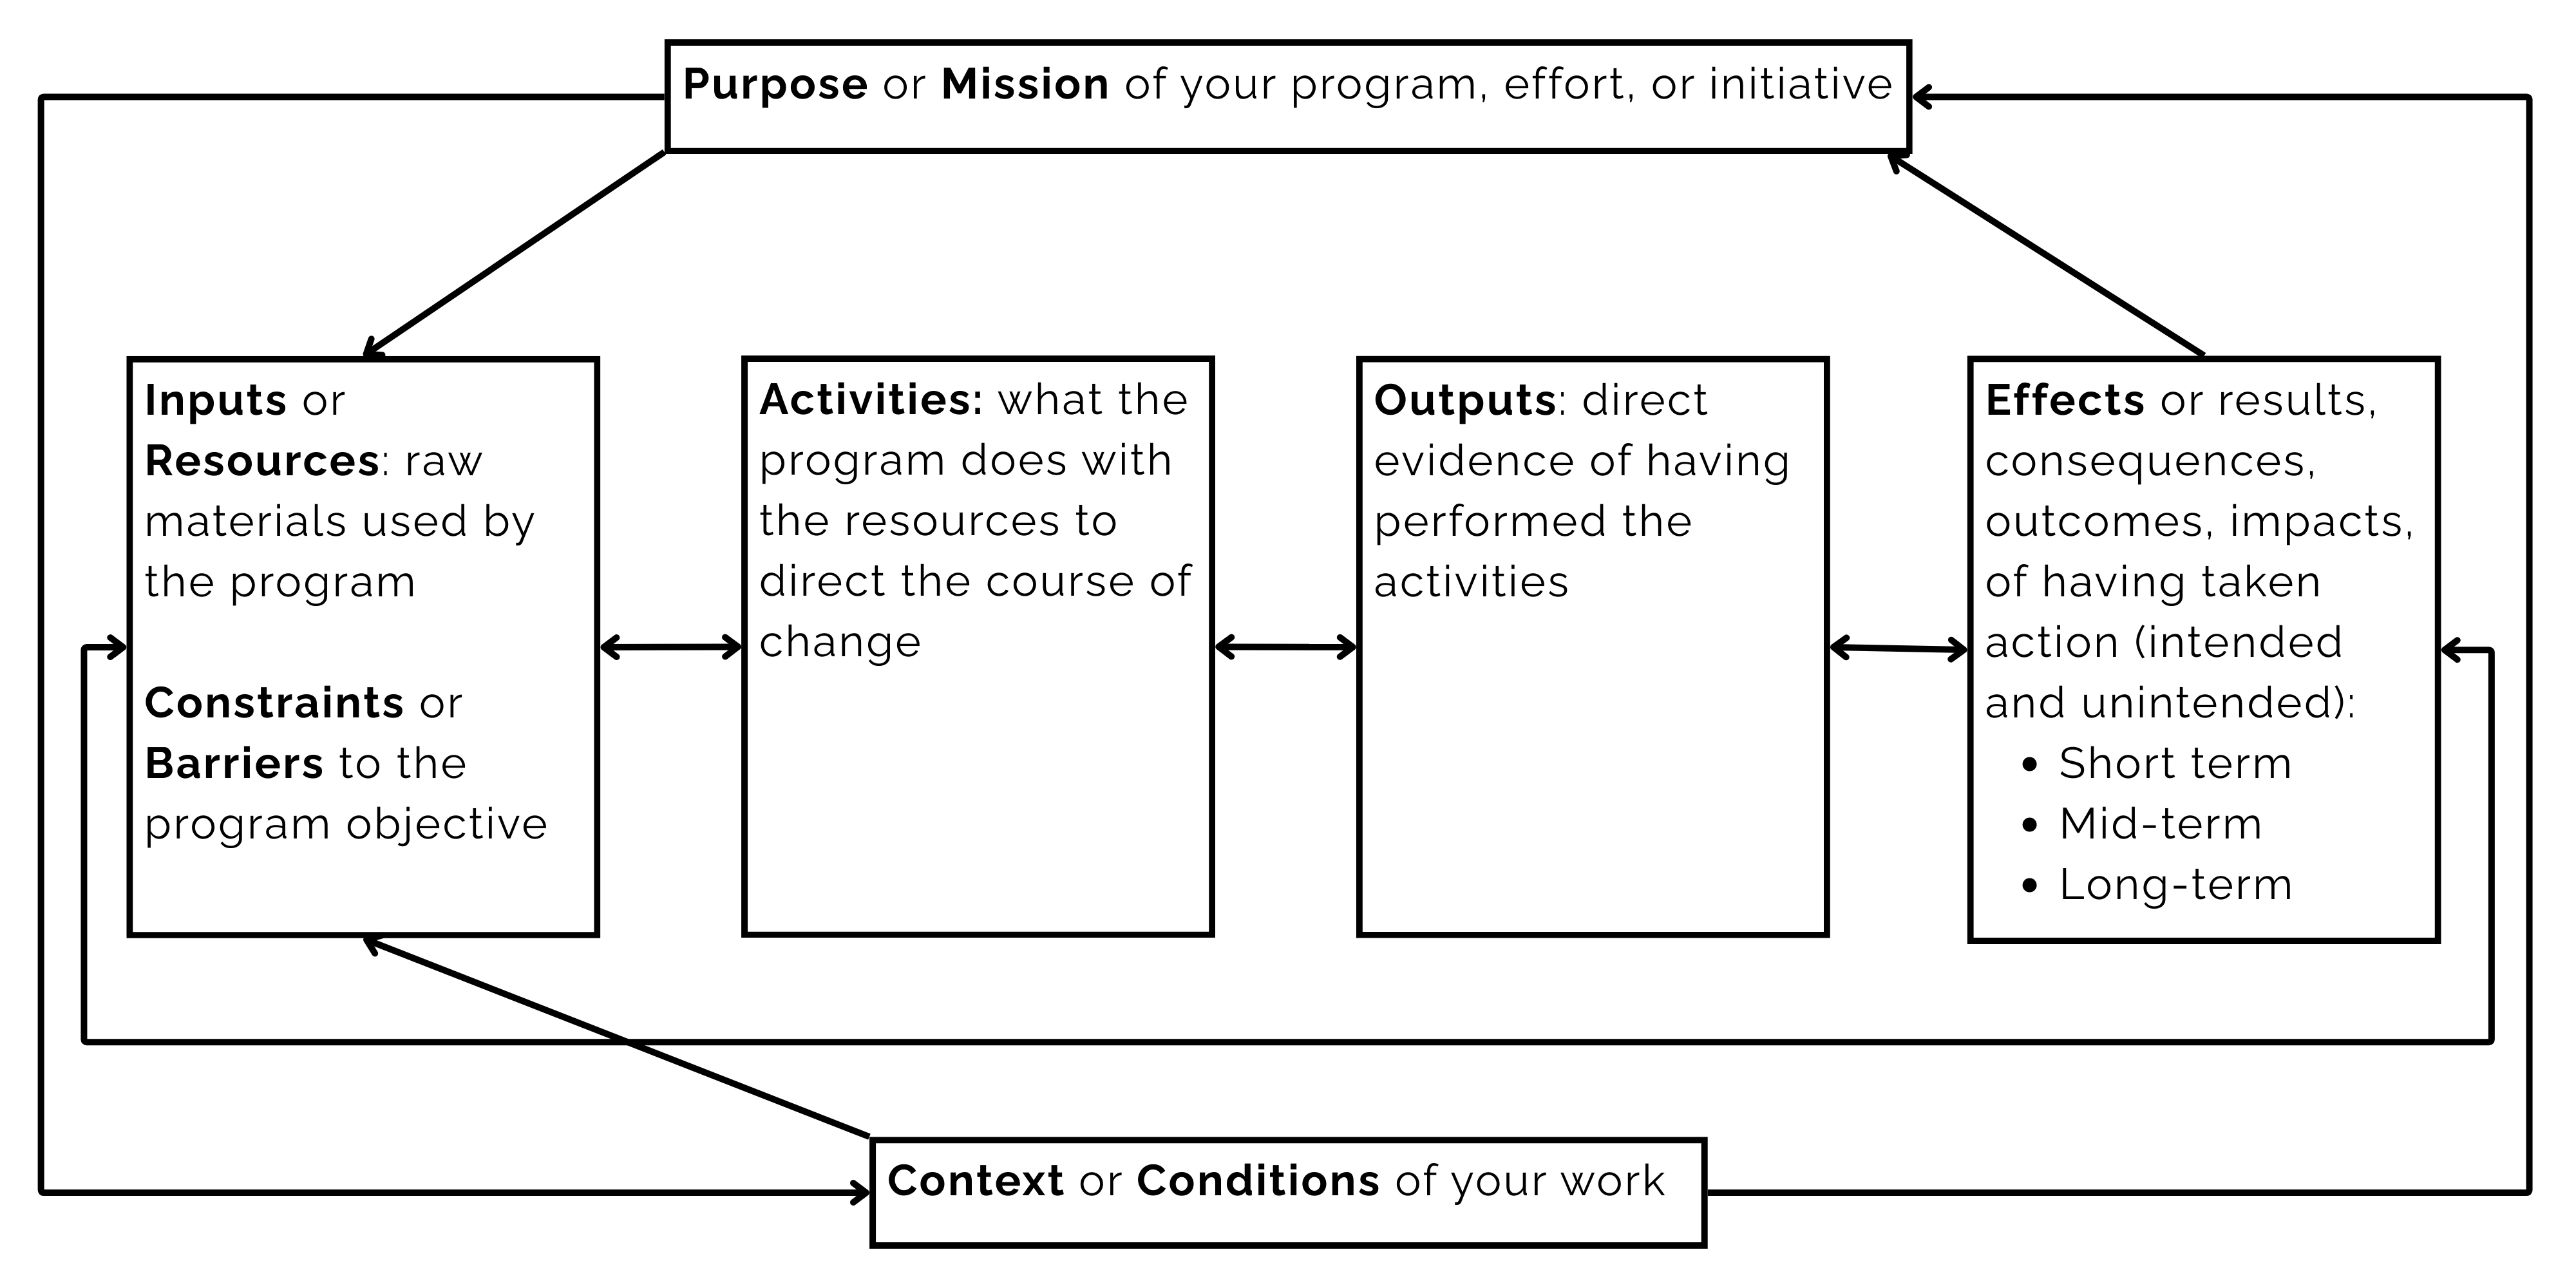
Using this generic model as a template, let's fill in the details with another example of a logic model, one that describes a community health effort to prevent tuberculosis.
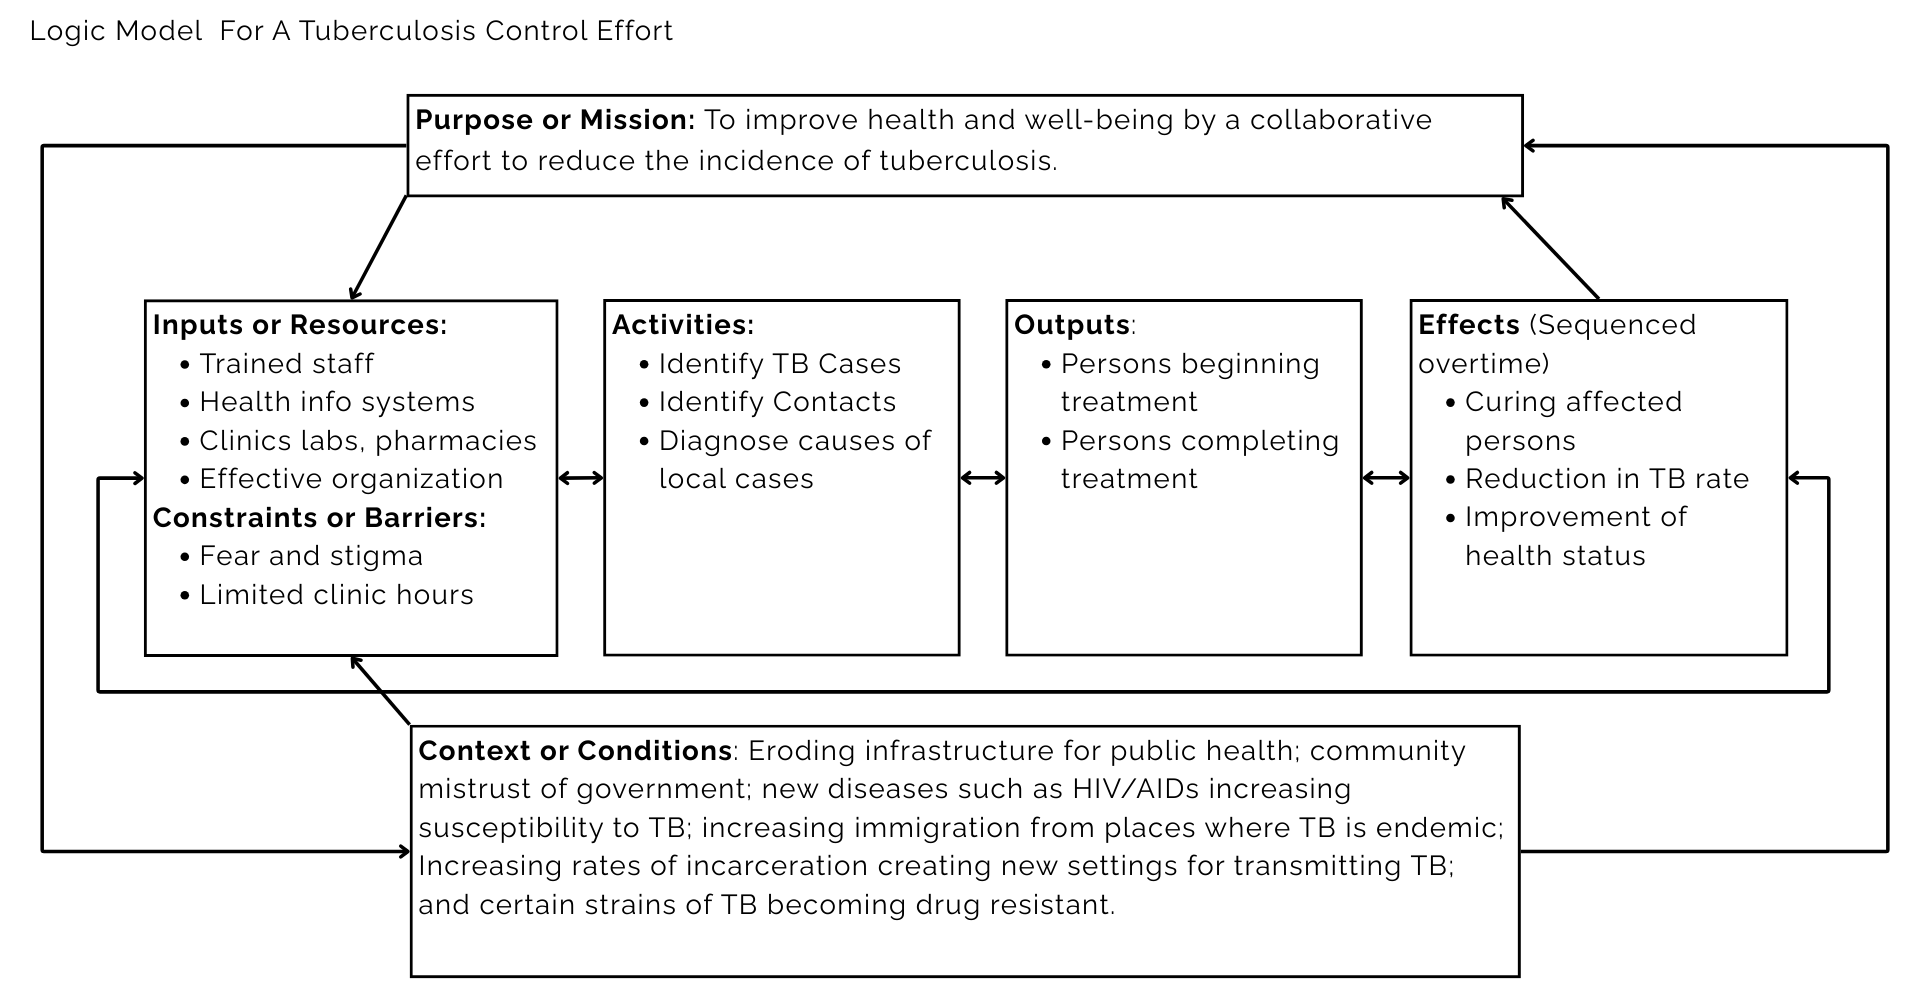
Remember, although this example uses boxes and arrows, you and your partners in change can use any format or imagery that communicates more effectively with your stakeholders.
As mentioned earlier, the generic model for Disease/Injury Control and Prevention in Examples depicts the same relationship of activities and effects in a linear and a nonlinear format. The two formats helped communicate with different groups of stakeholders and made different points.
The linear model better guided discussions of cause and effect and how far down the chain of effects a particular program was successful. The circular model more effectively depicted the interdependence of the components to produce the intended effects.
When exploring the results of an intervention, remember that there can be long delays between actions and their effects. Also, certain system changes can trigger feedback loops, which further complicate and delay our ability to see all the effects. A definition from the System Dynamics Society may help here: "Feedback refers to the situation of X affecting Y and Y in turn affecting X perhaps through a chain of causes and effects. One cannot study the link between X and Y and, independently, the link between Y and X and predict how the system will behave. Only the study of the whole system as a feedback system will lead to correct results."
For these reasons, logic models indicate when to expect certain changes. Many planners like to use the following three categories of effects (illustrated in the models above), although you may choose to have more or fewer depending on your situation.
- Short-term or immediate effects. (In the On Track example, this would be that young people who participate in mentoring improve their self-confidence and understand the importance of staying in school.)
- Mid-term or intermediate effects. (Mentored students improve their grades and remain in school.)
- Longer-term or ultimate effects. (High school graduation rates rise, thus giving graduates more employment opportunities, greater financial stability, and improved health status.)
Here are two important notes about constructing and refining logic models.
Outcome or Impact?
Clarify your language. In a collaborative project, it is wise to anticipate confusion over language. If you understand the basic elements of a logic model, any labels can be meaningful provided stakeholders agree to them. In the generic and TB models above, we called the effects short-, mid-, and long-term. It is also common to hear people talk about effects that are "upstream" or "proximal" (near to the activities) versus "downstream" or "distal" (distant from the activities). Because disciplines have their own jargon, stakeholders from two different fields might define the same word in different ways.
Some people are trained to call the earliest effects "outcomes" and the later ones "impacts." Other people are taught the reverse: "impacts" come first, followed by "outcomes." The idea of sequence is the same regardless of which terms you and your partners use. The main point is to clearly show connections between activities and effects over time, thus making explicit your initiative's assumptions about what kinds of change to expect and when. Try to define essential concepts at the design stage and then be consistent in your use of terms. The process of developing a logic model supports this important dialogue and will bring potential misunderstandings into the open.
For good or for ill?
Understand effects. While the starting point for logic modeling is to identify the effects that correspond to stated goals, your intended effects are not the only effects to watch for. Any intervention capable of changing problem behaviors or altering conditions in communities can also generate unintended effects. These are changes that no one plans and that might somehow make the problem worse.
Many times our efforts to solve a problem lead to surprising, counterintuitive results. There is always a risk that our "cure" could be worse than the "disease" if we're not careful. Part of the added value of logic modeling is that the process creates a forum for scrutinizing big leaps of faith, a way to search for unintended effects. (See the discussion of simulation in "What makes a logic model effective" for some thoughts on how to do this in a disciplined manner.)
One of the greatest rewards for the extra effort is the ability to spot potential problems and redesign an initiative (and its logic model) before the unintended effects get out of hand, so that the model truly depicts activities that will plausibly produce the intended effects.
Choosing the right level of detail: the importance of utility and simplicity
It may help at this point to consider what a logic model is not. Although it captures the big picture, it is not an exact representation of everything that's going on. All models simplify reality; if they didn't, they wouldn't be of much use.
Even though it leaves out information, a good model represents those aspects of an initiative that, in the view of your stakeholders, are most important for understanding how the effort works. In most cases, the developers will go through several drafts before producing a version that the stakeholders agree accurately reflects their story.
Should the information become overly complex, it is possible to create a family of related models, or nested models, each capturing a different level of detail. One model could sketch out the broad pathways of change, whereas others could elaborate on separate components, revealing detailed information about how the program operates on a deeper level. Individually, each model conveys only essential information, and together they provide a more complete overview of how the program or initiative functions. (See "How do you create a logic model?" for further details.)
Imagine "zooming in" on the inner workings of a specific component and creating another, more detailed model just for that part. For a complex initiative, you may choose to develop an entire family of such related models that display how each part of the effort works, as well as how all the parts fit together. In the end, you may have some or all of the following family of models, each one differing in scope:
- View from Outer Space. This overall roadmap shows the major pathways of change and the full spectrum of effects. This view answers questions such as: Do the activities follow a single pathway, or are there separate pathways that converge down the line? How far does the chain of effects go? How do our program activities align with those of other organizations? What other forces might influence the effects that we hope to see? Where can we anticipate feedback loops and in what direction will they travel? Are there significant time delays between any of the connections?
- View from the Mountaintop. This closer view focuses on a specific component or set of components, yet it is still broad enough to describe the infrastructure, activities, and full sequence of effects. This view answers the same questions as the view from outer space, but with respect to just the selected component(s).
- You Are Here. This view expands on a particular part of the sequence, such as the roles of different stakeholders, staff, or agencies in a coalition, and functions like a flowchart for someone's work plan. It is a specific model that outlines routine processes and anticipated effects. This is the view that you might need to understand quality control within the initiative.
Families, Nesting, and Zooming In
In the Examples section, the idea of nested models is illustrated in the Tobacco Control family of models. It includes a global model that encompasses three intermediate outcomes in tobacco control -- environments without tobacco smoke, reduced smoking initiation among young people, and increased cessation among young people and adults. Then a zoom-in model is elaborated for each one of these intermediate outcomes.The Comprehensive Cancer model illustrates a generic logic model accompanied by a zoom-in on the activities to give program staff the specific details they need. Notably, the intended effects on the zoom-in are identical to those on the global model and all major categories of activities are also apparent. But the zoom-in unpacks these activities into their detailed components and, more important, indicates that the activities achieve their effects by influencing intermediaries who then move gatekeepers to take action. This level of detail is necessary for program staff, but it may be too much for discussions with funders and stakeholders.
The Diabetes Control model is another good example of a family of models. In this case, the zoom-in models are very similar to the global model in level of detail. They add value by translating the global model into a plan for specific actors (in this case a state diabetes control program) or for specific objectives (e.g., increasing timely foot exams).
When can a logic model be used?
Logic models are useful for both new and existing programs and initiatives. If your effort is being planned, a logic model can help get it off to a good start. Alternatively, if your program is already underway, a model can help you describe, modify, or enhance it.
Planners, program managers, trainers, evaluators, advocates, and other stakeholders can use a logic model in several ways throughout an initiative. One model may serve more than one purpose, or it may be necessary to create different versions tailored for different aims. Here are examples of the various times that a logic model could be used.
During planning to:
- clarify program strategy
- identify appropriate outcome targets (and avoid over-promising)
- align your efforts with those of other organizations
- write a grant proposal or a request for proposals
- assess the potential effectiveness of an approach
- set priorities for allocating resources
- estimate timelines
- identify necessary partnerships
- negotiate roles and responsibilities
- focus discussions and make planning time more efficient
During implementation to:
- provide an inventory of what you have and what you need to operate the program or initiative
- develop a management plan
- incorporate findings from research and demonstration projects
- make mid-course adjustments
- reduce or avoid unintended effects
During staff and stakeholder orientation to:
- explain how the overall program works
- show how different people can work together
- define what each person is expected to do
- indicate how one would know if the program is working
During evaluation to:
- document accomplishments
- organize evidence about the program
- identify differences between the ideal program and its real operation
- determine which concepts will (and will not) be measured
- frame questions about attribution (of cause and effect) and contribution (of initiative components to the outcomes)
- specify the nature of questions being asked
- prepare reports and other media
- tell the story of the program or initiative
During advocacy to:
- justify why the program will work
- explain how resource investments will be used
How do you create a logic model?
There is no single way to create a logic model. Think of it as something to be used, its form and content governed by the users' needs.
Who creates the model? This depends on your situation. The same people who will use the model -- planners, program managers, trainers, evaluators, advocates, and other stakeholders -- can help create it. For practical reasons, though, you will probably start with a core group, and then take the working draft to others for continued refinement.
Remember that your logic model is a living document, one that tells the story of your efforts in the community. As your strategy changes, so should the model. On the other hand, while developing the model you might see new pathways that are worth exploring in real life.
Two main development strategies are usually combined when constructing a logic model.
- Moving forward from the activities (also known as forward logic). This approach explores the rationale for activities that are proposed or currently underway. It is driven by "But why?" questions or if-then thinking: But why should we focus on briefing Senate staff? But why do we need them to better understand the issues affecting young people? But why would they create policies and programs to support mentoring? But why would new policies make a difference?... and so on. That same line of reasoning could also be uncovered using if-then statements: If we focus on briefing legislators, then they will better understand the issues affecting young people. If legislators understand, then they will enact new policies...
- Moving backward from the effects (also known as reverse logic). This approach begins with the end in mind. It starts with a clearly identified value, a change that you and your colleagues would definitely like to see occur, and asks a series of "But how?" questions: But how do we overcome fear and stigma? But how can we ensure our services are culturally responsive? But how can we admit that we don't already know what we're doing?
At first, you may not agree with the answers that certain stakeholders give for these questions. Their logic may not seem convincing or even logical. But therein lies the power of logic modeling. By making each stakeholder's thinking visible on paper, you can decide as a group whether the logic driving your initiative seems reasonable. You can talk about it, clarify misinterpretations, ask for other opinions, check the assumptions, compare them with research findings, and in the end develop a solid system of program logic. This product then becomes a powerful tool for planning, implementation, orientation, evaluation, and advocacy, as described above.
By now you have probably guessed that there is not a rigid step-by-step process for developing a logic model. Like the rest of community work, logic modeling is an ongoing process. Nevertheless, there are a few tasks you should be sure to accomplish.
To illustrate these in action, we'll use another example for an initiative called "HOME: Home Ownership Mobilization Effort." HOME aims to increase homeownership in order to give neighborhood control to the people who live there, rather than to outside property owners with little connection to the community. It does this through a combination of educating community residents, organizing the neighborhood, and building relationships with partners such as businesses.
Steps for drafting a logic model
- Find the logic in existing written materials to produce your first draft.
- Available written materials often contain more than enough information to get started. Collect narrative descriptions, justifications, grant applications, or overview documents that explain the basic idea behind the intervention effort. If your venture involves a coalition of several organizations, be sure to get descriptions from each agency's point of view. For the HOME campaign, we collected documents from planners who proposed the idea, as well as mortgage companies, homeowner associations, and other neighborhood organizations.
- Your job as a logic modeler is to decode these documents. Keep a piece of paper by your side and sketch out the logical links as you find them. (This work can be done in a group to save time and engage more people if you prefer.)
- Read each document with an eye for the logical structure of the program. Sometimes that logic will be clearly spelled out (e.g., The information, counseling, and support services we provide to community residents will help them improve their credit rating, qualify for home loans, and purchase homes in the community; over time, this program will change the proportion of owner-occupied housing in the neighborhood).
- Other times the logic will be buried in vague language, with big leaps from actions to downstream effects (e.g., Ours is a comprehensive community-based program that will transform neighborhoods, making them controlled by people who live there and not outsiders with little connection to the community).
- As you read each document, ask yourself the "But why?" and "But how?" questions. See if the writing provides an answer. Pay close attention to parts of speech. Verbs such as teach, inform, support, or refer are often connected to descriptions of program activities. Adjectives like reduced, improved, higher, or better are often used when describing expected effects.
- Determine the appropriate scope of the model for its intended users and uses. Consider creating a family of models for multiple users.
- The HOME initiative, for instance, created different models to address the unique needs of its financial partners, program managers, and community educators. Mortgage companies, grantmakers, and other decisionmakers who decided whether to allocate resources for the effort found the global view from space most helpful for setting context. Program managers wanted the closer, yet still broad view from the mountaintop. And community educators benefited most from the You Are Here version. The important thing to remember is that these are not three different programs, but different ways of understanding how the same program works.
- Check whether the model makes sense and is complete.
- Logic models convey the story of community change. Working with the stakeholders, it's your responsibility to ensure that the story you've told in your draft makes sense (i.e., is logical) and is complete (has no loose ends). As you iteratively refine the model, ask yourself and others if it captures the full story.
- Here are the plot points common in most community change initiatives, presented with their "storytelling" names.
- The Promised Land (desired effects). Does the model show specific measurable results that you hope to achieve? Does it contain big leaps of faith or does it show change through a logical sequence of effects? Are crucial behavioral changes identified (e.g., more applications for homeownership, increased home buying, greater engagement in community and civic affairs, etc.)? And if those behavior changes are supposed to be sustained, does the model explain how community conditions will change to reinforce new behaviors (e.g., homeowner support groups, tax cuts on owner-occupied housing, discounts at the local hardware store for customers who own property in the neighborhood, etc.)? In the HOME model, we specified the following sequence of effects:
- Short-term -- Potential homeowners attain greater understanding of how credit ratings are calculated and more accurate information about the steps to improve a credit rating; mortgage companies create new policies and procedures allowing renters to buy their own homes; local businesses start incentive programs; and anti-discrimination lawsuits are filed against illegal lending practices.
- Mid-term -- The community's average credit rating improves; applications rise for home loans along with the approval rate; support services are established for first-time homebuyers; neighborhood organizing gets stronger; and alliances expand to include businesses, health agencies, and elected officials.
- Longer-term -- The proportion of owner-occupied housing rises; economic revitalization takes off as businesses invest in the community; residents work together to create walking trails, crime patrols, and fire safety screenings; and rates of obesity, crime, and injury are expected to fall.
- An advantage of the graphic model is that it can display both the sequence and the interactions of effects. For example, in the HOME model, credit counseling leads to better understanding of credit ratings, while loan assistance leads to more loan submissions, but the two together (plus other activities such as more new-buyer programs) are needed for increased homeownership.
- The Promised Land (desired effects). Does the model show specific measurable results that you hope to achieve? Does it contain big leaps of faith or does it show change through a logical sequence of effects? Are crucial behavioral changes identified (e.g., more applications for homeownership, increased home buying, greater engagement in community and civic affairs, etc.)? And if those behavior changes are supposed to be sustained, does the model explain how community conditions will change to reinforce new behaviors (e.g., homeowner support groups, tax cuts on owner-occupied housing, discounts at the local hardware store for customers who own property in the neighborhood, etc.)? In the HOME model, we specified the following sequence of effects:
- Drama (activities, interventions). How will obstacles be overcome? Who is doing what? What kinds of conflict and cooperation are evident? What's being done to rearrange the forces of change? What new services or conditions are being introduced? Your activities, based on a clear analysis of risk and protective factors, are the answers to these kinds of questions. Your interventions reveal the drama in your story of directed social change.
Dramatic actions in the HOME initiative include offering educational sessions and forming business alliances, homeowner support groups, and a neighborhood organizing council. At evaluation time, each of these actions is closely connected to output indicators that document whether the program is on track and how fast it is moving. These outputs could be the number of educational sessions held, their average attendance, the size of the business alliance, etc. (These outputs are not depicted in the global model, but that could be done if valuable for users.)
- Raw Materials (inputs, resources, or infrastructure). The energy to create change can't come from nothing. Real resources must come into the system. Those resources may be financial, but they may also include people, space, information, technology, equipment, and other assets. The HOME campaign runs because of the input from volunteer educators, support from schools and faith institutions in the neighborhood, discounts provided by lenders and local businesses, revenue from neighborhood revitalization, and increasing social capital among community residents.
- Setting (background, context, and conditions). Really good stories convey facts, but they also have texture. There is a backdrop against which the main action takes place. Community change always takes place in the context of history, geography, politics, etc. Although it is impossible to represent all of those factors in a model, you can strive to include features that remind users those conditions exist and will affect how change unfolds.
- Stakeholders working on the HOME campaign understood that they were challenging a history of racial discrimination and economic injustice. They saw gentrification occurring in nearby neighborhoods. They were aware of backlash from outside property owners who benefit from the status quo. None of these facts are included in the model per se, but a shaded box labeled History and Context was added to serve as a visual reminder that these things are in the background.
- Attend to the nuts and bolts of drawing the model.
- Draft the logic model using both sides of your brain and all the talents of your stakeholders. Use your artistic and your analytic abilities.
- Arrange activities and intended effects in the expected time sequence. And don't forget to include important feedback loops -- after all, most actions provoke a reaction.
- Link components by drawing arrows or using other visual methods that communicate the order of activities and effects. (Remember -- the model does not have to be linear or read from left to right, top to bottom. A circle may better express a repeating cycle.)
- Allow yourself plenty of space to develop the model. Freely revise the picture to show the relationships better or to add components.
- Neatness counts, so avoid overlapping lines and unnecessary clutter.
- Color-code regions of the model to help convey the main storyline.
- Try to keep everything on one page. When the model gets too crowded, either adjust its scope or build nested models.
- Make sure it passes the "laugh test." That is, be sure that the image you create isn't so complex that it provokes an immediate laugh from stakeholders. Of course, different stakeholders will have different laugh thresholds.
- Use presentation or diagramming software to animate or build the model step by step so that, when you present it to an audience, people can follow the logic behind every connection.
- Revisit and be ready to revise the model as necessary.
- Don't let your model become a tedious exercise that you did just to satisfy someone else. Don't let it sit in a drawer. Once you've gone through the effort of creating a model, the rewards are in its use. Revisit it often and be prepared to make changes. All programs evolve and change over time, if only to keep up with changing conditions in the community. Like a roadmap, a good model will help you to recognize new or reinterpret old territory.
- Also, when things are changing rapidly, it's easy for collaborators to lose sight of their common goals. Having a well-developed logic model can keep stakeholders focused on achieving outcomes while remaining open to finding the best means for accomplishing the work. If you need to take a detour or make a longer stop, the model serves as a framework for incorporating the change.
- As you improve, modify, or realign your model, take stock of emerging activities and effects. You might need to do one or more of the following:
- Clarify the path of activities to effects and outcomes
- Elaborate links
- Expand activities to reach your goals
- Establish or revise mile markers
- Redefine the boundary of your initiative or program
- Reframe goals or desired outcomes
What makes a logic model effective?
You will know a model's effectiveness mainly by its usefulness to intended users. A good logic model usually:
- Logically links activities and effects
- Is visually engaging (simple, parsimonious) yet contains the appropriate degree of detail for the purpose (not too simple or too confusing)
- Provokes thought and triggers questions
- Includes forces known to influence the desired outcomes
The more complete your model, the better your chances of reaching "the Promised Land" of the story. In order to tell a complete story or present a complete picture in your model, make sure to consider all forces of change (root causes, trends, and system dynamics). Does your model reveal assumptions and hypotheses about the root causes and feedback loops that contribute to problems and their solutions?
In the HOME model, for instance, low homeownership persists when there is a vicious cycle of discrimination, lower credit scores, and feelings of hopelessness that prevent neighborhood-wide organizing and social change. Three pathways of change were proposed to break that cycle: education, business reform, and neighborhood organizing. Building a model on one pathway to address only one force would limit the program's effectiveness.
You can discover forces of change in your situation using multiple assessment strategies, including forward logic and reverse logic as described above. When exploring forces of change, be sure to search for personal factors (knowledge, beliefs, skills) as well as environmental factors (barriers, opportunities, support, incentives) that keep the situation the same as well as ones that push for it to change.
Take time to simulate
After you've mapped out the structure of a program strategy, there is still another crucial step to take before taking action: some kind of simulation. As logical as the story you are telling seems to you, as a plan for intervention it runs the risk of failure if you haven't explored how things might turn out in the real world of feedback and resistance.
Simulation is one practical way to find out if a seemingly sensible plan will actually play out as you hope. Simulation is not the same as testing a model with stakeholders to see if it makes logical sense. The point of a simulation is to explore how things may change -- how the system may behave -- over time and under different conditions.
Though simulation is a powerful tool, it can be conducted in ways ranging from the simple to the sophisticated.
- Simulation can be as straightforward as an unstructured role-playing game, in which you talk the model through to its logical conclusions.
- In a more structured simulation, you could develop a tabletop exercise in which you proceed step by step through a given scenario with predefined roles and responsibilities for the participants.
- Ultimately, you could create a computer-based mathematical simulation using available software tools.
The key point to remember is that creating logical models and simulating how those models may behave involve two different sets of skills, both of which can help in discovering which change strategies may be effective in your community.
What are the benefits and limitations of logic modeling?
You can probably envision a variety of ways in which you might use the logic model you've developed or that logic modeling would benefit your work.
Here are a few advantages that experienced modelers have discovered.
- Logic models integrate planning, implementation, and evaluation. As a detailed description of your initiative, from resources to results, the logic model is equally important for planning, implementing, and evaluating the project. If you are a planner, the modeling process challenges you to think more like an evaluator. If your purpose is evaluation, the modeling prompts discussion of planning. And for those who implement, the modeling answers practical questions about how the work will be organized and managed.
- Logic models prevent mismatches between activities and effects. Planners often summarize an effort by listing its vision, mission, objectives, strategies, and action plans. Even with this information, it can be hard to tell how all the pieces fit together. By connecting activities and effects, a logic model helps avoid proposing activities with no intended effect, or anticipating effects with no supporting activities. The ability to spot such mismatches easily is perhaps the main reason why so many logic models use a flowchart format.
- Logic models leverage the power of partnerships. As the W.K. Kellogg Foundation notes (see Internet Resources below), refining a logic model is an iterative or repeating process that allows participants to make changes based on consensus-building and a logical process rather than on personalities, politics, or ideology. With a well-specified logic model, it is possible to note where the baton should be passed from one person or agency to another. This enhances collaboration and guards against things falling through the cracks.
- Logic models enhance accountability by keeping stakeholders focused on outcomes. As Connie Schmitz and Beverly Parsons point out (see Internet Resources), a list of action steps usually functions as a manager's guide for running a project, showing what staff or others need to do -- for example, "Hire an outreach worker for a TB clinic." With a logic model, however, it is also possible to illustrate the effects of those tasks -- for example, "Hiring an outreach worker will result in a greater proportion of people coming into the clinic for treatment." This short-term effect then connects to mid- and longer-term effects, such as "Satisfied patients refer others to the clinic" and "Improved screening and treatment coverage results in fewer deaths due to TB."
In a coalition or collaborative partnership, the logic model makes it clear which effects each partner creates and how all those effects converge to a common goal. The family or nesting approach works well in a collaborative partnership because a model can be developed for each objective along a sequence of effects, thereby showing layers of contributions and points of intersection.
- Logic models help planners set priorities for allocating resources. A comprehensive model will reveal where physical, financial, human, and other resources are needed. When planners are discussing options and setting priorities, a logic model can help them make resource-related decisions in light of how the program's activities and outcomes will be affected.
- Logic models reveal data needs and provide a framework for interpreting results. It is possible to design a documentation system that includes only beginning and end measurements. This is a risky strategy with a good chance of yielding disappointing results. An alternative approach calls for tracking changes at each step along the planned sequence of effects. With a logic model, program planners can identify intermediate effects and define measurable indicators for them.
- Logic models enhance learning by integrating research findings and practice wisdom. Most initiatives are founded on assumptions about the behaviors and conditions that need to change, and how they are subject to intervention. Frequently, there are different degrees of certainty about those assumptions. For example, some of the links in a logic model may have been tested and shown to be sound through previous research. Other linkages, by contrast, may never have been researched, and indeed may never have been tried or thought of before. The explicit form of a logic model means that you can combine evidence-based practices from prior research with innovative ideas that experienced practitioners believe will make a difference. A logic model also makes it easier to show the reasoning and evidence behind your work.
- Logic models define a shared language and shared vision for community change. The terms used in a model help to standardize the way people think and how they speak about community change. It gets everyone rowing in the same direction, and enhances communication with external audiences, such as the media or potential funders. Even stakeholders who are skeptical or opposed to your work can be drawn into the discussion and development of a logic model. Once you've got them talking about the logical connections between activities and effects, they're no longer simply criticizing from the sidelines. They can become engaged in problem-solving in an open forum where assumptions, disagreements, and different views of how change happens can be examined.
Limitations
Any tool this powerful must not be approached lightly. When you undertake the task of developing a logic model, be aware of the following challenges and limitations.
First, no matter how logical your model seems, there is always a danger that it will not be correct. The world sometimes works in surprising, counterintuitive ways, which means we may not comprehend the logic of change until after the fact. With this in mind, modelers will appreciate the fact that the real effects of intervention actions could differ from the intended effects. Certain actions might even make problems worse, so it's important to keep one eye on the plan and another focused on the real-life experiences of community members.
If nothing else, a logic model ought to be logical. Therein lies its strength and its weakness. Those who are trying to follow your logic will magnify any inconsistency or inaccuracy. This places a high burden on modelers to pay attention to detail and refine their own thinking to a great degree. Of course, no model can be perfect. You'll have to decide on the basis of stakeholders' uses what level of precision is required.
Establishing the appropriate boundaries of a logic model can be a difficult challenge. In most cases, there is a tension between focusing on a specific program and situating that effort within its broader context. Many models seem to suggest that the only forces of change come from within the program in question, as if there is only one child in the sandbox.
At the other extreme, it would be ridiculous and unproductive to map all the simultaneous forces of change that affect health and community development. A modeler's challenge is to include enough depth so the organizational context is clear, without losing sight of the reasons for developing a logic model in the first place.
On a purely practical level, logic modeling can also be time-consuming, requiring much energy in the beginning and continued attention throughout the life of an initiative. The process can demand a high degree of specificity; it risks oversimplifying complex relationships and relies on the ability to represent complex thought processes visually.
Indeed, logic models can be very difficult to create, but the process of creating them, as well as the product, can yield many benefits over the course of an initiative.
In Summary
A logic model is a story or picture of how an effort or initiative is supposed to work. The process of developing the model brings together stakeholders to articulate the goals of the program and the values that support it, and to identify strategies and desired outcomes of the initiative.
As a means to communicate a program visually, within your coalition or work group and to external audiences, a logic model provides a common language and reference point for everyone involved in the initiative.
A logic model is useful for planning, implementing, and evaluating an initiative. It helps stakeholders agree on short-term as well as long-term objectives during the planning process, outline activities and actors, and establish clear criteria for evaluation during the effort. When the initiative ends, it provides a framework for assessing overall effectiveness of the initiative, as well as the activities, resources, and external factors that played a role in the outcome.
To develop a model, you will probably use both forward and reverse logic. Working backward, you begin with the desired outcomes and then identify the strategies and resources that will accomplish them. Combining this with forward logic, you will choose certain steps to produce the desired effects.
You will probably revise the model periodically, and that is precisely one advantage to using a logic model. Because it relates program activities to their effects, it helps keep stakeholders focused on achieving outcomes, while it remains flexible and open to finding the best means to enact a unique story of change.
Contributor
Bobby Milstein
Tom Chapel
Resources
Online Resources
In this video series from CADCA’s Mid-year Training Institute, Paul Evensen introduces key concepts and provides an orientation to issue analysis and logic modeling. He explains classic representational logic models, explains the value of metaphor-based logic models for communicating cause and effect using familiar shapes or objects, and offers guidance on how to critique and strengthen logic models. The series also covers integrated issue logic modeling to help communities connect multiple factors and strategies into a cohesive framework.
The Community Builder’s Approach to Theory of Change: A Practical Guide to Theory Development, from The Aspen Institute’s Roundtable on Community Change.
The CDC Evaluation Working Group provides a linked section on logic models in its resources for project evaluation.
The Evaluation Guidebook for Projects Funded by S.T.O.P. Formula Grants under the Violence Against Women Act includes a chapter on developing and using a logic model (Chapter 2), and additional examples of model in the "Introduction to the Resource Chapters."
AEA365, Hot Tips + Rad Resources for Building Logic Models by David Howard offers practical tips, tools, and examples to help community groups and organizations create clear logic models that connect their activities to the outcomes they hope to achieve.
A logic model from Harvard that uses a family/school partnership program.
The CDC Evaluation Working Group provides a linked section on logic models in its resources for project evaluation.
Excerpts from United Way's publication on Measuring Program Outcomes See especially "Program Outcome Model."
Tara Gregory on Using Storytelling to Help Organizations Develop Logic Models discusses techniques to facilitate creative discussion while still attending to the elements in a traditional logic model. These processes encourage participation by multiple staff, administrators and stakeholders and can use the organization’s vision or impact statement as the “happily ever after.”
Theory of Change: A Practical Tool for Action, Results and Learning, prepared by Organizational Research Services.
Theories of Change and Logic Models: Telling Them Apart is a helpful PowerPoint presentation saved as a PDF. It’s from the Aspen Institute Roundtable on Community Change.
University of Wisconsin’s Program Development and Evaluation provides a comprehensive template for a logic model and elaborates on creating and developing logic models.
The U.S. Centers for Disease Control Evaluation Group provides links to a variety of logic model resources.
The W.K. Kellogg Foundation Logic Model Development Guide is a comprehensive source for background information, examples and templates.
Print Resources
American Cancer Society (1998). Stating outcomes for American Cancer Society programs: a handbook for volunteers and staff. Atlanta, GA, American Cancer Society.
Julian, D. (1997). The utilization of the logic model as a system level planning and evaluation device. Evaluation and Program Planning 20(3): 251-257.
McEwan, K., & Bigelow, A. (1997). Using a logic model to focus health services on population health goals. Canadian Journal of Program Evaluation 12(1): 167-174.
McLaughlin, J., & Jordan, B. (1999). Logic models: a tool for telling your program's performance story. Evaluation and Program Planning 22(1): 65-72.
Moyer, A., Verhovsek, et al. (1997). Facilitating the shift to population-based public health programs: innovation through the use of framework and logic model tools. Canadian Journal of Public Health 88(2): 95-98.
Rush, B. & Ogbourne, A. (1991). Program logic models: expanding their role and structure for program planning and evaluation. Canadian Journal of Program Evaluation 6: 95-106.
Taylor-Powell, E., Rossing, B., et al. (1998). Evaluating collaboratives: reaching the potential. Madison, WI, University of Wisconsin Cooperative Extension.
United Way of America (1996). Measuring program outcomes: a practical approach. Alexandria, VA, United Way of America.
Western Center for the Application of Prevention Technologies. (1999) Building a Successful Prevention Program. Reno, NV, Western Center for the Application of Prevention Technologies.
Wong-Reiger, D., & David, L. (1995). Using program logic models to plan and evaluate education and prevention programs. In Love, A. Ed. Evaluation Methods Sourcebook II. Ottawa, Ontario, Canadian Evaluation Society.
What is a logic model?
___You understand the purpose and elements of a logic model as a picture of why and how your effort is supposed to work
___You understand the utility of family, nested, or zoom in models for a complex initiative
___You have an initial plan for how and when to use your logic model
How do you create a logic model?
___Apply forward and/or reverse logic to your effort or initiative
___Create the first draft by finding the logic in existing written materials
___Adjust the model's scope to make it appropriate for intended users and uses
___Create multiple (family, nested, or zoom in) models if needed by users
___Check whether the model makes sense and is complete, including the common plot points
___Attend to the nuts and bolts of drawing the model
___Revisit and revise the model as necessary
These are examples of logic models that other people have found effective. Please note, however, that no other person's or group's logic model can serve as template for your own; even if your initiative is similar, the forces of change and other important details for each effort will differ.
Example 1: Community Health Assessment and Action Planning (CHAAP) Process Improvement Plan in St. Louis County
This logic model lays out St. Louis County’s Department of Public Health and Human Services’ proposed improvement plan to overcome the challenges of protecting vulnerable populations in the event of a disaster.
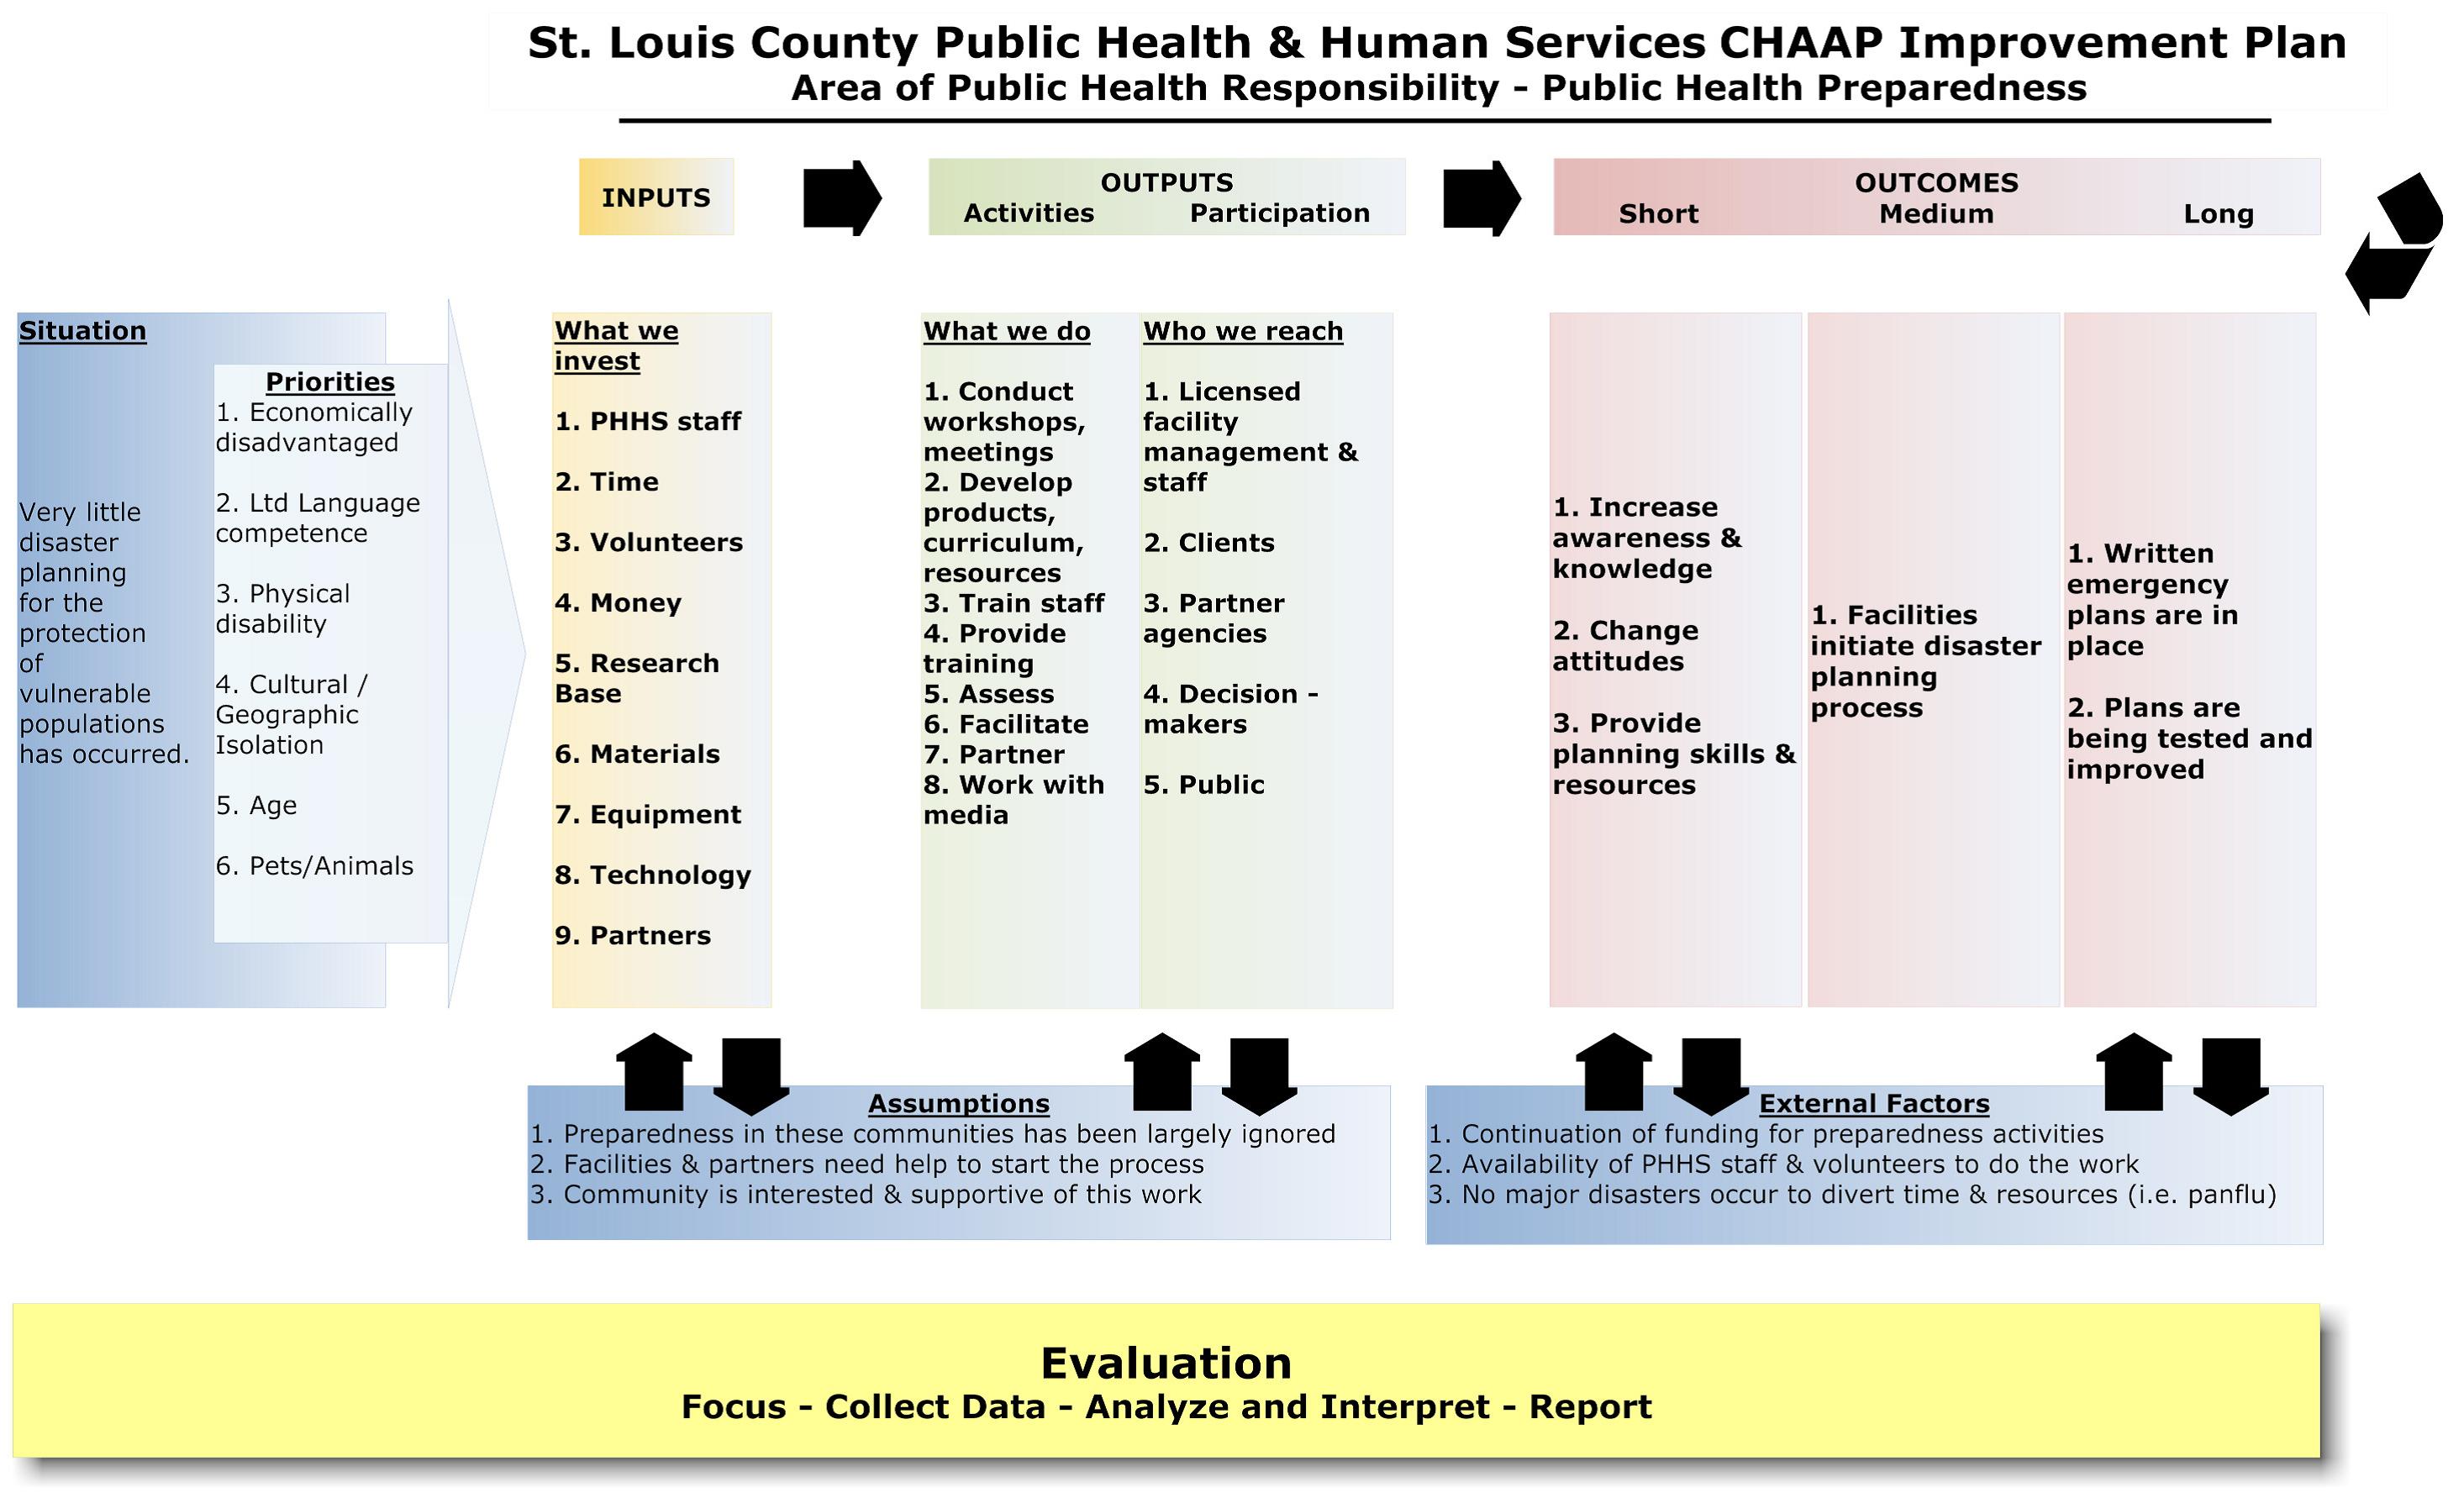
Example 2: Integration of Mental Health into Chronic Disease Prevention Strategies and Health Promotion Efforts
As mental health greatly affects an individual's capacity to participate in health promoting-behaviors, this logic model details possible steps to address mental health and its relationship with chronic disease prevention and health promotion.
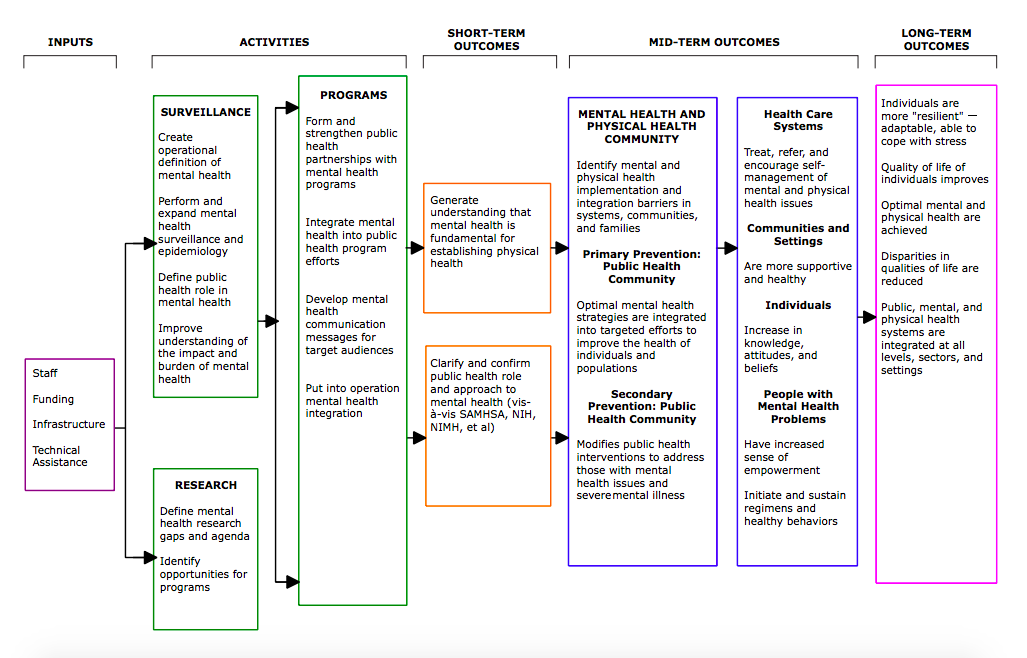
Example 3: Georgia Society for Public Health Education Logic Model
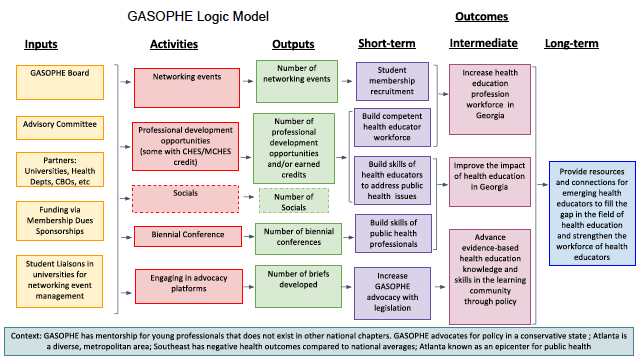
Example 4: Alcohol and Other Drugs (AOD) Education Program Logic Model
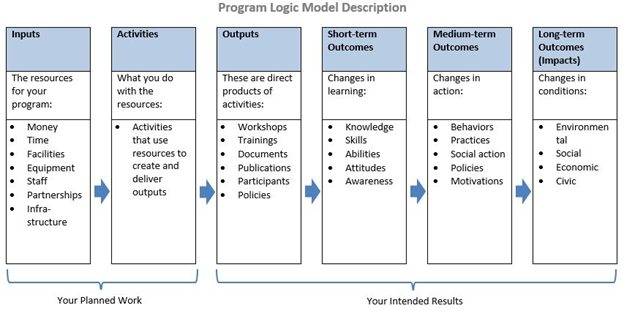
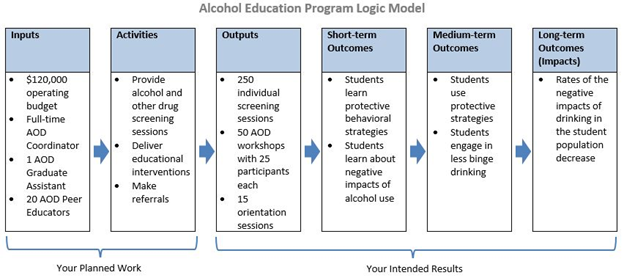
Example 5: National Endowment for the Arts - "Our Town" Logic Model
This logic model was developed by the National Endowment for the Arts for their Creative Placemaking Grants Program deemed "Our Town". The model promotes strengthening communities by advancing local physical, economic, and social outcomes.
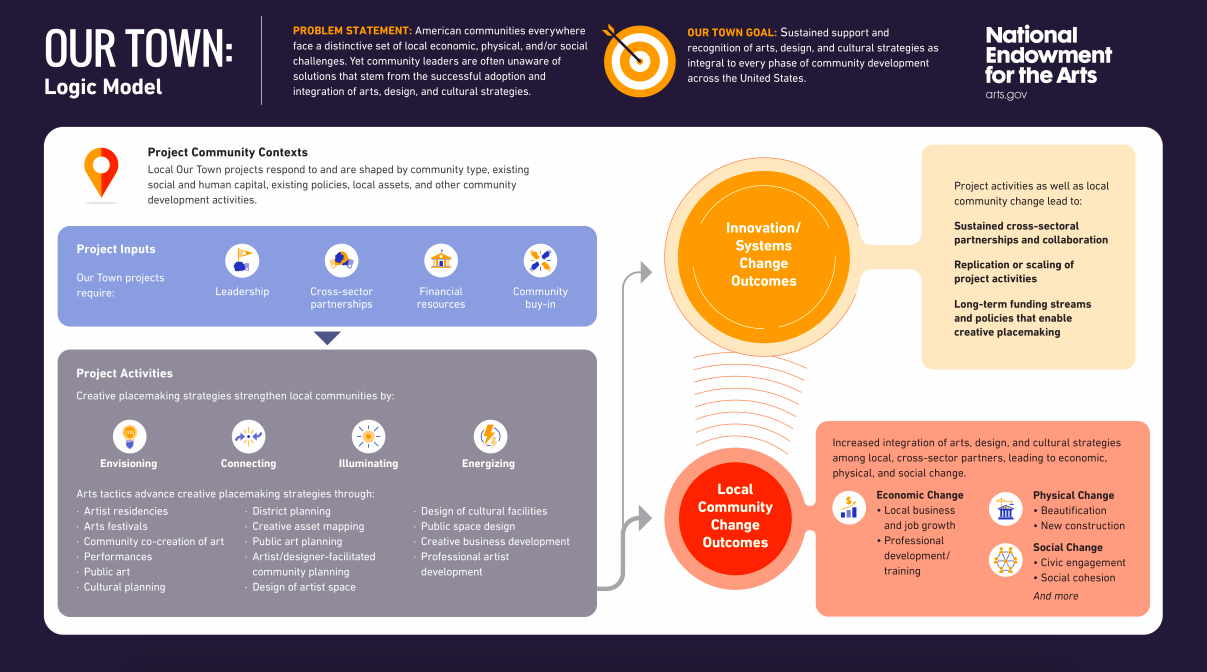
Example 6: CDC Cardiovascular Disease and Stroke Prevention Program Logic Model
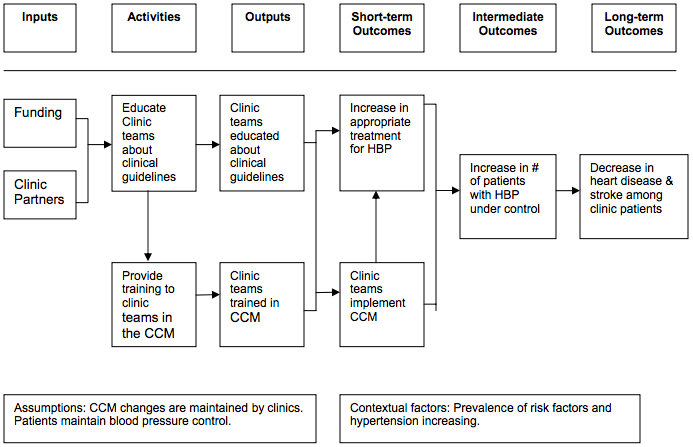
Example 7: LHFA Logic Model / Framework

Example 8: Tenderloin Health Improvement Partnership Logic Model
This logic model helps visualize how TLHIP, an initiative led by the Saint Francis Foundation, works collectively with community partners and other stakeholders to improve the health of Tenderloin residents in downtown San Francisco.
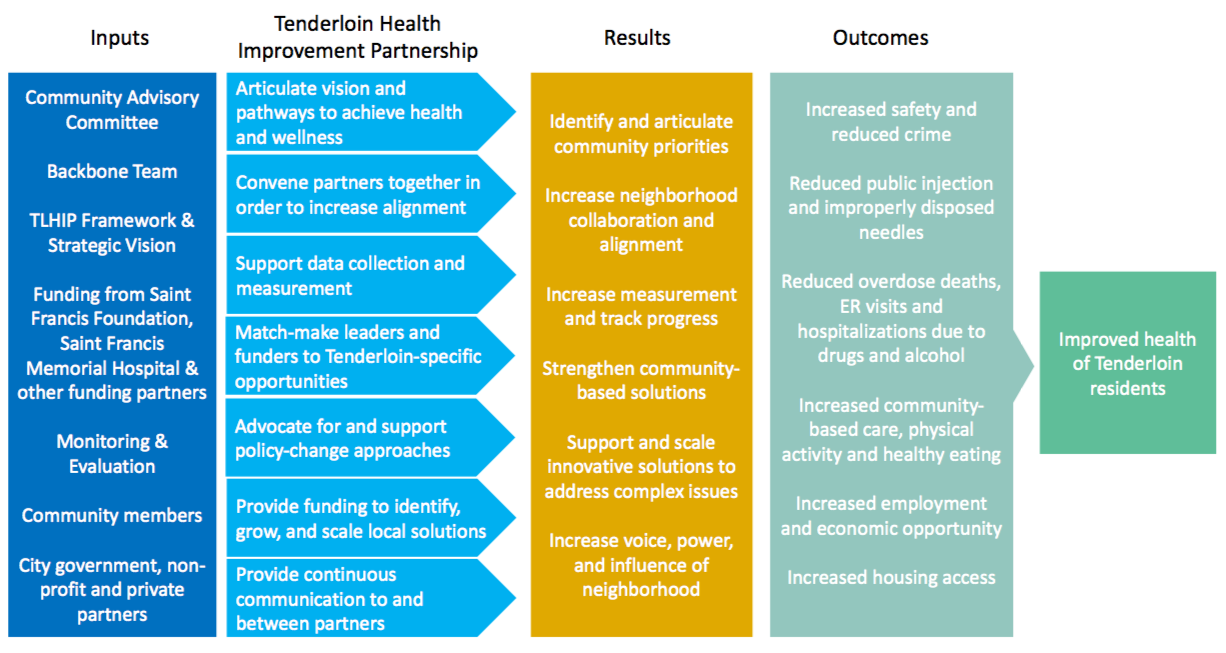
Tool 1: Tearless Logic Model

The Tearless Logic Model breaks down the logic model process into a series of manageable, jargon-free questions. Access the tool.
Tool 2: Logic Model to create a Framework or Model of Change
This logic model template (docx) provides a framework to help begin the process.
If you were a contractor setting out to build a wood-frame house, you wouldn’t just pick up whatever wood you found lying around and begin. You’d consult first with the owner, and start with an idea of the house they wanted – its size, its shape, its features. You’d want a picture of the finished house, and a floor plan as well, with some notes on measurements and materials. You’d plan the construction with them, and set out a process for getting it done. And you’d do all this before you ever picked up a tool, because otherwise the process would be hit-or-miss: they wouldn’t get the house they wanted, and your time would be wasted.
The same is true if you’re developing an intervention to address a health or community issue. It makes no sense to pick an issue at random, and to use whatever service happens to be available to try to address it. You have to consult with the community, understand and analyze community information, your own and others’ observations, and the context of the issue to create an intervention that will actually bring about the changes the community wants and needs.
In the first section of this chapter, we introduced the need for a process for doing health and community work. In this section, we’ll look at PRECEDE-PROCEED, the first of several specific models that may prove helpful to you in carrying out your own work. We’ll examine other models in subsequent sections of this chapter. Then in the last section, we’ll examine some ways in which elements of various models can be combined to respond to your particular situation.
What is PRECEDE-PROCEED?
Like most of the other models we’ll examine in this chapter, PRECEDE-PROCEED was developed for use in public health. Its basic principles, however, transfer to other community issues as well. As a result, we’ll treat it as a model not just for health intervention, but for community intervention in general. And in fact, PRECEDE-PROCEED focuses on the community as the wellspring of health promotion.
During the latter half of the 20th century, chronic conditions such as heart disease, stroke, cancer, and diabetes became increasingly prominent causes of disability and death. The focus of health maintenance, therefore, expanded beyond the treatment of disease to include prevention and, more recently, the active promotion of behaviors and conditions – proper diet, exercise, and reduction of stress, for instance – that can help maintain health and improve the length and quality of life.
Behind PRECEDE-PROCEED lie some assumptions about the prevention of illness and promotion of health, and, by extension, about other community issues as well. These include:
- Since many health-promoting behaviors and activities that individuals engage in are voluntary, carrying out health promotion has to involve the people whose behaviors or actions are affected. PRECEDE-PROCEED should be a participatory process, involving all stakeholders – those affected by the issue or condition in question – from the beginning.
- Health is, by its very nature, a community issue. It is influenced by community attitudes, shaped by the community environment (physical, social, political, and economic), and colored by community history.
- Health is an integral part of a larger context, probably most clearly defined as quality of life, and it’s within that context that it must be considered. It is only one of many factors that make life better or worse for individuals and the community as a whole. It therefore influences, and is influenced by, much more than seems directly connected to it.
The HIV/AIDS epidemic changed the way many people in the U.S. view and practice sex, for instance. In some other countries, it affected the whole social structure because of the number of orphans it created and its impact on the workforce. By the same token, violence involving young people changes the views and actions of many people who are not directly at risk of experiencing it, and may put a community at an economic disadvantage by making it less attractive to new business or industry. Almost any other issue could serve equally well as an example of the broad reach of community problems (or assets, for that matter).
- Finally, health is more than physical well-being, or than the absence of disease, illness, or injury. It is a constellation of factors – economic, social, political, ecological, and physical – that add up to healthy, high-quality lives for individuals and communities.
This broad perspective on health extends to other community issues. We can define the health of a community as its fitness in many areas, of which community members’ physical health is only one. Indications of a community’s overall health include how well it:
- Contributes to the stability of families
- Nurtures and supports children
- Fosters lifelong learning
- Provides meaningful work for community members
- Invites involvement in the democratic process
- Supports people who need help
- Protects and sustains the natural environment
- Encourages the arts
- Values and encourages racial and cultural diversity
- Works to promote and maintain safety and physical well-being for its members
PRECEDE and PROCEED are acronyms (words in which each letter is the first letter of a word). PRECEDE stands for Predisposing, Reinforcing, and Enabling Constructs in Educational/Environmental Diagnosis and Evaluation. As its name implies, it represents the process that precedes, or leads up to, an intervention.
PROCEED spells out Policy, Regulatory, and Organizational Constructs in Educational and Environmental Development, and, true to its name as well, describes how to proceed with the intervention itself.
PRECEDE has four phases, which we’ll explore in greater detail later in the section:
- Phase 1: Identifying the ultimate desired result.
- Phase 2: Identifying and setting priorities among health or community issues and their behavioral and environmental determinants that stand in the way of achieving that result, or conditions that have to be attained to achieve that result; and identifying the behaviors, lifestyles, and/or environmental factors that affect those issues or conditions.
- Phase 3: Identifying the predisposing, enabling, and reinforcing factors that can affect the behaviors, attitudes, and environmental factors given priority in Phase 2.
- Phase 4: Identifying the administrative and policy factors that influence what can be implemented.
Another premise behind PRECEDE-PROCEED is that a change process should focus initially on the outcome, not on the activity. (Many organizations set out to create community change without stopping to consider either what effect their actions are likely to have, or whether the change they’re aiming at is one the community wants and needs.) PRECEDE’s four phases, therefore, move logically backward from the desired result, to where and how you might intervene to bring about that result, to the administrative and policy issues that need to be addressed in order to mount that intervention successfully. All of these phases can be thought of as formative.
PROCEED has four phases (also to be discussed in more detail later) that cover the actual implementation of the intervention and the careful evaluation of it, working back to the original starting point – the ultimate desired outcome of the process.
- Phase 5: Implementation – the design and actual conducting of the intervention.
- Phase 6: Process evaluation. Are you actually doing the things you planned to do?
- Phase 7: Impact evaluation. Is the intervention having the desired impact on the population of focus?
- Phase 8: Outcome evaluation. Is the intervention leading to the outcome (the desired result) that was envisioned in Phase 1?
A word about logic models: Although most formal models, like PRECEDE-PROCEED, present themselves as a way to structure an intervention or other activity, the word “logic” implies that you should carefully consider your own situation as well as the model. If there are reasons why a particular part of a model might not work for you, it’s reasonable (logical) to change it. While PRECEDE-PROCEED presents a structure that could conceivably work well (and has worked well) in a variety of situations, it’s still important to think about whether all parts of it will work for you.
A flowchart of the model (see Fig. 1), developed by its originators, shows a circular process. It starts (on the upper right) with a community demographic and quality-of-life assessment, and goes counterclockwise through PRECEDE’s four phases that explain how to conceive and plan an effective intervention. PROCEED then picks up with the intervention itself (described here as a health program) and evaluates whether the intervention is being carried out as planned and producing the intended effects. The process evaluation in Phase 6 looks at whether the intervention is being implemented as intended. The impact evaluation in Phase 7 examines its effect on the behaviors or environmental factors identified earlier. And the outcome evaluation in Phase 8 explores whether the intervention has contributed to the desired quality-of-life outcome identified in Phase 1. Eventually, the process arrives back at the beginning, either having achieved the desired outcome or ready to begin another cycle incorporating lessons from the first effort. The arrows in the flowchart demonstrate the relationships among the phases and their effects.
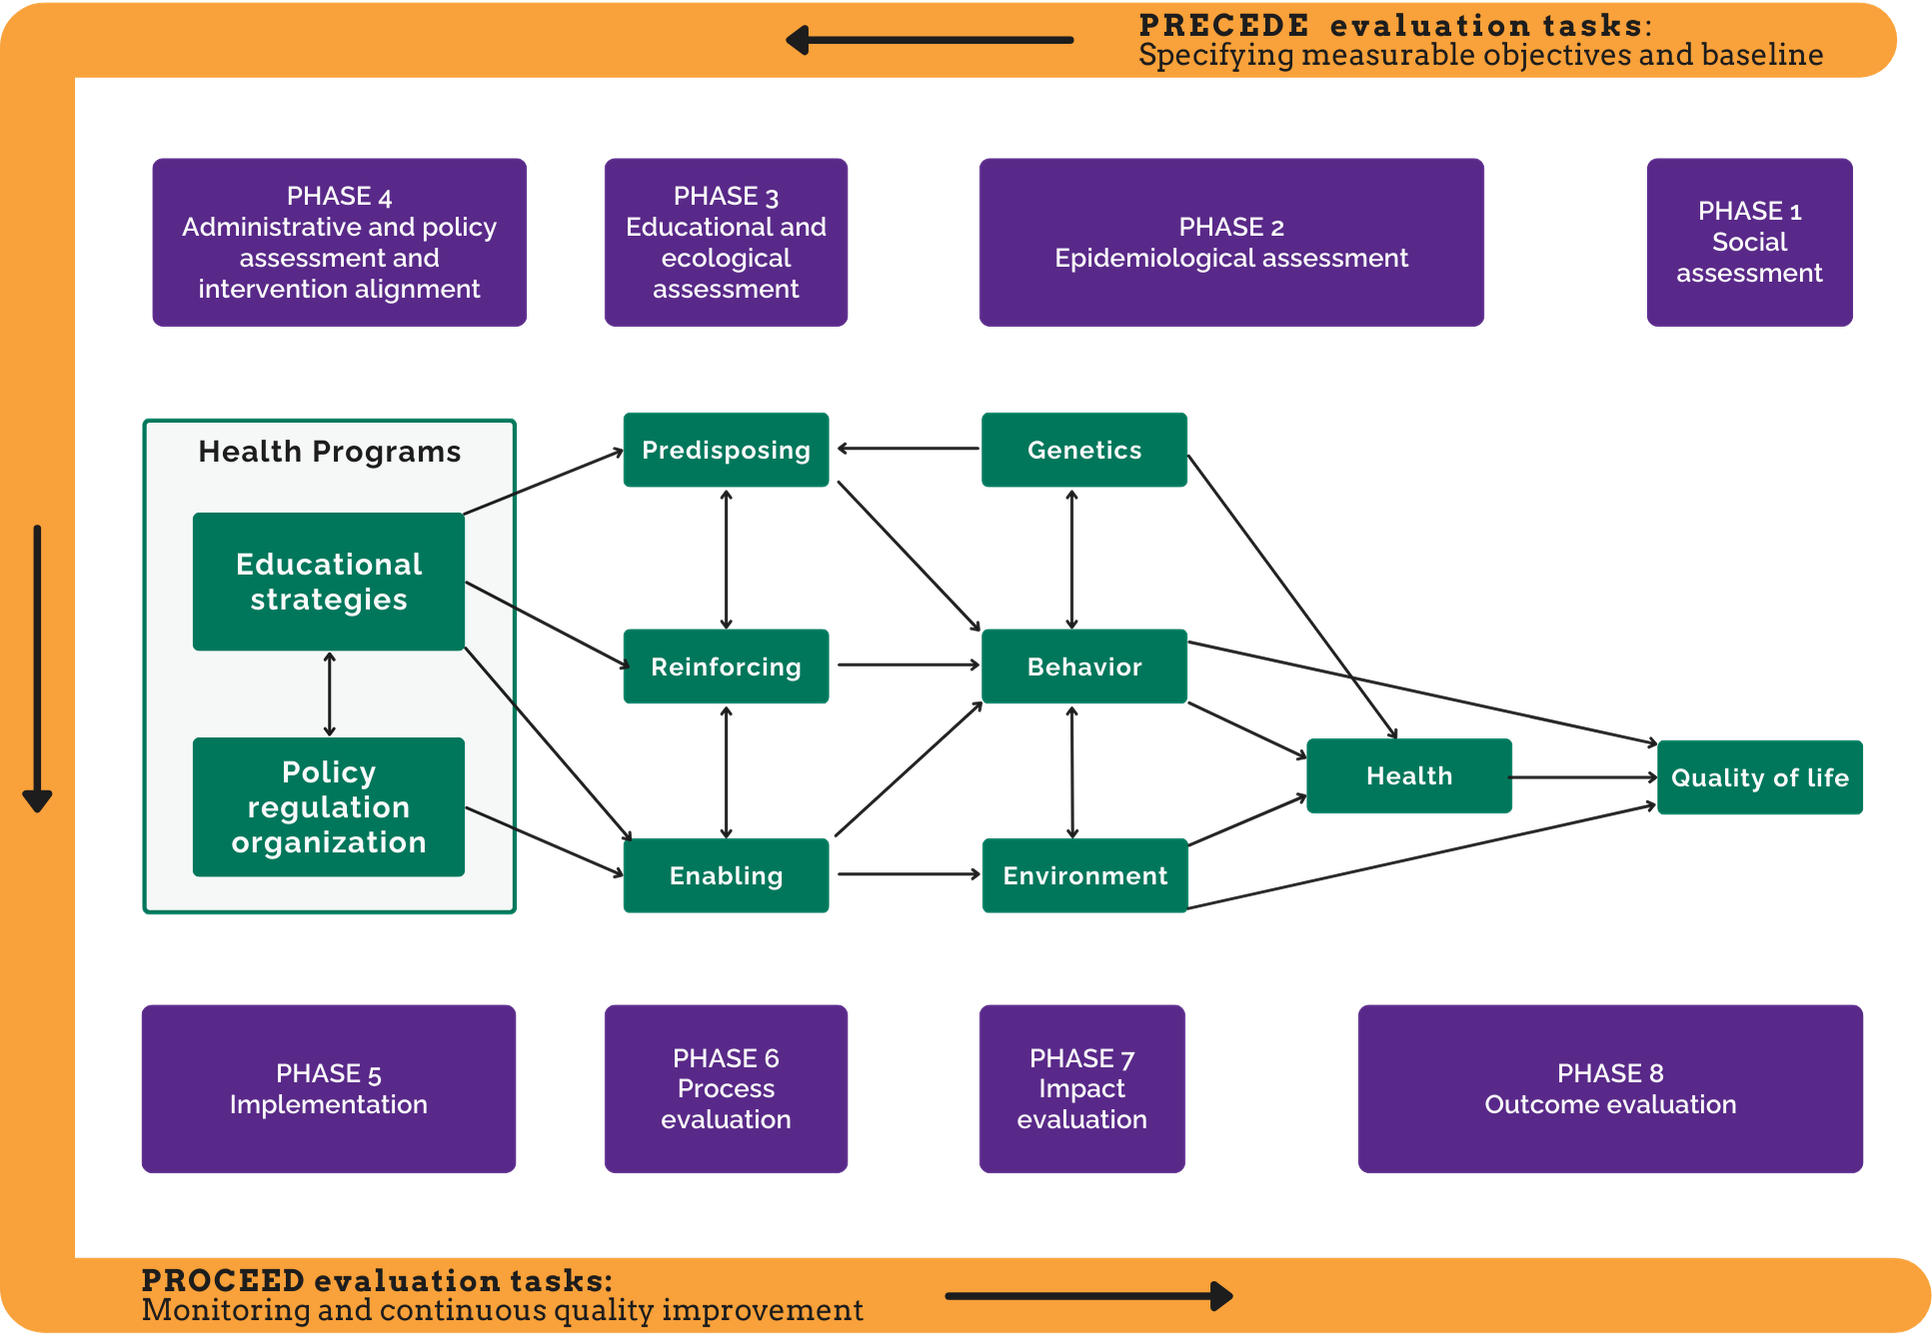
Figure 1. Generic representation of the PRECEDE-PROCEED Model. From L. Green and M. Kreuter. (2005). Health Promotion Planning: An Educational and Ecological Approach (4th Ed.). Mountain View, CA: Mayfield Publishers.
- The PRECEDE-PROCEED model applies a medical perspective to public health, even though its focus is health promotion, rather than treatment of disease. Just as a medical diagnosis precedes treatment, the model assumes that a far-reaching diagnosis should precede a public health intervention. A diagnosis suggests a treatment (an intervention), which is closely monitored for process (Is the person receiving the treatment prescribed?), impact (Is the treatment having the hoped-for impact on the symptoms?), and outcome (Does the treatment have the desired effect on the person’s overall health?). A premise of the model is that a diagnosis should start with the desired end result and work backward to determine what needs to be done to bring about that result.
- Another basic premise of the model is that the purpose of a health program – and by extension, the purpose of any proactive type of community intervention – is to improve the quality of life for individuals and their community, and that the two are largely inseparable. Thus, any intervention should be community-based, and should look at the needs of the community, even if the intervention is aimed at a more specific population of focus.
- A final premise of any community-based model for intervention is that planning and implementing a community intervention calls for a joint effort among health and other professionals and organizations, policymakers, community officials, community leaders, and community members broadly, including members of the population of focus. In order to ensure accurate information and community support, people from throughout the community should be involved in the process from the beginning.
Why use PRECEDE-PROCEED?
First, there are good reasons for using some kind of logic model or theoretical framework for any intervention:
- It provides a structure within which to plan your work, so that you’re not simply grasping at straws. As a result, you’re more likely to develop a coherent plan that addresses the necessary issues.
- Most models give you either a guide or a foundation for critical analysis of the issues at hand. That doesn’t guarantee that your analysis will be complete or accurate, but it significantly increases the chances. (See Analyzing Community Problems and Solutions for more on logical analysis.)
This is not to say that you have to use a logic model. There are other ways to approach developing an intervention, many of them outlined in the Community Tool Box. The advantage of PRECEDE-PROCEED and similar models is that they give you a structured procedure for developing an intervention. The disadvantage is similar: if some part of the model isn’t appropriate for your setting or your circumstances, you’ll have to recognize that and change it to fit, or risk a problem. PRECEDE-PROCEED offers a flowchart or algorithm to facilitate decisions for skipping some steps or phases, thereby tailoring the model to different local situations.
Originators or advocates of a model may encourage close adherence to it. In practice, however, you may need to adapt it. If you like the model, you can be sure to include its important elements while still changing some of them, changing the timing, or even changing the order to better match the needs of your community. You might also find yourself taking some pieces of one model and grafting them onto another, or reinterpreting a model in light of a particular theoretical framework.
Over and above the use of logic models in general, there are some good reasons for using PRECEDE-PROCEED specifically:
- PRECEDE-PROCEED provides a template for the process of conceiving, planning, implementing, and evaluating a community intervention.
- PRECEDE-PROCEED is structured as a participatory model, to incorporate the ideas and help of the community. That means that its use can provide you with more, and more accurate, information about the issues in question, and with a better understanding of their history and context in the community.
- Community involvement is also a means of building community ownership of the intervention, leading to more community support and a greater chance of success.
- PRECEDE-PROCEED considers the ways in which administrative and policy guidelines can limit or shape an intervention, an area of planning too often ignored.
- PRECEDE-PROCEED incorporates evaluation of the process, the intervention itself, and the final outcome. That allows the intervention to be monitored and adjusted to respond to community needs and changes in the situation, and checks whether its accomplishments actually lead to the projected goal.
- Although PRECEDE-PROCEED sets out a structured process, it says much less about content. It leaves plenty of room for adapting your intervention’s design and methods to the situation and the needs of the community.
Although these are good reasons to use PRECEDE-PROCEED, they are also good reasons to use some of the other models in this chapter. This is the reason we are presenting several – so that you can decide which among them, if any, makes the most sense to you, and would be best for your circumstances and community. PRECEDE-PROCEED’s greatest strength may be its comprehensive and rigorous structure – it covers all the bases.
How do you use PRECEDE-PROCEED?
Logic models don’t really mean much unless you actually use them in the community. Once you’ve decided that PRECEDE-PROCEED provides a good model for your intervention, how do you translate it into action? We’ll look at each of the eight phases of the model with that question in mind.
PRECEDE: Doing the groundwork. PRECEDE starts by determining the desired outcome for the community, and then works back to what has to be done to obtain that outcome. Each phase moves one step closer to the actual intervention.
Our presentation of the model assumes that, although it was developed for use in public health, it can be used by activists or organizations concerned with any issues that affect the quality of life in a community, as demonstrated in many published applications.
Phase 1: Defining the ultimate outcome. The focus here is on what the community wants and needs, which may seem unrelated to the issue you plan to focus on. What outcome does the community find most important? Eliminating or reducing a particular problem (homelessness)? Addressing an issue (race)? Improving or maintaining certain aspects of the quality of life (environmental protection)? Improving the quality of life in general (increasing or creating recreational and cultural opportunities)?
This phase starts with the collection of demographic data, which is then presented to the community to help community members decide on priorities. The way to determine what community members want for their community is to ask them. There are a number of options here, which can be used individually or in combination, including:
- Community surveys
- Focus groups
- Phone interviews
- Face-to-face interviews
- Questionnaires in community settings
Rather than just asking people for their opinions about what would improve the community, it’s far more powerful to involve community members in the whole process from the beginning, including them in all phases of the PRECEDE-PROCEED model. While actual applications of the model may sometimes be top-down, it is likely to work better if the community has significant input and decision-making power from the beginning.
Phase 2: Identifying the issue. In Phase 2 of PRECEDE, you look for the issues and factors that might cause or influence the outcome you’ve identified in Phase 1 (including supports for and barriers to achieving it), and select those that are most important, and that can be influenced by an intervention. (One of the causes of community poverty, for instance, may be the global economy, a factor you probably can’t have much effect on. As important as the global economy might be, you’d have to change conditions locally to have any real impact.)
It’s important to analyze these issues carefully, and to make sure that you’ve chosen the right ones. What would the elimination of a particular factor make possible, for instance, that isn’t possible already? How does a particular issue create a barrier to the desired outcome? What else do these issues affect, besides the desired outcome?
Which are the issues with the most significant effects? And how do you define “the most significant effects?” Are they economic? Social? Physical?
An industry responsible for pollution that actually or potentially causes health problems may also be the local economic mainstay. Even if the industry has the best of intentions, it may be unable to afford to clean up its operation. The town may be faced with the choice of either losing the jobs and tax base that the industry provides, or continuing to live with a health hazard. What’s more important here, and how do you decide what to focus on? (And is there an answer that isn’t either-or?)
This kind of situation is by no means universal...but it isn’t particularly unusual, either.
In some cases, the issues you choose to focus on may be directly related to the outcome you’re seeking – building more affordable housing as a way to address homelessness, for instance. In others, you may be trying to affect factors that have just as great an impact on the outcome, but seem further removed from it – e.g., addressing safe streets by providing parenting classes and other services for families facing greater risks.
Once again, involving stakeholders and other community members here is likely to get you the best information possible about which issues to emphasize, and to keep you from making mistakes based on ignorance of the community’s history or of the relationships among community members.
Phases 1 and 2 are where you develop the long-term goals for your intervention. They tell you what your ultimate desired outcome should be, and what the issue(s) or associated factors may be that influence it. Those are the things you’re ultimately aiming to change.
Most of the factors influencing the issues or outcomes can be classified as behavioral, lifestyle, or environmental.
The behavior referred to here is a specific, observable, often measurable – and usually customary – action. Some behaviors increase or reduce people's or communities’ risk for health or other problems.
- Sharing needles or other injection equipment among people who inject heroin increases the risk of hepatitis and HIV.
- Consistent studying usually lessens the risk of school failure for a student.
- If littering is a common individual behavior, it may have community consequences that range from the aesthetic (piles of trash creating an unattractive scene) to health (breeding of mosquitoes in garbage-strewn lots, water pollution, etc.) to the economic (businesses unwilling to locate in the community because of its physical condition). It may also have social consequences, with neighborhood conditions affecting residents’ self-image and leading eventually to a breakdown of civic responsibility.
A lifestyle is a collection of related behaviors that go together to form a pattern of living. Some lifestyles may increase the risk of health and other problems for people and communities.
- An example of a lifestyle that may increase health risks is one that includes very little exercise, a diet high in calories and saturated fats, and lots of stress. Such a lifestyle can increase the risk of heart attack, stroke, cardiovascular disease, diabetes, and other health problems.
- A lifestyle that involves gang membership and regular participation in violent acts has both individual consequences (the constant risk of serious injury or death, an arrest record, detachment from others’ humanity) and consequences for the community (people afraid to use the streets, reduced economic activity, scarce resources spent on extra law enforcement, etc.).
The environment of a particular issue or problem can refer to the natural, physical environment – the character and condition of the water, air, open space, plants, and wildlife, as well as the design and condition of built-up areas. But it can also refer to the social environment (influence of family and peers; community attitudes about gender roles, race, childrearing, work, etc.), the political environment (policies and laws, such as anti-smoking ordinances, that regulate behavior or lifestyle; the attitudes of those in power toward certain groups or issues), and the economic environment (the availability of decent-wage jobs, affordable housing, and health insurance; the community tax base; global economic conditions).
In general, behaviors, lifestyles, and environmental factors are what an intervention sets out to change. The changes in these areas in turn affect the crucial issues, and lead to the achievement of the final outcome that was identified in Phase 1 of the model.
So how do you choose which behaviors, lifestyles, or environmental factors to focus on? That’s where analysis comes in. What are people doing – or what are the factors in the environment – that lead to, maintain, or prevent the issue or condition you want to change? Using critical thinking and the “But why?” technique, you should be able to narrow it down to a handful. The criteria for choosing a particular target for your intervention are: (a) Is the potential target an important enough factor to have a real effect on the issue, and thus on the quality of life in the community? and (b) Is it likely that the potential target can actually be changed by an intervention that you have the resources to mount?
A classic example of community change through behavior change is reducing the incidence of lung cancer and heart disease in a community by helping people who smoke to quit. Fewer people smoking means less secondhand smoke, less time lost from work because of smoking-related illnesses, fewer low-birth-weight babies, fewer children with asthma and other respiratory ailments, and lower health care costs. Altogether, changing smoking behavior can contribute to an improvement in the overall quality of life for the community.
Changing smoking behavior fits both criteria described above. It has a profound effect on the issue and on the general quality of life; and it can be responsive to change because of many people's desire to quit, general knowledge about the dangers of smoking, the cost of tobacco products, community support, and already-existing strategies and smoking-cessation groups that can be incorporated into an intervention.
Phase 3: Examining the factors that influence behavior, lifestyle, and responses to environment. Here, you identify the factors that will create the behavior and environmental changes you’ve decided on in Phase 2.
The terms “health-promoting behavior” and “behavior that increases risk” below refer not only to physical health, but to any behavior that’s advantageous or harmful to the individual and/or the community, and is likely to have a significant effect on quality of life.
Predisposing factors are intellectual and emotional “givens” that tend to make individuals more or less likely to adopt health-promoting behaviors or behaviors that increase risk, or to approve of or accept particular environmental conditions. Some of these factors can often be influenced by educational interventions. They include:
- Knowledge. You’re more likely, for instance, to avoid sunburn if you know it can lead to skin cancer than if you don’t.
- Attitudes. People who have spent their youth as athletes often come to see regular exercise as an integral part of life, as necessary and obvious as regular meals.
- Beliefs. These can be mistaken understandings – believing that anything low in fat is also low in calories – or closely held beliefs based on religion or culture. For example, someone may interpret the old saying “Spare the rod and spoil the child” as justification for physically punishing children for mistakes or misdeeds.
- Values. A value system that renounces violence would make a parent less likely to use physical violence against a child, spouse, or other family member.
- Confidence. Many people fail to change behaviors that increase risk simply because they don’t feel capable of doing so.
Enabling factors are those internal and external conditions directly related to the issue that help people adopt and maintain healthy or unhealthy behaviors and lifestyles, or to embrace or reject particular environmental conditions. Among them are:
- Availability of resources. People experiencing mental health challenges, for instance, are much more likely to get help if services are readily available.
- Accessibility of services. Services do no good if they have waiting lists that run into years, or aren’t physically accessible to those who need them.
- Community and/or government laws, policies, priorities, and commitment to the issue. Government laws and policies can both require changes in behavior or environment, and underline the importance of those changes.
- Issue-related skills. People who start out with familiarity with workplace expectations and routines, for instance, may be better positioned to benefit from job placement programs.
Reinforcing factors are the people and community attitudes that support or make difficult the adoption of healthy behaviors or the fostering of healthy environmental conditions. These are largely the attitudes of influential people: family, peers, teachers, employers, health or human service providers, the media, community leaders, politicians, and other decisionmakers. An intervention might aim at these people and groups – because of their influence – in order to most effectively reach the population of focus.
Phases 2 and 3 comprise the part of the model where the real planning of an intervention has to take place. What are you trying to change, and what are the factors that will help to bring that change about? Answering these questions should bring you to an understanding of whom and what an intervention should target, who best might conduct the intervention, and what it should look like in order to hit its targets effectively.
Phase 4: Identifying “best practices” and other sources of guidance for intervention design, as well as administrative, regulatory, and policy issues that can influence the implementation of the program or intervention. Phase 4 helps you look at organizational issues that might have an impact on your actual intervention. It factors in the effects on the intervention of your internal administrative structure and policies, as well as external policies and regulations (from funders, public agencies, and others).
Design issues: “Matching, mapping, pooling, and patching” or “Selecting, designing, blending, and supporting interventions.”
The discussion of the ways in which organizational issues, particularly internal ones, interact with a proposed intervention is one that all too often never takes place. For that reason, Phase 4 is particularly important. Such a discussion can avoid mismatches between an organization and its proposed intervention (a strictly hierarchical organization attempting to implement an intervention meant to empower underrepresented community members, for instance), or alert an organization to an internal or external regulation or policy that needs to be changed or addressed for an intervention to proceed as planned.
Administrative issues include organizational structure, procedures, and culture; and the availability of resources necessary for the intervention.
- The organizational structure may be hierarchical, democratic, collaborative, or some combination, and may be more or less rigid or flexible within each of those categories. It should be appropriate to the design of the intervention (e.g., allowing for staff decisions in the field in a gang outreach program), and flexible enough to make adjustments when necessary.
- Organizational procedures are the ways in which the organization actually carries out its work. In order for an intervention to be successful, those procedures have to focus on its goals, rather than on internal convenience or traditional methods. An intake procedure, for instance, should be designed to be as straightforward and respectful for participants as possible – otherwise it can become a barrier to participation.
- The organizational culture. Organizations are social groups that develop cultures of their own. Those cultures often dictate, among other things, how staff members interact with one another, how program participants are treated, and how the organization views its work and its mission. (Is it just a job, or is it God’s work?) They also usually determine the fit between an organization and an intervention.
- The resources available for the intervention include not only money – although that’s certainly important – but time, personnel, skills, and space. Now is the time to pinpoint any gaps in resources beforehand and work to close them. Thus, finding funding and/or the right staff people may be a good part of this phase.
Policy and regulatory issues have to do with the rules and restrictions – both internal and external – that can affect an intervention, and their levels of flexibility and enforcement.
Internal policies:
- Staff members. Organizational policy may treat staff as employees who take orders, as colleagues who contribute to the work of the organization, or as collaborators who jointly own it. The amount of freedom they have to exercise their creativity and to take initiative probably depends on that policy, which may be unstated.
- Participants. Does organizational policy see participants as “clients” that the organization is doing something to or for, or as partners in a change effort? Does it treat participants respectfully, as equals, or does it act in a condescending or overly authoritative way?
How does the organization treat relationships among participants and staff? In some organizations, they may be friendly; in others, strictly professional. (Romantic or sexual relationships raise some ethical questions, and probably need to be considered separately. See “Professional ethics” below.)
- Specific practices, methods, or programs. Many organizations maintain policies that suggest or mandate certain ways of carrying out their work.
- Collaboration. Some nonprofits make it a point of policy to collaborate as much as possible, while others rarely, if ever, work with other organizations.
- Professional ethics. Many organizations expect staff members to adhere to a code of professional ethics – either an internal one, or one set out by a professional association – that governs confidentiality, inappropriate relationships, abuse of position, reporting (or non-reporting) of specific kinds of illegal behavior, etc. There may be organizational regulations about these areas as well.
External policies and regulations that might affect an intervention can come in a variety of forms:
- Funders’ requirements. These may apply to the intervention itself, or they may place restrictions on anything the organization can do, even those areas – such as, perhaps, this intervention – that aren’t funded directly by the funder in question.
- Oversight agency regulations. The organization may be subject to the authority of a state or federal agency whose regulations affect the intervention.
- State or federal laws, or local ordinances
- Unstated community policies. Certain actions may simply be unacceptable to the majority of the community, to coalition partners, etc.
PROCEED: Implementing and evaluating the intervention.
Phase 5: Implementation. At this point, you’ve devised an intervention (largely in Phases 3 and 4), based on your analysis. Now, you have to carry it out. This phase involves doing just that – setting up and implementing the intervention you’ve planned.
The final three phases take place as the intervention continues, and serve to help you monitor and adjust your work to make it as effective as possible.
Phase 6: Process Evaluation. This phase isn’t about results, but about procedure. The evaluation here is of whether you’re actually doing what you planned. If, for instance, you proposed to offer mental health services three days a week in a rural area, are you in fact offering those services?
Phase 7: Impact Evaluation. Here, you begin evaluating the initial success of your efforts. Is the intervention having the desired effect on the behavioral or environmental factors that it aimed at changing – i.e., is it actually doing what you expected?
Phase 8: Outcome Evaluation. Is your intervention really working to bring about the outcome the community identified in Phase 1? It may be completely successful in every other way – the process is exactly what you planned, and the expected changes are made – but its results may have no effect on the larger issue. In that case, you may have to start the process again, to see why the factors you focused on aren’t the right ones, and to identify others that might work.
Some outcomes may not be apparent for years or decades. Lifestyle changes made by young people to reduce their risk of heart disease and stroke, for instance, may not reveal their full health benefits until those people are older. If you know that an outcome may not show itself for a long time, you may just have to be patient and continue to monitor the process and impact of your intervention, with the expectation that longer-term outcomes may become apparent over time.
Phases 6-8 call for formal evaluations of each phase, with controlled studies and detailed findings, but many Community Tool Box users probably don’t have the resources for that, and shouldn’t expect to do it. That doesn’t mean you shouldn’t evaluate, however.
It’s a relatively simple matter, for instance, to keep records and examine them to find out whether your process was carried out as planned, or simply to look at what you are doing to see whether it matches what you intended to do. The same is true for the other stages of evaluation. Don’t worry if you can’t do a formal study...but don’t let evaluation go, either. It’s an important part of the process.
Remember also that evaluation is ongoing throughout the work. It takes place while the intervention is being implemented, not only afterward. The whole point of evaluation of each phase of the model is to adjust or change what you’re doing in that phase, if necessary, to make it more effective.
At any point in the PROCEED continuum, you should be prepared to revisit your analysis. If you find a gap between your planning and reality, or if you realize that your intervention isn’t achieving the results you aimed at, you should go back to the PRECEDE part of the model, try to determine what needs to be changed, and adjust what you’re doing accordingly. The point of evaluation is not to see whether you pass some kind of test – it’s to make sure that your intervention brings about the outcome that the community wanted or needed in the first place.
In Summary
PRECEDE-PROCEED provides a logic model that can serve as the basis for an individual, one-time intervention or a decades-long community development program or project. Although designed for health programs, it’s adaptable to other community issues as well. As with many models, it’s meant to be a guide, not a prescription.
PRECEDE-PROCEED is community-based and participatory, founded on the premise that many changes promoting health (and addressing other community issues) depend on voluntary action, and therefore need the participation of people directly affected by the change and others who might influence or be influenced by it.
A major reason to use PRECEDE-PROCEED is that it is a logic model. As a result, it will provide a structure within which to plan your work, and organize both your thinking and your actions, so that your intervention will be a carefully planned, coherent whole, rather than cobbled together. As a logic model, it also provides a guide for analyzing the issues involved, and choosing both the most likely areas to address and the most likely avenues to address them.
There are also reasons to use PRECEDE-PROCEED specifically. First, it’s a participatory model. By involving the community, it can bring more and better ideas about issues and ways of addressing them, and build community ownership of the intervention. Second, since it includes multi-level (ecological) planning and evaluation, PRECEDE-PROCEED builds in monitoring of the intervention, allowing for adjustment and greater effectiveness. And finally, the model allows the freedom to adapt the structure to whatever content and methods meet the needs of your community.
PRECEDE is the diagnostic portion of the model. It starts with the idea that the focus of change must be on its desired outcome, and works backward from that outcome to construct an intervention that will bring it about. It has four phases:
Phase 1: Social diagnosis – determine what the community wants and needs to improve its quality of life.
Phase 2: Epidemiological diagnosis – determine the health problems or other issues that affect the community’s quality of life. Include also the behavioral and environmental factors that must change in order to address these problems or issues. Behavioral factors include patterns of behavior that constitute lifestyles. In considering environmental factors, you should include the physical, social, political, and economic environments.
Phases 1 and 2 identify the goals of the intervention.
Phase 3: Educational and organizational diagnosis – determine what to do in order to change the behavioral and environmental factors identified in Phase 2, taking into account predisposing factors (knowledge, attitudes, beliefs, values, and confidence); enabling factors (availability of resources, accessibility of services, government laws and policies, issue-related skills); and reinforcing factors (largely the influence of significant others in the social environment).
Phase 4: Designing programs or interventions and the support for them through administrative and policy diagnosis – determine (and address) the internal administrative and internal and external policy factors that can affect the success of your intervention. The former include organizational structure, procedures, culture, and resources; the latter encompass both internal policies and funders’ requirements, oversight agency regulations, state or federal laws, local ordinances, and unstated community policies.
Phases 3 and 4 set the structure and targets for the planning and design of the intervention.
PROCEED is, in medical terms, the treatment portion of the model, and comprises the implementation and evaluation of the intervention. It consists of four phases:
Phase 5: Implementation – conduct the intervention.
Phase 6: Process evaluation – determine whether the intervention is actually taking the actions intended.
Phase 7: Impact evaluation – determine whether the intervention is having the intended effects on behaviors and/or the environment.
Phase 8: Outcome evaluation – determine whether the intervention ultimately brings about the improvements in quality of life identified by the community as its desired outcome.
An unstated but important part of the model is that, at any point, your plan or intervention can and should be revisited and revised, based on continued analysis and the results of the various evaluations.
Resources
Online Resources
A Framework for Planning and Evaluation: Precede-Proceed Evolution and Application of the Model by Lawrence W. Green and Judith M. Ottoson of Montreal, Quebec.
An explanation of the PRECEDE-PROCEED model from the Interdisciplinary Student Community-Oriented Prevention.
The website of Lawrence Green, originator of the PRECEDE-PROCEED model and co-author of the main text describing it. Includes a description of and ordering information for EMPOWER software, developed as a teaching tool for the model
Using the Precede-Proceed Model is a short resource with visual examples of program planning as well as case studies.
Phase 1: Defining the ultimate outcome.
The first phase is to involve the community in prioritizing the issues on which they want to focus. This involves collecting demographic data in the form of interviews, questionnaires, and focus groups. The entire community can then be involved in using those data to prioritize their outcomes.
Community Tool Box links related to Phase 1:
- Assessing Community Needs and Resources
- Conducting Public Forums and Listening Sessions
- Conducting Focus Groups
- Conducting Needs Assessment Surveys
- Conducting Concerns Surveys
- Conducting Interviews
- Conducting Surveys
- Creating and Using Community Report Cards
- Developing a Plan for Identifying Local Needs and Resources
- Leading a Community Dialogue on Building a Healthy Community
- Qualitative Methods to Assess Community Issues
- Understanding and Describing the Community
Phase 2: Identifying the issue.
In this phase, the community must involve all stakeholders in the process of identifying issues related to the outcome and determining what to influence. It must be decided what could prevent the desired outcome or aid in achieving it, which factors are the most significant, and which can be influenced by intervention.
Community Tool Box links related to Phase 2:
- Analyzing Community Problems
- Assessing Community Needs and Resources
- Collecting Information About the Problem
- Conducting Focus Groups
- Conducting Interviews
- Conducting Needs Assessment Surveys
- Conducting Public Forums and Listening Sessions
- Conducting Surveys
- Developing a Plan for Identifying Local Needs and Resources
- Leading a Community Dialogue on Building a Healthy Community
- Understanding and Describing the Community
Phase 3: Examining the factors that influence behavior, lifestyle, and responses to environment.
Phase three involves deciding what factors to manipulate in order to create the changes agreed upon in Phase 2. This requires analysis of the predisposing, enabling, and reinforcing factors including the knowledge, beliefs and values of members of the community, availability and accessibility of resources, and the attitudes of influential people.
Community Tool Box links related to Phase 3:
- Analyzing Community Problems
- Assessing Community Needs and Resources
- Collecting Information About the Problem
- Conducting Focus Groups
- Conducting Interviews
- Conducting Surveys
- Developing a Plan for Identifying Local Needs and Resource
- Developing Baseline Measures of Behavior
- Determining Service Utilization
- Identifying Community Assets and Resources
- Qualitative Methods to Assess Community Issues
- SWOT Analysis: Strengths, Weaknesses, Opportunities, and Threats
Phase 4: Identifying "best practices" and other sources of guides to intervention design and the administrative regulation, and policy issues that can influence the implementation of the intervention.
In Phase four, an organization must consider its own structure, policies and history in order to ensure that there are no internal factors that might act as barriers when trying to implement changes. Issues that must be considered include the group's organizational structures, procedures, culture and resources as well as policies regarding staff members, participants, specific practices, community laws, and issues related skills.
Community Tool Box links related to Phase 4:
- Assessing Community Needs and Resources
- SWOT Analysis: Strengths, Weaknesses, Opportunities, and Threats
Administrative Issues
- Creating and Gathering a Group to Guide Your Initiative
- Developing an Organizational Structure for the Initiative
- Developing a Plan for Staff Hiring, Orientation, and Trainin
- Developing Multisector Task Forces or Action Committees for the Initiative
- Developing an Ongoing Board of Directors
- Developing Personnel Policies
- Hiring and Training Key Staff of Community Organizations
- Maintaining a Board of Directors
- Maintaining Ethical Leadership
- Managing Finances
- Orienting Ideas in Leadership
- Organizational Structure: An Overview
- Planning and Writing an Annual Budget
- Understanding and Writing Contracts and Memoranda of Agreement
- Welcoming and Training New Members to a Board of Directors
- Writing Bylaws
External Policies and Regulations
- Adapting Community Interventions for Different Cultures and Communities
- Analyzing Community Problems and Solutions
- Choosing and Adapting Community Interventions
- Criteria for Choosing Promising Practices and Community Interventions
- Deciding Where to Start
- Defining and Analyzing the Problem
- Designing Community Interventions
- Ethical Issues in Community Interventions
- Generating and Choosing Solutions
- Identifying Strategies and Tactics for Reducing Risks
- Identifying Targets and Agents of Change: Who Can Benefit and Who can Help
- An Introduction to the Problem Solving Process
- Participatory Approaches to Planning Community Interventions
- Putting Your Solution into Practice
- Thinking Critically
- Understanding Risk and Protective Factors: Their Use in Selecting Potential Targets and Promising Strategies for Interventions
- Using Community Sectors to Reach Targets and Agents of Change
Phase 5: Implementing and evaluating the intervention
At this point, the interventions devised must be carried out. This phase involved setting up and implementing the intervention as planned.
Community Tool Box links related to Phase 5:
- Acting as a Watchdog
- Advocacy Over and For the Long Term
- Conducting Advocacy Research
- Conducting a Direct Action Campaign
- Conducting a Petition Drive
- Conducting a Public Hearing
- Conducting Research to Influence Policy
- Conducting Studies of the Issue
- Changing the Media's Perspective on Community Issues
- Creating News Stories the Media Wants
- Criticizing Unfavorable Action
- Demonstrating Economic Benefit or Harm
- Developing and Maintaining Ongoing Relationships with Legislators and Their Aides
- Developing a Plan for Advocacy
- Developing a Proposal for Change
- Documenting Complaints
- Electronic Advocacy
- Encouraging Involvement of Potential Opponents as well as Allies
- Establishing Formal Communications and Requesting Participation
- Establishing Lines of Communication within the Opposition's Traditional Allies
- Filing a Complaint
- Gathering Data on Public Opinion
- General Rules for Organizing for Legislative Advocacy
- How to Conduct Research: An Overview
- How to Respond to Opposition Tactics
- Identifying Opponents
- Initiating Legal Action
- Lobbying Decisionmakers
- Making Friends with the Media
- Meeting the Media
- Media Advocacy
- Overview Getting an Advocacy Campaign Off the Ground
- Organizing Audits of Consumer Services
- Organizing a Boycott
- Organizing a Strike
- Organizing Public Demonstrations
- Organizing Study Circles
- Overview of Opposition Tactics: Recognizing the Ten D's
- Principles of Advocacy
- Providing Encouragement and Education
- Providing Corrective Feedback
- Recognizing Allies
- Registering Voters
- Recognizing Allies
- Reframing the Issue
- Responding to Counterattack
- Requesting Accountability
- Seeking Enforcement of Existing Laws or Policies
- Seeking a Negotiator, Mediator, or Fact-Finder
- Studying the Opposition
- Survival Skills for Advocates
- Understanding the Issue
- Using Paid Advertising
- Using Personal Testimony
- Working with the Media
- Writing Letters to Elected Officials
- Writing Letters to the Editor
Phase 6: Process evaluation
In phase six, the organization must review the interventions underway to determine if the procedures are being carried out as planned. It must be determined if the specific tasks within the interventions are being carried out as intended.
Phase 7: Impact evaluation
In phase seven the effects of the interventions are reviewed. A basic analysis must be conducted to ensure that the interventions are having the desired effect.
Phase 8: Outcome evaluation
Even in you are implementing everything you planned, you may still not be having an impact on the larger issues. In phase eight the outcomes are examined to see if the direct effects of the interventions being made are effecting the bottom line, or if a focus on different factors is needed.
Community Tool Box links related to Phase 6, Phase 7, and Phase 8
- Behavioral Surveys
- Communicating Information to Funders for Support and Accountability
- Community-Level Indicators: Some Examples
- Collecting and Analyzing Data
- Collecting and Using Archival Data
- Conducting Interviews with Key Participants to Analyze Critical Events
- Choosing Evaluators
- Constituent Survey of Outcomes: Ratings of Importance
- Designing an Observational System
- Developing an Evaluation Plan
- Developing and Testing a Prototype Intervention
- A Framework for Program Evaluation: A Gateway to Tools
- Gathering Information: Monitoring Your Progress
- Information Gathering and Synthesis
- Introduction to Evaluation
- Intervention Research with Communities: A Gateway to Tools
- Measuring Success: Evaluating Comprehensive Community Health Initiatives
- Providing Feedback to Improve the Initiative
- Rating Community Goals
- Rating Member Satisfaction
- Reaching Your Goals: The Goal Attainment Report
- Some Operations in Evaluating Community Interventions
- Selecting an Appropriate Experimental Design
- Some Methods for Evaluating Comprehensive Community Initiatives
- Understanding Community Leadership, Evaluators, and Funders: What Are Their Interests?
- Using Evaluation to Understand and Improve the Initiative
Print Resources
Gielen, A. C., & Eileen M. M. (1996). The PRECEDE-PROCEED Planning Model. In Health Behavior and Health Education , edited by Glanz, K, Lewis, F., & Rimer, K. B. San Francisco : Jossey-Bass.
Green, Lawrence W., & Marshall W. Kreuter. Health Promotion and Planning: An Educational and Environmental Approach. (1999) (4th edition). Mountain View , CA : Mayfield Publishing Co.
What is PRECEDE-PROCEED?
___PRECEDE-PROCEED is a community-oriented, participatory model for creating successful community health promotion interventions.
PRECEDE has four phases:
___Phase 1: Social diagnosis
___Phase 2: Epidemiological diagnosis, including behavioral and environmental diagnosis
___Phase 3: Educational and organizational diagnosis
___Phase 4: Administrative and policy diagnosis
PROCEED has four phases:
___Phase 5: Implementation
___Phase 6: Process evaluation
___Phase 7: Impact evaluation
___Phase 8: Outcome evaluation
PRECEDE-PROCEED rests on the following premises:
___Since behavior change is by and large voluntary, health promotion (and, by extension, the promotion of other community benefits) is more likely to be effective if it's participatory.
___Health and other issues must be looked at in the context of the community.
___Health and other issues are essentially quality-of-life issues.
___Health is itself a constellation of factors that add up to a healthy life for individuals and communities.
Why use PRECEDE-PROCEED?
You use PRECEDE-PROCEED because:
___A logic model provides a procedural structure for constructing an intervention.
___A logic model provides a framework for critical analysis.
___PRECEDE-PROCEED is participatory, thus assuring community involvement.
___Community involvement leads to community buy-in.
___PRECEDE-PROCEED incorporates a multi-level evaluation, which means you have the chance to constantly monitor and adjust your evaluation.
___The model allows leeway to adapt the content and methods of the intervention to your particular needs and circumstances.
How do you use PRECEDE-PROCEED?
___In Phase 1, you ask the community what it wants and needs to improve its quality of life.
___In Phase 2, you identify the health behaviors and lifestyles and/or environmental factors that most clearly influence the outcome the community seeks that must be changed to affect the issues, and determine which of them are most likely to be changeable.
___In Phases 1 and 2, you create the objectives for your intervention.
___In Phase 3, you identify the predisposing, enabling, and reinforcing factors that act as supports for or barriers to changing the behaviors and environmental factors you identified in Phase 2.
___In Phases 3 and 4, you plan the intervention.
___In Phase 4, you identify (and adjust where necessary) the internal administrative issues and internal and external policy issues that can affect the successful conduct of the intervention.
___Those administrative and policy concerns include generating the funding and other resources for the intervention.
___In Phase 5, you carry out the intervention.
___In Phase 6, you evaluate the process of the intervention - i.e., you determine whether the intervention is proceeding according to plan, and adjust accordingly.
___In Phase 7, you evaluate whether the intervention is having the intended impact on the behavioral and environmental factors it's aimed at, and adjust accordingly.
- What is Healthy Cities/Healthy Communities?
- Why use Healthy Cities/Healthy Communities?
- Who should participate in Healthy Cities/Healthy Communities?
- How do you use Healthy Cities/Healthy Communities?
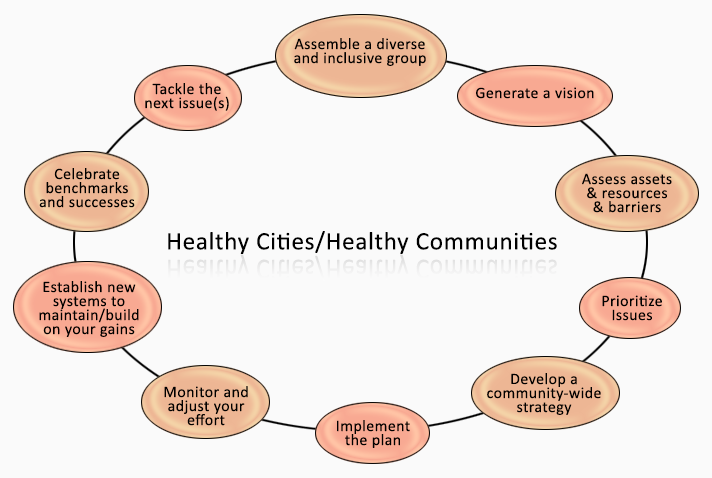
In this video, Tyler Norris, Vice President of Kaiser Permanente Center for Total Health, discusses the meaning and impacts of community health. "What is a healthy community? What is healthy, and what is a community?" he asks. In this section, we will explore the concepts of defining, creating, and promoting healthy communities.
What is Healthy Cities/Healthy Communities?
Healthy Cities/Healthy Communities is a theoretical framework for a participatory process through which community members can create healthy communities. In 1985, at a conference in Toronto organized by Trevor Hancock, Len Duhl spoke about his long-held conviction that health issues could only be effectively addressed through an inclusive, community-wide approach. Ilona Kickbusch, a World Health Organization (WHO) official who was attending the conference, brought the idea back to her colleagues at the WHO European office in Copenhagen. Within a matter of weeks, Duhl and Hancock had been hired as consultants to help WHO and Kickbusch start a Healthy Cities movement in Europe. A year later, the attendees of a WHO conference in Ottawa drafted the Ottawa Charter, the “Constitution” of Healthy Cities/Healthy Communities. In the years since that first conference, the concept has spread to hundreds of large and medium-sized cities on all continents, and has also been used in smaller municipalities and rural communities in countries with varying levels of resources. It has become an influential framework for addressing community health and related community issues.
A healthy community, as we discussed above, is one in which all systems work well (and work together), and in which all community members enjoy a good quality of life. This means that the health of the community is affected by the social determinants of health and development – the factors that influence individual and community health and development.
So, what does the Healthy Cities/Healthy Communities model look like? Unlike PRECEDE/PROCEED, it has no single prescribed flowchart or diagram, largely because its process may be very different in different communities. It’s a loosely defined strategy that asks community members and officials to make becoming a healthy community a priority, and to pursue that end by involving people throughout the community in identifying and addressing the issues most important to them.
We have created an informal logic model in order to connect you to Community Tool Box resources that can support your effort to implement Healthy Cities/Healthy Communities.
Healthy Cities/Healthy Communities rests on two basic premises:
A comprehensive view of health. As we’ve been discussing, a comprehensive view of health takes in all the elements of a community’s life, since they affect both individual health and the health of the community itself. The Ottawa Charter lays out the prerequisites for health in communities:
Peace. This can be interpreted to cover both freedom from warfare and freedom from fear of physical harm.
During the Vietnam War, young Black men on the streets of their home neighborhoods in the U.S. were statistically more likely to be killed by gunfire than were young Black soldiers in combat. Those home neighborhoods weren’t at peace, by anyone’s definition.
Shelter. Shelter adequate to the climate, to the needs of the occupants, and to withstand extremes of weather.
Education. Education for children (and often adults as well, as in the case of adult literacy) that is free, adequate to equip them for a productive and comfortable life in their society, and available and accessible to all.
Food. Not just food, but enough of it, and of adequate nutritional value, to ensure continued health and vigor for adults and proper development for children.
Income. Employment that provides an income adequate for a reasonable quality of life, and public support for those who are unable to work or find jobs.
A stable ecosystem. Clean air, clean water, and protection of the natural environment.
Sustainable resources. These might include water, farmland, minerals, industrial resources, power sources (sun, wind, water, biomass), plants, animals, etc.
Social justice. Where there is social justice, no one is mistreated or exploited by those with more power. No one is discriminated against. No one suffers needlessly because they are experiencing poverty, illness, or disability. All are treated equally and fairly under the law, and everyone has a voice in how the community and society are run.
Equity. Equity is not exactly the same thing as equality. It doesn’t mean that everyone gets the same things, but that everyone gets, or has access to, what they need.
If all of these factors are considered, then health must extend far beyond medical treatment to all aspects of community life.
A commitment to health promotion. Health promotion differs from the more familiar medical models of treatment and prevention. Treatment and prevention often focus on identifying and addressing illness or the risk of illness. Health promotion looks at health from a broader perspective: people and communities can take positive steps to improve and sustain well-being.
Health promotion – and we’ll use the term here to mean the promotion of healthy communities as well as healthy individuals – is key both to the thinking behind the Healthy Cities/Healthy Communities concept and to actually developing healthy communities. It calls for a commitment on the part of all sectors of the community, particularly government, to promote community health by:
Building healthy public policy. Communities can establish policies that foster the health of the community. According to the Ottawa Charter, such policies are “coordinated action that leads to health, income, and social policies that foster greater equity.” Thus, smoke-free policies in restaurants, local tax policies that encourage businesses to create jobs, training for police and people who work with young people to help them communicate with young people and reduce violence involving young people, and strong environmental ordinances might all be seen as healthy public policy. Community support of such policy produces an atmosphere that makes it easier for policymakers to make choices consistent with community goals, because they know the public is behind them.
Like all elements of a Healthy Cities/Healthy Communities strategy, healthy public policy is about a great deal more than simply fostering individual health – it’s about public policy that fosters a healthy society. That means equity, health for all, and attention to such things as supportive environments (see below).
Len Duhl talks about the fact that much public policy doesn’t deal with real needs, but rather with concerns of economics and power. For public policy to be healthy, it has to reflect reality, rather than what policymakers want to see, or what will get them elected. Objectivity can lead to public policy that benefits everyone, not just the influential few.
Creating supportive environments. Community environments run the gamut from the physical to the social to the economic to the political. Some supportive environments can be created by laws or regulations, some by community effort, and some only by changes in attitude (which may or may not be influenced by social and other pressures). Some examples:
The natural environment. Laws and regulations that restore and/or preserve clean air and water; preservation and creation of open space, natural beauty, and wilderness; restrictions on the use and disposal of toxic substances; conservation of natural resources, including plants and animals. All of these can enhance health and reduce stress, provide an aesthetic experience, and affect community life for the better.
The Peak to Peak Healthy Communities Project, based in Nederland, CO, has worked on renovating parks and creating a transportation link from downtown to trails and natural areas outside the city.
The built environment. People-friendly design of buildings and spaces (human scale, with pedestrian passageways, gathering places, views, attractiveness, etc.); accessibility for people with disabilities; preservation of historic and cultural heritage; cleanliness; safety (lighting, building and bridge design, long views, traffic patterns, restrictions on the use of toxic materials); good public transportation; traffic-free paths to encourage walking, jogging, and bicycling.
For example, a city that builds or designates traffic-free walking and bike paths will probably see more of its residents walk and bicycle to work and on errands than one where walking and biking are difficult and dangerous. Davis, California, for instance, has long encouraged bicycling and developed extensive infrastructure for people who bike, walk, or otherwise travel without cars.
The economic environment. A healthy economic environment is one where there is work for everyone capable of working, where workers are treated as assets (see directly below) and are paid a living wage, where there is equal economic opportunity for all, where those who can’t work are supported, and where money doesn’t buy political power or immunity from the law.
Bethel New Life, a faith-based, grassroots initiative in the Garfield Park neighborhood of Chicago, started out to rehabilitate derelict housing in the area, using “sweat equity” – i.e., the labor of local residents, who could then exchange their work for part of the cost of the home they had rebuilt. Bethel later expanded into housing, employment training and job placement, economic development, cultural, family support, and community development programs. Its work has focused on building assets and bringing greater economic stability to the West Side of Chicago.
The work environment. The work environment should be a source of stimulation, rather than stress. Respect for employees, good safety precautions and procedures, firm rules forbidding harassment or abuse, adequate pay and/or other compensation, humane and fair production expectations and treatment – all contribute to work environments that nurture creativity and enthusiasm, and improve, rather than detract from, both production and workers’ quality of life.
The leisure environment. The work and home environments can provide time for leisure. The community can provide recreational and cultural opportunities to use in that leisure time: museums, parks and beaches, cultural and sports events, libraries, etc.
The social environment. A healthy community encourages social networks, provides gathering places where people from all parts of the community may mingle, nurtures families and children, offers universal education and other services, fosters nonviolent and healthy behavior, invites familiarity and interaction among the various groups that make up the community, and treats all groups and individuals with respect.
The North Quabbin Community Coalition, in north central Massachusetts, was concerned, among other things, with the high incidence of child physical and sexual abuse in the area. A task force on the issue eventually developed into Valuing Our Children, a parent education and family life program that trained area parents as “parent educators” and provided services to area families.
The political environment. In a healthy community, all community members have a say in how and by whom their community is governed, and have easy access to the information necessary to understand political situations and make informed political decisions. Political decisions, opinions, and speech are protected. Community members feel they have power in the community – that they have a stake in it and can and should help control its direction.
Strengthening community action. Communities can encourage and strengthen community action in at least three ways. The first involves encouraging and fostering grassroots planning and action. When issues are identified and addressed by the people affected by them, as well as by others concerned, two things happen: the issues are more likely to be resolved successfully, and the people involved learn how to use their own resources to take charge of their lives and their communities. A second way of strengthening community action is through a commitment from government, community leaders, and other decisionmakers to encourage action by passing legislation conducive to it, lending public support to it through the media and other communication channels, and including members of all segments of the community in the conception, planning, and implementation of any community initiative. The third is by decisionmakers and the media ensuring a free and accurate flow of necessary information about the community and community initiatives to all community members, and providing everyone in the community with learning opportunities about issues and about quality of life in general.
The latter two of these methods are really top-down conceptions where government and others in power “let” community members share in the decision-making process. While community members – particularly those with less experience in planning and running projects, or with less access to formal education – may need support to learn some necessary skills, the drive for change can and should come from them to begin with. There is a big difference between officials organizing an initiative and inviting community members to join, and officials approaching community members with a request to participate in envisioning and organizing an initiative.
Developing personal skills. Healthy communities aid their community members in gaining the skills necessary to address health and community issues, by providing education and information in school, home (through the media and other sources), work, and community settings. Courses, workshops, posters, television and radio messages, news articles, mailings, community meetings, presentations in social clubs and faith communities, and digital communication tools might all serve to help community members understand an issue and make decisions about it.
The education referred to here doesn’t relate only to health and wellness issues and life skills (e.g., parenting). In fact, it could, and does, apply to all learning that touches on topics related to the life of the community – political, social, environmental, and economic issues, for instance. Furthermore, the encouragement and accessibility of lifelong learning is a mark of a healthy community.
Reorienting services. To be useful to a Healthy Cities/Healthy Communities strategy, health and other human and municipal services have to shift from an exclusively individual- and treatment-centered point of view to one that is also community-centered and focuses on the promotion of a healthy community.
It’s not only a matter of reorienting health services, but one of reorienting all services to work together toward the goal of a healthy community. Any community issue has to be viewed through the lenses of both the individual and the community. It takes a village not only to raise a child, but to help families move out of poverty, to create employment, to improve mental health, to stop violence, to safeguard the natural environment, and to create a just and equitable society.
Why use Healthy Cities/Healthy Communities?
There are a number of reasons to consider using the Healthy Cities/Healthy Communities framework in planning and implementing community action:
- Community perspective. Virtually all health and community issues are affected by economic, social, political, and/or environmental factors that operate at the community level. If you don’t deal with those factors, the chances are slim that you’ll be able to resolve the issue you’re concerned with.
- Participatory planning and community ownership. Planning that includes those who will be directly affected by or benefit from any community initiative is more likely to reflect the real needs of the community than planning done only by one group. Furthermore, the participatory nature of the Healthy Cities/Healthy Communities framework means that community members themselves create initiatives and goals for the community. Those initiatives and goals are theirs – not imposed by those in power or by outside “experts.” As a result, their commitment to the process and to the goals makes them far more likely to support and work for the outcomes they’ve chosen.
- Range of ideas. Community participation leads to the presentation and consideration of a greater range of ideas and possibilities, and is therefore more likely to identify effective goals and actions.
- Knowledge of the community. Community participation taps the community’s wisdom about its own history, relationships, and conflicts, and can thus steer initiatives around potentially serious pitfalls.
- Community-wide ties. Involving all segments of the community encourages interaction across social, economic, and political lines. Those ties strengthen the community as a whole, can broaden people’s perspectives, increase community-wide cooperation, and positively transform how the community works.
- Achievable and measurable goals. Although Healthy Cities/Healthy Communities’ ultimate goals are broad and long-term, individual goals can be achievable in a manageable amount of time, and their successful achievement can be demonstrated. Each success sets the stage for enthusiasm for the next initiative.
- Identification and use of community assets and resources. A Healthy Cities/Healthy Communities initiative depends to a large extent on human, institutional, organizational, environmental, and other assets and resources already available within the community. Through identifying and using these, communities learn that they can create their own positive change and reshape themselves in the ways they want to.
- Community commitment to the long-term process. Because of the participatory nature of the process, and because it requires recruiting more people at each new phase, it builds an ever-expanding core of people with varied skills, talents, and experience committed to the ideal of building a healthy community and improving the quality of life for everyone. That’s important for sustaining the work indefinitely.
- Community self-image. Through the use of the Healthy Cities/Healthy Communities process, the community comes to think of itself as a healthy community, and is concerned with maintaining that image through addressing issues as they come up. Perhaps more important, it is brought to look at the larger picture as well. Holding out an ultimate goal of a totally healthy community, whether attainable or not, keeps everyone working toward it, and means that planning goes on as a matter of course. The healthy community ideal becomes embedded in the self-image of the community, and people understand that they can take their future into their own hands and work to improve it. The process itself thus becomes an important element in the definition of a healthy community – one in which community members work together to identify and solve problems, create and consolidate assets, generate improvements, and raise the quality of life for all.
Who should participate in Healthy Cities/Healthy Communities?
The easy answer to this question is everyone in the community, and that’s in fact the ideal. In a perfect world, everyone everywhere would participate in some way in creating a healthy community. In the real world, while it’s important to try to involve all sectors of the community, you have to work to involve some particular people and groups if your effort is to be successful. Crucial participants include:
- Elected and appointed officials. Although a Healthy Cities/Healthy Communities initiative should not be top-down, it needs the commitment and backing of those with the power to make things happen. Officials can use the media to publicize the effort, pass laws and regulations (and enforce those already existing) that reinforce it, and bring the weight and resources of government behind it. Without official support, a community-wide effort is more likely to struggle.
- Those most affected by the issue. A sure recipe for failure is to try to impose an intervention or initiative on a population “for their own good.” All too often, “experts” – sometimes people who have little firsthand knowledge of the group or its issues – formulate plans that might make perfect sense on paper, but make no sense at all in the actual situation for which they’re proposed. The participation of those affected in identifying the issues to address, developing action plans for addressing them, and implementing and overseeing those plans is absolutely crucial to the success of a Healthy Communities initiative. (This is equally true when the group concerned is the whole community.)
There are many instances of a group resisting and short-circuiting well-meaning changes because they weren’t part of the planning. The author experienced one as a teacher in Philadelphia, which had, at the time, an innovative and progressive school superintendent. He tried to institute reforms that probably would have improved the lives of teachers and students in the system, but he did it without conferring with them. As a result, the teachers simply ignored directives from the central office, the reforms failed, and the superintendent was gone within three years.
- The people who will actually administer and carry out the initiative, or whose jobs or lives will be affected by it. It is both unfair and unwise to expect organization staff, community employees (police, firefighters, Department of Public Works personnel, etc.), business people, and others to throw themselves into carrying out an initiative they had no part in devising. It may have elements that ignore the realities of their jobs or their lives, or that make things harder than necessary for them, and they may be the only people who have the information to understand that. In addition, they may regard it as just another foolish imposition to be gotten around, and do as little as possible to make it effective.
- All the agencies and groups that will need to cooperate and coordinate their activities in order to implement a community-wide effort. Both the ways in which these groups will work together, and which of them will have responsibility for what, have to be part of the planning for any community-wide initiative. Without their full participation, there’s no guarantee that they’ll work together at all, let alone that the methods for doing so will be simple and efficient.
- Community opinion leaders. These are the people whose opinions others trust, and who lead the community by adopting new ideas and bringing others with them. They are seen as level-headed, thoughtful, and serving the best interests of the community. Some may be current or former members of the groups already listed, and others may be clergy, respected institutional or business leaders (college presidents or faculty, CEOs), or other community members known for their integrity and common sense.
If you can gain the participation of members of all these groups, it is more likely that others will follow. If you can’t get people from all these groups to buy in at the outset, an alternative is educating them about the process and persuading them to join it, while you continue to recruit other participants. Ultimately, the combination of education and your momentum may bring in those who were initially reluctant. That may take time and patience, but it’s worth the effort – it can easily mean the difference between a successful long-term Healthy Community movement and a dead-on-arrival, failed attempt at one.
How do you use Healthy Cities/Healthy Communities?
Because the Healthy Cities/Healthy Communities framework is just that – an intellectual framework, rather than a prescription – there is no single step-by-step instruction for employing it. It is meant to be adapted to the different needs of different communities. There are, however, necessary components of any Healthy Cities/Healthy Communities initiative:
- Create a compelling vision based on shared values. As with virtually any process that involves planning – and particularly participatory planning – the first step is to create a vision that defines the effort to be made. That vision may be broad (“A community that is truly just and equitable”) or more specific (“A community where every potential worker in the community can find employment that offers a living wage and acceptable working conditions”). Whatever the case, the vision must be compelling – one that motivates people to work for its realization. It must be founded in those values that they hold in common, and must be widely shared and recognized as legitimate and desirable. (Proclaiming Your Dream: Developing Vision and Mission Statements.)
In Orlando, Florida, the Healthy Community Initiative began with meetings of a few influential people. As they learned about healthy communities, they convened a group of about 160, representing all sectors of the city’s population – community members of all races and economic levels, organizations and institutions, city government, and other groups – to hash out a vision. That group, in turn, conducted focus groups and public meetings to hear and understand community members’ concerns. Ultimately, they drafted a vision, based on their own discussions and the input of hundreds of others from all walks of life, that contained 14 statements about what Orlando should be. That vision became the foundation of the initiative.
- Embrace a broad definition of health and well-being. Health must be seen as not merely the physical health of individuals, but the creation and nurturing of those factors leading to health named in the Ottawa Charter (peace, shelter, education, income, food, a stable ecosystem, sustainable resources, social justice, and equity). A truly healthy community encompasses – or works toward – all those elements and more.
- Address quality of life for everyone. The key word here is “everyone.” A Healthy Cities/Healthy Communities initiative should be aimed at improving the quality of life for all groups and individuals in the community, not just those in a particular population of focus or those who began the initiative.
- Engage diverse community participation and be community-driven. Initiatives should be originated, planned, and implemented with the full participation of community members from all racial, ethnic, socioeconomic, and other backgrounds and all walks of life. Community members themselves, rather than a government agency or outside experts, should be the force behind both the direction and the implementation of any community initiative.
- Seek multisectoral membership and widespread community ownership. All sectors of the community – government, the business and nonprofit communities, health care, education, faith communities, cultural institutions and the arts, populations of focus, and other community members – should be represented in an initiative, and the community should feel that it created the initiative and owns it.
In many places in this and other sections of the Community Tool Box, we refer to “ownership” of an initiative or intervention or organization. In most cases, what we mean is that those who take part in creating and/or running such an endeavor feel that it belongs to them. It was their idea, and they therefore see themselves as not only supportive of it, but responsible for it.
True ownership can rarely, if ever, be attached to actions or ideas that are imposed by others who “know better” or have more power. It comes from within, from the feeling that you’ve made a choice based on your best judgment. That’s why the inclusion of people from all sectors of the community is so important to a successful Healthy Cities/Healthy Communities process. At the end, perhaps after a lot of argument and soul-searching, participants feel that they’ve had a hand in creating something important that will result in better lives for everyone in the community. There’s no substitute for that feeling to ensure their doing all they can to make their creation work.
- Acknowledge the social determinants of health and the interrelationship of health with other issues (housing, education, peace, equity, social justice). The research on the social determinants of health points to three overarching factors:
- Socioeconomic equity. Within societies and communities, economic and social inequality can have significant effects on health and quality of life. The size of the income gap between the most and least affluent segments of a society or community is important, and affects whether people have access to what they need.
- Social connectedness. Many studies indicate that “belonging” – whether to a large extended family, a network of friends, a social or volunteer organization, or a faith community – is related to health and well-being, as well as to community participation.
- Sense of personal efficacy. This refers to people’s sense of control over their lives. A stronger sense of efficacy can support health, well-being, and participation in community affairs and politics.
Like the Ottawa Charter, the World Health Organization, in its publication The Solid Facts, identified a number of factors that affect health and life expectancy, and advocated addressing them within a coherent approach that looks at their relationships within society. These factors include:
- The social gradient (equity)
- Stress
- Early life
- Social exclusion (the opposite of social connectedness)
- Work
- Unemployment
- Social support
- Addiction
- Food
- Transport
- Address issues through collaborative problem-solving. Given a diverse group, there are bound to be disagreements and conflicts. These should be viewed as opportunities, rather than roadblocks, and people should be encouraged and helped to work together to reach creative solutions.
- Focus on systems change. To be successful, a Healthy Cities/Healthy Communities initiative has to be active, rather than reactive. It’s not enough to “fix” a problem: your goal is to address the causes of that and other problems and improve the long-term quality of life in the community in the process.
In order to address causes, you have to concentrate not only on individual problems, but on improving and changing systems – the ways in which the community operates, and the attitudes, assumptions, and policies behind them. That includes identifying, using, and strengthening the assets the community already possesses, as well as changing systems that create barriers.
- Build capacity using local assets and resources. All communities, no matter how troubled, have real and potential strengths. These vary from community to community, but could include:
Individuals with the talents, skills, leadership, and passion to work to change the community for the better.
Individuals, businesses, and foundations that can provide material resources – money, space, etc. – to a community effort.
- Institutions – libraries, schools, hospitals, houses of worship – that have the capacity to act as both resources for and agents of change.
- Community-based and other organizations whose mission is to work for the betterment of the whole community.
- Governments and individual government officials that can add both official support and legal and regulatory power to an initiative.
- Human resources – the skills, experience, and commitment of the community’s workforce, for example.
- Natural and other environmental resources – open space, clean air and water, wilderness, fisheries, historic sites or buildings, housing stock.
- Perhaps most important, the potential for all these individuals, groups, and resources to be joined in a coordinated pursuit of a common vision.
- At least some of these and other assets already exist in virtually every community – usually to a far greater extent than most community members realize until they start looking for them. They must be identified and included in a Healthy Cities/Healthy Communities effort.
- Measure and benchmark progress and outcomes. Whatever you’re doing, whether it’s a public relations campaign or a complex behavioral intervention, you have to monitor and evaluate it in order to be sure that it’s effective. That means setting objectives – benchmarks – to indicate your progress along the road to your goal, and defining clearly the outcome you’re aiming for. Regularly monitoring what you’re doing is crucial, because it allows you to spot problems or inadequacies in goals, methods, procedures, communication, etc., and correct them before they derail your initiative entirely. Even more important, regular monitoring allows you to change what you’re doing to respond to changes in circumstances and community needs, so that you’re always addressing current reality. Communities are dynamic: they develop and change, sometimes in short periods. Your initiative has to be dynamic, too, especially if you expect it to continue for the long term.
Implementing a Healthy Communities strategy
How do you actually put these components together to create a healthy community? There’s no one way to do that – it depends on your community, the issues you want to address, and the ideas and capacities of the groups and individuals that participate in the Healthy Cities/Healthy Communities process. There are, however, some basic procedures that, at least in outline, should be common to any Healthy Cities/Healthy Communities initiative.
- Assemble a diverse and inclusive group. To begin a Healthy Cities/Healthy Communities initiative, people from all parts of the community have to come together to hammer out a vision. That group, as we’ve been saying throughout this section, should be representative of everyone in the community, so that whatever it decides will be seen as legitimate by as much of the community as possible, and will be owned by the community.
Someone has to start the process. That may be a charismatic or persistent individual, an organization, a coalition, or a government office or agency. Whoever it is should be simply a convener, and not necessarily expect to lead over the long term. Leaders should be chosen by the group itself as it forms, and they should be collaborative (Collaborative Leadership.)
This is not to say that a Healthy Communities effort doesn’t need leadership. Quite the contrary – leadership and structure are necessary for any successful effort. But leadership should be collaborative and arise from the community. The leader may be an individual, or two, or a larger group. Whatever the situation, leadership should operate among equals, and decision-making should be the province of the whole group. That’s how a participatory process works.
It is assumed that all the other steps listed here will also be carried out by an inclusive group, and that all sectors of the community – including those affected and individual community members – will be represented and have decision-making power. The group may change from step to step or over time, but should remain inclusive and participatory.
- Generate a vision. A vision of how the community should be, based not on a single issue, but on values shared among all participants and on a high quality of life for everyone in the community, is needed to motivate and inspire participants and to guide the initiative over the long term. Generating such a vision may take time and a great deal of discussion, but it’s absolutely necessary for a successful effort.
- Assess the assets and resources in the community that can help you realize your vision, and the issues that act as barriers to it. Placing assets first is not just an accident here. A Healthy Cities/Healthy Communities initiative is best served by looking at the community through a positive lens, and asking first what’s right with it, rather than what’s wrong with it. The initiative then becomes an exercise in community health promotion, instead of the treatment of a diseased community. Taking a positive perspective can improve the attitudes of everyone involved, the community’s self-image, and the perception of whether realizing your vision is possible. By the same token, it’s important to be honest and clear-eyed about issues and problems in the community. Once they’ve been identified, they have to be acknowledged and understood, so they can be addressed at some point in the process.
- Choose a first issue to focus on. The best way to sink a long-term initiative is to try to accomplish all your goals at once. It’s vital to choose one issue – or in some cases, perhaps, two or three – to address, and to make it one that can be resolved, so that your first effort leads to success.
What the issue is doesn’t matter, except in that it must be one chosen by community members as important to them, and must be one that is specific enough to be resolvable. Len Duhl talks about the process in a 1993 interview by Joe Flower in Healthcare Forum Journal.
The first thing that happens when the Healthy Cities program develops in a new place is that some persons assume the responsibility of bringing together all segments of the community to deal with the issues: the business community, the government, the voluntary sector and the citizens themselves. ...
Then there are "vision workshops" in which people are asked, "What kind of city do you really want?" My personal surprise is that the clearer I am about what a Healthy City program is, the less likely a community is to develop it. The fuzzier I am in what a Healthy City is, "A Healthy City is what you want to make it," the greater the odds are that they will start.
The various participants define the program. All I say is that you have to start someplace. You have to begin to look at it in an ecological and systemic way. You have to involve people. You have to start thinking of values of equity and participation. Beyond that, you can start wherever you want.
Some cities start on the environment, on pollution, on smoking, seat belts and the quality of life index. Some have government operations, some have newspapers, big organizations, housing. Barcelona linked it to the Olympics. Glasgow linked it to developing itself as the cultural capital of Europe. It is being done every way.
- Develop a community-wide strategy, incorporating as many organizations, levels, and sectors as possible. Here’s where Healthy Cities/Healthy Communities differs most from many logic models and other methods that are clear on exactly how to go about planning and carrying out an initiative. Rather than offering a step-by-step process, HC might use any participatory planning process that incorporates a community-wide approach and that looks at all the possible areas that might affect the issue chosen. Thus, you might use VMOSA, PRECEDE/PROCEED, or some variant, or a less structured process – whatever seems appropriate and works for your community.
It is important, however, that your plan result in a community-wide, multi-pronged approach. If your focus is on violence involving young people, for instance, it should involve some sort of action or supportive function by local government, parents and parent advocates, schools, law enforcement, the court system, public assistance and human service agencies, organizations that work with young people and families, physical and mental health services, family planning services, the media, adult literacy programs, and young people who have experienced or participated in violence. All of these groups and individuals should be working together as a team, each referring young people to other appropriate services or agencies among them, and all coordinated and collaborating in their operation. The focus should be on changing the systems that make a problem possible, or that present barriers to the ideal the community is working toward.
- Implement the plan. Once again, this should involve a community-wide effort. Any oversight of the implementation should include a broad range of individuals and groups, representing a cross-section of the community.
- Monitor and adjust your initiative or intervention. Once you’ve implemented your plan, it’s crucial to evaluate the effectiveness of both your process (Are you doing what you set out to do?) and your results (Are you reaching your benchmarks? Are you having the planned effect on the issue?) If an evaluation gives unsatisfactory answers to any of these questions, you can revisit the issue, determine the reasons your plan isn’t working well, and change it accordingly.
- Establish new systems that will maintain and build on the gains you’ve made. Once you’ve reduced violence involving young people, for example, you still have to do whatever is necessary to make sure it doesn’t rise again, and that it continues to decline. (What’s the ultimate goal here? Is there an acceptable level of violence involving young people?) That may mean setting up new organizations or programs, working to change or cement changes in community attitudes and procedures, redesigning school curricula, working regularly with the media – whatever it takes to sustain progress.
- Celebrate benchmarks and successes. Public celebration of achievements not only energizes those who have been working toward them, but informs the community that the drive toward a healthy community is moving forward successfully. It helps to establish the idea of a healthy community in the public mind, and to build a foundation for the continuation of the initiative.
- Tackle the next issue(s). The ultimate goal here is the development of a truly healthy community, which translates to improving the quality of life for everyone in the community. After your first success, it’s time to use your momentum to address another (or more than one other) issue. That may be the removal of a barrier to a healthy community, or it may be the creation of a necessary element of a healthy community. In either case, it means sustaining community members’ commitment to an ongoing and long-term process, the end result of which is a community shaped by its residents, where systems work toward the public good.
In Summary
The health of a community, like that of an individual, depends on far more than freedom from pain or disease. Health, or its lack, for a community is the result of a large number of factors, often intertwined, that span the social, economic, political, physical, and environmental spheres. Virtually any community issue has an effect on, and is affected by, the overall health of the community as a whole, and therefore should be approached in a community context. Healthy Cities/Healthy Communities provides a philosophical framework for an inclusive, participatory process aimed at raising the quality of life for everyone, and creating a truly healthy community.
Two basic premises underlying the Healthy Cities/Healthy Communities concept are a comprehensive view of health and community issues, covering a broad range of factors that contribute to a healthy community; and a commitment to the active promotion of a healthy community, rather than the “treatment” of problems. By addressing the social and other determinants of health and community issues (including the Ottawa Charter’s list of peace, shelter, education, food, income, a stable ecosystem, sustainable resources, social justice, and equity), and by creating appropriate policies and environments, encouraging community action, developing personal skills, and reorienting services to a more wide-ranging approach, communities can foster community empowerment and equity.
Reasons for adopting the Healthy Cities/Healthy Communities approach include:
- Its community perspective, leading to a more effective approach to issues.
- Community ownership of any effort, resulting from community participation in its development and implementation.
- The broad range of ideas gained from a participatory process.
- Its access to community members’ knowledge of the community, helping to avoid pitfalls caused by ignorance of community history and relationships.
- The forging of community-wide ties that cross economic, social, racial, and other lines.
- Participatory planning leading to solutions that reflect the community’s real needs.
- The adoption of achievable goals, leading to success.
- The identification and use of community assets and resources, which both take advantage of what already exists and teach the community what it can do with its own considerable resources.
- The fostering of community commitment to the process of building a healthy community.
- The creation of a healthy community self-image.
While a Healthy Cities/Healthy Communities process should involve everyone, some particularly important participants include local government and officials; those affected by the issue(s); those who will actually administer and implement the initiative, or whose lives or jobs will be affected by it; any organizations that will be expected to work together; and opinion leaders.
There are 10 important components of a Healthy Cities/Healthy Communities process:
- Create a compelling vision based on shared values.
- Embrace a broad definition of health and well-being.
- Address quality of life for everyone.
- Engage diverse community participation and be community-driven.
- Seek multisectoral membership and widespread community ownership.
- Acknowledge the social determinants of health and the interrelationship of health with other issues (housing, education, peace, equity, social justice).
- Address issues through collaborative problem-solving.
- Focus on systems change.
- Build capacity using local assets and resources.
- Measure and benchmark progress and outcomes.
Although there is no one step-by-step procedure for a Healthy Cities/Healthy Communities initiative – both the content and the structure of the process depend upon your community’s needs, and particularly on community decisions – there is, given the ten components above, a reasonable way to approach it in most cases.
- Assemble a diverse and inclusive group.
- Generate a vision.
- Assess the assets and resources in the community that can help you realize your vision, and the issues that act as barriers to it.
- Choose a first issue to focus on.
- Develop a community-wide strategy, incorporating as many organizations, levels, and sectors as possible.
- Implement the plan.
- Monitor and adjust your initiative or intervention.
- Establish new systems that will maintain and build on the gains you’ve made.
- Celebrate benchmarks and successes.
- Tackle the next issue.
Resources
Online Resources
(The goal in choosing sites here has been to offer a few that give background or general information on Healthy Cities/Healthy Communities, and a few that are the sites of specific programs. Nearly every Healthy Cities site seems to have its own web page, and these can easily be found by searching “healthy cities” and/or “healthy communities.”)
Bethel New Life, a grass roots, church-based urban development effort in the Garfield Park neighborhood of Chicago. A bottom-up initiative that grew organically over many years, responding to the voiced needs of the community. Most staff and board members are community residents.
Mesa County, CO: A case study of community transformation. A grass roots effort that involved the whole community and grew into the Civic Forum; and a more top-down community health assessment.
Community Partners, Inc., an organization deeply involved in the Healthy Communities movement.
Greater Orlando Healthy Communities Initiative. A very top-down effort, started by current and former Junior League presidents, the newspaper editor, the mayor, and other prominent citizens. They involved the community with the help of a consultant.
The Healthy Communities Program in Aiken, South Carolina. A “model” program, focused on infant mortality. A top-down effort, it nonetheless involves the community in planning and input, and has been highly successful not only at reducing infant mortality, but at providing other needed services, many not directly related to health.
Healthy Cities information from WHO Denmark, the godfather of the Healthy Cities/Healthy Communities movement.
The Healthy Cities initiative of Illawarra, Australia.
Healthy People in Healthy Communities, a guide from the US Dept. of Health and Human Services.
The International Healthy Cities Foundation.
Links to numerous articles on Healthy Cities/Healthy Communities from the Change Project. Includes interviews with Len Duhl and Ilona Kickbusch by Joe Flower from the Healthcare Forum Journal.
The Ottawa Charter.
The Peak to Peak Healthy Communities Project, Gilpin County, Colorado.
The Twenty-Fifth Anniversary of Healthy Communities
WHO information on Healthy Cities
Print Resources
Norris, T. (2002). America’s Best Kept Secret: The Healthy Communities Movement. (Reprint by Healthy Communities Massachusetts from the National Civic Review, introduction, Spring, 1997.) Pan American Health Organization. Healthy Municipalities and Communities: Mayors’ Guide for Promoting Quality of Life. Washington, DC.
Public Health, Vol. 115, Nos. 2 and 3 (March/April & May/June, 2000): Focus on Healthy Communities., Vol. 115.
Wilkinson, R., & Michael M. (1998) eds. The Solid Facts: Social Determinants of Health. World Health Organization: Copenhagen.
What is Healthy Cities/Healthy Communities?
___Healthy Cities/Healthy Communities provides an intellectual and philosophical framework for an inclusive, participatory process of developing a healthy community.
The two basic premises upon which Healthy Cities/Healthy Communities rests are:
___A comprehensive view of health.
___A commitment to health promotion.
Why use Healthy Cities/Healthy Communities?
You use Healthy Cities/Healthy Communities because:
___It takes a community perspective on issues and health promotion.
___It brings a sense of community ownership to any initiative.
___It provides a broader range of ideas.
___It gives access to citizens’ knowledge of the community.
___It encourages community-wide ties.
___It assumes participatory planning.
___It sets achievable goals.
___It asks for the identification and use of community assets and resources.
___It establishes a community commitment to the process over the long term.
___It creates a healthy community self-image.
Who should participate in Healthy Cities/Healthy Communities?
___You try to engage everyone in the community.
You make particular efforts to engage:
___Local officials.
___Target populations.
___Anyone who implements or administers, or whose life or job will be changed or affected by, the initiative.
___All the agencies, organizations, and institutions that will need to cooperate or collaborate in order to realize goals.
___Local opinion leaders.
How do you use Healthy Cities/Healthy Communities?
You include the necessary components of a successful Healthy Cities/Healthy Communities initiative by encouraging the community to:
___Create a compelling vision based on shared values.
___Embrace a broad definition of health and well-being.
___Address quality of life for everyone.
___Engage diverse citizen participation and be citizen-driven.
___Encourage multisectoral membership and widespread community ownership.
___Acknowledge the social determinants of health and the interrelationship of health with other issues (housing, education, peace, equity, social justice).
___Address issues through collaborative problem-solving.
___Focus on systems change.
___Build capacity using local assets and resources.
___Measure and benchmark progress and outcomes.
To approach a Healthy Cities/Healthy Communities process, you:
___Assemble a diverse and inclusive group.
___Generate a vision.
___Assess the assets and resources in the community that can help you realize your vision, and the issues that act as barriers to it.
___Choose a first issue to focus on.
___Develop a community-wide strategy, incorporating as many organizations, levels, and sectors as possible.
___Implement the plan.
___Monitor and adjust your initiative or intervention.
___Establish new systems that will maintain and build on the gains you’ve made.
___Celebrate benchmarks and successes
Example 1: The Mayor’s Guide for Promoting the Quality of Life, produced by Maria Teresa Cerqueira, Marilyn Rice, and their colleagues at the Unit on Healthy Settings, the Area of Sustainable Development, Pan-American Health Organization (PAHO)
PAHO is the Americas’ regional arm of the World Health Organization (WHO). In the Mayor’s Guide, it presents an alternative to the top-down model of health care and maintenance, and an example of the ways in which PAHO encourages the building of healthy communities. Rather than setting out a prescription for creating healthy communities, the Guide offers some basic principles and a framework within which municipalities and communities can work to plan and carry out initiatives that meet their unique needs.
While PAHO serves all of the Americas, the Guide is – rightly – oriented toward the countries in the region with the greatest needs and most difficult health situations. Its emphasis on shoring up the “infrastructure” of health – the physical, political, economic, and social conditions whose presence promotes, and whose absence prevents, healthy living and a good quality of life – is likely to benefit most the less developed nations where that infrastructure is weakest. At the same time, its encouragement of participatory process and decision-making speaks to all the countries in the hemisphere.
Rather than simply describing it, we’re including an edited version of the Mayor’s Guide here, as an example of a Healthy Communities framework. Also included are links to relevant Community Tool Box sections and tool kits.
Guide for Mayors and Other Local Authorities
Key Concepts related to the Healthy Municipalities and Communities (HMC) Strategy
This guide is intended to strengthen the implementation of health promotion activities at the local level, placing health promotion on the political agenda of mayors and other local authorities… [I]t is hoped that efforts will be made to ensure healthy public policies, the maintenance of healthy environments, and the promotion of healthy lifestyle.
What is the Importance of Having a Kit for Mayors and Other Local Authorities?
…PAHO offers a basic set of tools with which mayors and other local authorities can begin to implement the HMC strategy…[T]his material does not by any means pretend to be a “prescription for, or key to, success”…Successful experiences have shown that there is no single best way to deal with problems that arise.
[L]ocal government is closest to the people and can use its resources to achieve major improvements in health and the quality of life. As the community’s representative, the municipal government is in the best position to involve politicians, administrators from other sectors, and the community itself in coordinating joint projects. Finally, at the local level it is possible to mobilize the collective will…
What is the Healthy Municipalities and Communities Strategy?
The mission of the Healthy Municipalities and Communities Strategy consists of improving the implementation of health promotion and protection activities at the local level and ensuring that such activities are accorded the highest political priority, thereby encouraging the participation of government authorities and the active participation of the community…[Its] objective is to promote health together with people and communities, in settings where they study, work, play, love, and live.
A municipality begins the process of becoming healthy when its political leaders, local organizations and citizens commit themselves to, and initiate, the process of continuously and consistently improving the health and quality of life of all its inhabitants…It uses local planning as a basic tool, including social participation in management, evaluation, and decision-making. A municipality becomes healthy with sustained long-term improvement in social conditions with a view to ensuring the health and quality of life of all those who live within that particular environment.
What Do We Mean by a Comprehensive Vision of Health?
…WHO regards health as a fundamental human right and defines it as “a state of complete physical, mental and social well-being, and not the mere absence of disease or infirmity.” Several factors have been identified that affect, and often determine, the health of individuals and communities, including:
- Living and working conditions (income, education employment, physical environment, public policies);
- Psychosocial factors (care groups and/or support networks; sense of belonging to a community; the environment in which children develop; social support of family and friends; support for older adults, adolescents, pregnant women, and other vulnerable populations);
- Individual behaviors (lifestyles and behaviors: physical exercise, diet, tobacco use, alcohol and drug abuse); and
- Genetic factors.
Research indicates that living and working conditions have the greatest influence on health. Therefore, health is as much the result of our physical and social environment…as it is a product of the health-care system and social services. [See Chapter 17, Section 5, Addressing Social Determinants of Health and Development.]
What Do We Mean by Health Promotion?
The Ottawa Charter for Health Promotion (1986) defines health promotion as “the process of enabling people to increase control over, and to improve, their health”… Health promotion goes beyond the health-care sector alone, emphasizing that health should be part of the political agenda of all sectors and at all levels of government. Furthermore, the participation of the population/community is essential if health promotion actions are to be sustained.
[F]ive priority action areas are recommended:
- Build healthy public policy;
- Create supportive environments;
- Strengthen community action;
- Develop personal skills; and
- Reorient health services.
What Do We Mean by Community Participation?
…Members of a community may or may not reside in the same geographical area. What is important is that they consider themselves to be a community. An organized community is not necessarily a participatory community. To facilitate participation, the community should be given the right and opportunity to make effective decisions regarding issues affecting the lives of its members.
Steps in Developing Community Participation:
- Become familiar with the community…This step permits technical personnel and local government to comprehend how the community understands and explains the world, whether through its beliefs, folklore, or other ways of looking at life, and to know its assets. [See Chapter 3, Sections 1, Developing a Plan for Identifying Local Needs and Resources, 2, Understanding and Describing the Community, and 8, Identifying Community Assets and Resources.]
- Build a common vision. [See Chapter 8, Section 2, Proclaiming Your Dream: Developing Vision and Mission Statements.]
- Utilize language and communication resources appropriate to the cultural context of the community. [See Chapter 6, Sections 1, Developing a Plan for Communication, and 19, Handling Crises in Communication; Chapter 27, Section 1, Understanding Culture and Diversity in Building Communities; and Chapter 45, Section 5, Promoting Awareness and Interest Through Communication.]
- Keep the community informed and ensure that it takes part in decision-making throughout the process. [See Chapter 18, Section 2, Participatory Approaches to Planning Community Interventions.]
- As the community members perceive and establish a relationship between the HMC goals and their personal lives, their health, education, housing, and other conditions, they are also able to set personal goals and feel a sense of responsibility, not just for a community initiative but for their lives in general.
What Do We Mean by Creating Effective Strategic Alliances?
Strategic alliances are relationships and agreements between different stake-holding sectors, organizations, and actors in order to achieve a desired goal. The most common strategic alliances are carried out with government agencies; health institutions and other related sectors such as education, judicial, transportation and agriculture; nongovernmental organizations (NGOs); schools and universities; the mass media; religious groups and public and private organizations. [See the CTB Toolkit 1: Creating and Maintaining Partnerships, as well as Chapter 5, Sections 5, Coalition Building I: Starting a Coalition, and 6, Coalition Building II: Maintaining a Coalition; Chapter 7, Encouraging Involvement in Community Work; and Chapter 9, Section 3, Developing Multisector Task Forces or Action Committees for the Initiative.]
What Do We Mean by Healthy Public Policies?
Healthy public policies are those that have a significant positive influence on people’s health status through their influence in the areas of education, housing, food, human resources, employment, mental health, and sustainable development. [They are] characterized by an explicit concern for health and equity…[,and] the recognition and effective exercise of the rights of the people, based on equality, with no restrictions imposed on access to, or use of services provided by different social sectors.
Healthy public policies should be translated into legislation that safeguards the conditions necessary for developing healthy lifestyles…:guaranteeing the human rights and fundamental liberties of members of the community; protecting communities, families, and individuals from risk factors; and promoting conditions that ensure that the healthiest options are those that are most accessible and most easily attainable.
Why Has the HMC Strategy Been So Successful and Appealing in the Region of the Americas?
[It] has helped to support and focus the decentralization process that many countries have been undergoing, and in light of the democratization of local decision-making, it has provided a platform on which all local stakeholders can participate in defining priorities and key interventions in a collaborative manner…Health promotion programs are more cost-effective than treatment…By coordinating the efforts of different sectors and actors, resources can be maximized and duplications eliminated.
What are the Essential Elements of a Healthy Municipality and Community?
- Building public commitment by the mayor and municipal council, local government (key sectors), nongovernmental and private sectors and the community (leaders and representatives of organizations and social groups) to the process of improving the quality of life through the HMC strategy. [See Chapter 7, Section 6, Involving Influential People in the Initiative.]
- Ensuring and continuously strengthening community participation during the planning, implementation, and evaluation phases. The HMC Strategy calls for strong community involvement and action and offers a genuine chance to strengthen and consolidate democratic processes at the regional level, especially through the participation of civil society in making decisions about priorities, activities, and the use of resources. [See Chapter 7, Encouraging Involvement in Community Work; Chapter 13, Sections 5, Developing a Community Leadership Corps, and 11, Collaborative Leadership; and Chapter 18, Section 2, Participatory Approaches to Planning Community Interventions.]
- Developing a strategic plan to overcome obstacles and threats to developing and maintaining a healthy municipality or community. This plan highlights the need to mobilize internal and external resources, provide adequate support and technical cooperation, and create healthy spaces. The participatory, multi-sectoral development process encourages decentralization and should enhance the ability of local communities to make decisions and control resources. [See the CTB Toolkit 5: Developing Strategic and Action Plans, as well as Chapter 8, Developing a Strategic Plan.]
- Building consensus and forming partnerships through various networks and projects comprised of a wide range of institutions and organizations, both within the health sector itself and with other sectors. Efforts are made to reach consensus among participants with opposing views. The strategy strongly supports the inclusion of local governmental representatives, NGOs and the private sector. “A partnership for health promotion is a voluntary agreement between two or more partners to work cooperatively toward a set of shared health outcomes.” [See the CTB Toolkit 1: Creating and Maintaining Partnerships, as well as Chapter 1, Section 7, Working Together for Healthier Communities: A Framework for Collaboration Among Community Partnerships, Support Organizations, and Funders.]
- Encouraging leadership and the participation of all social sectors including the health sector, as many strategies and activities extend beyond the capacity of the health sector alone. At the same time, reorienting health services to include health promotion and illness prevention is both a major challenge and a fundamental opportunity that should be pursued. Care should be taken to guard against excessive control by the health sector. [See the CTB Toolkit 6: Building Leadership, as well as Chapter 13, Section 5, Developing a Community Leadership Corps, and Section 11, Collaborative Leadership.]
- Formulating healthy public policies at the local, regional, and national levels. This process enables capacity building of those involved in a more democratic form of governance; it gives people the opportunity to participate in public decision-making that affects them, their families, and their communities. [See the CTB Toolkit 11: Influencing Policy Development, as well as Chapter 25, Sections 1, Changing Policies: An Overview, and 10, Modifying Policies to Enhance the Quality of Services.]
- Conducting ongoing monitoring and evaluation to track and assess progress of the initiative, and to identify the intended and the unintended results. It is critical that information and surveillance systems are strengthened and are used to rethink and revise the activities of the initiative. [See the CTB Toolkit 12: Evaluating the Initiative, as well as Chapter 36, Introduction to Evaluation and Chapter 38, Some Methods for Evaluating Comprehensive Community Initiatives.]
Sustainability: How to Guarantee the Continuity of a Healthy Municipality and Community Initiative
Lessons learned from previous experiences have shown that initiatives that are initiated and/or motivated from outside the community often fail to sustain themselves or continue over time. …Experience shows that in communities where social participation and community organization are high, there is greater opportunity to ensure the continuity of the HMC Strategy and for social organizations and new authorities to negotiate its continuation. The key then is to motivate all community actors sufficiently so that they become involved in and make a commitment to a medium- and long-term process. …Securing the support of the municipal council or legislature is essential in guaranteeing a regulatory framework for the sustainability of HMC because it helps to ensure that the HMC initiative will remain effective and operational regardless of any institutional changes that may occur in the local authority. [See the CTB Toolkit 16: Sustaining the Work or Initiative as well as Chapter 45, Social Marketing of Successful Components of the Initiative, and Chapter 46, Planning for Long-Term Institutionalization.]
Establishing HMC Networks
At the Second Latin American Congress on Healthy Municipalities and Communities held in Boca del Rio, Mexico, in 1997, 18 nations signed an agreement to create the Latin American Network of Healthy Municipalities and Communities to build and strengthen their national networks and ensure their sustainability. Networks make it easier to share information about successes and challenges and facilitate addressing the needs of other groups and at different levels, such as the private sector, government, and international organizations, and can play a major role in the development of new experiences. … In some countries of the region, such as Mexico, Costa Rica, Chile, and Cuba, national networks have already been established and have been working for a number of years with good results.
Why Are Evaluation and Monitoring Important?
Evaluation and monitoring play a fundamental role in the health promotion and protection process because they empower individuals and communities to make informed decisions, justify the expenditures and the contributions of donors, improve the initiatives, and contribute to the health promotion knowledge-base. Making informed decisions contributes to empowerment – one of the basic concepts of the health promotion strategy – which means achieving the power to make decisions concerning individual or collective actions, with a view to improving the quality of life and social justice. In monitoring it is particularly important to strengthen the information and surveillance systems at the community level in order to collect data and information, and make sure that it is reviewed appropriately by all involved groups, including the community. Evaluation examines how an undertaking meets the standards and objectives of a project, whereas monitoring is concerned with the “continuous overseeing of the implementation of an activity to make sure that inputs, schedules, targets, and other actions required are proceeding according to plan.”
It is through monitoring that a thorough understanding of a project can be grasped, and all impacts planned and unplanned can be observed. Policy monitoring allows decision-makers and community members to have a thorough grasp of the policies that are being implemented, and how they are affecting the community in order to adjust, modify, or change actions to best serve their own local needs. Evaluation is important because it enables members participating in initiatives to reflect on the work being carried out in terms of its limitations and achievements, determine whether municipalities and communities are indeed adhering to initial proposals, and refine actions or activities in keeping with their needs. It is an important feedback mechanism for all participants in the process, and can also increase the legitimacy of health promotion activities.
Phases of the Healthy Municipalities and Communities Strategy
Initial and Organizational Phase (1 to 3 Months)
Expected Outcome:
An approved proposed HMC strategic plan
Suggested Strategies:
- Conduct a participatory assessment with the community to ascertain the health and quality of life situation of the municipality or community by identifying needs, enabling conditions, obstacles and resources. [See the CTB Toolkit 2: Assessing Community Needs and Resources, as well as Chapter 3, Assessing Community Needs and Resources, and Chapter 18, Section 2, Participatory Approaches to Planning Community Interventions.]
- Create an intersectoral and municipal committee to carry out a consultation with the community and together define a common vision and mission. Also, it is important to designate a focal point on the municipal council for the HMC Strategy. [See Chapter 5, Sections 5, Coalition Building I: Starting a Coalition, and 6, Coalition Building II: Maintaining a Coalition; and Chapter 9, Section 3, Developing Multisectoral Task Forces or Action Committees for the Initiative.]
- Develop a proposed strategic plan through a participatory and intersectoral process – which should include local authorities, community (including men and women of all ages and ethnic groups) and other organizations – that defines objectives, goals, expected results, and targets. [See Chapter 8, Developing a Strategic Plan.]
- Gain approval and assign resources for the plan by the Municipal Council. [See Chapter 7, Section 6, Involving Influential People in the Initiative.]
- Present, discuss, and disseminate the approved plan through a public forum. [See Chapter 3, Section 3, Conducting Public Forums and Listening Sessions.]
Planning Phase (4 to 6 Months)
Expected Outcome:
A work group and detailed work plan
Suggested Strategies:
- Designate members of the intersectoral municipal committee to be part of a working group for activity implementation and monitoring.
- Develop a detailed work plan based on the community assessment (Initial Phase) with activities, assigned responsibilities and resources, a timeline, and indicators for monitoring and evaluation. [See the CTB Toolkit 7: Developing an Intervention, as well as Chapter 19, Choosing and Adapting Community Interventions.]
- Identify strategies to encourage sustained participation and partnerships for the implementation of the plan and resource mobilization.
[See the CTB Toolkit 5: Developing Strategic and Action Plans and Chapter 8, Developing a Strategic Plan.]
Action Phase (2/3 years and beyond…):
Expected Outcome:
A Healthy Municipality and Community
Suggested Strategies:
- Promote local healthy public and institutional policies and intersectoral actions.
- Develop a policy framework and infrastructure to support and sustain the implementation of the Healthy Municipalities and Communities Strategy. [See the CTB Toolkit 11: Influencing Policy Development, as well as Chapter 25, Changing Policies.]
- Create a range of healthy spaces.
- Encourage politicians and other decision-makers to commit themselves to community capacity-building, strengthening the HMC Strategy and ensuring its sustainability and intersectoriality. [See Chapter 33, Sections 10, General Rules for Organizing for Legislative Advocacy, and 11, Developing and Maintaining Ongoing Relationships with Legislators and Their Aides.]
Expected Outcome:
Community Participation
Suggested Strategies:
- Involve the community (including women and men of all ages and ethnic groups) in the entire process, from initial assessment of the situation, to actions to identify resources and possible solutions, to implementation, monitoring, and evaluation.
- Identify strategies to mobilize the community effectively while respecting the cultural and social values of each specific population.
[See Chapter 7, Encouraging Involvement in Community Work; Chapter 18, Section 2, Participatory Approaches to Planning Community Interventions; and Chapter 27, Sections 1, Understanding Culture and Diversity in Building Communities, and 8, Multicultural Collaboration. See also the CTB Toolkit 9: Enhancing Cultural Competency.]
Expected Outcome:
Communications
Suggested Strategies:
- Use all forms of communication available in the community (mass media, interpersonal discussions, organized groups and all forms of cultural expression including events, songs, dances, story telling, etc.) [See Chapter 6, Communications to Promote Interest.]
- Ensure that messages and information are shared with the community on a continuous basis.
- Adapt health promotion messages (addressing action throughout the life cycle) to specific target audiences, taking into account reaching vulnerable population groups.
- Promote the messages of the HMC Strategy, utilizing existing positive examples and influential personalities. [For more information on how to carry out this and the previous strategy, see Chapter 45, Social Marketing of Successful Components of the Initiative, as well as the CTB Toolkit 13: Implementing a Social Marketing Effort.]
Expected Outcome:
Capacity-Building
Suggested Strategies:
- Use multiple channels to offer capacity-building (i.e., courses, Internet meetings, etc.)
- Include orientation and skill development for each aspect of HMC development.
Expected Outcome:
Monitoring and Evaluation
Suggested Strategies:
Cover process, outcome, and impact, including quantitative and qualitative indicators. Make it participatory and interactive. [See the CTB Toolkit 12: Evaluating the Initiative.]
Guidelines for Evaluating Healthy Municipalities and Communities
[PAHO considers evaluation so important that it devotes a separate part of the Mayor’s Guide to it. The Guide explains that, since “[e]valuation should be a continuous cycle of ongoing feedback,” monitoring is an ongoing activity, and that the term “evaluation” includes it. Evaluation is not something that only takes place once a year or at the end of a project, but an ongoing part of the HMC Strategy. The Community Tool Box supports relevant to all of these guidelines for evaluating a healthy municipalities initiative are the Toolkit 12: Evaluating the Initiative and Chapters 36, Introduction to Evaluation; 38, Some Methods for Evaluating Comprehensive Community Initiatives; and 39, Using Evaluation to Understand and Improve the Initiative.]
Why and What to Evaluate
Evaluation of healthy municipalities and communities is very important for many reasons, including:
- Providing the stakeholders the opportunity to reflect on the HMC initiative.
- Designing the best HMC initiative in the context of the community health resources and needs.
- Creating accountability, or determining/gauging if the healthy municipality is doing what was proposed, and redirecting efforts when needed.
- Contributing to general knowledge development; sharing what works and what doesn’t work with other communities.
- Sustaining the work of HMC over time.
- Creating opportunities for intersectoral multidisciplinary dialogue, and strengthening participatory efforts within the municipalities.
- Developing networks, links, and contacts between different community processes.
- Convincing decision-makers and policy-makers that HMC is a beneficial strategy.
… Because of the participatory nature of healthy municipality initiatives, it is suggested that participatory evaluation play an important role in the evaluation of healthy municipality initiatives. …[I]t is a collaborative approach that builds on strengths and values the contribution of everyone involved.
[A PAHO] working group on healthy municipality evaluation in the Americas…recommended different areas that should be taken into account when evaluating HMC initiatives, such as context, planning and implementation of the evaluation, and evaluation methodologies:
Context
- Evaluation must factor in the different political, economic, social, and cultural contexts of the country, municipalities, and communities involved in the evaluation. It is important to consider the influence of the following:
- Socioeconomic and political situation (national and local)
- Local and national policies
- Local health situation
- Administrative structures and management styles, both national and local
- Geographical, ecological, and demographic characteristics
- Stage in the development process of the healthy municipality
- Sociocultural aspects
Considerations for Planning and Implementing Evaluations
- The conception and development of the evaluation as a formative process originating from the municipalities and the stakeholders. This implies adopting the rigor and complexity required by the topic and the collective definition of the variables and indicators to be used.
- The definition of work processes that ensures: a) a broad and diverse commitment that reflects a consensus of joint evaluation objectives, and b) clearly identified ways to disseminate this work to other relevant groups.
- The relationships between health and well-being and between health and development.
- The conceptual definitions of what “healthy” means in the context of the psychosocial and physical aspects of the environment, health promotion, human and social development, and equity.
Evaluation Methodologies
- Utilize an evaluation methodology that integrates qualitative and quantitative approaches.
- Develop qualitative indicators constructed with the actors involved in the process itself – this requires intersectoral and participatory work. [See Chapter 3, Section 15, Qualitative Methods to Assess Community Issues.]
- Aim for an evaluation that covers structures, processes, and outcomes.
- Take advantage of the information available in each municipality, strengthening the existing databases with qualitative data (and creating databases where they do not exist).
- Conduct the evaluation recognizing the influence of the various levels (international, national, and local, and, at the local level, institutional/government and community forces or social groups) and contexts (geographical, demographic, political/administrative, economic-environmental, social, and cultural). [See Chapter 36, Section 2, Community-Based Participatory Research.]
Areas for Evaluation
The following areas have been identified as key in the evaluation of healthy municipalities:
- Public Policies
- Social Participation
- The Intersectoral Approach
- Sustainability
- Development Process Undergone by the HMC Initiative
Evaluating the Process
…[I]t is wise to think about evaluation from the very beginning…Good evaluation goes hand in hand with planning. A planning approach that works well with for participatory evaluation is one in which evaluation, implementation, and planning activities interact with each other at any point in the life of the endeavor.
[E]valuation should review the various steps of the process itself: its successes, difficulties, strengths, and weaknesses. It should not simply register, describe, or quantify attainments and products.
Evaluating Results
Results in health promotion are dynamic and diverse in nature, and measuring these results can include information from the following areas:
- Health education
- Influence and social action
- Healthy public policies and organizational practices
- Healthy living conditions and lifestyles
- Effectiveness of health services
- Healthy environment and spaces
- Social results
- Health outcomes
- Capacity-building and development
[The following] is a list of suggested guidelines [for evaluating healthy municipalities initiatives] but it is not comprehensive; it is recommended that each HMC advisory group or committee review, adapt and augment the guidelines based on the evaluation needs and particular context.
Describe the context
- Clearly define the vision of the healthy municipality initiative. What does the community understand by the phrase “healthy municipalities”? What do the various sectors involved understand by the phrase? What activities are being carried out in order to achieve this goal? How will people know when those objectives have been met? [See Chapter 8, Section 2, Proclaiming Your Dream: Developing Vision and Mission Statements.]
- Use the logical framework method to illustrate the steps involved in the process as well as the expected results. [See the CTB Toolkit 4: Developing a Framework or Model of Change, as well as Chapter 2, Section 1, Developing a Logic Model or Theory of Change.]
- Establish an intersectoral group comprised of community representatives to coordinate and perform the evaluation. [See Chapter 36, Section 4, Choosing Evaluators.]
- When will the evaluation be carried out? Within what timeframe?
Indicate causes for concern
- What is the purpose of the evaluation? What are the main concerns of the various parties involved?
- How will the results of the evaluation be used?
- What are the specific questions that need to be addressed by the evaluation within the context of the healthy municipalities initiative?
- Are public policy, the intersectoral approach, social participation, and sustainability addressed in the questions and the objectives?
- Do the evaluation’s questions and objectives address the basic principles of the HMC movement (the concern for equity, the intersectoral approach, social participation, and strengthening local capacities)?
Organize the data-collection process
- What methodologies will be used? (This will depend on the responses to the questions above.) Have a range of qualitative methods been considered?
- Are the methods appropriate to the local context? Have both process and results been taken into account?
- Is the methodology understandable to those involved?
- Have pilot studies been conducted, using the same tools that will be used in the evaluation?
- Have the tools to be used in the evaluation been validated?
- How will broad participation be achieved?
- Is care being taken to include marginalized groups or individuals (both from among those who are the object of the evaluation and those in charge of conducting it) in the proposed evaluation? [See Chapter 36, Section 2, Community-Based Participatory Research.]
Compile the data
- This task should be carried out using the methods established in the previous steps.
- This task should be monitored to ensure that the data compiled are of good quality.
Describe, analyze, and evaluate the data
- What was learned through the evaluation?
- How different are the results from what was expected?
- Were the qualitative and quantitative methods complementary?
- How can discrepancies be addressed and resolved?
- Consider the possibility of using other qualitative methods in order to provide more information about unexpected results.
- Promote the participation of interested parties in the interpretation of the results.
[See Chapter 17, Analyzing Community Problems and Solutions.]
Make recommendations
- What are the short- and long-term implications of the conclusions?
- What changes might be made to address negative results? Analyze recommended changes, taking their costs and benefits into account.
Disseminate conclusions
- Communicate conclusions, recommendations, and anticipated actions to donors, all interested parties, networks, etc.
- Use the Internet to share experiences wherever appropriate.
Make changes based on the results of the evaluation
- Obtain feedback from all evaluation participants.
- Adapt initiatives wherever necessary.
- Continue to monitor evaluations.
[See Chapter 39, Using Evaluation to Understand and Improve the Initiative.]
The steps listed might also be presented as a continuous cycle.
Other principles for evaluation [agreed upon at a 2001 conference by the Working Group on the Evaluation of Healthy Municipalities and Communities Initiatives in the Americas]
Value
The evaluation process must reveal any theoretical, ideological, or political assumptions and explicitly indicate any power relationships (including those in which the evaluator is involved). The evaluation should also respect and value experience and local knowledge, recognizing the people as the principal health resource. The evaluation should embody a spirit of hope, happiness, love, and fun, while never forgetting equity, social justice, and solidarity.
Empowerment
Evaluation of Healthy Municipalities initiatives should:
- be based on the community’s strong points;
- support local problem-solving;
- ensure equity by allowing all voices to be heard, including the voices of the most vulnerable and least powerful; and
- make it possible for information about the evaluation to be used by those concerned to lobby for and promote Healthy Municipalities.
Usefulness
Evaluation of Healthy Municipalities initiatives is useful when:
- it answers the questions of who, why, and how;
- it is integrated into the planning process and oriented toward action and change;
- it contributes to the creation of resources in the community;
- it has practical and political relevance;
- it helps define the healthy municipality as an investment; and
- it recognizes the need for a range of dissemination methods and feedback mechanisms.
Learning
Evaluation of Healthy Municipalities initiatives should:
- promote a joint learning process;
- promote dialogue and reflection, and encourage all means of developing knowledge by those affected and influenced by the process, including any external evaluators;
- recognize that learning is the key to the community and to increasing the capacity for local organization; and
- lead to action and change.

Adolescence is a time of experimentation. Young people test themselves physically, intellectually, socially, and emotionally, all in the service of learning what it means to be an adult. Most young people move through their teen years without experiencing serious, lasting problems. They may have some close calls and have their hearts broken once or twice, but, by and large, they move into adulthood, go on to further education or work, and build lives for themselves.
Some young people experience more serious challenges. They may smoke heavily, drink excessively, use drugs, become involved in violence, get in trouble with the law, experience pregnancy or parenthood during adolescence, or even die – including by suicide or in an alcohol-related driving crash.
We often view young people who have difficulty in a negative way: they have “problems,” or are seen as lacking basic traits – intelligence, self-control, empathy, or persistence, for instance. There’s another way to consider the issue, however: perhaps these young people simply haven’t had enough of the factors in their lives that adolescents need in order to grow into successful, caring, productive adults.
A child benefits from caring parents or caregivers, of course, but is also helped by having positive lessons and values reinforced by what they see and hear from other adults in the community, and by the behavior of society as a whole. It really does take a village to raise a child.
Chapter 2 of the Community Tool Box is about models of community change – ways to introduce changes that will continue improving the quality of life for everyone in the community indefinitely. In this section, we’ll discuss using a model of community change that focuses on young people. It assumes that fostering the internal and external assets that contribute to the healthy development of children and adolescents is the task not only of parents and caregivers, but of the whole community, and proposes that communities be organized to accomplish it. And it assumes that improving life for the community’s children and adolescents will also improve it for the community as a whole.
What is asset development?
Developmental assets are positive characteristics and factors that form the foundation of the healthy development of children and adolescents. A community engaged in asset development for young people is committed to identifying developmental assets that may be less available to children and adolescents in the community, and to working to strengthen access to those assets. The Search Institute (SI) of Minneapolis, Minnesota developed a framework of 40 developmental assets for adolescents, based on its own survey research and the theories and research of others in the field.
In the research summarized in this section, the more of these assets adolescents reported having in their lives, the less likely they were to report behaviors or situations that increased risk. Those behaviors and situations included:
- Substance use (alcohol, drugs, tobacco).
- Sexual activity. Sexual activity during adolescence can involve emotional and physical risks. Those risks can be greater when protection is not used or when adolescents have multiple sexual partners.
- Violence. This can mean anything from experiencing bullying or abuse to carrying or using a gun.
- Behavioral and legal problems. The range here extends from persistent conflict with teachers or other authority figures to serious trouble with the law.
- Depression and suicide risk. Not all depression leads to suicide, of course, and not all adolescents experiencing depression consider suicide. Depression during adolescence can nevertheless be serious, and suicide is a critical concern.
- School difficulties. Academic difficulties, truancy, absence, etc.
- Alcohol-impaired driving. A combination that can lead to arrest, property damage, injury, and death.
- Gambling. Gambling can lead to serious financial problems and put adolescents and their families under significant pressure when debts accumulate.
Thriving indicators are the traits or conditions that indicate positive development. Search Institute studies summarized in this section also found that the more developmental assets adolescents reported, the more thriving indicators they were likely to have. The thriving indicators measured included:
- School success. Good grades, mostly A’s or A’s and B’s.
- Helping others. Spending at least one hour a week helping others outside one’s own family.
- Valuing diversity. Having friends from different ethnic and racial groups, and an interest in their experiences and cultures.
- Good health. Engaging in behaviors – exercise, adequate sleep, good nutrition, and regular medical and dental care – that promote and maintain good physical health.
- Leadership. Taking a leadership position at school, in extracurricular activities, or in the community.
- Resistance to danger. The ability to manage one’s own impulses and peer pressure in order to avoid dangerous behavior and situations.
- Delaying gratification. The ability to save for a future purchase, or otherwise put off immediate pleasure in favor of a larger or more important gain later.
- Overcoming adversity. The capacity to keep going after a failure, or to continue a task or effort in the face of difficulty.
The original list of developmental assets SI compiled numbered 30, but it was increased to 40 as a result of information received in its early surveys. The list was derived both empirically – i.e., as a result of information gathered directly by the Search Institute itself – and from the theories and research of others.
In the studies summarized here, SI identified 31 or more assets as an ideal range associated with positive adolescent development, while fewer than 10% of adolescents surveyed reported that many. The average number reported in most of the communities described was 18-20, and more than 60% of young people surveyed reported 20 or fewer. The communities surveyed were largely White, but varied in economic status, education, types of employment, and urban, suburban, and rural characteristics.
The survey described in this section consisted of 156 items, each intended to gather information about a specific asset, behavior that increases risk, or thriving indicator. It was designed for young people in grades 6-12. The emphasis was not on completing it within a particular amount of time, but on providing accurate information, with appropriate allowance for age, reading ability, language fluency, and other factors that could affect completion.
Half of the 40 assets are labeled external, provided directly by parents, teachers, the community, or environmental factors. The rest are considered internal, coming from within the adolescent. In reality, however, the distinction is less clear. Internal assets are often specifically taught or encouraged by parents, caregivers, and other significant adults, for instance, or are fostered by community norms and attitudes. External assets may also be influenced by the child’s or adolescent’s relationships, experiences, and individual characteristics.
External assets are further divided into four categories:
- Support. People significant to the adolescent encourage, help, and respect them.
- Empowerment. The adolescent has opportunities to exercise responsibility and to feel a sense of control over important parts of their own life.
- Boundaries and expectations. The adolescent is expected to adhere to clear rules and meet high standards.
- Constructive use of time. The adolescent has opportunities to engage in meaningful and productive activity.
Internal assets are also divided into four categories:
- Commitment to learning. The adolescent understands the value of learning and education, and can apply themselves in school and other areas of learning.
- Positive values. The adolescent has developed and internalized a positive value system.
- Social competencies. The adolescent possesses personal and interpersonal skills to manage their own life and engage in positive relationships with others.
- Positive identity. The adolescent sees themselves in a positive light and has a healthy sense of self-worth.
What are the characteristics of an asset development program?
In the process described in this section, a community organizes to conduct an asset assessment, often through the schools, administers the survey, and receives an analysis of the results. The community then uses that information to determine how to respond to its own needs. Many communities have used their initial organization to mount a participatory effort based on the analysis.
Communities that have assessed developmental assets have used their results to create community plans for supporting children and adolescents.
Once a community – or, more likely, a school system, community-based organization, parents’ group, community official, or governing body – has decided to establish an asset development approach, what should that approach look like? There are some specific characteristics common to a careful asset development effort.
- The effort demands a commitment from the whole community. The asset development approach assumes that, to address challenges affecting young people, it isn’t enough to focus only on individual adolescents experiencing greater risks. A community must make a commitment to developing supportive assets for all its young people. In broadest terms, that commitment includes:
- A commitment to administering an asset assessment or conducting a similar study that asks children and adolescents themselves – and, in some cases, adults important in their lives and in the community – about the assets they believe are available to them.
- A commitment by community leaders – elected and appointed officials, school personnel, the business community, opinion leaders, etc. – to support an asset development effort, both with their voices and their resources.
- Acceptance by the community of the idea that asset development is a community-wide activity that demands a commitment from adults whether or not they are parents.
- The effort should be participatory. As with most types of community efforts, asset development works best if it is conceived, planned, and implemented through a process that involves all sectors of the community, particularly those most directly affected – young people, in this case. A participatory process often involves the formation of a coalition or other leadership body that includes representation from all sectors of the community, including young people, to plan, coordinate, monitor, and oversee asset development efforts.
- The effort should be based on what’s actually needed in the particular community. An asset assessment or some other form of community assessment should be conducted to determine which assets are already widely available to young people and which may need strengthening. Strategies can then be devised to strengthen assets that are less available while maintaining those that are already strong.
- The effort should focus on the positive. Like the other health and community development models we’ve discussed so far in this chapter, asset development has a proactive, positive thrust. It is based on building assets rather than fixing deficits. An asset-developing community is engaged in positive actions that are meant to become an integral part of community life and to affect the quality of that life for generations to come.
At the same time, the need to strengthen assets may coexist with immediate concerns – violence involving young people, school difficulties, substance use among adolescents, etc. Asset-building may be accompanied by strategies that address current problems as well as seek to keep them from recurring. While stronger developmental assets may help reduce violence involving young people over time, for instance, it’s also important to address immediate safety concerns. You can keep a positive and future-oriented emphasis on the overall effort and still deal with current realities. Don’t let ideology steer you away from reality.
- Asset development demands a coordinated, community-wide effort. This means something slightly different from community commitment, although that commitment is probably necessary for a community-wide effort to be mounted. An asset development effort needs to be carefully coordinated so that all sectors of the community – young people and adults, health and human service organizations, community-based and nonprofit organizations, community officials and agencies, businesses, etc. – are working together toward the same goals and sending the same messages.
A community-wide effort also implies that people throughout the community take responsibility for supporting the community’s children and adolescents. It may mean adults responding appropriately when they see a young person in a situation likely to lead to harm or serious trouble. It may also mean parents, caregivers, and other adults volunteering time with adolescents or younger children as coaches, supervisors of after-school activities, community-service mentors, etc.
In the working-class urban neighborhood where the author grew up, for instance, adults knew the children in the neighborhood and wouldn’t hesitate to intervene or call a parent if they saw a child doing something likely to cause trouble. While that made childhood mischief a problem, it also meant that children felt fairly safe. They knew adults would intervene to keep them from getting hurt, and they also knew that the rules would be enforced throughout the neighborhood. In that environment, adults generally felt some responsibility for the children around them, whether or not they were parents themselves.
What are the developmental assets that children and young people need?
The following list of the 40 developmental assets, divided into categories, is based on the Search Institute’s 1997 framework.
External Assets
- Support
- Family Support – Family life provides high levels of love and support.
- Positive Family Communication – Young person and parent(s) communicate positively, and the young person is willing to seek advice and counsel from parents.
- Other Adult Relationships – Young person receives support from three or more nonparent adults.
- Caring Neighborhood – Young person experiences caring neighbors.
- Caring School Climate – School provides a caring, encouraging environment.
- Parent Involvement in Schooling – Parent(s) are actively involved in helping the young person succeed in school.
- Empowerment
- Community Values Youth – Young person perceives that adults in the community value young people.
- Youth as Resources – Young people are given useful roles in the community.
- Service to Others – Young person serves in the community one hour or more per week.
- Safety – Young person feels safe at home, in school, and in the neighborhood.
- Boundaries and Expectations
- Family Boundaries – Family has clear rules and consequences and monitors the young person’s whereabouts.
- School Boundaries – School provides clear rules and consequences.
- Neighborhood Boundaries – Neighbors take responsibility for monitoring young people’s behavior.
- Adult Role Models – Parent(s) and other adults model positive, responsible behavior.
- Positive Peer Influence – Young person’s best friends model responsible behavior.
- High Expectations – Both parent(s) and teachers encourage the young person to do well.
- Constructive Use of Time
- Creative Activities – Young person spends three or more hours per week in lessons or practice in music, theater, or other arts.
- Youth Programs – Young person spends three or more hours per week in sports, clubs, or organizations at school and/or in the community.
- Religious Community – Young person spends one or more hours per week in activities in a religious institution.
- Time at Home – Young person is out with friends “with nothing special to do” two or fewer nights per week.
- Internal Assets
- Commitment to Learning
- Achievement Motivation – Young person is motivated to do well in school.
- School Engagement – Young person is actively engaged in learning.
- Homework – Young person reports doing at least one hour of homework every school day.
- Bonding to School – Young person cares about their school.
- Reading for Pleasure – Young person reads for pleasure three or more hours per week.
- Positive Values
- Caring – Young person places high value on helping other people.
- Equality and Social Justice – Young person places high value on promoting equality and reducing hunger and poverty.
- Integrity – Young person acts on convictions and stands up for their beliefs.
- Honesty – Young person “tells the truth even when it is not easy.”
- Responsibility – Young person accepts and takes personal responsibility.
- Restraint – Young person believes it is important not to be sexually active or to use alcohol or other drugs.
- Social Competencies
- Planning and Decision Making – Young person knows how to plan ahead and make choices.
- Interpersonal Competence – Young person has empathy, sensitivity, and friendship skills.
- Cultural Competence – Young person has knowledge of and comfort interacting with people from different cultural, racial, and ethnic backgrounds.
- Resistance Skills – Young person can resist negative peer pressure and dangerous situations.
- Peaceful Conflict Resolution – Young person seeks to resolve conflict nonviolently.
- Positive Identity
- Personal Power – Young person feels they have control over “things that happen to me.”
- Self-Esteem – Young person reports having high self-esteem.
- Sense of Purpose – Young person reports that “my life has a purpose.”
- Positive View of Personal Future – Young person is optimistic about their personal future.
Why would you (and why would you not) use an asset development approach?
Advantages to the asset development approach
- It’s based on extensive research. The asset development concept, as well as the contents of the asset list, grew out of Search Institute research with adolescents as well as research and theory by others in the field.
As discussed above, the research summarized in this section included surveys of more than a million adolescents. It found associations between the number of assets adolescents reported and both behaviors that increase risk and thriving indicators.
While the average number of assets reported was fairly steady across communities in this research, the particular assets that were present or less available varied by community. Thus, although adolescents in several surveyed communities might report a similar average number of developmental assets, the specific assets in question could be significantly different in each community. By the same token, young people in each community might report different behaviors that increase risk and different thriving indicators. An assessment can help each community better understand which assets, challenges, and thriving indicators are common among its young people.
The research described here does not establish a simple one-to-one relationship between particular assets and particular behaviors or thriving indicators. Communities therefore need to be careful about assuming that one specific asset will automatically produce one specific result.
- Its participatory approach to planning and implementing the effort encourages community buy-in and puts many minds to work. The emphasis on an inclusive and widespread process increases the chances that the community will see the effort as its own, and thus work hard to make it succeed. Including all sectors of the community, particularly young people, in planning and implementation provides a broad range of knowledge and ideas to work with and can increase the effectiveness of the effort.
Including young people, particularly those experiencing greater risks or barriers, reduces the likelihood that the effort will be seen as just another attempt by adults who may not understand their experiences. If young people are involved from the beginning, treated with respect, and know that their opinions matter, they’re more likely to see themselves as part of the effort.
- Placing the accent on positive asset development can make challenges affecting young people seem more possible to address. A community facing high levels of violence involving young people, substance use, or pregnancy among adolescents may see no clear solution to the problem. If the issues are multiple, they can seem even more difficult to address. A positive approach – actively building assets and strengthening adolescents’ connections with supportive adults and institutions – allows the community to identify constructive steps it can take to bring about change.
- Each community develops its own approach to asset development, based on the assets it needs and other factors unique to it. Rather than taking a cookie-cutter approach, asset development encourages the examination of each community as a unique entity. Each community examines its own situation and develops asset-building strategies designed for its own needs.
- Data can be analyzed in numerous ways. It may be that young people attending one school report different asset needs than those attending another, or that young people from a particular neighborhood or population report different experiences than others. Breaking down assessment data can help a community understand those differences and plan accordingly.
- Asset development aims at long-term social change. With its focus on the next generation, and on changes in attitudes and behavior throughout the community, an asset development approach can contribute to long-term positive change.
- Asset development can address a broad range of issues. School difficulties, leaving school before graduation, crime involving young people, substance use among adolescents, pregnancy among adolescents – all of these and more may be affected by the ongoing strengthening of developmental assets and by changes in community attitudes and behavior.
- Asset development can increase community cohesiveness. Because it concentrates on continuity and on preparing the next generation, an asset development approach can bring together people throughout the community to work toward its future. That not only heightens awareness of the meaning of community among those involved, but creates a sense of purpose as well. People aren’t just solving a problem – they’re moving forward into the future as a community.
- Healthy Youth helps to foster a Healthy Community. SI calls its asset development approach Healthy Community/Healthy Youth. If you focus on supporting the healthy development of all young people in the community, you’re focusing on the development of the community as well. A healthy community is one where children and adolescents have access to the support and opportunities they need. If that happens, the chances are that equity is being nurtured in other areas as well.
Despite these reasons to pursue asset development, there are also cautions to consider before proceeding with it.
Potential disadvantages to the asset development approach
- The original data underlying the framework were drawn from a largely White sample of young people. The research described in this section drew heavily from a population that was about 80% White. That raises questions about how well findings from that sample represent young people from the full range of racial, ethnic, cultural, and community backgrounds. Surveying only young people also raises several considerations:
- First, self-reported data reflect adolescents’ own perceptions of their lives and circumstances. Those perceptions are important, but they may differ from the perspectives of parents, caregivers, teachers, or others.
- Second, school-based surveys may not fully capture the experiences of young people who are no longer enrolled in school. Excluding them could leave an important part of the community’s adolescent population out of the assessment.
- Finally, perspectives from adults who are significant in adolescents’ lives may add useful context to young people’s responses.
- An assessment by itself does not tell a community exactly how to develop assets. The ability of each community to plan for its own unique needs is an advantage, but communities may still need research, technical assistance, and local expertise to decide how best to strengthen the particular assets they choose to address.
- Using an external survey and analysis process may require resources and reliance on an outside organization. Communities need to consider the costs, timing, support, and analysis available through whatever assessment process they choose.
The original section also discussed CADY (Community Asset Development for Youth) as an alternative asset-development model. At the time described, CADY focused more narrowly on reducing substance use, violence, and bullying among young people and combined an asset framework with identified community deficits.
It also sought information from school personnel, parents, community leaders, community members, and young people. This broader set of perspectives was intended to provide additional context for understanding conditions affecting adolescents.
At the same time, the model described here provided young people with less direct involvement in planning and coordinating the asset-development program and relied more heavily on leadership from schools, agencies, officials, and organizations. That distinction is important in a section that emphasizes participatory community work.
- Small communities or small schools may not have large enough populations for detailed statistical analysis. Statistical analyses require enough participants to produce reliable findings, particularly when a community wants to examine smaller subgroups. Rural communities and small schools may therefore face limitations in how specifically they can break down their results.
- There is no guarantee that an asset-development effort will address every current problem. Asset development is largely future-oriented. Young people currently experiencing serious difficulties may need immediate forms of support in addition to a longer-term community asset-building strategy.
- Another question is how developmental assets function at different ages and stages of development. Older adolescents and young adults may respond differently from younger adolescents, and communities should not assume that the same strategy will have the same effect for everyone.
- Most adolescents do well despite not reporting the ideal number of assets. Even though relatively few adolescents in the research summarized here reported the number of assets SI associated with optimal development, that does not mean that everyone with fewer assets is experiencing serious difficulties, or that everyone with many assets is necessarily doing well. The developmental assets can be useful indicators without determining any individual young person’s future.
The SI picture of an adolescent with all the desired assets can sometimes look like an ideal young person from an adult’s point of view – good grades, likes school, helps others, and avoids experimenting with potentially harmful behavior. Sometimes we lose sight of the fact that adolescents also question, test limits, experiment, and sometimes flounder as they develop an adult identity. The ideal is to provide ways for them to do that as safely as possible, but not every adolescent will follow the same path, assets or not.
Then there are the poets, the dreamers, the rule-breakers who refuse to be bound by convention. They may spend their adolescence struggling, sometimes because they don’t have support for who they are from either their families or society. Some may continue to struggle as adults, while others may go on to make remarkable contributions. They may not fit an ideal asset profile, but they may still be developing internal strengths that shape their future.
There is little question within the framework presented here that children and adolescents benefit from developmental assets, particularly support from caring adults. But some internal assets may develop later, as older adolescents test themselves against the adult world. The fact that they don’t yet appear to have every asset may be part of the process of adolescence. An asset-development approach therefore has to leave room for the questioning, experimentation, and occasional failure that can be part of developing an adult identity.
- When considered together, the advantages listed here may outweigh the potential disadvantages, but those disadvantages still deserve attention. Perhaps an overriding reason to consider asset development as a means of community building is that supporting the next generation is one of the most important functions of a community. An inclusive, participatory effort to provide young people with support, opportunities, values, skills, and meaningful roles can sharpen the community’s focus on what a community is and does. The result can improve the quality of life not only for young people, but for the whole community.
How do you use an asset development approach?
A note about asset development approaches:
This section examines a specific logic model – the Search Institute framework of 40 developmental assets for adolescent growth and development. The original approach described here included use of a formal survey and analysis process. Not all communities, however, have the resources – or the desire – to approach asset development in so formal a way.
There are ways around this. One – perhaps the most straightforward – is to focus on developing and/or strengthening developmental assets broadly. Another is to focus on an area that you already know represents a gap in your community – involving young people in town government and community service (empowerment), for instance, or creating or strengthening mentoring programs for parents and adolescents (support). Still a third is to develop your own method of identifying assets and gaps, perhaps with help from a university or another research partner if such support is available.
A fourth possibility is that you can employ asset development as part of a larger healthy community initiative. You may want to take SI’s 40 developmental assets into account without using them as the sole foundation for your effort.
Much of what follows assumes the use of a structured asset assessment. It’s important to realize, however, that that’s not necessarily the only way to address developmental assets in your community.
Once you’ve decided to employ an asset development approach in your community, how do you go about it? Because a successful effort has to involve the whole community, it’s not just a matter of starting and picking up support as you go along.
Someone has to take the initiative. Whether or not you plan to use a formal survey, the community has to be informed about developmental assets and prepared to focus on them. Existing efforts may be spearheaded by schools, but one could be led by other entities as well:
- A pre-existing coalition
- Civic officials or a civic agency – the mayor or the police department, for instance
- A parents’ or caregivers’ group
- A community-based or other nonprofit organization, particularly one that works with, or is concerned with, young people
- A community-wide nonprofit, such as United Way
- A faith-based organization or clergy association
- A business or a business group, such as the Chamber of Commerce
Form a coalition or other group to introduce asset development (and the idea of an asset assessment) to the community. The group should contain people from all sectors of the community, including young people, and should be participatory, involving everyone in decision-making.
Whoever takes the initial lead should expect to be a collaborative leader and allow for the possibility of sharing leadership with, or relinquishing leadership to, a community member or group.
Good communication by this group – in speaking, in writing, and through the media – is crucial to the success of an asset development effort, especially if a survey is to be part of it. (Please see Communicating Information about Health and Community Issues and Promoting Awareness and Interest Through Communication.) People may have questions about surveys and about how their responses will be used. In order to build trust, the coalition or group should provide the information people need, answer questions candidly and clearly, and try to anticipate common concerns. Questions people in many communities might have include:
- Who is conducting the survey or assessment? What organization is involved, what are its credentials, and what role will it play?
- What other communities have used this assessment, and what did they do with the results?
- Is the survey anonymous and confidential? What will happen to the results after they’re tabulated? Can young people or their parents opt out?
This last question, if not carefully considered, can cause major problems. If you go through the schools, the school system may have its own requirements regarding parental permission and research involving students, and may also be subject to applicable laws or policies. Whether parents are asked to take a positive action to allow participation, or are informed of the process and given an opportunity to decline, can be an important issue. It’s the kind of detail that can stall or even prevent a community effort if it isn’t handled carefully.
- What will the assessment cost the community?
- Who will be responsible for setting up the assessment and transmitting, receiving, and publicizing the results?
Once the community agrees to pursue an asset assessment, its logistics have to be worked out. Will the survey be carried out in school? Will all eligible young people be surveyed, or only those in certain schools or grade levels, or a sample? If subgroup analysis is important, the community also needs enough participants to produce meaningful results for those groups.
- If the school system isn’t able or willing to administer the assessment, another local organization, members of the coordinating coalition, or another appropriate group may be able to assist. Whatever process is used, it is useful to designate a coordinator to manage communication and administration.
Implement the assessment. The survey or other assessment now has to be administered, collected, and prepared for analysis. If it is school-based, the cooperation of the school system will probably be important. Communities may also want to consider ways of hearing from young people who are not enrolled in public schools, so that the assessment does not automatically exclude their experiences.
Analyze the assessment results. Once the assessment has been completed and analyzed, the community has to make sense of the findings: which assets appear widely available, which appear less available, which challenges are most common, and whether experiences differ among groups of young people.
- If an outside organization conducts the analysis, communities should understand what interpretation or technical assistance is included and what additional support, if any, may be needed to move from results to action.
By this point, more people may want to be part of your coordinating or planning group. It’s probably a good idea to keep the group open to new membership in some way, although a group that’s too big can become unwieldy. The formation and use of subcommittees or task forces may be one way to keep the planning group to a reasonable size and still accommodate many people who want to help.
Depending on how the population is assessed and how results are reported, an examination of the findings can tell you:
- Which assets are most often less available to young people in your community.
- Which behaviors or situations that increase risk are most common among young people in your community.
- Whether experiences differ among groups of young people by neighborhood, school, age, gender, socioeconomic conditions, or other relevant factors.
- Which thriving indicators are most often found, and among whom.
Communicate your findings to the community. If this is to be a community-wide effort, the community has to have as much information as possible. The coordinating group or individual should communicate the results through the media, public meetings, neighborhood gatherings, community organizations, schools, and other channels that can reach people throughout the community. The goal is to prepare community members to take part in planning the next steps if they so choose, and to think about their eventual participation in an asset development effort.
Plan your next steps. The character of your plan will depend on which developmental assets your community decides to address, but there are some general steps that can be helpful in any planning process.
- Convene a diverse, inclusive, and participatory planning group (or, as mentioned above, a number of task forces or committees, perhaps one for each related group of assets you plan to address), representing all sectors of the community, including young people. It might be the same group that has guided the process so far, that group with members added, or an entirely different group. Some people may be invited to join because of their skills or influence; others may volunteer solely out of interest and dedication to the community.
- Determine what assets you’ll focus on. A community with considerable resources – money, people, space, available expertise, etc. – might decide to address many assets at once. Another with fewer resources might choose to focus initially on one area – support, for instance – and/or on a particular part of the youth population.
Many communities may decide that the appropriate focus is all adolescents and/or children in the community. A “community,” however, could be a relatively small neighborhood as well as a diverse city or a whole rural county. How the community is defined may have a great deal to do with where its focus lies.
- Do your research. Find out what other communities have done, and how. Look at promising and effective practices, and at the research on the areas you’re addressing. Enlist faculty and students at local colleges and universities to help.
Research on asset and child/adolescent development can help communities understand different approaches to strengthening developmental assets. Community partners, universities, and organizations with experience in youth development may all be useful sources of information and assistance.
- Develop a strategic plan for building assets. The strategic plan is long-range, and should serve as a guide to what may be a decades-long process of community change. This is your conception of how you’ll build and maintain developmental assets in your community over time, including which you’ll approach first, how you’ll keep the community involved, how you’ll measure your success, etc. It should include a timeline, with benchmarks to check your progress against.
- Design an action plan. In general, each benchmark will require some kind of action – often an effort or program designed to address a particular developmental asset or group of assets. Each of these actions will need its own action plan, describing exactly what you’re going to do and how. Issues to consider here are cultural differences in the community and the actual practice of promoting the development of various assets. The Community Tool Box deals with the specifics of interventions and initiatives in a number of different areas, many focused specifically on young people.
Strategic and action plans can be devised regardless of whether you choose to use a formal survey. Developing and strengthening developmental assets can remain a goal even when many are already strong among the community’s young people. Assets won’t necessarily remain strong without continued support for parents and caregivers, adolescents, teachers and other adults significant in young people’s lives, and community members in general.
Present the plan to the community. Communication is again the key here. Community members should have a chance to understand, discuss, and react to the plan. Their feedback should then be considered in developing a final version.
Implement your initial action plan. Once you’ve finalized how you’re going to approach developing assets, it’s time to get to work. The first phase of your plan may involve only one small group of assets, or it may address changing your community in many ways.
Continue to monitor, evaluate, and adjust your action plan. As with any type of intervention or action, it’s vital to make sure that you’re doing what you planned, and that it’s having the results you aimed for. If either of these is not the case, or if circumstances in the community change, you may need to alter what you’re doing, or even rethink it completely. Even if it’s working well, careful monitoring and evaluation can often show you ways to make it better.
Continue to form, implement, monitor, and adjust new action plans, and to maintain the gains you’ve made. As you make progress in asset development, remember that the goal is to transform the community over the long term. Once assets have been made more widely available to adolescents and children in the community, that access has to be maintained. The work of making your community a place where all children and adolescents are valued, supported, and able to thrive has no end.
In Summary
Asset development is the fostering of developmental assets that can support children and adolescents in becoming healthy, caring, productive, and successful adults. The Search Institute framework described in this section identifies 40 assets and links adolescents’ reported access to those assets with both behaviors that increase risk and “thriving indicators.”
Assets are divided into eight categories. Four are external (support, empowerment, boundaries and expectations, and constructive use of time), and four are internal (commitment to learning, positive values, social competencies, and positive identity).
The research summarized in this section found that adolescents varied widely in the number of assets they reported. The framework emphasizes not only how many assets are available to young people, but which assets appear strong or less available within a particular community.
Asset development is a community enterprise that demands commitment from people throughout the community, from school and civic officials to businesses, institutions, organizations, community members, and young people themselves. Because asset development has to be seen as a shared community responsibility, the effort should be inclusive and participatory, helping to foster community ownership. It should be focused on the actual needs of the particular community and emphasize the positive – proactively building assets rather than simply reacting to problems. The effort should also be community-wide.
Advantages of an asset-building approach:
- A foundation in both empirical research and theory.
- Community ownership and diverse, broad-ranging input stemming from a participatory process.
- An emphasis on positive asset development that can make challenges affecting young people seem more possible to address.
- The ability of each community to design asset-building solutions that fit its own needs.
- The ability to analyze data in multiple ways and across different populations.
- An emphasis on long-term social change.
- The capacity to address a broad range of issues.
- The possibility of increasing community cohesiveness.
- The emphasis on what supports young people also contributing to the health of the community.
Potential disadvantages or limitations of the asset development approach:
- Limitations in how representative the original research sample was of all young people and communities.
- An assessment alone may provide limited guidance about exactly how to develop particular assets.
- Formal assessment and analysis may require outside expertise or resources.
- Statistical limitations that may make detailed analysis difficult for small communities or schools.
- No guarantee that asset development alone will address immediate problems.
- Questions about how developmental assets function across different young people, ages, and life circumstances.
In sum, the potential benefits of focusing on developmental assets may outweigh the limitations for many communities, but those limitations shouldn’t be ignored.
Although each community’s approach to asset development will be different, based on the needs and resources of the community, there are some basic steps that can be used to structure the process:
- Someone has to take the initiative.
- Form a coalition or other group to introduce asset development and the idea of an asset assessment to the community.
- Once the community agrees to pursue asset development, work out the logistics of the assessment.
- Implement the assessment.
- Analyze the assessment results.
- Communicate your findings to the community.
- Plan your next steps.
- Convene a diverse, inclusive, and participatory planning group, representing all sectors of the community, including young people.
- Determine what assets you’ll focus on.
- Do your research.
- Develop a strategic plan for building assets.
- Design an action plan.
- Present the plan to the community.
- Implement your initial action plan.
- Continue to monitor, evaluate, and adjust your action plan.
- Continue to form and implement new action plans and maintain the gains you’ve made.
Resources
Online Resources
Asset-Based Community Development is an excellent guide provided by the Indianapolis Neighborhood Resource Center that includes useful examples, sample worksheets, and real-life scenarios as well as tips.
An Asset-Based Approach to Skills-Banking within Respond! Communities. A research working paper prepared by Respond!
Building from Strength: Asset-Based Community Development is an article by John E. Walker from the Northeast Assets Leadership Project.
Chapter 10: Empowerment in the "Introduction to Community Psychology" addressed the different levels of empowerment, how to contribute to power redistribution, and ways to take action to make changes in communities.
The Family Leadership Connection, and organization started in California, based on both SI’s 40 Developmental Assets and on the asset-based community development work of John McKnight and others at Northwestern University. FLC offers both parent training and training in becoming a parent trainer.
Community Asset Development for Youth (CADY); A report to the Michigan Department of Education and the Michigan Office of Drug Control Policy on the Genesee County Pilot Test.
The Search Institute: information on asset development, the 40 developmental assets, links, resources, etc.
What is asset development?
___You work to build the 40 developmental assets that will support and enhance the healthy development of children and adolescents in your community.
___You seek to develop assets that will help youth guard against high-risk behaviors and patterns.
___You seek to enhance the assets that encourage thriving indicators in youth:
What are the characteristics of an asset development program?
___You seek commitment from the whole community.
___You create an inclusive, participatory effort.
___You base your effort on what’s needed in the community.
___You focus on the positive.
___You seek a comprehensive, community-wide effort.
What are the developmental assets kids need?
___You are familiar with the 40 developmental assets listed in the section.
Why (and why not) should you use an asset development approach?
___You are familiar with the advantages of an asset-building approach:
- A strong base in both empirical research and theory.
- Community ownership and diverse, broad-ranging input stemming from a participatory process.
- An accent on positive asset development, making youth issues seem more resolvable.
- The ability of each community to design its own asset-building solutions.
- The ability to analyze data in numerous ways and by different populations.
- An emphasis on long-term social change.
- The capacity to address a broad range of issues.
- The possibility of increasing community cohesiveness.
- The emphasis on what’s best for youth leading to what’s best for the community.
___You know the potential disadvantages to the asset development approach:
- A data base that’s 80% white and all youth for the Search Institute’s 40 assets.
- No real guidance as to how to develop assets.
- Community dependence on the Search Institute or CADY to analyze the surveys.
- Statistical limitations that may make accurate analysis difficult for small communities or schools.
- The lack of any guarantee that asset development will address current problems.
- The question of how necessary assets actually are for eventual success for most youth.
How do you use asset development?
___You find someone to take the initiative (or do it yourself).
___You form an inclusive, participatory group to introduce the asset development concept and the idea of the survey of developmental assets to the community.
___You work out the logistics of administering the survey.
___You implement the survey.
___You analyze the survey results.
___You communicate the survey results and analysis to the community.
___You plan your next steps.
___You develop an initial action plan.
___You implement your action plan.
___You monitor, evaluate, and adjust your plan.
___You continue to develop, implement, monitor, and adjust action plans, and to maintain the gains you’ve made.

Many funders and health and human service organizations aim to make progress on large and complex social problems – such as improving educational outcomes for all children, reducing homelessness, or improving community health outcomes. This has proved challenging for all of us.
This community-level work goes by different names and associated models – including collaborative action, community mobilization, and comprehensive initiatives. One version of this approach is known as “collective impact.” Collective impact refers to the commitment of participants and organizations from different sectors to a common agenda for addressing a specific social problem at scale. Like other models in Chapter 2 of the Community Tool Box, this section aims to provide an overview of this approach and links to resources for its implementation.
WHY USE A COLLECTIVE IMPACT APPROACH?
A premise of the collective impact approach is that not all problems are created equal – some are simple, some are more complicated, and some are truly complex. Each type requires a somewhat different approach to solving it.
- An example of a simple problem is baking a cake – the right “recipe” is essential, but once you’ve discovered it, replication will get you almost the same result every time.
- An example of a complicated problem is sending a rocket to the moon – the right “protocols and formulas” are needed, as are high levels of expertise and training. Experience is built over time to get to the right result, which can be repeated with the expectation of success.
- An example of a complex problem is raising a child – there are no “right” recipes or protocols that work in every situation. There are many outside factors that influence the situation, and every situation is unique. Experience helps, but in no way guarantees success.
A single service program may be quite appropriate for addressing problems that are simple or only somewhat complicated. Collective impact, however, is an approach to addressing complex social problems.
Taking a collective impact approach requires moving away from more isolated ways that service organizations may attempt to address problems. Isolated approaches to making an impact on outcomes often look like this:
- Funders select individual grantees.
- Organizations seeking to implement change work separately and often compete with one another for funding.
- Evaluation is structured to isolate a particular organization’s impact to show progress.
- Large-scale change is assumed to depend upon scaling individual organizations or interventions.
- Business and public sectors are not heavily involved in the process.
Like other approaches to collaborative action, the collective impact approach engages multiple participants in working together to address complex social problems:
- Funders and implementers understand that social problems – and their solutions – arise from the interaction of many organizations and community forces within a larger system.
- Organizations actively coordinate their actions and share lessons learned.
- Progress depends on working toward the same goal and measuring the same things.
- Large-scale change depends on increasing cross-sector alignment and learning among many organizations.
- Business and public sectors are essential partners.
What Is Collective Impact?
As noted above, collective impact is the commitment of participants and organizations from different sectors to a common agenda for addressing a specific social problem at scale.
Organizations and communities have used collective impact approaches for years. Collective impact initiatives generally incorporate five conditions associated with their success:
- Common Agenda
- All participants share a vision for change that includes a common understanding of the problem and a joint approach to addressing it through agreed-upon actions.
- Shared Measurement
- All participating organizations agree on the ways success will be measured and reported, with a short list of common indicators identified and used for learning and improvement.
- Mutually Reinforcing Activities
- A diverse set of stakeholders, typically across sectors, coordinate differentiated activities through a mutually reinforcing plan of action.
- Continuous Communication
- All participants engage in frequent and structured open communication to build trust, maintain shared objectives, and create common motivation.
- Backbone Support
- Dedicated, funded staff provide ongoing support to the initiative by helping guide its vision and strategy, supporting aligned activities, establishing shared measurement practices, building public will, advancing policy, and mobilizing resources.
Below is a selected list of Community Tool Box resources that support implementation of a collective impact approach.
Common Agenda
- Toolkit 3: Analyzing Problems and Goals
- Toolkit 7: Developing an Intervention
- Chapter 2, Section 9: Community Readiness
- Chapter 2, Section 13: MAPP: Mobilizing for Action through Planning and Partnerships
- Toolkit 5: Developing Strategic and Action Plans
- Chapter 8, Section 1: An Overview of Strategic Planning or “VMOSA” (Vision, Mission, Objectives, Strategies, and Action Plans)
- Chapter 8, Section 2: Proclaiming Your Dream: Developing Vision and Mission Statements
Shared Measurement
- Chapter 3, Section 9: Developing Baseline Measures of Behavior
- Chapter 3, Section 18: Creating and Using Community Report Cards
- Chapter 3, Section 19: Using Public Records and Archival Data
- Chapter 8, Section 3: Creating Objectives
Mutually Reinforcing Activities
- Chapter 1, Section 7: Working Together for Healthier Communities: A Framework for Collaboration Among Community Partnerships, Support Organizations, and Funders
- Chapter 1, Section 8: Some Lessons Learned on Community Organization and Change
Continuous Communication
- Chapter 6, Section 1: Developing a Plan for Communication
- Chapter 6, Section 2: Using Principles of Persuasion
- Chapter 6, Section 3: Preparing Press Releases
- Chapter 6, Section 4: Arranging News and Feature Stories
- Chapter 6, Section 6: Preparing Guest Columns and Editorials
- Chapter 6, Section 7: Preparing Public Service Announcements
- Chapter 6, Section 8: Arranging a Press Conference
- Chapter 6, Section 9: Using Paid Advertising
- Chapter 6, Section 10: Creating Newsletters
- Chapter 6, Section 11: Creating Posters and Flyers
- Chapter 6, Section 12: Developing Creative Promotions
- Chapter 6, Section 13: Creating Brochures
- Chapter 6, Section 15: Creating Fact Sheets on Local Issues
- Chapter 6, Section 16: Creating a Website
- Chapter 6, Section 17: Using Email Lists
- Chapter 6, Section 18: Using Direct Mail
- Chapter 6, Section 19: Handling Crises in Communication
- Chapter 4, Section 5: Making Community Presentations
- Toolkit 13: Implementing a Social Marketing Effort
- Chapter 4, Section 2: Communicating Information about Community Health and Development Issues
Backbone Support
The term “collective impact” was introduced in a 2011 article in the Stanford Social Innovation Review.
Collective impact has been applied to social change efforts in a variety of fields and domains. Examples identified in this section include:
In education
In public health
- Shape Up Somerville
- LiveWell Colorado
- Global Alliance to Improve Nutrition (GAIN)
- Tackling Youth Substance Abuse
In addressing homelessness
In youth development
In economic/urban development
In community development
In addressing environmental issues
When Is a Collective Impact Approach Appropriate?
You can use the following readiness assessment to determine whether a collective impact approach is appropriate for your situation. This assessment is most valuable when completed by a group of stakeholders committed to addressing a specific social or environmental issue, with the results and implications discussed together.
- Is a collective impact approach appropriate for pursuing your goals?
- There are many forms of collaboration, each suited to different types of social and environmental issues. Consider whether you are addressing a complex, large-scale social or environmental issue. Do you have the time and resources required?
- Do the preconditions exist for the potential success of a collective impact approach?
- Are there influential champions, sufficient resources to support the planning process and infrastructure, and enough urgency to address the issue in new and different ways?
- Are the nuts and bolts for a collective impact approach already in place?
- If your group has determined that this collaborative approach is appropriate and the preconditions are in place, an in-depth readiness assessment can help you take stock of the extent to which the necessary structures are in place to begin your work.
Collective impact is not right for every problem. The process can take a long time and requires significant resources to sustain – resources from partners making new investments and changing their practices, as well as support for the underlying backbone infrastructure.
How Do You Implement a Collective Impact Approach?
Before implementation of this approach can begin, the organizations and individuals involved must embrace the logic of collaborative, adaptive, and servant leadership.
- Pay attention to adaptive work, not just technical solutions: The group has to move beyond thinking only about technical solutions, which are best suited for simple and complicated problems, and begin to think about adaptive solutions to problems that require continuous learning.
- Look for silver buckshot instead of the silver bullet: Achieving population-level change, the ultimate goal for collective impact initiatives, requires stakeholders to abandon the search for a single silver-bullet solution. Instead, they must recognize that progress comes from the combination of many interventions.
- Sharing credit is as important as taking credit: Seeking to take direct credit is extremely difficult in large-scale collaborations where change is being created by many participants simultaneously. Organizations should think about their decisions in the context of others and share credit with the group to encourage greater collaboration and cohesion.
PHASES OF A COLLECTIVE IMPACT APPROACH
Collaborative action of this type can generally be categorized by levels of maturity, or phases. Every initiative is unique, however, and should be rooted in the local context and the readiness of stakeholders. Some generalizations about phases:
- Phase 1: Assess Readiness
- Conduct a readiness and landscape assessment – assess the complexity and urgency of the problem, the history of collaboration, existing local collaborations, potential champions, and available resources.
- Phase 2: Initiate Action
- Launch a steering committee.
- Begin community engagement.
- Create baseline landscape and data mapping.
- Review research and lessons from other collaborative efforts.
- Phase 3: Organize for Impact
- Create a common agenda: a clear problem definition, common vision, population-level goal, and basic theory of change.
- Develop a high-level population goal.
- Seek and incorporate community perspectives and input.
- Phase 4: Begin Implementation
- Determine shared measurement and aligned strategies to create mutually reinforcing activities.
- Develop working groups to implement strategies. We’ll talk more about who is on working groups in the next section.
- Select backbone support.
- Introduce the initiative to the broader community and share what you are trying to accomplish.
- Establish the backbone structure that will help sustain the work moving forward.
- Phase 5: Sustain Action and Impact
- Begin implementing strategies and measuring indicators.
- Collect and use data to learn and refine strategies, and identify quick wins.
- Evolve steering committee and working group composition to match adaptive strategies.
- Continue sharing initiative progress and seeking community input.
Who Should Be Engaged By Your Collective Impact Effort?

As we noted earlier in this chapter, one of the common features of collective impact is that it is cross-sector. Complex problems generally require cross-sector coalitions that engage people and organizations beyond the nonprofit sector – or any other single sector.
However, it isn’t just who you bring together, but how you bring them together. The structures that collaborative efforts create enable people to come together regularly to look at data and learn from one another, and to understand what is working and what is not. The main structural components described here are the steering committee, working groups, backbone support, and community engagement.

Steering Committee
Collaborative action often begins with the establishment of an oversight group, usually called a steering committee or executive committee. The key responsibilities of the steering committee are to:
- Provide long-term strategic direction to the initiative.
- Oversee the work of the backbone.
- Determine staff and resource needs to support sustainability, in coordination with the executive team.
- Monitor progress against common-agenda goals and indicators to ensure continued advancement and uncover obstacles.
- Review data and use it to inform changes in stakeholder engagement, working group composition, or strategies.
- Provide guidance to working groups’ efforts.
- Champion the effort broadly in the community.
The composition of the steering committee is vital to the success of the initiative, because its members help set the initiative’s strategic direction. Some important characteristics to consider when selecting steering committee members include:
- Decision-making authority: Members should include people able to influence systems and decisions relevant to the effort.
- Representation: Membership should reflect the geographic area of the effort as well as relevant sectors.
- Influential champions: Members should include people who are trusted or influential among broader groups of stakeholders, who can bring people to the table, help keep them engaged, and champion the strategy with the broader community.
- Content expertise and practitioners: Members should include people familiar with the subject matter who can contribute substantively.
- Passion and urgency: Members should care about the issue and recognize the need for change.
- Focused on the greater interest: Members may represent the needs of their own organizations, but should also be able to think and act in the broader interest of the community.
- Commitment: Members should be willing and able to commit time and energy to attend meetings and get work done.
- Lived experience: Residents and community members with lived experience of the issue being addressed should be included.
Effective steering committees often have two co-chairs from different agencies or organizations; meet at least quarterly, and often monthly at first; have diverse, cross-sector membership and opportunities for shared or rotating leadership; coordinate activity with working groups and other coalitions through backbone leadership and working group chairs; communicate regularly according to agreed-upon schedules and methods; and report processes, findings, and concerns to stakeholders.
Working Groups
Once the strategic action framework is agreed upon, different working groups – also known as action committees – are formed around each of its primary leverage points or strategies. The key responsibilities of the working groups are to:
- Identify effective strategies to support achievement of goals:
- Collect research on effective, evidence-informed strategies.
- Use data to inform identification of strategies.
- Suggest refinement of indicators based on strategy development, as needed.
- Identify funding sources and local agencies to support strategies.
- Community engagement:
- Convene relevant stakeholder dialogues and other forms of community engagement.
- Coordinate communication messages and strategy with other working groups.
- Implementation:
- Coordinate activities among working group member organizations and others in the community to implement strategies.
- Dedicate time to practical tasks such as planning events, identifying volunteers, and carrying out other necessary work.
Effective working groups often have at least two co-chairs from different organizations; meet at least monthly, and sometimes more often at first; include diverse, cross-sector membership and opportunities for shared or rotating leadership; coordinate activity with other working groups through backbone leadership and working group chairs; communicate regularly according to agreed-upon schedules and methods; and report processes, findings, and concerns to the steering committee.
Backbone Support
Backbone support is provided by dedicated, funded staff supporting the collective impact initiative. Backbone support includes six major areas:
- Guide Vision and Strategy:
- Build a common understanding of the problem that needs to be addressed.
- Provide strategic guidance to develop a common agenda and serve as a thought leader and standard bearer for the initiative.
- Support Aligned Activities:
- Help ensure mutually reinforcing activities take place by:
- Coordinating and facilitating partners’ continuous communication and collaboration, and convening partners and key external stakeholders.
- Catalyzing or incubating new initiatives or collaborations.
- Providing technical assistance to build management and administrative capacity, such as coaching, mentoring, training, and fundraising support.
- Creating pathways for new partners to become involved and actively recruiting them.
- Seeking opportunities for alignment with other efforts.
- Help ensure mutually reinforcing activities take place by:
- Establish Shared Measurement Practices:
- Collect, analyze, interpret, and report data.
- Catalyze or develop shared measurement systems.
- Provide technical assistance for building partners’ data capacity.
- Build Public Will:
- Build public will, consensus, and commitment by:
- Framing the problem to create a sense of urgency and articulating a call to action.
- Supporting community-member engagement activities.
- Producing and managing communications, such as news releases and reports.
- Build public will, consensus, and commitment by:
- Advance Policy:
- Advocate for an aligned policy agenda.
- Mobilize Resources:
- Mobilize and align public and private resources to support the initiative’s goals.
It is vitally important that backbone support be viewed as fair and trustworthy by stakeholders on the steering committee and in the wider community. It is just as important, however, to understand what backbone support is not. Backbone staff do not set the agenda for the group, do not drive all the solutions, do not receive all the funding, should not be self-appointed rather than selected through the initiative’s process, and are not simply “business as usual” in terms of staffing, time, and resources. They are a facilitative support team that can help plan, manage, and support the initiative through ongoing facilitation, technology and communications support, data collection and reporting, and the many logistical and administrative details needed for the initiative to function smoothly.
There is no one model of backbone support. The models identified in this section include:
- Funder-Based: One funder initiates a collective impact strategy as planner, financier, and convener.
- New Nonprofit: A new entity is created, often with private funding, to serve as the backbone.
- Existing Nonprofit: An established nonprofit takes the lead in coordinating the strategy.
- Government: A government entity, at the local or state level, helps coordinate the effort.
- Shared Across Multiple Organizations: Multiple organizations share responsibility for supporting and coordinating the work.
Community Engagement

In collaborative action, it is vitally important to include multiple organizations and sectors – business, nonprofit, government, and philanthropy. However, it is equally important to engage the community. Effective community engagement is a critical factor in the long-term success of collective impact initiatives.
When considering community engagement, it is important to use both broad-based community engagement – which seeks to reach a large and varied set of stakeholders within a community, including community members broadly rather than only experts, leaders, or special-interest groups – and targeted community engagement, which seeks to involve a particular group that may otherwise be underrepresented or less likely to participate without a more focused effort.
How the community is engaged depends upon the goals of the initiative and how community members can best participate in achieving those goals. A few ways a community can be engaged, based on thinking from Tamarack Institute, are shown below:
- Understand pressing systemic community challenges
- Begin a process of understanding the issue.
- Clarify questions that arise during the process.
- Co-create solutions
- Spark innovative problem-solving rooted in the lived experience of the community.
- Identify and spread solutions that already exist within the community.
- Verify the direction
- Get feedback on specific strategies and indicators from community members and groups.
- Expand the reach of involvement
- Expand participation in and adoption of initiative strategies.
- Build and sustain the will to take aligned action.
- Build community capacity to lead and sustain change
- Support stakeholders in developing skills for effective collaboration and strategy execution, such as shared measurement.
- Share resources and learning across the community to support the spread of effective practices.
Shared Measurement
Creating and using shared measures is a key component of a rigorous collaborative effort. Shared measurement means identifying a targeted set of indicators that participants agree to pursue, and then using those data both to track progress and to improve efforts over time. This differs from more traditional approaches to evaluation that focus on isolating the impact of a single organization or grant, rather than examining multiple organizations working together to address a common problem.
There are several common challenges to shared measurement:
- Competing priorities among organizations when establishing common measures.
- Differences in organizations’ capacity for data collection and analysis.
- Willingness to invest the time, and sometimes money, needed to develop a shared measurement system.
- The ability to shift from using data primarily to prove performance toward using data to improve the work, which may require overcoming concerns that organizations will be compared negatively.
There are some basic practices that can help address these challenges and support successful shared measurement:
- Effective relationships with funders – Successful implementation of shared measurement requires commitment not only from collaborators, but also from funders. Funding requirements may need to align with the initiative’s shared measures. This calls for leadership, adequate resources, and enough independence for participants to develop appropriate indicators and manage the system.
- Broad and open engagement – The shared measurement design process should include broad engagement, with clear expectations about participation, confidentiality, and transparency.
- Infrastructure for deployment – Infrastructure includes both technological and human capacity. Effective digital tools may be needed, along with ongoing staffing to train people to use the measures, facilitate the shared measurement process, and help ensure data quality.
- Pathways for learning and improvement – The power of shared measurement comes from testing and continuously improving through ongoing feedback. This requires a facilitated process in which participants can share data and results, learn from them, and better coordinate their efforts.
For organizations that choose to embrace shared measurement, potential benefits include:
- Improved data quality.
- Greater alignment across organizations.
- The ability to track progress toward a shared goal.
- More collaborative problem-solving.
- Learning that benefits organizations working on a common problem and supports course corrections that can lead to better results.
Evaluating Collective Impact
Evaluating the overall impact of an initiative is an important part of the process for all parties. Practitioners need timely, high-quality data that support reflection and inform strategic and tactical decision-making. Funders and other supporters need approaches to performance measurement and evaluation that can provide evidence of progress toward the initiative’s goals at different points along the collective impact journey.
The change process typically involves three stages of development, each of which requires a somewhat different approach to performance measurement and evaluation:
The initiative’s early years are typically focused on understanding context and designing and implementing the initiative. This includes establishing the five core conditions of collective impact, as well as coordinating multiple programs, activities, and campaigns according to the initiative’s overarching strategy or theory of change.
- Recommended approach to performance measurement: Partners should agree on a set of early performance indicators to track their progress in establishing key elements of the initiative’s infrastructure.
- Recommended approach to evaluation: Developmental evaluation, aimed at helping partners understand their initiative’s context and learn more about how the initiative is developing.
Evaluating a comprehensive initiative’s context and carefully assessing the quality of its design and implementation in its early years is critically important and should not be dismissed as merely a focus on process. The successful reorganization and alignment of the system of people and organizations addressing a problem can itself be an important outcome of the change process.
The initiative’s middle years are when partners may expect to see meaningful changes in patterns of behavior – such as changes in professional practice or individual behavior – and in the way systems operate, such as changes in cultural norms, funding flows, or public policy. These changes can serve as a gateway to the initiative’s ultimate population-level outcomes and are therefore an important area of focus for both performance measurement and evaluation.
- Recommended approach to performance measurement: Partners should use data from the initiative’s shared measurement system to determine whether, where, and for whom the initiative is making progress.
- Recommended approach to evaluation: Formative evaluation to help partners refine, improve, and fine-tune the work, along with developmental evaluation to explore newer aspects of the initiative.
The initiative’s later years are when collective impact partners may expect to see meaningful, measurable change related to the initiative’s ultimate goals. At this point, the initiative may be ready for a summative evaluation to assess its impact, merit, value, or significance.
In Summary
Collective impact – like other models in Chapter 2 of the Community Tool Box – offers a promising approach to addressing complex social problems at scale.
Contributor
This section was contributed by Jennifer Splansky Juster, Director of the Collective Impact Forum, FSG. Visit the CI Forum.
Resources
Online Resources
Advancing the Practice of Collective Impact from the Collective Impact Forum consists of a previous article by Tom Wolff, on how collective impact can lead to better results particularly for those whom collaborative efforts seek to serve, and a response written from the Forum in order to create a productive conversation.
Aligning Collective Impact Initiatives explores how to align multiple coalitions into a system collective impact initiative.
Bringing Soul to the Work of Collective Impact is an article by Michael McAfee, from the Stanford Social Innovation Review.
Channeling Change: Making Collective Impact Work is a follow-up to FSG's 2011 Stanford Social Innovation Review article. It explores new examples of collective impact initiatives and provides "how to" guidance for those who seek to initiate and lead collective impact initiatives.
Committing to Collective Impact: From Vision to Implementation addresses what happens after the vision is agreed upon and how an infastructure is created that can make progress toward achieving the common agenda.
The Community Engagement Toolkit from the Collective Impact Forum shares a series of tools for planning community engagement to be more purposeful, equitable, transparent, and strategic so that community members are true partners for achieving impact.
Collective Impact is the original FSG article describing collective impact, published in the Winter 2011 Stanford Social Innovation Review. The article highlights how large-scale social change requires broad cross-sector coordination, and explains how substantially greater progress could be made in alleviating many of our most serious and complex social and environmental problems if nonprofits, governments, businesses, and the public were brought together around a common agenda to create collective impact.
Collective Insights on Collective Impact shares cutting-edge thinking from 22 practitioners, funders, community organizers, and thought-leaders.
Download the Collective Impact Readiness Assessment Tool (PDF) from the Collective Impact Forum.
The Collective Impact Table follows a framework that determines what part(s) of collective impact have been achieved and what part(s) still need to be achieved and/or improved.
Essential Mindset Shifts for Collective Impact is part of a compilation of nine new articles about collective impact.
The Guide to Evaluating Collective Impact from the Collective Impact Forum offers practical guidance for planning and implementing evaluations of collective impact initiatives.
How Do You Successfully Put Collective Impact into Action? features the Collective Impact Principles of Practice and originally appeared on the Collective Impact Forum's website.
How Public Policy Can Support Collective Impact provides examples and recommendations of public policies that use funding streams, regulations, reporting and auditing practices, and interdepartmental collaboration to enable communities to apply the collective impact approach to tackling complex social problems.
Interview: Bringing an Anti-Racist Approach to Collective Impact from the Stanford Social Innovation Review. Two collective impact leaders, Zea Malawa of Expecting Justice, and Miya Cain of FSG, discuss using the framework to achieve social change and how to put anti-racism at the center of cross-sector collaborations.
This readiness assessment is designed for a group considering using the collective impact approach to determine if collective impact is the right approach for the social issue, and the extent to which the conditions for success are in place for the initiative to succeed.
Steering Committee and Work Group Roles is a memo that summarizes key responsibilities and was developed through FSG's work with the Health and Wellness Alliance for Children collective impact initiative.
Ten Places Where Collective Impact Gets It Wrong is an article by Tom Wolff in the Global Journal of Community Psychology Practice, where he articulates ten important issues and concerns which Collective Impact fails to adequately acknowledge, understand, and address.
Tools for Working Groups -- this toolkit includes a number of tools for Working Groups as they form, determine strategic direction, develop implementation plans, and identify measurement indicators.
The Value of Backbone Organizations in Collective Impact, originally published as a 4-part blog series on the Stanford Social Innovation Review website, shares FSG's and GCF's experience of working with a cohort of six backbone organizations in Cincinnati to help funders and practitioners understand what it takes to be a backbone and what the value of this necessary, though often behind the scenes, role is in collective impact.
What is Collective Impact? from the Collective Impact Forum.
Print Resources
(2013). Collective Impact Cast Study: Shape Up Summerville. FSG consulting firm.
Collie-Akers, V., Landry, S., Ehule, N.J. et al. Enhancing the Capacity of Local Health Departments to Address Birth Equity: The Institute for Equity in Birth Outcomes. Matern Child Health J 25, 1010–1018 (2021). https://doi.org/10.1007/s10995-021-03135-1
Landry, S., Collie-Akers, V., Foster, K. et al. Assessing the Development of Collective Impact Initiatives Addressing Maternal and Child Health. Matern Child Health J 24, 405–411 (2020). https://doi.org/10.1007/s10995-020-02894-7
Westley, F., Patton, Q.M., & Zimmerman. B. (2006) Getting to Maybe: How the World Is Changed. Toronto: Random House Canada.
Collective Impact – Progress Assessment
Is There a Common Agenda?
_____ Do we have all of the necessary stakeholders at the table?
_____ Does the group have an explicit definition of the problem in agreed-upon language to refer to?
_____ Has the group agreed upon the scope of the landscape it is focusing on? (i.e., Which stakeholders need/do not need to be involved?)
_____ Has the group written a vision and mission statement?
_____ Does the group have agreed upon goals, and measurable targets related to those goals?
Does Backbone Support Exist?
_____ Has a structure for the backbone been clearly decided (e.g., existing organization, new organization, hybrid)?
_____ Is there a funder willing to fund the creation of backbone infrastructure over several years?
_____ Is the backbone actively supporting aligned activities through convening partners, providing technical assistance, and recruiting new partners?
_____ Has the backbone organization begun to build public will with consensus and commitment through communications management, articulating the call to action, and supporting community member engagement activities?
Is a Shared Measurement System in Place?
_____ Is ongoing staffing assigned and funding allocated to develop and implement a shared measurement strategy?
_____ Have we decided what metrics and benchmarks to use to gauge our progress?
_____ Have we established processes to ensure that measurement remains aligned to hold all organizations accountable? Is this data accessible enough so that organizations can easily course-correct?
_____ Have we established a web-based technology tool for bringing shared measurement to scale?
_____ Is that web-based tool easily accessible to stakeholders, customizable, and inexpensive?
_____ Are stakeholders sharing results and learning from each other using the tools and processes we’ve created?
Have Mutually Reinforcing Activities Been Established?
_____ Is there an up-to-date map of the players, strategies and work underway?
_____ Is it clear who is responsible for the different strategic elements of the initiative?
_____ Has overlap and redundancy between organizations been identified and minimized?
_____ Have sub-groups been established by locality and type of activity?
_____ Has a list of prioritized activities and next steps been written so that the different groups are coordinated around common agenda?
Is There Continuous Communication?
_____ Have meeting schedules been established for activity-focused sub-groups? Will these meetings occur yearly? Monthly? Weekly?
_____ Have meeting schedules been established for community-focused sub-groups? Will these meetings occur yearly? Monthly? Weekly?
_____ Have vertical and horizontal reporting processes been established? (i.e., How will sub-groups report out to the steering committee? How will groups report to each other?)
_____ Have decision-making processes been established?
Collective Impact – Readiness Assessment
Use the following gauges to determine “readiness” for Collective Impact by identifying which preconditions the group is well prepared for or will need further investment in:
Progress Gauges:
Significant Investment Needed – The group does not currently have these elements/processes in place. There is an incomplete or unclear plan to accomplish this goal and/or significant time and resources will need to be allocated to either begin or complete this process.
Some Investment Needed – While these elements/processes are not fully in place, significant thought and planning has gone into these elements. Time and resources have been allocated and clear progress is being made.
Current Situation Strong – These elements/processes are either fully in place or sufficient progress has been made in them so that they are operationally functional in the context of the initiative.
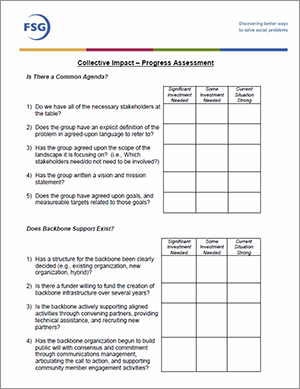
Example #1: Early Wins in Early Childhood - A Case Study in Seeding Systems Change

Southeast Virginia has long been home to numerous early care and education programs. However, operating traditionally in silos, these programs were not seeing the results they desired.
In 2016, Hampton Roads Community Foundation initiated a region-wide process involving nearly 100 stakeholders to scope and plan Minus 9 to 5, an initiative designed to unite previously disparate programs and people together for greater impact through systems change. This case study details the opportunities, highlights, and lessons learned in the first two years of the initiative. Read more from FSG Reimagining Social Change.
Example #2: Collective impact in different fields or domains:
In education
In public health
- Shape Up Somerville
- LiveWell Colorado
- Global Alliance to Improve Nutrition (GAIN)
- Tackling Youth Substance Use
In addressing homelessness
In youth development
In economic/urban development
In community development
In addressing environmental issues
Example #3: How collective impact is being used to solve homelessness:

The Collective Impact Forum's September 18th, 2023 podcast covers how complex issues such as homelessness can feel unsolvable or intractable, but that through a commitment to a collective approach and strategies, communities can end homelessness.
Speaking with Community Solutions' (a nonprofit that is dedicated to ending homelessness) president Rosanne Haggerty, the program Built for Zero is discussed, which is a program network of more than 100 cities and counties working to ensure that homelessness can be rare or brief in their regions.
The Institute of Medicine (IOM), now known as the National Academy of Medicine, developed a framework for thinking about community health improvement. Suppose you mount a community effort to address an important local issue – let’s say domestic violence. You put together a group to spearhead your effort, study the issue in the community, and come up with a plan.
You realize that domestic violence has many dimensions. It’s not simply an isolated incident in which someone loses their temper, but can be part of a recurring pattern of abuse and control. In addition, domestic violence can intersect with issues such as substance use, unemployment and other economic circumstances, and social attitudes that tolerate or minimize abuse.
So your group sets out to address the different aspects of the problem. Police may need training, and they and the courts may need to examine how they respond to domestic violence. Safe shelter and other forms of support have to be available for survivors and family members at risk. Survivors, children or others who witness abuse, and people who use abuse may need appropriate forms of counseling, support, or intervention. Substance use may also need to be addressed and treated when it is present. In addition, attention may have to be paid to job training and the overall economic circumstances of the community. Finally, there may need to be a public education campaign to reinforce that domestic violence is not a normal or acceptable part of a relationship.
Each element of your plan requires an action, and each action requires someone to carry it out. Furthermore, you’ll need someone or some group in the coalition to coordinate and oversee the whole process. A complex plan won’t work unless everyone does what is expected. That’s a major concern of the IOM framework. It treats accountability as an important part of community health and development planning, and as a crucial ingredient in creating a healthy community.
This section will describe CHIP (Community Health Improvement Process), the IOM model, which is similar to others in this chapter in many ways – it’s participatory; takes a community perspective; embodies a broad view of health; calls for community assessment, strategic planning, and evaluation in intervention, etc. – but features an accountability component. The IOM framework emphasizes performance monitoring – starting with a clear statement of everyone’s responsibilities, and then checking regularly, using measurable indicators of performance, to make sure those responsibilities have been carried out and have been effective. This can make the difference between success and failure in a drive to build a healthy community.
What is a CHIP?
CHIP is a framework for a process for building community health. As explained above, it has a performance monitoring element built in. It is specific about process – the way you go about creating a community health effort – but not about content – the issues you might tackle or the methods you might use to tackle them. Content is left up to individual communities.
You could read the words “Community Health Improvement” in two ways: (1) the improvement of the overall physical health of the individuals who make up a community; or (2) the improvement of the health of the community itself. IOM largely concerned itself with the first possibility, but we’ll concentrate on the second, in keeping with the fact that the Community Tool Box is concerned with all aspects of community functioning. Striving for a healthy community, instead of community health, doesn’t change the CHIP framework at all, but gives us the leeway to address various aspects of community life, rather than health alone.
The diagram below describes the CHIP model using graphics. The text that follows explains the components of the model and how they relate to one another.

From J.S. Durch, L.A. Bailey, and M.A. Stoto, eds. Improving Health in the Community, Washington, DC: National Academy Press, 1997.
As the model diagram shows, a CHIP has two cycles – cycles because each is seen as a sequence that can and should be repeated over the course of time. A cycle can be initiated in any of its phases, although the implication of the diagram seems to be that there is a “most logical” sequence that most communities will use, and that we’ll use here.
The problem identification and prioritization cycle
In this cycle, you start with an area of concern – health in the original IOM conception, but as we’ve discussed, it could just as easily be the overall quality of community life – assess the situation, identify areas that the community needs to work on, and decide where you’ll put your energies.
- Form a community coalition to address community health/quality of life. There has to be some coordinating body for such an effort. A coalition satisfies the demands of the IOM model for inclusiveness and broad participation. It implies a relationship of equals working toward a common goal, and makes it easier to bring people and organizations together than would a more hierarchical structure.
- Prepare and analyze community profiles. This is the process of examining the various factors that could influence community well-being. Looking at the results of your analysis should highlight the areas that most need to be addressed. IOM suggests five areas to examine:
- Sociodemographics. Age, geographic distribution, race/ethnicity, income, employment, housing, etc.
- Status of the issue. The frequency and seriousness of issues in the community, whom they affect, related issues, and their effects and frequency. Frequency and seriousness are both important. A very common but relatively less serious condition may be a matter of concern, for instance, but so may a less common condition that has far more severe consequences.
- Risk and protective factors. The factors already existing in the community that make people more or less likely to be affected by particular issues. Easy access to tobacco products among young people, for example, could be a risk factor for later tobacco-related illness; strong smoke-free policies in public spaces could be a protective factor.
- Resource consumption on issues. The community resources – services, funding, etc. – already devoted to particular issues.
- How people view the issues with respect to themselves. To what extent do they report being affected by them? If people don’t see an issue as a problem that affects them in some way, or as something important, it can be difficult to involve the community in action on that issue.
- This profile will help you decide what issues to work on, and will be useful to the community in examining itself in many ways, and in continuing the work of the CHIP after the initial effort has been completed.
- Identify the critical issues (the problem). What are the most critical needs in the community? What issues motivate – or could motivate – community members to work on them? What does the community have the resources to do? On what issues can you actually make a difference? These are the questions to ask in deciding what issues you’ll address.
The “problem” here is assumed to be an aspect of a larger concern – specifically health, in the original IOM conception. It may be an actual specific problem – pregnancies among adolescents, homelessness, tuberculosis, violence, students leaving school before graduation – but could also be a community asset that needs to be developed – youth leadership, an empty historic building – or the creation of something new that contributes to the health and well-being of the community – a community arts center, a well-baby program.
- Once you’ve identified the issues you plan to work on, you move on to the next cycle, that of analysis and implementation. The diagram above describes the second cycle of the process for one issue. If the CHIP has identified and means to address several issues – domestic violence, gang activity, and child sexual abuse, for example – then it will go through an analysis and implementation cycle for each of them.
The analysis and implementation cycle
Here, you work out both a long-term strategy and an action plan to effectively address the issue at hand, agree on responsibility for each element of the plan, put it into effect, and then monitor your results to determine whether everything is working properly and whether all partners are fulfilling their responsibilities.
- Analyze the issue. Using the information it has gathered, its knowledge of the community, reports of effective and promising practices, and the available research, the coalition analyzes the issue. IOM’s model, like PRECEDE/PROCEED, Healthy Communities, and others, emphasizes that both individual and community health are influenced by a combination of social and physical environments, individual biology and genetics, and economic and political conditions. Thus, the natural environment, economic inequality, the racial and ethnic composition and experiences of the community, the employment situation, and the attitudes of those in power toward the role of government may all have a profound effect on a particular issue or on the general quality of community life.
- The goal here is to understand the particular factors that cause or contribute to the issue you’re concerned with, how they play out in the community, and how they can best be approached. You should be careful to consider all possible factors, not just those that are obviously related to the issue.
- Inventory your resources. What do the coalition and the community have available to address issues?
- Local assets. Organizations and institutions, local foundations and other funders, expertise, current services, etc.
- Protective factors within the community. Family, social, and faith networks; community norms and values; physical environment; community activities; etc.
- Human resources. “Natural helpers,” academic researchers, people with connections to particular groups in the community, and people with skills in relevant areas.
- Resources from outside the community. National and statewide public and private funding sources, for instance, or sources of technical assistance.
- Develop a strategy. Understanding the issue and having a clear sense of available resources will help you come up not only with a short-term plan for addressing the specific issue you’re currently focusing on, but also with a strategy for promoting and maintaining community well-being over the long term. Your strategy should be geared to your community, and should be arrived at through an inclusive, participatory process.
- Identify accountability. Your coalition or partnership – with the input and collaboration of those who will be carrying out the plan, who ideally will already be involved – determines who will be responsible for which elements of the plan. You should identify who will oversee each part of the process, who is responsible for carrying out the actual work of a particular intervention or piece of an intervention, who will evaluate and provide feedback, etc. There are some important considerations as you agree on accountability:
- It should be realistic. Before individuals or groups take on responsibility for a part of the process, you should make sure that they have the resources, capacity, and support to accomplish what they’re attempting. To assign accountability to someone who can’t succeed is both unfair and counterproductive.
- It should be voluntary. If accountability is to mean anything – and if it is to lead to results – it must be taken on willingly. Individuals or groups that accept accountability for an element of the strategy are also agreeing to think carefully about what they do, to be willing to change course if their efforts aren’t working or if community needs change, to accept constructive criticism without defensiveness, and to see themselves as integral parts of a larger effort. If they accept accountability under pressure, or disagree with the accountability process, they’re unlikely to agree to any of that, and their supposed accountability won’t make much difference.
- It should involve clear and observable responsibilities. Both the accountable individuals or organizations and the coalition should understand exactly what they’re agreeing to, and how they’ll determine whether and how responsibilities have been met. Clarity makes performance itself and its monitoring easier, confirms that you’re operating with a coherent and understandable plan, and – because everyone knows exactly what they’re supposed to do – increases the chances of success.
No matter how carefully you plan, you can’t anticipate everything that might or will happen, and you should expect surprises. If you plan carefully, however, and try to be as clear as possible, there will be fewer of them, and they’ll breed less bad feeling among those who find themselves surprised. As long as everyone agrees at the beginning that the responsibilities they’re taking on are reasonable and achievable, unexpected events and circumstances can be weathered.
- Develop a set of performance indicators in order to be able to monitor the process, outcomes, and performance. Accountability should be measurable, and should be based on what needs to be accomplished. Its point is not to single out or punish those who don’t reach their intended goals, but rather to:
- Help those who are having difficulty improve their performance. This might be through better support, redefining goals, changing methods or techniques, changing staffing arrangements, focusing on a different group of participants, changing to a more realistic timeline – whatever it takes to make sure that what they do has the desired effect.
- Identify problems in the system. It may be that performance is ineffective because the assumptions behind it are inaccurate, or because you understood the issue in the wrong way to begin with. Performance problems can often shed light, not on the failures of those responsible, but on the inadequacy of the system within which they are working.
- Help everyone learn and improve both action plans and the overall strategy.
IOM specifically suggests that indicators should be quantitative – i.e., tied to numbers, such as the number of people served or the average time participants spend in a program – but there are other ways to assure that accountability is measurable. Qualitative measures such as observation, participants’ own reports, and community impressions may also provide accurate and important information relating to accountability. Numbers don’t always tell the whole story.
The point of accountability here is not to make it easier to assign blame if something doesn’t get done or go as planned. Rather, it is to make it possible to improve your strategy and actions so that they become more effective. If there’s a failure in the system, clear accountability enables you to figure out where it happened and why. Then you can take action to correct it, whether that’s providing better support to whoever is responsible or rethinking your strategy entirely.
- Implement your strategy. Do whatever you’ve decided is necessary – intervention, program, community education initiative, etc.
- Monitor the process and outcomes. As with other models (PRECEDE/PROCEED, for example), the concern here is both with process and outcomes.
- Process: Did you do what you set out to do (e.g., deliver a specific service to a specific number of people in a specified time frame)? If not, why not?
- Outcomes: What effect did your actions have? Was it the desired effect, or at least positive? If not, why not?
If the process broke down, or the outcomes weren’t satisfactory, you should be able to analyze the situation and pinpoint what went wrong and how by using the performance indicators that you developed earlier in the cycle. Then you can choose from a number of possible courses of action to correct mistakes or misconceptions, strengthen the performance of an organization that wasn’t able to accomplish what it expected to, etc. Among the possibilities:
- Change your strategy or action plan.
- Shift responsibility elsewhere.
- Provide more support and/or resources to those accountable.
- Eliminate a particular action or element of strategy.
- Start the cycle again, with another issue or group of issues. What you’ve done so far may have resolved some issues, or may only have made clear how complex they are. Whatever the result, you’re not done: the ultimate aim here is long-term, fundamental change that improves life in the community. Whether you’re moving up to a larger concern, or merely addressing a different issue, there will always be a next step in the process.
Why use a CHIP?
Why would you employ the CHIP model as opposed to another? There are a number of reasons why this model might be a good one for many communities.
- It takes a community perspective. CHIP asks you to consider the whole community when you address an issue. That broad perspective is more likely to encompass the factors contributing to an issue – and potential ways to address it.
- It’s inclusive and participatory. The CHIP model not only considers but involves the whole community in generating strategy and carrying it out. That means that a wide range of opinions, viewpoints, and ideas can go into a strategy, and that the community can develop ownership of the eventual effort. Community ownership, in turn, can strengthen community support and willingness to work for the effort and see it through.
- It demands a comprehensive view of health. Again, like many of the other models in this chapter, CHIP sees health as more than the absence of disease or a chronic condition. Community health includes social, economic, political, ecological, and other dimensions. (The Evans and Stoddart field model illustrated earlier provides an example of this comprehensive view.) This perspective allows you to consider the range of community factors that may need to be addressed when working to improve health and well-being.
- It sees equity as a key. Equity – the condition in which everyone in a community has access to what they need for a decent quality of life – is an important factor in both individual and community health. Fostering equity is crucial to the creation of a healthy community and to the establishment of social justice in a community or society.
- It’s flexible. The model leaves the community to determine the structure and content of its strategic and action plans, based on its own analysis and knowledge of its own needs.
- It builds in accountability. As discussed above, that makes it possible to structure an effort clearly and identify gaps as they appear.
- It builds in performance monitoring. Not only does performance monitoring make accountability a reality, but it allows focused course correction as it identifies problem areas in strategy or in the implementation of an effort.
- It can incorporate or fit in with other models. CHIP can be used as the framework for a healthy community effort, for instance. Its flexibility in form and content makes it adaptable to a wide range of circumstances.
- It sees the process as ongoing and long-term. Real change is not a one-shot affair. It takes place over time, and as a result of constant, steady effort. CHIP recognizes that, and its cyclical model is one that is meant to be used over the long term.
Perhaps the model’s biggest drawback from the point of view of the Community Tool Box is that, while it advocates inclusiveness and participatory planning, the original IOM formulation has a largely top-down structure. It assumes that the initial planning and spearheading of the effort may be done by professionals or institutional leaders – public health officials, health administrators, legislators, etc. Although others are invited to join, the group that does the inviting may already have formed and developed ideas about how things should proceed. This is different from gathering a large number of participants from diverse backgrounds at the very beginning and working out together where to start and how to proceed.
Who should be part of a CHIP?
A CHIP should involve all stakeholders, i.e., those who are in any way affected by or involved in a community health or development effort. These include:
- Those who are directly affected by the issue at hand. They may, for example, include people who have used or survived violence, people affected by a particular disease or physical condition, people experiencing unemployment because of community economic circumstances, people experiencing homelessness, etc.
- Those whose lives or jobs will be affected by the CHIP effort. In addition to those at whom any intervention or program is directly aimed, this group includes anyone who is involved in carrying out the effort – health and human service staff, police, teachers, etc. – and anyone who is indirectly affected – landlords, property owners, public agencies, employers, etc.
- Change agents. Those with the power or authority to help create change: public officials, lawmakers, potential funders, and opinion leaders.
- Influential people. Business leaders, clergy and other faith leaders, leaders of various groups, and other respected community members.
- Community members broadly. Since the process demands commitment by and accountability to the community, it makes sense to involve community members in it.
How do you implement a CHIP?
IOM guidelines
As we’ve discussed, the CHIP model, by design, offers no specific methods or techniques, so that a community can design a strategy that fits its needs. IOM did, however, recommend some basic guidelines for successfully implementing a CHIP.
The following is from J.S. Durch, L.A. Bailey, and M.A. Stoto, eds., Improving Health in the Community. Washington, DC: National Academy Press, 1997.
- Communities should base a health improvement process on a broad definition of health and a comprehensive conceptual model of how health is produced within the community.
- A CHIP should develop its own set of specific, quantitative [i.e., number-based] performance measures, linking accountable entities to the performance of specific activities expected to lead to the production of desired health outcomes in the community.
- A CHIP should seek a balance between strategic opportunities for long-term health improvement and goals that are achievable in the short term.
- Community coalitions guiding CHIPs should strive for strategic inclusiveness, incorporating individuals, groups, and organizations that have an interest in health outcomes, can take actions necessary to improve community health, or can contribute data and analytic capabilities necessary for performance monitoring.
- A CHIP should be centered in a community health coalition or similar entity.
- State and local public health agencies should assure that a community health improvement process is in place in all communities. These agencies should at a minimum participate in CHIP activities, and, in some communities, should provide its leadership and/or organizational home.
- In support of community-level health improvement processes, state health agencies, in cooperation and collaboration with local health departments, should assure the availability of community-level data needed for health profiles.
- States and the federal government, through health departments or other appropriate channels, should require that health plans, indemnity insurers, and other private entities report standard data on the characteristics and health status of their enrolled populations, on services provided, and on outcomes of those services, as necessary for performance monitoring in the community health improvement process.
The last four of these guidelines demonstrate the top-down nature of the original IOM concept, and the last may seem to conflict with the voluntary nature of accountability discussed earlier. If yours is a grassroots or community-generated effort, an inclusive coalition – either one that already exists, or one that forms to address community needs – could provide collaborative leadership for a CHIP-type process. Data, both for community assessments and performance monitoring, can be gathered by participants from online sources, organizational and community records, and other public documents, without requiring the process to be led by a government agency. In other words, a community-change process modeled on CHIP could be conducted collaboratively by the community, rather than under the oversight and leadership of a public health or similar agency.
Steps those guidelines imply for implementing a CHIP
- Assemble a broad-based, inclusive, participatory coalition or coordinating council to guide the CHIP process, if one does not already exist.
- Do your research. Depending on the circumstances, that research will probably include examination of some or all of the following:
- Census data, for demographic information.
- Information on the issue(s) in the community. Some of this may be available from census data, some from public records of various sorts, some from the records of community-based and other nonprofit organizations, some from interviews and surveys of the community, some from academic or other studies, etc. It should include the interaction of demographic information and the issue(s). What’s the relationship of race, for instance, or gender to the frequency or experience of the issue? Is it experienced differently by older and younger people, or by people in specific geographic areas? Is it evenly spread throughout the community? Is it related to employment, economic status, education, genetics, living conditions, etc.?
- Community attitudes about the issue(s). You’ll learn about these from a community survey, from group or individual interviews, from focus groups, and/or from reliable community informants – people in the community whom you trust to give you an accurate reading of what you’re looking for.
- The trends and realities of the issue(s). Are things getting better or worse? How do particular issues affect the lives of real people? How are the details of the issue changing or likely to change in the foreseeable future? Much of this information may come from organizations that work directly on the issue and, importantly, from people directly affected by it.
- The theories and formal research results of those who have studied the issue(s) – commonly called “the literature,” meaning the information that’s been published about the issues.
- Identify the issue(s) you’re going to work on, if you haven’t started with a specific issue in mind.
- Analyze the issue(s) carefully. That means looking at their possible root causes, the consequences – intended and unintended – of addressing and not addressing them, how they might be approached, etc. In order to conduct an accurate analysis, you’ll need to consider the range of factors that influence health and other community issues:
- The social determinants of health. In the framework presented here, these are discussed broadly in terms of socioeconomic equity, social connectedness, and sense of personal efficacy.
- The nine factors – subsets of the broader social determinants listed above – identified in the Ottawa Charter and discussed in relation to the Healthy Communities movement: peace, shelter, food, education, income, a stable ecosystem, sustainable resources, social justice, and equity.
- Factors that are relatively fixed or difficult to change: genetics, geography, demographic patterns, population patterns, etc.
An understanding of these factors and their interactions with one another and with the issue as it plays out in the community will help you carry out your analysis, and will also shed light on another important consideration: Are you in fact addressing the right issue(s) to create the changes you’re aiming for? It’s sometimes the case that an issue that seems self-contained is in fact a small part of a larger issue. That may mean that you won’t resolve your issue without tackling the larger one.
In doing an analysis of this sort, it’s often helpful to remember the story of the blind men and the elephant. Several blind men are introduced to an elephant and asked to describe it. The one who grasps the elephant’s trunk exclaims that the elephant is like a snake. Another feels its leg and says that the elephant is like a tree. The man at the elephant’s tail says the animal is like a rope. And the one who feels its side says the elephant is like a wall. All of their analyses are correct as far as they go...but none of them go far enough. Make sure that you go beyond your first impression: don’t assume you’ve seen all there is to see about the issue.
- Take stock of potential resources, particularly those already available in the community. There are really three courses of action you should be taking here:
- Start with a positive, proactive stance, and assume that the community already possesses many of the resources necessary to address its own issues and improve its quality of life. Then find and enlist the community assets – people, organizations and institutions, funding, etc. – that can contribute to your effort.
- Decide whether more resources will be needed, and strategize about how – and from where – to get them.
- Approach potential funders and invite them into your CHIP process as participants, if you haven’t already.
- Develop a strategic plan and action plans to carry it out. The strategic plan should be devised by a group representing all sectors of the community, so that it will both respond to the realities of the community situation and be seen as belonging to the community.
There are really two plans needed:
- A long-term strategic plan to address systemic change in the community. Carrying out this plan can contribute not only to lasting progress on your issue, but to broader improvement in the well-being of the community. At the same time, it may cover a decade or more, which is a long time for people to wait for results.
- Shorter-term strategic goals that allow for some reasonably quick success. These are necessary not only to address immediate problems, but to keep people enthusiastic about the long term and to benchmark your progress toward your eventual outcomes.
This is where the IOM guideline about striking a balance between long-term and short-term achievable goals becomes relevant.
- Agree on who will be accountable for which parts of the plan. As discussed above, accountability should be voluntary, involve realistic expectations, and be based on clearly defined and observable responsibilities.
Accountability doesn’t always mean that those accountable are responsible for personally doing what needs to be done, but rather that they are responsible for seeing that it gets done. Thus, an organization may take on accountability for something not in its area of expertise with the understanding that it will find and recruit the appropriate provider or practitioner to see that it gets done.
- Work out how accountability will be monitored. Here’s where you develop performance indicators to monitor the process and outcomes of your effort, and to see whether everyone did what they agreed to and accomplished what they expected to. While the original IOM framework emphasizes quantitative measures, it can also be informative to use qualitative measures. Observation, participant self-reports, and other qualitative information may reveal important aspects of performance or outcomes that numbers alone may not capture.
- Implement your strategy. By this point, you should have both a long-term strategy and an immediate action plan. It’s the action plan – or the first of your action plans, depending on what your overall strategy looks like – you’ll start out with, and it should include clear goals, a process, a clear statement of who’s accountable for what, and ways of measuring both performance and the success of your plan.
- Monitor both the process and the outcomes of your effort. Monitoring has two purposes: to make sure everyone is doing what they’ve agreed to do and that it’s working – performance monitoring – and to see whether your overall plan is effective – outcome monitoring.
The point of performance monitoring, as mentioned earlier, is not to find someone to blame for not doing their job, but rather to find weak points in the system and strengthen them. If an organization, for instance, isn’t able to play its part in the process, it may need more resources, technical assistance, or some other support. If the process is going as planned – everyone is doing what they’re supposed to do – and there are still no results, then the group may need to change methods or address another facet of the issue.
Performance monitoring will tell you what you need to know about accountability and about whether the process is working. Outcome monitoring will tell you whether you need to adjust and refine – or rethink – your strategy and action plans. You may have misunderstood the needs or attitudes of the community, relied on techniques that simply don’t work in that situation, or failed to respond to a change in circumstances. Whatever the issue, if there’s no evidence of your hoped-for outcomes, it’s time to alter your approach.
Even if things are going well, there’s always room for improvement. Monitoring may also show you ways that you can tweak your effort to make things work better: improved communication and coordination, for instance, or increased concentration on a particular area might make success quicker and easier for everyone.
- Maintain your gains. No matter how successful an action plan is, it won’t amount to much if its successes aren’t maintained. The job isn’t over once progress has been made on an issue – that progress has to be sustained, and that takes ongoing effort. Once you’ve accomplished something, you have to continue paying attention to it even as you tackle the next task.
Maintenance is best accomplished through system change. The ideal solution is to put a new system in place, or change the community climate so a new behavior or condition is more likely to be sustained. If that’s not possible – and it may not be, especially early in a long-term effort – then you simply have to keep paying attention to it, or you may lose what you’ve gained.
- Start the cycle again, with another issue. As we made clear at the beginning of this section, a CHIP isn’t a one-shot deal. It’s meant to be an ongoing, long-term effort to change the community in fundamental ways. The cycles continue, tackling different issues, changing systems, and working to improve well-being and the quality of life for everyone in the community.
In Summary
The Institute of Medicine’s Community Health Improvement Process (CHIP) is a framework for promoting community health that may also be used as a model for creating healthy communities. It is similar to many of the other models in this chapter in that it takes a comprehensive, community-based view of health and calls for an inclusive, participatory, community-based coalition or coordinating group. In the first cycle of the two-cycle process, that group assesses and analyzes the community to identify critical issues that affect the health of the community as a whole.
In the second cycle – a cycle repeated for each issue that the CHIP addresses – the coordinating group analyzes the issue, inventories the resources available to address it, develops long-term and short-term strategies, identifies accountability for carrying out the strategic plan, develops measurable indicators for monitoring both the performance of those accountable and the plan’s overall success, implements the strategy, monitors its process and outcomes, makes whatever adjustments and changes are necessary, and then repeats the cycle with the same or another issue.
A CHIP has a number of advantages. It takes a community-based and comprehensive perspective on health, allowing it to consider factors that contribute to or create barriers to building a healthy community. It’s inclusive and participatory, and sees equity as a key factor in community health, thus involving and paying attention to a broad range of voices and interests in the community. It’s flexible, encouraging communities to create solutions that reflect their own needs and circumstances. It builds in accountability and monitors performance so that responsibilities and gaps can be identified. It can incorporate or fit in with other models. And perhaps most important, it sees the process as ongoing and long-term, one that aims to change systems and attitudes in the community in fundamental ways.
A CHIP’s biggest drawback from the point of view of the Community Tool Box is that, although it incorporates people from many sectors, the original model gives public health professionals and institutions a prominent role in initiating and leading the process. A community doesn’t necessarily have to accept that particular aspect of the model, however, and can establish a more collaborative process. Indeed, a CHIP should involve all stakeholders, from those most affected by the issues, to those who will be indirectly affected by an intervention, to those who influence policy or other community decisions, to community members who are involved simply out of concern for the public good.
Implementing a CHIP is different for each community, but the original IOM framework provides some guidelines:
- Communities should base a health improvement process on a broad definition of health and a comprehensive conceptual model of how health is produced within the community.
- A CHIP should develop its own set of specific, quantitative performance measures, linking accountable entities to the performance of specific activities expected to lead to desired health outcomes in the community.
- A CHIP should seek a balance between strategic opportunities for long-term health improvement and goals that are achievable in the short term.
- Community coalitions guiding CHIPs should strive for strategic inclusiveness, incorporating individuals, groups, and organizations that are stakeholders or can contribute to the process.
- A CHIP should be centered in a community health coalition or similar entity.
- State and local public health agencies should help ensure that community health improvement processes are available to communities.
- State health agencies, in cooperation and collaboration with local health departments, should help ensure the availability of community-level data needed for health profiles.
- The original IOM framework also calls for appropriate public and private entities to make relevant standardized data available to support community health improvement and performance monitoring.
In addition, using the CHIP model, the steps to implementation might be:
- Assemble a broad-based, inclusive, participatory coalition or coordinating council to guide the CHIP process, if one does not already exist.
- Do your research.
- Identify the issue(s) you’re going to work on, if you haven’t started with a specific issue in mind.
- Analyze the issue(s) carefully.
- Take stock of potential resources, particularly those already available in the community.
- Develop a strategic plan and action plans to carry it out.
- Agree on who will be accountable for which parts of the plan.
- Work out how accountability will be monitored.
- Implement your strategy.
- Monitor both the process and the outcomes of your effort.
- Maintain your gains.
- Start the cycle again, with another issue.
Resources
Online Resources
CHIP Index Page
Wisconsin Department of Health Services provides examples of local CHIP plans.
CHIP Action Planning Model
Simple graphic outline of CHIP process from the University of Calgary, Canada.
Douglas County Community Health Improvement Partnership
Douglas County, Kansas CHIP home page.
Healthy Montgomery - Montgomery County CHIP
Outline of the CHIP plan for Montgomery County, Maryland.
The Institute of Medicine
The homepage for the Institute of Medicine.
Oconto County Community Health Improvement Process - General Information
Oconto County CHIP home page, briefly describing the process and including links to the county plan and the statistics it was based on.
Washington state Department of Health on CHIP.
A guide for preparing for and defending CHIP.
Print Resource
Durch, J. S., Bailey,A.L., & Stoto, A. M. (1997) eds. The Committee on Using Performance Monitoring to Improve Community Health. Improving Health in the Community: A Role for Performance Monitoring. Washington, DC: National Academy Press.
What is a CHIP?
___A CHIP is a Community Health Improvement Process that can also be used for building a healthy community.
___CHIP is slightly different from other similar processes in that it incorporates accountability into the planning, implementation, and evaluation of the community health efforts it fosters.
Why use a CHIP?
___It takes a community perspective.
___It’s inclusive and participatory.
___It demands a comprehensive view of health.
___It sees equity as key.
___It’s flexible.
___It builds in accountability.
___It builds in performance monitoring.
___It can incorporate or fit in with other models.
___It sees the process as ongoing and long-term.
Who should be part of a CHIP?
___Those who are directly affected by the issue at hand.
___Those whose lives or jobs will be affected by the CHIP effort.
___Change agents.
___Influential people.
___Community members at large.
How do you implement a CHIP?
___Incorporate IOM’s general guidelines.
- Define health broadly.
- Develop specific quantitative measures and hold responsible groups accountable to them.
- Balance long- and short-term goals.
- Include all stakeholders and other potential contributors to the work in assessment, planning, and implementation.
- A CHIP should be centered in a community health coalition or similar entity.
- State and local public health agencies should assure that a community health improvement process is in place in all communities.
- State health agencies, in cooperation and collaboration with local health departments, should assure the availability of community-level data needed for health profiles.
- States and the federal government should require that appropriate private entities report standard data on their enrolled populations, to facilitate the CHIP.
___Form an inclusive, participatory coalition or coordinating group, or tie into one that already exists.
___Do your research.
___Identify the issue(s) you’re going to work on.
___Analyze the issue(s) carefully.
___Take stock of potential resources, particularly those already available in the community.
___Develop a strategic plan and action plans to carry it out.
___Agree on who will be accountable for which parts of the plan.
___Work out how accountability will be monitored.
___Implement your strategy.
___Monitor both the process and the outcomes of your effort.
___Maintain your gains.
___Start the cycle again, with another issue.
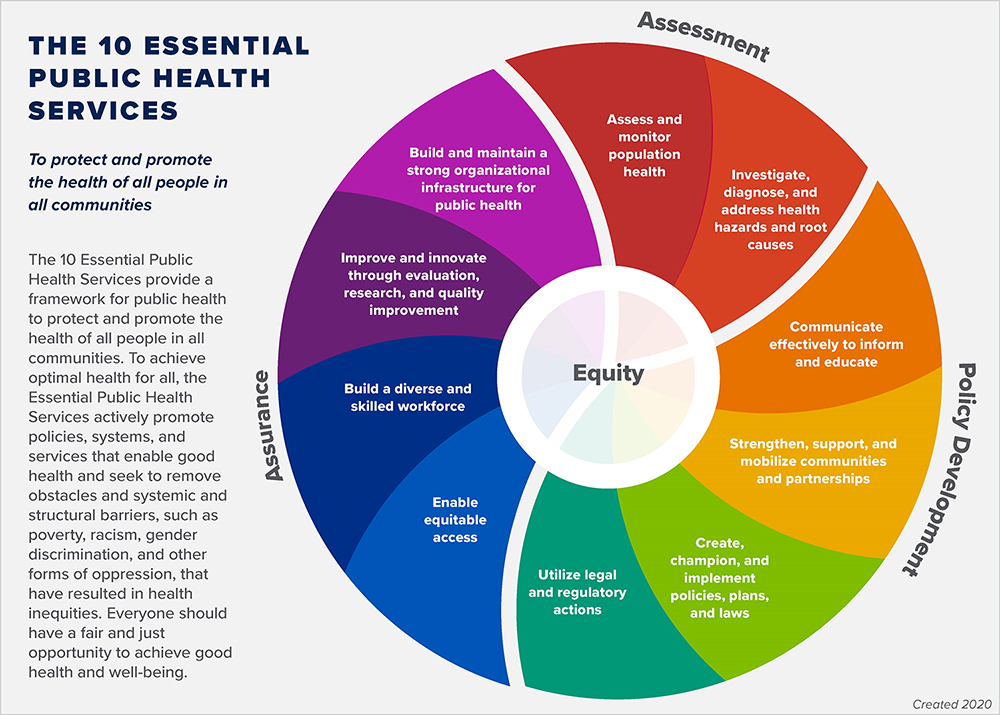
Note: The Ten Essential Public Health Services framework was revised in 2020. The text below reflects the revised framework and terminology.
Before you read this section's information about the Ten Essential Services, we invite you to take a quiz. Answers are provided at the bottom of this page. See how well YOU do!
As you read the front page of the local news, you notice an alarming article about an outbreak of “disease X” in your community. You read on to learn about the scientifically established cause of “disease X” and precautionary measures for avoiding exposure.
This valuable information was published prominently because:
- The local football team lost its game last night
- The front-page columnist is on vacation
- State and local health officials and their staff have worked to gather data, conduct laboratory and statistical tests, develop and test hypotheses, and collaborate with the media to alert and educate the public about “disease X” as effectively as possible.
On your way into the local grocery store, you notice a flier advertising a toll-free number or website for enrolling eligible uninsured children in a publicly funded health insurance program.
This insurance program and its outreach efforts exist because:
- The federal government has a budget surplus and is looking for a way to spend it
- A telephone company offered the state health department a great deal on toll-free numbers
- Public health professionals have documented gaps in health coverage and worked with federal and state policymakers and community partners to improve outreach and access to health coverage and care.
While shopping in the local mall, you come across a group of nurses offering free blood pressure and cholesterol screenings.
The nurses are offering these screenings because:
- They need to moonlight
- They enjoy people watching at the mall
- They are public health nurses dedicated to community health promotion, including the prevention of heart disease
You and your sweetheart share a romantic dinner at your favorite restaurant. Not only is the meal delicious – you do not get food poisoning!
This enjoyable experience has been brought to you by:
- The restaurant management
- Your local health department
- A joint effort of the restaurant management and your local health department
In an urban area, some liquor stores are gradually being replaced by grocery stores. The public transit system has been rerouted to improve store access for residents without vehicles.
This change in the community’s planning and development is probably a result of:
- The Department of Transportation needing to increase revenue
- The liquor store owners deciding that they weren’t doing enough business and moving elsewhere
- A collaborative effort of community members, public health professionals, city planners, and local government officials working toward shared goals for community health and well-being
Answers: 1. c; 2. c; 3. c; 4. c; 5. c
What, besides the same answer, do the quiz scenarios above have in common? They are real-life, everyday examples of some of the Ten Essential Public Health Services that public health professionals and their partners work to provide in the communities they serve.
This Tool Box section will teach you what the Ten Essential Public Health Services are and illustrate their function in public health. When you have completed the tool, you will be able to identify which Essential Services are reflected in public health activities in your community. More importantly, we hope that you will understand how efforts across all ten Essential Service areas can work together to promote the health of everyone in the community.
To help you get started with identifying how the Ten Essential Public Health Services are reflected in day-to-day public health activities, Table 1 below matches five of the Ten Essential Public Health Services with their corresponding quiz scenarios.
Table 1: Examples of How Essential Services Are Reflected in Day-to-Day Public Health Activities
|
Quiz Scenario
|
Essential Public Health Service Implemented
|
|
Informing the public about an epidemiological outbreak investigation in the community
|
“Investigate, diagnose, and address health problems and hazards affecting the population”
|
|
Promoting enrollment in publicly funded health coverage
|
“Assure an effective system that enables equitable access to the individual services and care needed to be healthy”
|
|
Health education and health promotion to prevent heart disease
|
“Communicate effectively to inform and educate people about health, factors that influence it, and how to improve it”
|
|
Maintenance of a sanitary restaurant environment for public well-being
|
“Utilize legal and regulatory actions designed to improve and protect the public's health”
|
|
Shaping health policy, city planning, and transportation routes to create an environment that supports healthy behavior
|
“Create, champion, and implement policies, plans, and laws that impact health”
|
We hope that you want to read on and learn more. But before we discuss each of the Essential Services, we will visit the broader concept of defining the purpose and function of public health.
What is public health?
As you probably concluded from the quiz scenarios, public health is everywhere – it is part of the infrastructure that keeps our communities safe and healthy.
Definitions of public health vary somewhat among organizations and disciplines. The current Ten Essential Public Health Services framework is organized around protecting and promoting the health of all people in all communities.
Public health services may go unnoticed within a community because much of the work is preventive rather than reactive. For example, which community service are you more likely to notice – an environmental health specialist inspecting the safety of a local university’s food service establishments, or a fire truck speeding down the street with its lights and sirens on?
Despite having a relatively “low profile,” public health services play a key role in protecting and improving the health and well-being of communities. Improvements in sanitation, vaccination, disease prevention and control, safer workplaces, safer food and water, and other public health efforts have contributed greatly to longer and healthier lives.
Who is the typical public health professional?
There really is no “typical” public health professional. The public health workforce includes people with widely varied professional training, expertise, and lived experience.
- Some are nurses, physicians, or laboratory professionals by training.
- Some are educators, nutrition professionals, community health workers, or social workers.
- Some are biostatisticians, epidemiologists, or data professionals.
- Others are economists, planners, communications professionals, or lawyers.
- Community-based and grassroots contributors may include parents, caregivers, community leaders, advocates, and other community members who contribute their experience and time.
How do all of these people, with a common purpose but different skills and perspectives, work together successfully to carry out the work of public health? One framework they can use is the Ten Essential Public Health Services.
The Ten Essential Public Health Services differ in some ways from other logic models presented in Chapter 2 of the Tool Box. Other logic models discussed incorporate prescribed processes – for example, from planning to implementation to evaluation – that can then be applied to one priority goal such as preventing pregnancies among adolescents. In contrast, there is no prescribed order of implementation for the Ten Essential Services and no one specific outcome that results from implementing all ten. Rather, the Ten Essential Services provide a comprehensive framework that can support many different public health priorities in a community.
Although more prescriptive logic models may focus on one defined goal, they can also take a comprehensive approach within a community. For example, a planning phase might involve stakeholders from sectors beyond public health in an effort to create supportive conditions for change. This is not unlike the role of the Ten Essential Services.
You may be wondering,
“Why do people need a common framework for direction if they are already working toward the same mission?”
Because of their diverse backgrounds, professionals and community partners may have been trained to work from different models. One example is the “medical model” compared with the “public health model.” A major distinction is that public health activities generally focus on populations and the conditions affecting them, while clinical care generally focuses on individual patients. Table 2 below summarizes some broad differences between these approaches.
Table 2: Public Health and Medical Models of Professional Practice
| Public Health Model | Medical Model |
| Primary focus on populations | Primary focus on individuals |
| Public service ethic, with attention to individuals and communities | Personal service ethic, with awareness of broader social responsibilities |
| Emphasis on prevention, protection, and health promotion across populations | Emphasis on diagnosis, treatment, and care for individual patients |
| Uses a range of interventions addressing environments, behaviors, systems, policies, and access to care | Places primary emphasis on clinical care while recognizing other influences on health |
The Ten Essential Public Health Services provide common ground for people trained in either approach, as well as community-based workers and leaders from outside the traditional public health system, so they can work collaboratively to protect and promote health.
What are the Ten Essential Public Health Services?
In 1988, the Institute of Medicine identified three core functions of public health:
- Assessment
- Policy development
- Assurance
Public health leaders later worked to define a more detailed framework for carrying out those broad functions. The original Ten Essential Public Health Services framework was released in 1994.
The framework was revised in 2020 to better reflect current and future public health practice. The revised framework places equity at its center and gives greater attention to community engagement, social and structural conditions, cross-sector partnerships, and the systems needed to support public health.
Why is it important to implement and monitor the Ten Essential Public Health Services?
The Ten Essential Public Health Services put the public health approach into practice. Key principles include:
- A primary focus on populations and communities
- A commitment to public service and community well-being
- An emphasis on prevention, protection, and health promotion
- Attention to the conditions, systems, policies, environments, behaviors, and services that influence health
- A commitment to equity and to reducing barriers that prevent people and communities from achieving optimal health
Prevention remains a powerful element of public health practice.
- Prevention can reduce injuries, illnesses, and chronic disease.
- Prevention can save lives.
- Prevention can reduce avoidable health care costs and other social and economic costs.
- Prevention can benefit individuals, families, and communities through population-based public health efforts.
It is important not only to implement but also to monitor – track, assess, learn from, and modify as needed – the Ten Essential Public Health Services. Information about implementation, resources, reach, quality, and outcomes can inform decisions about public health programs, policies, priorities, and funding at local, state, tribal, territorial, and national levels.
How are the Ten Essential Services used in community practice?
On the pages that follow, each Essential Service is discussed in order from 1 to 10. Each discussion includes a description of the Service and examples of how it may appear in public health practice. Keep in mind that the Services do not have to be implemented in a “1-10” sequence or independently.
The Ten Essential Services are distinct but complementary areas of public health practice. Communities and public health systems should work across them together rather than treat them as isolated tasks. However, you may find that one or two connect particularly closely to your role in your community’s public health efforts.
Essential Service #1: Assess and monitor population health status, factors that influence health, and community needs and assets.
Public health surveillance – the ongoing, systematic collection, analysis, interpretation, and use of health-related data – is central to this Essential Service. Assessment can also include community knowledge and information about the social, economic, environmental, and structural conditions affecting health.
Essential Service #1 encompasses public health activities such as:
- Identifying threats to health and assessing community health needs and assets;
- Collecting, analyzing, and sharing timely information on health status, access to services, service use, costs, and outcomes;
- Examining differences in health conditions and outcomes among populations and geographic areas; and
- Collaborating with health care providers, community organizations, agencies, and other partners to strengthen information systems and community assessment.
National population-based surveillance systems administered or supported by the Centers for Disease Control and Prevention (CDC) include:
- The Behavioral Risk Factor Surveillance System;
- The National Vital Statistics System;
- The National Health Interview Survey; and
- Cancer registries.
You can access public health data through the Centers for Disease Control and Prevention and other federal, state, and local sources. You may not immediately think to use national data when working at the community level. However, national and state surveillance data can provide useful benchmarks as you assess health measures in your community.
Prior to investing significant resources and time in a program, it is often useful to conduct a needs and assets assessment. Community data can then be compared with state or national information to help determine where attention and resources may have the greatest value.
If you do not have the time or resources to conduct your own comprehensive assessment, community-level information may also be available through sources such as:
- State and local health reports and dashboards;
- School and community health reports;
- Public safety and transportation data; and
- Community surveys, focus groups, interviews, and other sources of local knowledge.
Essential Service #2: Investigate, diagnose, and address health problems and hazards affecting the population.
Essential Service #2 encompasses public health activities such as:
- Epidemiologic identification and investigation of emerging health threats;
- Public health laboratory capacity to conduct timely screening, testing, and analysis;
- Infectious disease investigation and response;
- Investigation of patterns of chronic disease, injury, environmental hazards, and other threats to health; and
- Working with communities and partners to understand and address the conditions contributing to health problems and hazards.
At the national level, the United States Department of Health and Human Services includes agencies such as the Agency for Toxic Substances and Disease Registry (ATSDR), which works to prevent harmful exposures and health effects related to hazardous substances.
At the state and local levels, public health laboratories, epidemiologists, environmental health professionals, and other partners provide testing, surveillance, investigation, applied research, communication, and other essential services to the communities they serve.
These professionals often work behind the scenes on issues that appear in the news – infectious disease outbreaks, foodborne illness, environmental exposures, newborn screening, emerging diseases, and other public health threats and emergencies.
Essential Service #3: Communicate effectively to inform and educate people about health, factors that influence it, and how to improve it.
You have probably encountered – and perhaps participated in – health promotion and public health communication efforts in your community.
Essential Service #3 encompasses public health activities such as:
- Public communication and health promotion through appropriate media and communication channels;
- Providing clear, accessible, and useful health information at the community level;
- Collaborating with health care providers and community partners to reinforce accurate health information;
- Conducting health education with schools, workplaces, faith communities, community organizations, and other partners; and
- Developing culturally and linguistically appropriate communication that reflects health literacy and accessibility needs.
National public health campaigns provide familiar examples. One is Safe to Sleep, formerly known as Back to Sleep, which provides parents, caregivers, and health professionals with information about reducing the risk of sudden infant death syndrome (SIDS) and other sleep-related infant deaths.
Many national awareness events also relate directly to public health efforts. The American Public Health Association sponsors National Public Health Week each year. Communities may also sponsor local events, presentations, health fairs, workshops, or other activities to increase awareness and connect people with useful information and resources.
Essential Service #4: Strengthen, support, and mobilize communities and partnerships to improve health.
These activities represent a comprehensive approach to community health, in which community members, professionals, organizations, and sectors collaborate to understand issues, plan and implement action, monitor progress, evaluate results, and modify their efforts as needed.
Essential Service #4 encompasses public health activities such as:
- Convening, supporting, and engaging community groups and associations, including those not traditionally considered health-related, to work on shared community priorities; and
- Building and sustaining partnerships that draw on the full range of human, organizational, and material resources available in the community.
This is similar in some respects to the PATCH logic model – the Planned Approach to Community Health.
Included in the PATCH strategy are five elements that are fundamental to community health promotion:
- Community members participate in the process.
- Data guide the development of programs.
- Participants develop a comprehensive health promotion strategy.
- Evaluation emphasizes feedback and program improvement.
- Community capacity for health promotion is increased.
You can read about a similar process for mobilizing community partnerships to identify and address health problems in the Community Tool Box's Community Action Guide: A Framework for Addressing Community Goals and Problems.
The overall goal of action planning is to increase your community’s ability to work together to affect conditions and outcomes that matter to its residents – and to do so both over time and across issues of interest.
As your community works toward a broad vision of health for all, creating supportive conditions for change requires comprehensive efforts among diverse sectors of the community. These can include health organizations, community groups, faith communities, schools, businesses, housing organizations, transportation agencies, and others. Representatives and community members can come together to form a community coalition. Your coalition can then work to influence systems – programs, policies, practices, and community conditions – that can enhance or detract from health and well-being.
Essential Service #5: Create, champion, and implement policies, plans, and laws that impact health.
Public health policies and plans can affect health far beyond the boundaries of a single program. Data on health conditions, program performance, community priorities, and disparities can help policymakers and communities determine which policies and plans are working and where changes may be needed.
Essential Service #5 encompasses public health activities such as:
- Leadership development at different levels of public health and community systems;
- Community and jurisdiction-level planning for health improvement;
- Development and tracking of measurable health objectives as part of continuous learning and improvement;
- Collaboration across public health, health care, government, community organizations, and other sectors in policy and planning; and
- Development and implementation of policies, plans, codes, regulations, and legislation that can improve health.
Community design provides one example. Public health professionals can work with city planning, transportation, architecture, recreation, public safety, schools, community groups, and others to create environments that support physical activity and community health. Strategies may address land use, public transit, walking and bicycling, public spaces, parks, trails, and other aspects of the built environment.
Essential Service #6: Utilize legal and regulatory actions designed to improve and protect the public's health.
You may not always be conscious of how laws and public health regulations influence your community environment. Think, for example, about some of the things you see or experience when you visit restaurants. You may notice a certificate or inspection grade showing that the restaurant has been evaluated for compliance with food safety requirements.
You may also encounter smoke-free requirements in restaurants, workplaces, and other public settings. Such policies are examples of legal and regulatory actions intended to protect health.
States also establish vaccination requirements for school attendance, subject to applicable laws and exemptions. When enough people are protected against a contagious disease, transmission becomes more difficult, helping protect the broader community.
Essential Service #6 encompasses public health activities such as:
- Implementing and enforcing food safety and sanitation requirements;
- Protecting drinking water supplies;
- Implementing clean air and environmental health protections;
- Following up on hazards, preventable injuries, and exposure-related conditions identified in occupational and community settings;
- Monitoring compliance with applicable health and safety requirements; and
- Using legal and regulatory tools to address emerging health and safety concerns.
Essential Service #6 may be carried out through local, state, tribal, territorial, or federal law and regulation. Community members and public health professionals can also identify emerging concerns and advocate for appropriate changes in public policy.
Essential Service #7: Assure an effective system that enables equitable access to the individual services and care needed to be healthy.
Essential Service #7 encompasses public health activities such as:
- Helping people experiencing social, economic, geographic, or other barriers connect with coordinated systems of health and social services;
- Providing culturally and linguistically appropriate information and support to connect people with services;
- Helping coordinate care and services when needed;
- Addressing transportation and other practical barriers to care;
- Providing targeted health information and outreach to populations experiencing greater barriers or health risks; and
- Working with health care, social service, workplace, and community partners to strengthen access to prevention and care.
The implementation of this Essential Service is closely linked to social, economic, geographic, and policy conditions. Two important public coverage programs in the United States are Medicaid and the Children’s Health Insurance Program (CHIP).
Medicaid provides health coverage to millions of eligible people, including children, pregnant people, adults, older adults, and people with disabilities. The program is jointly funded by the federal government and the states and is administered by states according to federal requirements.
The Children’s Health Insurance Program (CHIP) provides health coverage to eligible children in families whose incomes are too high to qualify for Medicaid but who may otherwise have difficulty affording private coverage. CHIP is jointly funded by states and the federal government and administered by states according to federal requirements.
To learn more about Medicaid and CHIP, visit the Centers for Medicare & Medicaid Services.
The existence of a program does not automatically mean that everyone who could benefit from it can easily access it. Public health and community partners may therefore provide outreach such as:
- Community education about available programs and services;
- Assistance with applications and enrollment;
- Referrals and connections among related health, nutrition, social service, and community programs; and
- Transportation assistance or other support needed to reach services.
Culturally and linguistically appropriate information is also a critical component of outreach. Community assessments, census data, and other local information can help identify languages spoken and communication needs within a geographic area. Effective outreach should also consider health literacy, disability access, cultural context, and the ways community members prefer to receive information.
Essential Service #8: Build and support a diverse and skilled public health workforce.
Essential Service #8 encompasses public health activities such as:
- Education, training, and professional development needed to meet public and community health needs;
- Appropriate licensure, credentialing, and certification processes where required;
- Continuous learning, professional development, and quality improvement;
- Partnerships with educational and training programs to provide community-relevant learning and practice experiences;
- Management and leadership development for people in supervisory, administrative, and executive roles; and
- Recruitment, support, and retention of a workforce that reflects a broad range of disciplines, backgrounds, perspectives, and communities.
There are many opportunities for education, training, and continuing professional development in public health. The Association of Schools and Programs of Public Health represents accredited schools and programs of public health, while the Council on Education for Public Health is the independent agency recognized by the U.S. Department of Education to accredit schools and programs in public health.
Continuing education is available through professional organizations, conferences, universities, training centers, online programs, and workplace-based learning. Online and hybrid education can make professional development more accessible to public health workers who might otherwise face barriers related to travel, time, or cost.
Building the public health workforce is not limited to formal academic education. It also includes continuing development of practical skills, leadership capacity, cultural responsiveness, communication, data use, emergency preparedness, community engagement, and other competencies needed to respond to changing community needs.
Essential Service #9: Improve and innovate public health functions through ongoing evaluation, research, and continuous quality improvement.
Evaluation helps public health professionals and their partners understand what is working, what is not, for whom, under what conditions, and at what cost. Evaluation findings can then be used to refine programs, improve implementation, allocate resources, and make future decisions.
Essential Service #9 encompasses activities such as:
- Ongoing evaluation of public health programs, policies, services, and systems;
- Using performance management and continuous quality improvement to strengthen public health practice;
- Identifying and testing promising or innovative approaches;
- Connecting public health practice with academic, research, community, and other partners;
- Conducting epidemiologic, policy, economic, public health systems, and other forms of applied research; and
- Using evidence and evaluation findings to improve programs and decision-making.
Surveillance and assessment data from Essential Service #1 can support evaluation. For example, a community may examine baseline data before implementing an initiative and then compare those measures with later data to understand whether conditions or outcomes have changed.
Evaluation plans and concepts are addressed in several chapters and sections of the Community Tool Box. These include:
Chapters 36-39, which fall under the broad topic, “Evaluating Community Programs and Initiatives.”
Research for new insights and innovative solutions can take many forms. Public health agencies may work with universities, health care systems, community organizations, or other partners when specialized expertise or additional capacity is needed.
Economic evaluation is one example. Two commonly used approaches are cost-benefit and cost-effectiveness analysis.
A cost-benefit analysis compares the costs of an intervention with benefits expressed in monetary terms. For example, the cost of a prevention program might be compared with health care costs avoided as a result of the program.
A cost-effectiveness analysis compares program costs with specific outcomes that do not necessarily have to be expressed in dollars. It can be useful for comparing different approaches that pursue the same or similar objectives.
Essential Service #10: Build and maintain a strong organizational infrastructure for public health.
Strong public health practice depends not only on individual programs, but also on the organizations and systems that support them. Public health agencies and partnerships need the leadership, staffing, technology, financial management, planning, communication, and governance capacity necessary to carry out their responsibilities effectively.
Essential Service #10 encompasses activities such as:
- Managing financial and human resources effectively;
- Maintaining strong communication and strategic planning capacity;
- Maintaining information technology systems that meet current operational, privacy, and security needs;
- Understanding how government agencies, elected officials, community organizations, health care systems, and other institutions contribute to the broader public health system;
- Allocating needed resources fairly and effectively to support the public’s health;
- Practicing accountable, transparent, and inclusive decision-making with partners and communities; and
- Providing effective and ethical leadership and governance.
Organizational infrastructure may not be as visible as an outbreak investigation, health campaign, vaccination clinic, or restaurant inspection, but all of those activities depend on it. A health department or community public health system needs functioning financial systems, qualified staff, reliable technology, effective communication, clear leadership, and strong partnerships in order to carry out the other Essential Services.
The Ten Essential Public Health Services are therefore best understood not as ten isolated programs, but as parts of a larger public health system. Assessment, investigation, communication, community partnership, policy, regulation, access to services, workforce development, evaluation and innovation, and organizational infrastructure reinforce one another.
Communities may enter the framework through different activities and priorities, but strengthening the system across all ten Essential Services can improve its ability to protect and promote health, respond to changing needs, and work toward health and well-being for everyone.
Resources
Online Resources
- American Public Health Association
- Association of Schools of Public Health
- Association of State and Territorial Health Officials
- Environmental Council of the States
- Essential Public Health Services. Public Health Foundation (2002)
- The Essential Services of Public Health. American Public Health Association (2003)
- National Association of County and City Health Officials
- National Association of State Alcohol and Drug Abuse Directors
- National Association of State Mental Health Program Directors
- Programs in Brief Centers for Disease Control and Prevention (2003)
- Public Health Code of Ethics (Issue Brief) American Public Health Association
- Public Health Foundation
- Publich Health Quality Improvement Exchange (PHQIX) allows people to submit short explanations of their initiatives and observations/lessons-learned.
- United States Public Health Service
- What is Public Health? Association of Schools of Public Health (2003)
Guide for Enhancing Core Functions and Essential Services for Public Health Improvement
1. Assess and monitor population health.
- Analyzing Community Problems
- Assessing Community Needs and Resources
- Collecting Information About the Problem
- Conducting Concerns Surveys
- Conducting Focus Groups
- Conducting Interviews
- Conducting Needs Assessment Surveys
- Conducting Public Forums and Listening Sessions
- Conducting Surveys
- Determining Service Utilization
- Developing a Plan for Assessing Local Needs and Resources
- Developing Baseline Measures of Behavior
- Identifying Community Assets and Resources
- Understanding and Describing the Community
2. Investigate, diagnose, and address health hazards and root causes.
- Adapting Community Interventions for Different Cultures and Communities
- Analyzing Community Problems
- Analyzing Problems and Goals
- Analyzing Root Causes of Problems: The "But Why?" Technique
- Collecting Information About the Problem
- Conducting Interviews
- Defining and Analyzing the Problem
- Designing Community Interventions
- Developing an Intervention
- Ethical Issues in Community Interventions
- Identifying Targets and Agents of Change: Who Can Benefit and Who Can Help
- Identifying Strategies and Tactics for Reducing Risk
- An Introduction to the Problem Solving Process
- Understanding Risk and Protective Factors: Their Use in Selecting Potential Targets and Promising Strategies for Interventions
3. Communicate effectively to inform and educate.
- Arranging a Press Conference
- Arranging News and Features Stories
- Communicating Information about Community Health and Development Issues
- Creating Brochures
- Creating Fact Sheets on Local Issues
- Creating Newsletters
- Creating Posters and Fliers
- Creating a Website
- Conducting a Social marketing Campaign
- Developing a Plan for Communication
- Developing Creative Promotions
- Handling Crises in Communication
- Implementing a Social Marketing Effort
- Making Community Presentations
- Our Model of Practice: Building Capacity for Community and System Change
- Preparing Press Releases
- Preparing Guest Columns and Editorials
- Preparing Public Service Announcements
- Reframing the Issue
- Some Lessons Learned on Community Organization and Change
- Talking About Risk and Protective Factors Related to Community Issues
- Using Paid Advertising
- Using E-mail Lists
4. Strengthen, support, and mobilize communities and partnerships.
- Attracting Support for Specific Programs
- Changing Policies to Increase Funding for Community Health and Development Initiatives
- Community (Locality) Development
- Creating Objectives
- Developing an Action Plan
- Our Model of Practice: Building Capacity for Community and System Change
- Our Evaluation Model: Evaluating Comprehensive Community Initiatives
- Working Together for Healthier Communities: A Framework for Collaboration Among Community Partnerships, Support Organizations, and Funders
- Developing a Plan for Getting Community Health and Development Issues on the Local Agenda
- Developing an Ongoing Board of Directors
- Developing Strategic and Action Plans
- Developing Successful Strategies: Planning to Win
- Identifying Action Steps in Bringing About Community and System Change
- Maintaining a Board of Directors
- Marketing the Initiative to Secure Financial Support
- Obtaining Feedback from Constituents: What Changes Are Important and Feasible?
- Organizational Structure: An Overview
- An Overview of Strategic Planning or VMOSA (Vision, Mission, Objectives, Strategies, Action Plan)
- Proclaiming Your Dream: Developing Vision and Mission Statements
- Promoting Adoption of the Initiative's Mission and Objectives
- Promoting Coordination, Cooperative Agreements, and Collaborative Agreements Among Agencies
- Social Action
- Sustaining the Work or Initiative
- Strategies for the Long-Term Institutionalization of an Initiative: An Overview
- Strategies for Sustaining the Initiative
- Welcoming and Training New Members to a Board of Directors
5. Create, champion, and implement policies, plans, and laws.
- Advocating for a Change
- Conducting a Petition Drive
- Conducting a Public Hearing
- Developing a Plan for Advocacy
- Encouraging Involvement of Potential Opponents as well as Allies
- Filing a Complaint
- General Rules for Organizing for Legislative Advocacy
- Identifying Opponents
- Lobbying Decisionmakers
- Overview: Getting an Advocacy Campaign Off the Ground
- Recognizing Allies
- Survival Skills for Advocates
- Understanding the Issue
- Using Personal Testimony
- Writing Letters to Elected Officials
- Writing Letters to the Editor
6. Utilize legal and regulatory actions.
- Adapting Community Interventions for Different Cultures and Communities
- Building Leadership
- Capturing What People Say: Tips for Recording a Meeting
- Coalition Building I: Starting a Coalition
- Conducting Effective Meetings
- Creating and Maintaining Coalitions and Partnerships
- Developing a Plan for Building Leadership
- Developing a Plan for Involving Volunteers
- Strategies for Community Change and Improvement: An Overview
- Social Action
- Using Principles of Persuasion
- Designing Community Interventions
- Developing a Community Leadership Corps: A Model for Service-Learning
- Developing a Plan for Increasing Participation in Community Action
- Developing Facilitation Skills
- Developing Training Programs for Volunteers
- Developing Volunteer Orientation Programs
- Establishing Micro-grant Programs
- Ethical Issues in Community Interventions
- Identifying Strategies and Tactics for Reducing Risks
- Identifying Targets and Agents of Change: Who Can Benefit and Who Can Help
- Involving Key Influentials in the Initiative
- Involving People Most Affected by the Problem
- Making Personal Contact with Potential Participants
- Methods of Contacting Potential Participants
- Promoting Neighborhood Action
- Promoting Participation Among Diverse Groups
- Recruiting Volunteers
- Servant Leadership: Accepting and Maintaining the Call of Service
- Training for Conflict Resolution
- Understanding Risk and Protective Factors: Their Use in Selecting Potential Targets and Promising Strategies for Interventions
- Writing Letters to Potential Participants
7. Enable equitable access.
- Developing Multisector Collaborations
- Identifying Opponents
- Increasing Participation and Membership
- Overview: Getting an Advocacy Campaign Off the Ground
- Promoting Coordination, Cooperative Agreements, and Collaborative Agreements Among Agencies
- Recognizing Allies
- Survival Skills for Advocates
- Understanding and Describing the Community
- Understanding the Issue
- Applying for Grants
8. Build a diverse and skilled workforce.
- Building Leadership
- Building and Sustaining Commitment
- Building and Sustaining Relationships
- Building Relationships with People from Different Cultures
- Capturing What People Say: Tips for Recording a Meeting
- Conducting a Workshop
- Conducting Effective Meetings
- Collecting Information About the Problem
- Conducting Needs Assessment Surveys
- Conducting Surveys
- Designing a Training Session
- Delivering a Training Session
- Defining and Analyzing the Problem
- Developing a Community Leadership Corps: A Model for Service-Learning
- Developing and Communicating a Vision
- Developing a Management Plan
- Developing a Plan for Staff Hiring and Training
- Developing a Plan for Building Leadership
- Developing Facilitation Skills
- Discovering and Creating Possibilities
- Enhancing Cultural Competence
- Generating and Choosing Solutions
- Healing from the Effects of Internalized Oppression
- Influencing People
- An Introduction to the Problem Solving Process
- Learning From and Contributing to Constituents
- Learning How to Be a Community Leader
- Making Decisions
- Multicultural Collaboration
- Promoting Coordination, Cooperative Agreements, and Collaborative Agreements Among Agencies
- Providing Supervision for Staff and Volunteers
- Providing Support for Staff and Volunteers
- Putting Your Solutions into Practice
- Servant Leadership: Accepting and Maintaining the Call of Service
- Transforming Conflicts in Diverse Communities
- Understanding Culture and Diversity in Building Communities
- Understanding People’s Needs
9. Improve and innovate through evaluation, research, and quality improvement.
- Behavioral Surveys
- Choosing Evaluators
- Communicating Information to Funders for Support and Accountability
- Conducting Interviews with Key Participants to Analyze Critical Events
- Constituent Survey of Outcomes: Ratings of Importance
- Developing an Evaluation Plan
- Establishing Formal Communication and Requesting Participation
- Evaluating the Initiative
- A Framework for Program Evaluation: A Gateway to Tools
- Gathering Data on Public Opinion
- Gathering Information: Monitoring Your Progress
- Gathering and Using Community-Level Indicators
- How to Conduct Research: An Overview
- Measuring Success: Evaluating Comprehensive Community Initiative
- Our Evaluation Model: Evaluating Comprehensive Community Initiatives
- Providing Feedback to Improve the Initiative
- Rating Community Goals
- Rating Member Satisfaction
- Reaching Your Goals: The Goal Attainment Report
- Understanding Community Leadership, Evaluators, and Funders: What Are Their Interests?
10. Build and maintain a strong organizational infrastructure for public health.
- Adapting Community Interventions for Different Cultures and Communities
- Assessing Community Needs and Resources
- Conducting Public Forums and Listening Sessions
- Collecting Information About the Problem
- Designing Community Interventions
- Developing a Plan for Assessing Local Needs and Resources
- Developing Multisector Collaborations
- Identifying Targets and Agents of Change: Who Can Benefit and Who Can Help
- Identifying Strategies and Tactics for Reducing Risks
- Understanding and Describing the Community
- Understanding Risk and Protective Factors: Their Use in Selecting Potential Targets and Promising Strategies for Interventions
- Promoting Coordination, Cooperative Agreements, and Collaborative Agreements Among Agencies
Print Resources
American Public Health Association (June 2003). The Guide to Implementing Model Standards. This resource includes discussion of PATCH implementation along with other model standards for community health development, such as the Assessment Protocol for Excellence in Public Health.
Association of Schools of Public Health (2003). The Population Approach to Public Health.
Centers for Disease Control and Prevention (1999). Ten Great Public Health Achievements—United States, 1900 – 1999. Morbidity and Mortality Weekly Report, April 02, 1999: 48(12); 241-243.
The remaining nine links will take you to the web pages of organizations that served on the Public Health Functions Steering Committee, which adopted the Ten Essential Public Health Services in 1994.
United States Department of Health and Human Services (1989). Making Health Communication Programs Work: A Planner’s Guide. Bethesda, MD: United States Department of Health and Human Services, Public Health Service, National Institutes of Health, Office of Cancer Communications, National Cancer Institute.
Wholey, J., Hatry, H., & Newcomer, K. (Eds.) (1994). Handbook of Practical Program Evaluation. San Francisco: Jossey-Bass.
What is public health?
___Public health is the part of the civic infrastructure that keeps communities safe and healthy.
___The current generally accepted mission of public health is: “Promote physical and mental health, and prevent disease, injury, and disability.”
Who are public health professionals?
___Nurses
___Physicians
___Laboratory technicians
___Educators
___Nutritionists
___Social workers
___Biostatisticians
___Epidemiologists
___Economists
___Lawyers
___Community-based or “grassroots” workers might include concerned parents, grandparents, or civic leaders who volunteer their time.
What are the Ten Essential Public Health Services?
___The Ten Essential Public Health Services fall into three categories that define thecore functions of public health:
- Assessment
- Policy Development
- Assurance
Assessment:
___1. Monitor health status to identify community health problems.
___2. Diagnose and investigate health problems and health hazards in the community.
Policy Development:
___3. Inform, educate, and empower people about health issues.
___4. Mobilize community partnerships to identify and solve health problems.
___5. Develop policies and plans that support individual and community health efforts.
Assurance:
___6. Enforce laws and regulations that protect health and ensure safety.
___7. Link people to needed personal health services and assure the provision of health care when otherwise unavailable.
___8. Assure a competent public health and personal health care workforce.
___9. Evaluate effectiveness, accessibility, and quality of personal and population-based health services.
___10. Research for new insights and innovative solutions to health problems.
How do you use the Ten Essential Public Health Services in Community Practice?
1. Monitor health status to identify community problems.
___This service comprises the ongoing, systematic collection, analysis, and interpretation of health related data, including:
- Identification of threats to health and assessment of health service needs;
- Timely collection, analysis, and publication of information on access, utilization, costs, and outcomes of personal health services;
- Attention to the vital statistics and health status of specific groups that are at higher risk than the total population; and
- Collaboration to manage integrated information systems with private providers and health benefit plans.
___To monitor community health status, you can use federal, state, and community-level information, such as:
- Census data
- Centers for Disease Control (CDC) data, including the National Vital Statistics System, the Behavioral Risk Factor Surveillance System, the National Health Interview Survey, and the Cancer Registries.
- State-level “report cards” on maternal and child health and other areas, as well as reports and statistics from the state public health agency.
- School health reports.
- Community surveys.
- Information about community-level indicators, such as drunk driving arrests, fett of store shelf space devoted to healthy products, and heart-related emergency room visits.
2. Diagnose and investigate health hazards in the community.
___This service encompasses public health activities such as:
- Epidemiologic identification of emerging health threats;
- Public health laboratory capability using modern technology to conduct rapid screening and high volume testing;
- Active infectious disease epidemiology programs; and
- Technical capacity for epidemiologic investigation of disease outbreaks and patterns of chronic disease and injury.
3. Inform, educate, and empower people about health issues.
___Social marketing and targeted media public communication (e.g., Toll-free information lines).
___Providing accessible health information resources at community levels (e.g., free, mobile health screening initiatives).
___Active collaboration with personal health care providers to reinforce health promotion messages and programs.
___Joint health education programs with schools, churches, and worksites (e.g., stress reduction seminars; parenting support groups for enhancing mental health; and health fairs).
4. Mobilize community partnerships to identify and solve health problems.
___Convene and facilitate community groups and associations, including those not typically considered to be health-related, to undertake defined preventive, screening, rehabilitation, and support programs.
___Build multi-sector community coalitions in order to draw upon the full range of potential human and material resources in the cause of community health.
5. Develop policies and plans that support individual and community health efforts.
___Leadership development at all levels of public health.
___Systematic community-level and state-level planning for health improvement in all jurisdictions.
___Development and tracking of measurable health objectives as a part of continuous quality improvement strategies.
___Joint evaluation with the medical health care system to define consistent policy regarding prevention and treatment services.
___Development of codes, regulations, and legislation to guide the practice of public health.
6. Enforce laws and regulations that protect health and ensure safety.
___Full enforcement of sanitary codes, especially in the food industry.
___Full protection of drinking water supplies.
___Enforcement of clean air standards.
___Timely follow-up of hazards, preventable injuries, and exposure-related diseases identified in occupational and community settings.
___Monitoring quality of medical services (e.g., laboratory, nursing homes, and home health care).
___Timely review of new drug, biologic, and medical device application.
___Advocacy for needed new health and safety laws and regulations.
7. Link people to needed personal health services and assure the provision of health care when otherwise unavailable.
___Effective entry for socially disadvantaged people into a coordinated system of clinical care.
___Culturally and linguistically appropriate materials and staff to assure linkage to services for special population groups.
___Ongoing “care management.”
___Transportation services.
___Targeted health information to high risk population groups.
___Technical assistance for effective worksite health promotion/disease prevention programs.
___Outreach and support to populations in need of government services.
8. Assure a competent public health and personal care workforce.
___Education and training for personnel to meet the needs for public and personal health service.
___Efficient processes for licensure of professionals and certification of facilities, with regular verification and inspection follow-up.
___Adoption of continuous quality improvement and life-long learning within all licensure and certification programs.
___Active partnerships with professional training programs to assure community-relevant learning experiences for all students.
___Continuing education in management and leadership development programs for those charged with administrative / executive roles.
9. Evaluate effectiveness, accessibility, and quality of personal and population-based health services.
___Evaluation helps public health professionals continually refine or revise program approaches in future years of funding.
___Evaluation data provide information about the relative costs and effort for tasks so activity and budget adjustments can be made.
___To ensure useful results that lead to more effective services, it is necessary to conduct ongoing evaluations of health programs based on analysis of health status and service utilization data, to assess program effectiveness and to provide information necessary for allocating resources and reshaping programs.
10. Research for new insights and innovative solutions to health problems.
___Link with appropriate institutes of higher learning and research.
___Mount timely epidemiologic (e.g., outbreak investigations) and economic analyses (e.g., cost-benefit studies).
___Conduct needed health services research (e.g., survey design; conducting interviews and facilitating focus groups; conducting clinical trials; and accessing and using public records).
___Engage in collaborative research with other programs, and publicize your results.
___Seek funding for both individual and collaborative research into health problems.
___Publicize research results so others can use and build on them.
In Chapter 2, we’ve looked at a variety of different models for building healthy communities, including one – asset development – that focused on building the advantages that young people need in order to develop into healthy, successful adults. That model approaches adolescent health and growth from a positive angle, assuming that if you can provide young people with the appropriate support and opportunities, healthy development is more likely.
But there are negative as well as positive influences at work in families, schools, and communities. If completing high school is uncommon or not strongly supported in an adolescent’s environment, that young person may be less likely to see graduation as important or attainable. Young people may find it harder to avoid substance use if substances are readily available at school or in the community. If violence is common or normalized in a community, young people may be more likely to experience or become involved in it.
In this section, we’ll look at a model that acknowledges both the positive (protective) and negative (risk) factors that affect adolescents, with the goal of enhancing the former and reducing the latter. The model has a narrower focus than some we’ve profiled, but its purpose is the same – to enhance the healthy development of young people, and thus to create a healthier community.
Like most other models, Communities That Care takes a community-wide perspective and calls for broad community participation. Similar to PRECEDE/PROCEED, it identifies problems and resources, develops solutions aimed directly at the identified issues, and integrates evaluation into implementation.
Communities That Care resembles the Search Institute’s asset development model in its emphasis on young people and the protective and risk factors affecting them. Where asset development looks at the overall development of children and adolescents, however, Communities That Care focuses more specifically on preventing health and behavior problems and promoting healthy youth development.
What is Communities That Care?
Communities That Care (CTC) is based on the Social Development Strategy developed through the work of J. David Hawkins, Richard Catalano, and colleagues at the University of Washington. Rather than being a single prevention program, CTC is a prevention-planning system that provides the structure, but not the specific content, of a community effort to address youth health and behavior issues. It focuses on risk and protective factors through a community-wide process that includes assessment, planning, training, implementation, and evaluation.
The current Communities That Care PLUS system is supported by the Center for Communities That Care at the University of Washington. The Center provides licensing, training, coaching, tools, and technical assistance to help communities carry out the process.
The version of CTC discussed in this section has historically focused on several major adolescent health and behavior outcomes:
- Substance use
- Delinquency
- Pregnancy among adolescents
- Leaving school before graduation
- Violence
Risk factors
Risk factors are conditions or characteristics that can increase the likelihood of particular behaviors or outcomes. An assumption behind the CTC model, which it shares with the other models described in this chapter, is that risk and protective factors span many areas of community life. With that assumption in mind, CTC organizes risk factors into four broad contexts: community, family, school, and individual/peer.
Community risk factors. These have to do with conditions within the community as well as community attitudes, policies, and structures.
- Availability of drugs. Easier access to alcohol and other drugs can increase opportunities for young people to use them and can contribute to community norms that make substance use appear more acceptable.
- Availability of firearms. Access to firearms can increase the potential for serious harm when violence occurs.
- Community laws and norms favorable to drug use, firearms, and crime. Laws, policies, enforcement practices, and community norms can influence how acceptable or common particular behaviors appear to young people.
Lack of clarity in laws and practices can also raise problems for young people. If alcohol is routinely available at community events, if minimum drinking-age laws are rarely enforced, or if excessive drinking by adults and adolescents is widely accepted, young people may receive inconsistent messages about what is expected of them.
- Media portrayals of problem behavior. Media can influence attitudes and beliefs about violence, substance use, and other behavior, particularly when those behaviors are repeatedly portrayed as normal, desirable, or without consequences.
- Transitions and mobility. Transitions – from one school to another, for example, or from middle to high school – can be difficult for adolescents. Frequent moves or major community disruptions can make it harder for young people and families to maintain stable relationships and support systems.
- Low neighborhood attachment and community disorganization. When residents feel little connection to their neighborhoods or limited ability to influence community conditions, community participation and informal support may weaken. Deteriorating physical conditions, instability, and a lack of shared responsibility for public spaces can increase risks for young people.
- Extreme economic deprivation. Severe economic hardship can expose young people and families to multiple stresses and barriers that increase the likelihood of a range of negative health, educational, and social outcomes.
Family. Family relationships, expectations, and circumstances can have an important effect on a young person’s present and future behavior.
- Family history of problem behavior. Young people may be influenced by behaviors, experiences, and expectations within their families. A family history of substance use, involvement with the justice system, leaving school before graduation, violence, or other challenges can increase risk, although it does not determine what any individual young person will do.
- Family management problems. Young people benefit from clear expectations, appropriate supervision, consistent boundaries, and supportive relationships. A lack of these structures, or the use of abuse or violence as discipline, can increase risk.
- Family conflict. High levels of ongoing conflict among members of a household can contribute to stress and increase the likelihood of difficulties for children and adolescents.
- Parental attitudes toward, or involvement in, substance use, crime, and violence. When parents or caregivers approve of, normalize, or engage in these behaviors, young people may be more likely to view them as acceptable. Risk can be especially high when adults directly involve children or adolescents in harmful or illegal activity.
School. School represents more than a place to learn reading or algebra. It is also an important social environment in which young people develop relationships, skills, expectations, and a sense of belonging.
- Academic failure beginning in late elementary school. Persistent academic difficulty can be frustrating and discouraging. A student who doesn’t understand the material may disengage, miss additional learning, and fall further behind. Over time, repeated difficulty can weaken the student’s connection to school and confidence as a learner.
Peer and group norms can sometimes make academic achievement seem inconsistent with belonging or with the identity a young person values. When young people feel pressure to choose between academic success and acceptance by people important to them, school engagement can suffer. Supportive peers, families, teachers, and communities can help make achievement compatible with a young person’s identity and sense of belonging.
- Lack of commitment to school. This may result from academic difficulty, negative experiences at school, a lack of belonging, or a belief that school and education are not relevant or worthwhile.
Individual/peer. This set of risk factors concerns personal characteristics, attitudes, experiences, and close peer relationships.
- Early and persistent antisocial behavior. Persistent patterns of aggressive or seriously disruptive behavior beginning early in life can signal increased risk, particularly when they continue without effective support or intervention.
- Rebelliousness. Persistent rejection of rules, social expectations, or conventional goals may increase risk when it becomes connected with harmful or illegal behavior.
- Friends who engage in problem behaviors. Because peer relationships are especially important during adolescence, friends’ attitudes and actions can strongly influence behavior. Put more simply: the people adolescents spend time with matter.
- Favorable attitudes toward the problem behavior. Young people are more likely to engage in a behavior when they view it as acceptable, desirable, harmless, or normal.
- Early initiation of the problem behavior. The earlier a behavior begins, the more opportunity there may be for it to become established as a regular part of a young person’s life.
- Constitutional factors. CTC uses this term for individual characteristics that may have biological, neurological, developmental, or environmental influences and that can affect behavior, such as impulse control and sensation-seeking. These characteristics do not determine a young person’s future, but can interact with other risk and protective factors.
Protective factors
Just as some factors increase risk, protective factors can support healthy development and buffer young people from risk. The Social Development Strategy organizes protection around several closely connected elements.
Individual characteristics.
Young people differ in temperament, abilities, interests, experiences, and ways of responding to stress. Some individual characteristics and skills can make it easier to cope with challenges, but no single characteristic guarantees healthy development, and the absence of a particular characteristic does not determine a young person’s future.
- Resilience-related characteristics. Some children and adolescents appear better able to adapt to difficulties than others. Their ability to cope can also be strengthened by relationships, experiences, skills, and supportive environments.
- Positive orientation. Hopefulness, positive relationships, and a sense that challenges can be managed can support healthy development.
- Cognitive, social, and problem-solving skills. Skills that help young people understand situations, consider consequences, manage emotions, solve problems, and interact effectively with others can help protect against a variety of risks.
Individual characteristics should never be treated as destiny. Young people develop over time, and skills, coping strategies, relationships, and confidence can grow through supportive experiences, learning, and appropriate services.
Bonding. Children and adolescents form strong connections to parents and caregivers, other adults, peers, schools, organizations, and communities. When young people feel connected to people or groups that model and support healthy behavior, those relationships can serve as important protective factors.
CTC emphasizes positive bonding. Not every strong bond is necessarily protective. A young person who feels deeply connected to a group that encourages violence or other harmful behavior may be influenced in that direction. Protective bonds are connections with people and groups that support healthy development and positive social values.
These might include:
- Parents, caregivers, and families
- Other significant adults – relatives, neighbors, counselors, mentors, etc.
- Teachers
- Peer groups
- Schools
- Organizations – Scouts, faith-based groups, social clubs, workplaces, etc.
- Sports teams
- Community groups, service organizations, cultural organizations, and others
Healthy beliefs and clear standards. Significant adults and groups help create environments that communicate positive values and make expectations clear to young people.
Families, other adults, schools, and communities can communicate and model values that support healthy behavior. They can also establish reasonable, clearly stated expectations and standards for children’s and adolescents’ behavior and achievement.
In other words, adults in the community should practice the values they communicate and make clear what they expect of young people.
The ideal here – the one that CTC hopes to strengthen in communities – is not that every person has exactly the same values or opinions, but that the important adults and institutions in young people’s lives communicate consistent expectations around safety, responsibility, respect, and healthy behavior. If parents and caregivers, teachers, coaches, mentors, and other adults communicate reasonable standards and model them themselves, young people receive a clearer message.
How protective factors work to counter high-risk environments: the Social Development Strategy
Hawkins and Catalano’s Social Development Strategy explains how protective factors can be strengthened.
The Social Development Strategy emphasizes a sequence of opportunities, skills, recognition, bonding, and healthy beliefs and clear standards.
Provide meaningful opportunities. Children and adolescents need developmentally appropriate opportunities to participate actively in their families, schools, peer groups, organizations, and communities.
Build skills. Opportunities are most useful when young people have the skills they need to succeed. These may include social and emotional skills, problem-solving, communication, academic or vocational skills, specialized knowledge, and physical or creative abilities.
Provide recognition. Like anyone else, young people need to know that their effort, improvement, and contributions are valued. Specific and consistent recognition can strengthen their sense of connection to the people and groups around them.
Depending on a child’s age, interests, and abilities, meaningful contributions can range from household responsibilities to participating in a youth organization or serving on a community advisory group. Other examples include tutoring younger students, peer mediation, responsibilities in clubs or faith-based groups, participation in a band or orchestra, helping care for younger family members, volunteering, or working on a community project.
Opportunities, skills, and recognition can strengthen bonding. Making a meaningful contribution to a family, school, organization, or community can help young people develop a stronger sense of attachment and commitment to it.
Bonding increases the influence of healthy beliefs and clear standards. Young people are more likely to take seriously the expectations of people and groups they trust, respect, and feel connected to.
Ultimately, this progression supports healthy behavior. The work of protective factors is demonstrated in the following diagram illustrating the Social Development Strategy:

Why would you want (or not want) to adopt the Communities That Care approach?
As with all the models discussed in this chapter, there are both advantages and potential limitations to using CTC. Some characteristics can be viewed either way, depending on the community and how the process is carried out.
Advantages
- CTC is grounded in prevention science and practice. The ideas underlying CTC – including risk and protective factors – come from prevention research. Communities use local data to select tested and effective programs, policies, and practices that address their priorities.
- CTC can be inclusive and participatory. The planning process is designed to involve people from different sectors of the community in discussion and decision-making, with a community board helping guide implementation and evaluation.
There are real advantages to being inclusive – involving people from different sectors of the community, including young people and others directly affected by the issues – and participatory – engaging people beyond formal leaders in decision-making. First, it taps a broad range of ideas, knowledge, and lived experience, particularly about the history and character of the community and its young people. Second, it helps ensure that decisions are carefully discussed. Perhaps most important, meaningful participation can create community ownership of the final plan. When people have helped shape an effort rather than having it imposed on them, they are more likely to support it and work to make it successful.
- CTC takes a community perspective. Adopting an outlook similar to that of the other models reviewed in this chapter, CTC treats the prevention of health and behavior problems and the healthy development of young people as a community-wide responsibility that calls for a community-wide effort.
- CTC provides training and implementation support. Rather than simply presenting a model or providing an assessment tool, the current CTC PLUS system provides training, coaching, and technical assistance to help communities carry out assessment, planning, implementation, and evaluation.
- CTC emphasizes tested and effective prevention strategies. Instead of requiring communities to design every intervention from scratch, CTC helps them identify programs, policies, and practices with evidence of effectiveness and match them to locally identified needs.
“Tested and effective” does not simply mean that a program is popular or widely used. It means that it has been evaluated rigorously enough to provide evidence that it can improve relevant outcomes.
- CTC is adapted to the needs of each community. Rather than using a completely cookie-cutter approach, CTC uses local risk and protective factor data, existing resources, and community priorities to guide planning and the selection of prevention strategies.
- CTC includes evaluation and adjustment as an integral part of the effort. No program or method is perfect for every community, and no implementation is perfect either. Regular evaluation and adjustment allow communities to learn from results and improve what they are doing.
- CTC has evidence of effectiveness. A community-randomized trial found reductions in several youth health and behavior problems in communities implementing CTC, and follow-up research has found that some benefits continued into adulthood.
Potential limitations
- Participation depends on who is actually included and how power is shared. CTC places substantial responsibility on community leaders and a community board. If those groups do not reflect the people, neighborhoods, and experiences within the larger community – or if a small group controls the decisions – the process may be less inclusive than intended.
Especially in a large or diverse community, identifying appropriate participants takes deliberate outreach. Young people themselves, parents and caregivers, people with lived experience of the issues, residents of different neighborhoods, and groups that have traditionally had less influence in community decision-making may need to be intentionally included. Representation alone is not enough: participants also need a meaningful role in decisions.
- Its emphasis on tested and effective interventions can constrain some choices. Evidence-based programs and policies provide communities with useful options and reduce the need to start entirely from scratch. At the same time, an emphasis on established interventions can make it harder to use a locally developed approach that has not yet been formally evaluated.
This can be a double-edged sword. On one hand, communities benefit from programs and strategies that have worked elsewhere and from clear guidance for implementing them. On the other, communities still need room to use local knowledge, adapt thoughtfully to local circumstances, and recognize approaches that are already working.
- Following an established model can sometimes encourage people merely to follow directions rather than throwing heart and soul into the effort. Even a tested and effective intervention does not automatically produce results simply because all the instructions were followed. Communities still have to examine implementation, local conditions, participation, and whether the selected strategies actually fit the issues they are trying to address.
- CTC has a specific focus. CTC centers on healthy youth development and the prevention of particular adolescent health and behavior problems. This focus can be an advantage because it keeps the effort manageable and measurable. On the other hand, a community seeking a broader framework for all aspects of community health and development may need to use CTC alongside other approaches.
If the ultimate goal is defined only as reducing one particular behavior, there is a danger of assuming that reaching that goal “fixes” the broader problem. Long-term community change may require attention to underlying social, economic, institutional, and environmental conditions as well.
- Research evidence does not guarantee identical results in every community. CTC has substantial research support, including long-term evidence, but outcomes still depend on local conditions, the quality of implementation, sustained community participation, and how well selected strategies match the community’s priorities.
- Formal CTC implementation requires resources. The current CTC PLUS system includes licensing, training, coaching, assessment, and implementation support. These services can strengthen implementation, but communities still need to consider the money, staff time, organizational capacity, and long-term commitment required.
None of these limitations necessarily rules out CTC. They do mean that communities should use the model thoughtfully. You can broaden participation, make sure young people and people with lived experience have real decision-making roles, use local knowledge alongside research evidence, and continually assess whether the process fits your community. No model is sacrosanct, and no model works equally well in every community.
Who should be involved in Communities That Care?
As we’ve just discussed, CTC should be as broad-based as possible. Community leaders – elected officials, business and institutional leaders, and others with influence – are important, but an effort that expects community-wide support should also include the people most affected by the issues and by the decisions being made.
Stakeholders include all who have a meaningful interest in the initiative: people directly affected, supporters, participants, planners, implementers, community partners, and others. Some possibilities include:
- People directly affected by the health and behavior issues. They can bring experience and a deep understanding of the issues and their effects.
- Young people themselves, especially those with lived experience – young people formerly involved in gangs or the justice system, people in recovery from substance use disorders, young people who became parents during adolescence, and those who left school before graduation. They can offer not only personal knowledge but also credibility with other young people. They speak from experience, not simply from an adult position of moral rectitude.
- Families, caregivers, significant others, and friends of people affected by these issues. Their experiences may provide important insight into both challenges and possible solutions.
- People who have been harmed by delinquency or violence involving young people.
- People affected indirectly by the issues. This group may include people with a number of different perspectives.
- Teachers, counselors, coaches, and other school staff.
- People who work in community organizations serving young people – outreach workers, caseworkers, mentors, coaches, youth-group leaders, and others.
- People who respond when serious problems occur – law enforcement officers, health professionals, judges, probation officers, social service staff, and others.
- Business owners, neighborhood organizations, and others concerned about the effects that public substance use, violence, unsafe conditions, or other community problems can have on businesses, public spaces, and neighborhood life.
- Community leaders and decisionmakers. There are both official and unofficial community leaders.
- Official leaders. These include current and former elected and appointed officials.
- Unofficial leaders. This larger group can include opinion leaders, business, institutional, and civic figures, community activists, people who speak for particular neighborhoods or cultural and language communities, labor and workforce representatives, faith leaders, and other community members whom people respect and listen to.
- People with a community interest. These are people who may not be directly affected by a specific problem but care about young people and the community.
- Parents, caregivers, and others who want a supportive environment for young people.
- Business people, community developers, and others concerned about the community as a place to live, work, raise children, or operate a business.
- Community volunteers and other concerned community members.
- The media. Involving media representatives from the beginning – as community members as well as in their professional roles – can help ensure that accurate information about CTC and its activities reaches the larger community.
How do you employ the Communities That Care approach?
Communities That Care has evolved since its early implementation. The current CTC PLUS system is supported by the Center for Communities That Care at the University of Washington and combines prevention science, community assessment, training and coaching, planning tools, selection of tested and effective interventions, and ongoing evaluation.
Communities interested in formal CTC PLUS implementation can work with the Center for Communities That Care for training, coaching, tools, and technical assistance.
The current CTC process is organized into five phases:
Phase 1: Get Started
The first phase involves determining whether the community is ready and able to undertake the process, identifying people and organizations that can help lead and support the effort, and developing an initial understanding of how CTC can address local priorities.
Community readiness still matters. People need to recognize that youth health and behavior issues deserve attention and that prevention is both important and possible. If that understanding is not yet widespread, additional communication and community engagement may be needed before the effort can move forward successfully.
This reflects a broader principle of community change: people are more likely to support action when they understand the issue, believe it matters, believe change is possible, and see a meaningful role for themselves in creating that change. No matter how good your process or proposed intervention, an effort is unlikely to succeed if the larger community has no understanding of or support for it. Sometimes groundwork has to come first.
Phase 2: Get Organized
In this phase, community leaders, organizations, young people, families, and other stakeholders establish or strengthen the community coalition or board that will guide the process. Participants learn about prevention science, the CTC framework, risk and protective factors, and their roles in the effort.
Who participates matters. A board that represents only people who already know and agree with one another may miss important community knowledge and perspectives. Creating a truly inclusive group may require deliberate outreach beyond the networks of the people who first organized the effort.
The Orlando Healthy Community initiative offers a useful example of this issue. An initial group of community leaders developed what it believed was an inclusive list of people to invite. A facilitator pointed out that the list did not come close to representing the full community. To the group’s credit, members went back to square one, researched the community, contacted people they had never worked with before, and eventually created a much broader group.
The lesson applies to CTC as well. A board doesn’t become representative simply because its members come from several organizations. Geography, age, race and ethnicity, socioeconomic circumstances, language, lived experience, and other dimensions of community life may all be relevant. Young people themselves should have meaningful opportunities to participate.
The community board or coalition also works to develop a shared vision for healthy youth development and the community conditions it wants to create.
Phase 3: Develop a Community Profile
Community assessment in CTC involves identifying both risks and strengths. The goal is not simply to catalog problems, but to develop a clear picture of the risk and protective factors affecting young people, the outcomes the community wants to improve, and the programs, policies, organizations, and other resources already available.
Strategies for gathering information may include:
- Youth survey. CTC uses survey data from young people to help identify local patterns of risk and protection and guide prevention priorities.
- Census, demographic, and GIS (Geographic Information Systems) data. These sources can help identify population patterns, changes over time, geographic differences, economic conditions, and other characteristics relevant to community planning.
- Archival and administrative records. Records from schools, public agencies, health organizations, law enforcement, media archives, and other sources can provide information about past and current conditions and previous community efforts.
- Direct engagement with young people and other community members. Focus groups, community forums, interviews, conversations, and other forms of engagement can provide information from people who experience local risks, protective factors, programs, and community conditions firsthand.
Using these sources, the community identifies priority risk and protective factors to address. The point is to focus attention where local data and community knowledge indicate that stronger prevention and protection are most needed.
The community also assesses the resources already available to support the effort:
- Money, including local funders and other funding sources.
- Expertise, including researchers, prevention professionals, community organizations, and people with lived experience working with young people and families.
- People – both paid staff and volunteers – who can provide direct services, outreach, coordination, and other support.
- Ways to reach young people – schools, libraries, community organizations, social and traditional media, sports and recreation programs, outreach programs, families, and other community settings.
- Existing programs, policies, and community strengths that can be strengthened rather than replaced.
Phase 4: Create a Community Action Plan
Planning is where the community decides where to put its efforts, identifies measurable goals and outcomes, and selects strategies to address its priority risk and protective factors.
The community board looks carefully at the factors identified during assessment and at the populations, neighborhoods, schools, or other settings where attention may be most needed. It then establishes clear outcomes for reducing risk, strengthening protection, and improving youth well-being.
CTC emphasizes the use of tested and effective programs, policies, and practices. The community chooses strategies that fit its priorities and existing resources and can work across several areas of young people’s lives – such as family, school, peer, and community settings.
The plan should also establish timelines, responsibilities, ways of measuring progress, and a strategy for sustaining successful efforts over time.
Phase 5: Implement and Evaluate
In this phase, the community puts its action plan into practice. People who will actually implement the selected programs, policies, or practices should be actively involved in planning the details of implementation along with community board members, young people, participants, and other relevant partners.
With CTC, as with any model, the keys to good implementation are thorough and inclusive planning, a carefully structured implementation process – everyone knows what comes when and who is responsible for doing what – and good communication among all parties. If these elements are present, the chances are better that implementation will go smoothly.
That doesn’t guarantee effectiveness, however. Results still depend on whether you’ve chosen strategies that actually address the issues at hand, whether they are implemented well, whether they fit the local context, and whether the people doing the work establish strong relationships with the young people, families, and communities involved.
Evaluation compares what happens with the outcomes and accountability measures established during planning. It should help the community understand where implementation is going well, where results are appearing, where challenges remain, and what adjustments may be necessary.
Evaluation and adjustment are integral parts of the process and should continue throughout the life of the effort. An initiative doesn’t end simply because the community begins to see positive results. If an approach is working, the community has to consider how to sustain it. If results are less positive than hoped, the community needs to examine why and adjust the strategy, implementation, or both.
Even if results are overwhelmingly positive, it’s not time to rest on your laurels. Community conditions change, young people grow up, new groups of children enter adolescence, resources shift, and new challenges emerge. Maintaining progress requires continuing to evaluate, adapt, and strengthen prevention efforts over time.
In Summary
Communities That Care (CTC) is a prevention-planning system that grew out of the work of J. David Hawkins, Richard Catalano, and colleagues at the University of Washington. Based on prevention science, the Social Development Strategy looks at the ways risk and protective factors influence young people’s health and development.
The version of CTC discussed in this section has historically focused on substance use, delinquency, pregnancy among adolescents, leaving school before graduation, and violence. Rather than assuming that these outcomes result simply from individual choices, CTC examines risk and protective factors across community, family, school, and individual/peer contexts.
The Social Development Strategy emphasizes protective processes that can support healthy development. Providing meaningful opportunities, building skills, and recognizing young people’s efforts can strengthen bonding to families, schools, adults, organizations, and communities. Strong positive bonds can, in turn, make healthy beliefs and clear standards more influential.
Advantages of the process include:
- CTC is grounded in prevention science and practice.
- CTC can support inclusive and participatory community planning.
- CTC takes a community perspective.
- CTC provides training, coaching, and implementation support.
- CTC emphasizes tested and effective programs, policies, and practices.
- CTC uses local information to adapt prevention planning to the needs of each community.
- CTC includes evaluation and adjustment as integral parts of the effort.
- CTC has research evidence supporting its effectiveness, including long-term follow-up.
Potential limitations include:
- Participation may not be truly inclusive unless communities deliberately involve a broad range of people and share decision-making power.
- An emphasis on tested and effective interventions can limit the use of locally developed approaches that have not yet been formally evaluated.
- Following an established process can encourage communities merely to follow directions rather than continuously analyze whether the effort fits local conditions.
- CTC is focused specifically on young people and prevention, rather than on every aspect of community health and development.
- Evidence of effectiveness does not guarantee the same results in every community.
- Formal implementation requires resources for training, coaching, assessment, coordination, and sustained community work.
Because broad-based participation is important to a successful effort, CTC should involve stakeholders from throughout the community. This includes young people and families directly affected by the issues and proposed interventions; people who work with young people; people who respond to the consequences of health and behavior problems; community leaders and decisionmakers; other concerned community members; and media and communication partners.
The current CTC PLUS process has five phases:
- Get Started – assess readiness, build initial support, and establish the foundation for the effort.
- Get Organized – develop a representative community coalition or board, build knowledge and skills, and establish a shared vision.
- Develop a Community Profile – use youth survey data, community information, and an assessment of existing programs and resources to identify priority risk and protective factors.
- Create a Community Action Plan – establish measurable outcomes and select tested and effective programs, policies, and practices that fit community priorities.
- Implement and Evaluate – carry out the plan, monitor implementation and outcomes, use data to make adjustments, and sustain effective strategies.
Finally, the process and successful prevention efforts have to be maintained if gains are to continue. Communities change, and prevention is not a one-time undertaking. The long-term goal is to strengthen the conditions that help young people thrive and to keep learning, adapting, and improving as the community changes.
Resources
Online Resources
Channing-Bete, the contractor for providing CTC programs. Information on CTC, background, success stories, publications, etc.
Intensive Aftercare for High-Risk Juveniles: A Community Care Model by Office of Juvenile Justice and Delinquency prevention.
Investing in Your Community’s Youth: An Introduction to The Communities That Care System is a guide that provides an overview for helping communities build positive, healthy futures for their youth.
Lower Dauphin School District (PA). Example of one school district that has adopted a CTC approach. Pennsylvania has recommended adoption to districts statewide, and many Pennsylvania districts have accepted the recommendation.
Information on CTC from the Regional Prevention Center of the Flint Hills (KS).
Southern York County (PA) School District. Another Pennsylvania school district that has adopted CTC. The site includes a history of the development of the process in the district.
Print Resources
Communities That Care Delinquency Prevention Model: A Study in Florida. Research report #72, Florida Dept. of Juvenile Justice. A study trying to determine the effects of risk factors on problem behaviors, and the role of race in those effects.
Hawkins, J., Catalano, R., & Michael W. (2002). Promoting science-based intervention in communities. Addictive Behaviors, vol. 27. pp. 951-976.
Hawkins, J., & Catalano, R. (1992). Communities That Care: Action for Drug Abuse Prevention. San Francisco: Jossey-Bass.
Paglin C. An article on the Portland, OR CTC program from the Winter (1998) issue of Northwest Education Magazine, Communities That Care a quarterly publication of the Northwest Regional Educational Laboratory.
What is Communities That Care?
___Your community focuses on one or more of the five youth problem behaviors:
- Substance use
- Delinquency
- Teen pregnancy
- School drop-out
- Violence
___You attend to all four domains in which risk factors occur:
- Individual/peer
- Family
- School
- Community
___You encourage the three protective factors:
- Individual characteristics
- Bonding
- Healthy beliefs and clear standards
Why would you want (and not want) to adopt the Communities That Care approach?
You use CTC because
___CTC is grounded in theory and practice.
___CTC is inclusive and participatory.
___CTC takes a community perspective.
___CTC involves training at every step.
___CTC provides a menu of best practices to choose from.
___CTC is adapted to the needs of each community.
___CTC includes evaluation and adjustment as an integral part of any effort.
___CTC seems to work for most problem behaviors.
You see disadvantages to CTC in that:
___The CTC approach is only inclusive and participatory for certain people.
___CTC allows the choice of only a finite number of approaches.
___Choosing from among best practices may encourage communities merely to follow directions, rather than throwing heart and soul into the effort.
___CTC is narrowly focused on youth and specific behaviors.
___CTC is, to a certain extent, based on assumptions.
___CTC has a service to sell.
Who should be involved in Communities That Care?
You strive to involve:
___Those most directly affected by the problem behavior(s).
___Those indirectly affected by the problem behavior(s).
___Those who deal with the consequences of the problem behaviors in the community.
___Concerned citizens.
___The media.
How do you employ the Communities That Care approach?
___You gauge the awareness of the community.
___You provide community education about the problem behaviors.
___You mobilize the community, starting with key leaders (or a more inclusive group) and a community board.
___You conduct an assessment of community needs and resources.
___You create a strategic plan for the initiative, choosing from among best practices in the areas of family, school, and community.
___You implement your plan.
___You evaluate the process and outcomes of your intervention, and adjust it accordingly.
___You maintain your gains, and continue your efforts over time.

Often, community members are expected to respond immediately to new projects and community change without adequate time to adjust to new ideas or gain the knowledge needed to fully understand them. This section is about how to understand and measure how ready a community is to address a particular issue, and how to use that knowledge to support community change.
What is community readiness?
Community readiness is the degree to which a community is ready to take action on an issue. That readiness can range from none at all – the issue may not yet be recognized in the community – to having established efforts in place and making progress. Community readiness has some specific characteristics that are important for community builders to understand:
- Community readiness is issue-specific. A community can be highly ready to address one issue while being at the earliest stages of readiness in relation to another. Readiness can also be assessed across multiple dimensions. We’ll discuss those dimensions in the next part of this section.
- Community readiness can vary across dimensions. A community may be more ready to address an issue in some ways than in others. It may know a great deal about the issue and recognize it as a concern, for instance, but have little experience with possible ways of addressing it.
- Community readiness can vary across different segments of the community. Some groups – those directly affected by the issue, for example – may be far more ready to address it than others. As we’ll see, there are ways to help move communities toward higher levels of readiness.
- Understanding community readiness is essential for addressing an issue. You can easily undermine an effort by trying to push a community into something it isn’t ready for. People are more likely to support what they see as reasonable, logical, and doable. You may be proposing something that is all of those, but if the community sees it differently, the effort is unlikely to be successful.
An understanding of community readiness allows you to tailor an intervention or strategy to what the community is prepared to consider, accept, and support. By taking small steps forward – by setting goals that require people to stretch, but not so far beyond their current knowledge, experience, or willingness that the effort becomes unrealistic – you can make steady progress.
What is the community readiness model?
The Tri-Ethnic Center for Prevention Research at Colorado State University developed the Community Readiness Model to identify dimensions and levels of community readiness. The model also includes an instrument for assessing readiness that can be administered and scored by community members. We’ll include the instrument and instructions for scoring it in the “How to” part of this section.
Dimensions of community readiness
Dimensions of readiness are key factors that influence a community’s preparedness to take action on an issue. The six dimensions used in this version of the model are:
- Community efforts. To what extent are there existing efforts, programs, activities, or policies that address the issue?
- Community knowledge of the efforts. To what extent do community members know about existing local efforts and their effectiveness? Are the efforts accessible to different segments of the community?
- Leadership. To what extent are formal leaders and other influential community members supportive of addressing the issue?
- Community climate. What is the prevailing attitude of the community toward the issue? Do community members generally feel that change is possible and that they can play a role in it?
- Community knowledge about the issue. To what extent do community members understand the issue, its causes and consequences, and how it affects their community?
- Resources related to the issue. To what extent are local resources – people, time, money, space, expertise, and other support – available for efforts to address the issue?
Your community’s status with respect to each of these dimensions forms the basis of its overall level of readiness. Remember that readiness can vary – sometimes widely – across dimensions. For example, community efforts may be well developed while resources remain limited. The community’s level of readiness for one issue also doesn’t necessarily correspond to its readiness for another, because readiness is issue-specific.
Community readiness can be described by nine different levels:
- No Awareness. The issue is not generally recognized by the community or its leaders as a concern.
- Denial/Resistance. At least some community members recognize the issue as a concern, but there is little recognition that it may be occurring locally.
- Vague Awareness. Most people recognize that there is a local concern, but there is little immediate motivation to do anything about it.
- Preplanning. There is clear recognition that something should be done, and there may already be a group addressing the issue. However, efforts are not yet focused or detailed.
- Preparation. Active leaders begin planning in earnest. The community offers modest support for their efforts.
- Initiation. Enough information is available to justify action, and activities are underway.
- Stabilization. Activities are supported by administrators or community decisionmakers. Staff and participants have gained experience in carrying out the effort.
- Confirmation/Expansion. Efforts are established. Community members feel comfortable using or participating in them and support expanding them. Local data are collected regularly.
- High Level of Community Ownership. Detailed knowledge exists about the issue, its prevalence, causes, and consequences. Evaluation guides new directions, and the community uses what it has learned to address additional issues.
Once you know your community’s level of readiness, you can plan your effort to begin at that level and work toward the next. Over time, the community can continue moving forward one level at a time.
Why use the community readiness model?
- It conserves valuable resources – time, money, and people – by guiding the selection of strategies that are more likely to succeed. Rather than spinning your wheels trying to get the community to do something it isn’t ready for, you – and the community – can start where things actually stand.
- It is an accessible and relatively inexpensive tool. Community members can be trained to administer and score the assessment without having to rely entirely on outside professionals.
- It promotes community recognition and ownership of the issue. Because it can be used by community members and takes local perspectives into account, the model can help people understand an issue and its effects in their own community.
- Community ownership can help strategies remain culturally responsive, locally appropriate, and sustainable.
- It encourages the use of local knowledge and resources rather than unnecessary reliance on outside expertise. Local experts may include professionals, but they may also be community members whose lived experience and knowledge give them a strong understanding of what is happening locally.
- The process of community change can be complex and challenging, but the model breaks it into manageable steps. Moving from little readiness to the highest level is a large undertaking. Moving from one readiness stage to the next is easier to understand and plan for.
- It helps create a community vision for healthy change. The levels of readiness also describe, to some extent, how a community develops its capacity to recognize, address, evaluate, and sustain work on important issues.
When should you use the community readiness model?
The nature of the model makes it useful in many situations where a community issue needs to be addressed, but there are some times when it can be particularly useful.
- In the course of an ongoing effort. If your effort is successful, the community may move forward not only in addressing the issue, but also in its readiness. To make sure the work continues to involve tasks and goals that community members can accept and accomplish, it’s important to monitor readiness and adjust your strategy accordingly.
- Each time you tackle a new issue. Because readiness is issue-specific, it’s important to understand where the community stands on each issue you address. Successful work on one issue may leave people more prepared to address another, but you shouldn’t assume that it automatically will.
- When several different communities, or different segments of one community, are involved. Groups within a community may be at very different places on the readiness scale. You may need somewhat different strategies for different groups in order to mount a successful effort.
- When you’re planning an effort that involves a participatory process. What level of participation can you expect at the beginning? Where should you start in order to have a reasonable possibility of success? Applying the model can help answer these and similar questions.
- When you’re engaged in a community or neighborhood planning effort. Many such efforts begin by assuming that everyone is at roughly the same readiness level. Looking carefully at where different parts of the community are actually starting may help broaden participation and make the planning process more effective.
Who should be involved in using the community readiness model?
In any use of the model, there are really two groups whose involvement is important: those who will apply and administer the model and assessment, and those who will be interviewed when the assessment is conducted.
- Who should consider using the model and/or administering the assessment?
- Policymakers and planners. These are often the people with the authority or resources to act, but community readiness can easily be overlooked when proposed solutions are developed.
- Community activists and organizers. Many organizers already understand that successful change depends on where a community is starting. An assessment can add systematic information to what organizers learn through experience and relationships.
- Health and human service organizations. These organizations often help initiate efforts addressing such issues as hunger, homelessness, HIV/AIDS, mental health, and substance use. Knowing where to begin can be crucial to success.
- Coalitions. Understanding readiness in relation to their issue can help coalitions decide how to plan, communicate, and organize.
- Anyone else interested in community or social change. Simply understanding the concept can be valuable in community work of many kinds.
- Who should be interviewed when the model is being applied? To some extent, the answer depends on the issue. If the issue directly concerns young people – violence involving young people or pregnancies among adolescents, for example – young people should be among those consulted. The same principle applies to other groups directly affected by an issue, such as older adults living alone, people from particular racial, ethnic, or cultural communities, people with particular health conditions, or people experiencing economic barriers. Some general possibilities include:
- Schools and universities
- Municipal, county, or tribal government
- Law enforcement
- Health and medical professionals
- Social service organizations
- Mental health and treatment services
- Faith and spiritual communities
- Community members broadly
- Young people
- People living on limited or fixed incomes, including people receiving Social Security or disability benefits
How do you use the community readiness model?
The model relies on the Community Readiness Assessment.
The Community Readiness Assessment
In the version presented here, the assessment is conducted through an interview that generally takes 30-60 minutes. The questions are divided into sections addressing the dimensions of readiness. Some questions are needed for scoring, while others may be adapted to the issue being studied, as long as the meaning needed for scoring is preserved.
Community Readiness Assessment Interview Questions
A. Community efforts (programs, activities, policies, etc.)
B. Community knowledge of efforts
- Using a scale from 1-10, how much of a concern is this issue in your community, with 1 being “not at all” and 10 being “a very great concern”? Please explain. (This number is used only as a reference point and is not included in scoring this dimension.)
- Please describe the efforts available in your community to address this issue. (A)
- How long have these efforts been going on in your community? (A)
- Using a scale from 1-10, how aware are people in your community of these efforts, with 1 being “no awareness” and 10 being “very aware”? Please explain. (This number is used only as a reference point and is not included in scoring this dimension.) (B)
- What does the community know about these efforts or activities? (B)
- What are the strengths of these efforts? (B)
- What are the weaknesses or limitations of these efforts? (B)
- Who do these programs serve? For example, are they intended for people of particular ages or other groups within the community? (A)
- Are there segments of the community for whom these efforts or services may be less accessible? For example, consider age, race or ethnicity, income, language, disability, geography, transportation, or other relevant factors. (A)
- Is there a need to expand these efforts or services? If not, why not? (A)
- Is there any planning for additional efforts or services related to this issue going on in your community? If yes, please explain. (A)
- What formal or informal policies, practices, and laws related to this issue are in place in your community, and for how long? (A)
- Are there segments of the community for whom these policies, practices, and laws are applied differently or may have different effects? Please explain. (A)
- Is there a need to expand or change these policies, practices, or laws? If so, are there plans to do so? Please explain. (A)
- How does the community view these policies, practices, and laws? (A)
C. Leadership
- Who are the leaders or influential people specific to this issue in your community?
- Using a scale from 1-10, how much of a concern is this issue to community leadership, with 1 being “not at all” and 10 being “of great concern”? Please explain. (This number is used only as a reference point and is not included in scoring.)
- How are these leaders involved in efforts related to the issue? Please explain.
- Would community leadership support additional efforts? Please explain.
D. Community climate
- Describe the community.
- Are there circumstances in which members of your community might think this issue should be accepted or tolerated? Please explain.
- How does the community support efforts to address this issue?
- What are the primary barriers to efforts addressing this issue in your community?
- Based on the answers you have provided so far, what do you think is the overall feeling among community members regarding this issue?
E. Knowledge about the issue
- How knowledgeable are community members about this issue? Please explain. For example, consider causes, dynamics, signs, symptoms where relevant, local data, and effects on individuals, families, and the community.
- What types of information are available in your community regarding this issue?
- What local data are available on this issue in your community?
- How do people obtain this information in your community?
F. Resources for efforts related to the issue (time, money, people, space, expertise, etc.)
- Where would a person affected by this issue be most likely to turn first for help in your community? Why?
- On a scale from 1-10, what is the level of expertise and training among those working on this issue, with 1 being “very low” and 10 being “very high”? Please explain. (This number is used only as a reference point and is not included in scoring.)
- Do efforts addressing this issue have a broad base of volunteers or other community participants?
- What is the attitude of community members and local businesses toward supporting efforts through volunteering, financial contributions, space, or other resources?
- How are current efforts funded? Please explain.
- Are you aware of proposals or action plans that have been submitted for funding to address this issue in your community? If yes, please explain.
- Are efforts currently being evaluated? If yes, how developed is the evaluation process?
- Are evaluation findings being used to change existing programs, activities, or policies or to develop new ones?
There are two questions to be answered here:
- How do you administer and score the Community Readiness Assessment?
- How do you use community readiness information?
How do you administer and score the Community Readiness Assessment?
- Choose and train interviewers. You’ll probably do best with people who are good interviewers and/or community members who are trusted by the people they’ll be interviewing. Ideally, you can find interviewers who fit both descriptions. They don’t have to be professionals, but they should be comfortable with others, able to think on their feet, and understand how to put people at ease and gather information from them. Interviewers should also understand the community readiness model well enough to know when clarification or additional detail is needed.
- Choose and train scorers. Because the assessment uses a specific scoring process, scorers need to understand both the scoring procedure and the community readiness model.
- Revise the assessment tool, if necessary, to reflect the issue you’re concerned with. Some wording may need to be adjusted so that the questions make sense for your particular issue, while retaining the meaning required for scoring.
Community Readiness: A Handbook for Successful Change emphasizes that adaptations to the questions should be made carefully because the questions are closely connected to the scoring process. In most cases, the specific issue can simply be substituted for the phrase “this issue.” Questions that are required for scoring should be retained, and any additional questions should be added in a way that does not interfere with scoring.
If questions are translated into another language, the handbook recommends using people familiar with both the language and cultural context and checking the translated version to make sure the original meaning has been retained.
Pilot test revised questions to make sure they are understandable and provide the information needed for scoring each dimension.
- Select people to interview who know the community well. They should reflect a range of perspectives, particularly those of people directly or indirectly affected by the issue.
- Contact the people you have identified and ask whether they are willing to discuss the issue. Allow enough time for thoughtful responses.
- Conduct your interviews. Avoid debating the issue with interviewees, but ask for clarification when needed and use prompts as appropriate. Record responses as accurately as possible, without adding your own interpretation or assuming what the interviewee meant.
- Score the interviews. Determine scores for each readiness dimension and an overall readiness score.
Scoring the instrument
Scoring is a step-by-step process that produces a readiness score for each dimension. Ideally, two people participate in scoring qualitative interview data.
- Working independently, both scorers should read each interview in its entirety before scoring individual dimensions so that they have an overall sense of the interview.
- Each scorer then compares the interview with the anchored rating scale for each dimension, beginning with the lowest stage and moving upward. To assign a particular stage, the evidence needed for the earlier stages should also be present.
- Each scorer records an independent score for every dimension in every interview.
- The scorers then meet, compare their ratings, discuss differences, and reach a combined score based on the evidence in the interviews.
- To calculate the score for a dimension, add the combined scores for that dimension and divide by the number of interviews.
- To calculate the overall readiness score, add the calculated dimension scores and divide by the number of dimensions.
Scores correspond with the numbered stages of readiness. Record any important observations or qualifications that help explain the scores; the numbers are most useful when considered alongside what interviewees actually said.
How do you use community readiness information? With the information you’ve gathered about the individual dimensions and overall readiness, you can begin developing strategies appropriate to your community. Ideally, this should happen through a participatory planning process that includes people interviewed for the assessment as well as others representing different parts of the community and groups affected by the issue.
First, look at the distribution of scores across the dimensions. Are they all about the same? Are some noticeably lower than others?
Readiness may differ across dimensions, and lower-scoring dimensions may require particular attention.
If one or more dimensions score lower than the others, consider strategies that strengthen readiness in those areas. The intensity and expectations of your strategies should fit where the community currently is rather than assuming that every dimension is equally developed.
To be successful, efforts toward community change should begin with strategies appropriate to the community’s current stage of readiness.
Goals and General Strategies Appropriate for Each Stage
- No Awareness. Here, your goal is to raise awareness that the issue exists.
- Make one-on-one contact with community leaders and other community members.
- Visit existing small groups and organizations to share information about the issue.
- Reach out directly to potential supporters.
- Use local media and community communication channels to explain or call attention to the issue.
- Denial/Resistance. The goal at this level is to increase recognition that the issue exists locally.
- Continue one-on-one conversations and encourage people you’ve spoken with to help.
- Discuss local examples and data related to the issue.
- Engage local education, health, and outreach programs to help share accessible information.
- Draw attention to local news and community information related to the issue.
- Share information through local media and community communication channels about the issue’s local effects.
- Provide information through faith communities, neighborhood organizations, clubs, community newsletters, and similar channels.
- Present information to relevant community groups.
- Vague Awareness. Now that people recognize the concern, the next goal is to strengthen understanding that the community can do something about it.
- Present information at community events and to groups that may not yet be directly involved with the issue.
- Use posters, flyers, digital communication, and other public information methods.
- Organize informal community events and use them as opportunities for discussion.
- Conduct informal surveys, interviews, and conversations with community members.
- Publish or share general information about the issue and its local implications.
- Preplanning. At this level, people are ready to begin thinking seriously about how the issue might be addressed.
- Continue providing information about the issue through presentations and communication channels.
- Meet with community leaders and other influential people to build support.
- Review existing community efforts to understand whom they reach, what they do, and what is known about their effectiveness.
- Conduct local focus groups to discuss the issue and possible strategies.
- Increase communication and public awareness through appropriate local media and community channels.
- Preparation. Here, the goal is to gather the information and support needed for detailed planning.
- Conduct appropriate school or youth surveys when the issue directly concerns young people.
- Conduct community surveys or other forms of assessment.
- Hold community events to build awareness and participation in the effort.
- Conduct public forums to develop strategies through grassroots participation.
- Invite community leaders, people with lived experience, and other trusted voices to speak with groups and through local media.
- Plan how you will evaluate the effort.
- Initiation. As a more substantial community effort gets underway, provide community-specific information and support for new and existing activities.
- Provide training on community readiness and the issue for professionals, paraprofessionals, volunteers, and other participants as appropriate.
- Plan communication efforts associated with the start of activities.
- Attend community meetings and provide updates on progress.
- Interview participants and people using services to identify gaps, improve existing efforts, and determine where information should be shared.
- Search for additional resources and potential funding.
- Begin basic evaluation activities.
- Stabilization. Now that efforts are underway, the goal is to stabilize and support them so that the overall community effort can continue.
- Plan community events to maintain involvement and support.
- Provide continued training for professionals and other people involved in the work.
- Provide training and information for community members and explain how the effort will be evaluated.
- Hold regular meetings to review progress and modify strategies where needed.
- Recognize the contributions of local supporters, participants, and volunteers.
- Share progress and future plans through community communication channels.
- Strengthen coordination among service providers, community organizations, and other systems.
- Confirmation/Expansion. Once efforts are established, the task is to strengthen and expand them based on experience and data.
- Formalize collaboration and service agreements where useful.
- Prepare a community assessment or profile relevant to the issue.
- Develop and maintain accessible information about available community programs and services.
- Maintain useful community data and make appropriate information available to the public.
- Develop local speakers or community ambassadors and support appropriate policy change where needed.
- Share specific data trends and findings with the community.
- Use evaluation findings to improve or modify efforts.
- High Level of Community Ownership. At the highest level, the challenge is to sustain progress while continuing to learn and improve. Community members have ownership of the effort and take responsibility for maintaining and strengthening it.
- Maintain support from local businesses and other community partners.
- Diversify funding and other resources.
- Continue advanced training and professional development where appropriate.
- Continue reassessing the issue and the progress being made.
- Use evaluation and outside feedback when useful to improve programs and strategies.
- Track outcome data for planning, accountability, and future funding.
- Continue sharing progress with community members, leaders, participants, partners, and funders.
In Summary
Understanding community readiness – how prepared a community is to address a particular issue – is an important tool for anyone concerned with health and community development. An effort is unlikely to gain support if people do not yet recognize that the issue exists locally, understand why it matters, or believe that meaningful action is possible.
The Community Readiness Model provides a structured way to understand where a community currently stands. Community builders can then use that information to develop strategies that fit the community’s current readiness while helping it move toward the next stage.
The model provides an accessible way of assessing readiness on a particular issue. Because community members themselves can participate in the assessment and planning process, the approach can draw on local expertise and assets rather than relying only on outside professionals. That participation can strengthen community ownership and support steady progress over time.
Community readiness can be described by nine different levels:
- No Awareness. The issue is not generally recognized by the community or its leaders as a concern.
- Denial/Resistance. At least some community members recognize the issue as a concern, but there is little recognition that it may be occurring locally.
- Vague Awareness. Most people recognize a local concern, but there is little immediate motivation to act.
- Preplanning. There is clear recognition that something should be done, but efforts are not yet focused or detailed.
- Preparation. Active planning is underway, with modest community support.
- Initiation. Activities are underway and enough information is available to support action.
- Stabilization. Efforts have become established and are supported by community organizations or decisionmakers.
- Confirmation/Expansion. Established efforts are supported, evaluated, and expanded as appropriate.
- High Level of Community Ownership. The community has substantial knowledge, uses evaluation to guide decisions, and takes responsibility for sustaining and extending the work.
Resources
Online Resources
Assessing Community Needs and Readiness is a toolkit for working with communities on ATOD (alcohol, tobacco and other drug prevention).
Chapter 11: Community Interventions in the "Introduction to Community Psychology" explains professionally-led versus grassroots interventions, what it means for a community intervention to be effective, why a community needs to be ready for an intervention, and the steps to implementing community interventions.
Community Readiness, from the Tri-Ethnic Center for Prevention Research, is a worksheet primer consisting of interview questions that serve as a handbook for using the Community Readiness Model.
Community Readiness: A Handbook for Successful Change (PDF)
Community Readiness Manual: Assessing Community Readiness for Change; Increasing Community Capacity for HIV/AIDS Prevention; Creating a climate that makes healthy change possible.
The Community Readiness Model: Research to Practice by Ruth W. Edwards, Pamela Jumper-Thurman, Barbara A. Plested, E.R. Oetting, and Louis Swanson (2000). Journal of Community Psychology, 28(3), 291-307.
The Tri-Ethnic Center for Prevention Research, Colorado State University.
Print Resource
"Community Readiness: A Promising Model for Community Healing.”
A Native American Topic-Specific Monograph from the Center on Child Abuse and Neglect at the University of Oklahoma Health Science Center.
What is community readiness?
___Community readiness is the degree to which a community is ready to take action on an issue.
Community readiness is:
___Issue-specific.
___Measurable.
___Measurable across multiple dimensions.
___Variable across dimensions.
___Variable across different segments of the community.
___Able to be increased successfully.
___Is essential knowledge for addressing an issue.
What is the community readiness model?
___The community readiness model has six dimensions and nine levels.
Dimensions of community readiness:
___Community efforts.
___Community knowledge of the efforts.
___Leadership.
___Community climate.
___Community knowledge about the issue.
___Resources related to the issue.
Levels of community readiness:
___No awareness.
___Denial/Resistance.
___Vague awareness.
___Pre-planning.
___Preparation.
___Initiation.
___Stabilization.
___Confirmation/Expansion.
___High level of community ownership.
Why use the community readiness model?
___It conserves valuable resources (time, money, people) by guiding the selection of strategies that are most likely to be successful.
___It is an efficient, inexpensive, and easy-to-use tool.
___It promotes community recognition and ownership of the issue.
___Because of strong community ownership, it helps to assure that strategies are culturally congruent and sustainable.
___It encourages the use of local experts and resources instead of reliance on outside experts and resources.
___The process of community change can be complex and challenging, but the model breaks down the process into a series of manageable steps.
___It creates a community vision for healthy change
When should you use the community readiness model?
___In the course of an ongoing effort.
___Each time you tackle a new issue.
___When several different communities, or different segments of the community, are involved.
___When you’re planning an effort that involves a participatory process.
___When you’re engaged in a community or neighborhood planning effort.
Who should be involved in using the community readiness model?
___Who should consider using the model and/or administering the assessment?
- Policymakers and planners.
- Community activists.
- Health and human service organizations.
- Coalitions.
- Anyone else interested in community or social change.
___Who should be surveyed when the model is being applied?
- Schools/Universities
- Municipal/county/tribal government
- Law enforcement
- Health & medical professions
- Social services
- Mental health & treatment services
- Clergy or spiritual community
- Community at large
- Youth
- People on fixed incomes
How do you use the community readiness model?
Administering and scoring the community readiness assessment:
___Choose and train interviewers.
___Choose and train scorers.
___Revise the assessment tool, if necessary, to reflect the issue you’re concerned with.
___Select four to ten people to interview.
___Contact the people you have identified and see if they would be willing to discuss the issue.
___Conduct your interviews.
___Score the interviews.
Using community readiness information:
___Initiate a participatory planning process, if possible.
___To move ahead, readiness on all dimensions must be at about the same level.
___Begin with strategies appropriate to the community’s stage of readiness.
___Stick to it – the job’s never really done.
Example #1 - Preventing Suicide in Native Alaskan Communities
After hearing about the model at a conference, a Native Alaskan woman came to the Center seeking help. In her village of 600 people, there had been 18 suicides in the previous six months. She requested that the team go to her community and help them to use the Community Readiness Model. Because of the urgency of the situation, and with the financial support of the Colorado Injury Control Research Center at Colorado State University, Tri-Ethnic Center staff members traveled to the remote village. The staff were expecting no more than 15-20 people from the village to attend, but were very moved when they were greeted by almost 100 Native people, young and old, from six different villages. Many people had overcome great challenges to come to the meeting. Between villages, there are no roads, and the only way in is by flying in small airplanes or by barging down the river if it isn’t frozen. Once visitors arrive, there are no hotels, so visitors must find a family that is willing to take them in. Despite these difficulties, people found a way to be there.
Initially, community members spoke of their grief and helplessness in the face of the pain of their losses. The model was presented, and participants divided into village groups. The members of each group used the model to assess their village’s stage of readiness and to identify their strengths and resources. An outsider might think that these small villages had very little in the way of resources (no clinics, shelters, etc.). But the village groups recognized many resources – human resources to cultural resources. They later talked about how grateful they were to rediscover those strengths because they had forgotten them in their grief, or because they hadn’t really recognized them as strengths.
Community members offered their time, their creativity, and their knowledge of the culture. The youth formed their own group to develop strategies to offer support to friends in school. Elders lined the outer walls of the community center. Most couldn’t hear what was going on and some were blind, yet they stayed from eight in the morning until eleven at night to offer their support. At the conclusion, the groups from each village summarized the strategies they had developed. Finally, the entire group formed a circle and again, using the model, worked together to brainstorm an action plan to maintain inter-village communication and support.
They indicated that for the first time in a long time, the communities felt hope and empowerment. A woman from the state office who had attended the gathering was so impressed by the efforts that she offered each of the six villages $2,000 to begin working on their strategies. Another woman donated her 80 acres of allotment land for a treatment center. The group was so motivated that they were able to move from a lower to a higher stage of readiness in only two days. The villages continue to work toward their goals, and their strategies have been remarkably successful. From having experienced 18 suicides in a six-month period before the training, they did not lose a single person to suicide in the three years following the training and the suicide rate has continued to be very low.
Example #2 - Tai Chi in the Parks
This section was developed by combining portions of participatory evaluation materials provided by the Area of Sustainable Development and Environmental Health of the Pan American Health Organization.
Background
The “Tai Chi in the Parks” initiative was implemented in the 1990s as a public health strategy in the municipality of Miraflores in Lima, Peru. Today, the “Tai Chi in the Parks” Association is responsible for the maintenance, improvement and advancement of the initiative along with Tai Chi Clubs and more than 20,000 elderly people who practice Tai Chi in the municipality.
The mission of the “Tai Chi in the Parks” program was to transform Miraflores into the municipality with the healthiest and most active elderly population in Peru, thereby, promoting healthy aging of the population.
The initiative’s main objectives were to:
- Incorporate the practice of Tai Chi and its philosophy as a daily, voluntary and accessible habit in the life of Miraflores’ elderly population.
- Achieve physical, psychological, social and spiritual development of Miraflores’ elderly population through the practice of Tai Chi.
To reach its objectives, the program aimed to achieve the following goals:
- Increase the number of elders practicing Tai Chi up to 25,000.
- Multiply the effects of the initiative in other parks and share the experience with other municipalities.
- Maintain support by the Ministry of Health and the Peruvian Sports Institute.
- Secure financing to expand the program to Lima’s underserved communities.
- Disseminate program results among health workers to improve collaboration in the construction of a primary care system for the elderly based on health promotion.
Activities of the Tai Chi in the Parks initiative include:
- Tai Chi classes offered weekdays in various parks in Miraflores.
- Support the formation of Tai Chi clubs, which are informal Tai Chi groups, and the development of a “Tai Chi in the Parks” network.
- Organize gatherings such as the “Tai Chi Convention” organized by the Peruvian Sports Institute.
- Promote community activities such as festivals, Tai Chi championships, conferences, etc., jointly organized by the Miraflores municipality and the Peruvian Sports Institute.
- Train community elderly to become Tai Chi instructors and therefore increase human resources necessary to expand the program.
- Hold capacity-building workshops with other municipalities to share the experience.
- Prepare and publish promotional material.
Preparation
After years of implementing the Tai Chi in the Parks Initiative, partners decided it was time to engage in a participatory evaluation process. An Evaluation Subcommittee was formed with 15 members that represented the following sectors and institutions
- Tai Chi in the Parks Association
- Tai Chi in the Parks Network
- Peruvian Federation of Kung Fu
- Peruvian Sports Institute
- Miraflores’ Health Department
- Local universities
- Mayor’s office
- Miraflores’ Elderly Program
- Ministry of Health and Ministry of Women and Social Development
- NGO EsSalud
- Tai Chi Clubs formed by elderly who practice Tai Chi
- PAHO/WHO
- Network of groups working on elderly health in Miraflores
By engaging in the preparation process, the group was able to identify potential problems for their joint work, as well as facilitating factors.
Potential barriers included:
- Different interests and agendas from each of the institutions and sectors represented.
- Lack of coordination of sectors and activities
- Lack of public policies geared toward the elderly
Among the factors facilitating the group’s work, the following were identified:
- Existence of a “House of the Elderly” that belongs to the municipality and that offered its premises for the meetings of the group.
- The presence of representatives from the program’s users.
- Commitment to community participation by local authorities.
- Presence of Tai Chi instructors that enjoyed great acceptability by the community.
Defining Evaluation Questions in Miraflores
The main interest of the Evaluation Subcommittee was to understand what influence the initiative had on the wellbeing of Miraflores’ elderly population. This interest was based on the fact that the Tai Chi in the Parks Program had a positive unexpected outcome: it had become one of the most popular physical exercise and social interaction programs in the municipality and, as a result, it had been implemented in another 15 municipalities through the Peruvian Sports Institute. After discussion, the Evaluation Subcommittee came up with the following evaluation questions:
- What has been the contribution of each stakeholder sector
- What factors have facilitated or hindered the participation of each sector (i.e. competing interests; creation of Tai Chi clubs managed by program users, etc.)?
- What is the impact of the Tai Chi in the Parks program on:
- Promoting social integration of the elderly?
- Improving the health of the elderly population?
Evaluation Questions selected in Miraflores
The Miraflores’ Evaluation Subcommittee decided to focus its efforts on answering the following evaluation questions:
What is the impact of the Tai Chi in the Parks program on:
- Promoting social integration of the elderly?
- Improving the health of the elderly population?
Documenting Information
To document health improvements among those participating in the Tai Chi in the Parks program, the Evaluation Subcommittee will use various sources of information. For example, it will interview participants (participants are the source of this information) and review program attendance sheets (sheets are the source of information).
- Qualitative information helps to understand the meaning of an initiative and its effects from the community’s standpoint (i.e. the community feels that the initiative is improving its quality of life).
- Qualitative information can provide rich descriptions about activities, context and behaviors and are usually collected by reviewing documents, observations, and interviews.
- It can also be expressed in numbers or quantified. For example, interview responses can be added up to report how many people responded in a certain way, for example, how many participants reported feeling healthier after enrolling in the Tai Chi program.
- Similarly, an observer can report how many people out of a group engaged in a particular behavior, for example, how many people who were present at the Tai Chi classes actually performed the exercises as opposed to just observing his or her classmates doing the exercises.
- Quantitative information is measured and expressed with amounts or quantities (i.e. attendance records of elderly participating in Tai Chi classes, number of participants who were trained to be Tai Chi instructors, etc.)
Interpret Results
The Evaluation Subcommittee wanted to know if the elderly population of Miraflores had been empowered through participation in the Tai Chi in the Parks Program. In order to find out, they interviewed program participants, their family members, Tai Chi instructors, and members of the municipality’s Elderly Program. They also observed the Tai Chi classes and meetings of the Miraflores Elderly Program.
The results showed that:
- A large number of elderly people, who had a low level of physical activity before the program, reported they are now exercising and are physically active.
- Many are actively involved in Tai Chi clubs and are in training to become Tai Chi instructors themselves.
- Family members report the elderly are more assertive and less dependent on them to care for their daily needs.
- Some program participants have joined committees that implement programs for the elderly in Miraflores.
- However, even though they are physically present at the meetings of the Miraflores Elderly Program they rarely participate or express their opinions.
Questions Asked Based on Results
- What do these results mean?
- How can the Evaluation Subcommittee interpret this data?
- What do these results say about goal of ‘empowering elderly people’ through the practice of Tai Chi?
Defining Audiences
The Evaluation Subcommittee decided that the results demonstrating the benefits of the Tai Chi in the Parks Program should be disseminated to various groups in order to encourage more elderly to join the Program and bring new partners into the process. Audiences included the elderly, with a focus on men and low-income groups; their family members, neighbourhood networks and associations; Tai Chi instructors; health professionals; municipal staff; NGOs and funders.
Defining key messages to target audiences
One of the target audiences for the evaluation results was the elderly population of Miraflores. The goal of sharing the evaluation results with this group was to promote the idea of Tai Chi as a health promotion strategy and to encourage more people to participate in the program, particularly men and those with low-income.
Some of the key messages developed for this communication strategy included:
- Tai Chi is the exercise most practiced by Lima’s elderly population.
- The practice of Tai Chi can help you better manage your blood pressure, prevent depression and improve your health in general.
- (for men) Tai Chi is closely related to martial arts and is a very popular sport among Asian men.
- (for low-income populations) Tai Chi can be practiced by everyone since it does not require special equipment and it does not cost anything.
The results of the evaluation were presented, and the focus was put on the evaluation committee collaboration: what it achieved, how it worked, what were the constraints and the possibilities of such strategy, etc.
Action Based on Evaluation Results
Evaluation question: What is the impact of the Tai Chi in the Parks Program in improving the health of Miraflores’ elderly population?
Information collected: The information collected shows that the practice of Tai Chi could improve health: participants showed lower blood pressure and decreased levels of depression after one year of practice. However, the majority of the participants were women from mid to high income levels.
Interpretation: The initiative was successful in improving health in the elderly population, however it reached more women and those in the mid to higher-income sections of the population.
Recommendation: Expand the initiative but review efforts to encourage men and low-income people to join the program. Action:
- Schedule a meeting of the evaluation committee and organizations working in low-income areas of the municipality to discuss how to better promote the initiative.
- Incorporate Kung Fu and other martial arts demonstrations into presentations given by the Tai Chi clubs to encourage more men to join the program.
- Prepare and distribute a report to health centers, NGOs and institutions working on issues related to elderly health.
Tool 1: IPFS Tri-Ethnic Community Readiness Assessment Process
The Tri-Ethnic Community Readiness Assessment (.docx), developed by the Van Buren County Safe Coalition, is a meticulously structured process designed to evaluate a community's preparedness to tackle specific issues, particularly underage and binge drinking among youth. The primary objective is to align interventions with the community's current level of readiness, ensuring their effectiveness.
This assessment utilizes survey interviews conducted with at least six individuals, each representing diverse community sectors such as education, law enforcement, healthcare, clergy, and youth. This comprehensive approach guarantees that a variety of perspectives are taken into account.
The survey comprises questions that span six dimensions: Knowledge of the Issue, Community Efforts, Community Knowledge of Efforts, Leadership, Community Climate, and Resources for Prevention. The scores from the interviews and dimensions are averaged to ascertain the community's overall readiness stage, which ranges from 1 (No Awareness) to 9 (High Level of Community Ownership).
Nearly every community – large or small, urban, suburban, or rural – must cope, to some extent, with substance use, substance misuse, and substance use disorders involving alcohol, tobacco and nicotine products, and other drugs. Most communities try to address these problems, and some are reasonably successful. Others find themselves doing everything they can think of and barely staying even, or – worse – losing ground.
The difference is sometimes in the way they approach the problem. Those that are most successful often try to prevent problems before they start or become more serious. They focus on the community as a whole and try to devise ways to help community members experiencing increased risk – often including young people – avoid behaviors, conditions, or situations that could put them in harm’s way. Although they don’t ignore treatment, law enforcement, policy decisions, public education, or other actions needed to address problems that already exist, these communities take a long-term perspective and work to prevent or reduce substance misuse over time.
Most of the models we’ve described in this chapter look to both the present – addressing a current issue – and the future. In this section, we examine another that does the same: the Strategic Prevention Framework developed by the Center for Substance Abuse Prevention (CSAP), part of the Substance Abuse and Mental Health Services Administration (SAMHSA) of the U.S. Department of Health and Human Services.
What is the Strategic Prevention Framework?

Note: The graphic above reflects an earlier version of SAMHSA’s SPF terminology. Current SAMHSA guidance retains the same five steps but identifies Community Relevance and Sustainability as the framework’s two guiding principles.
The Strategic Prevention Framework (SPF) outlines a process that an organization, initiative, community, tribe, territory, or state can follow to prevent substance use and misuse and reduce related problems.
SAMHSA’s SPF is designed specifically for substance use prevention and related behavioral health problems. Because its basic process – assessment, capacity building, planning, implementation, and evaluation – is broadly applicable, communities may also find elements of the framework useful when thinking about other prevention and community-change efforts.
The framework addresses both risk and protective factors. Risk factors are characteristics or conditions within individuals, relationships, communities, or broader environments that can increase the likelihood of harmful behaviors or outcomes. Protective factors are characteristics or conditions that can reduce risk or help support healthy development and well-being. Neither risk nor protective factors determine what will happen to any particular person.
Risk and protective factors vary depending on the issue. Some examples of risk factors related to harmful or underage alcohol use, for instance, include:
- The availability of alcohol in the community, including adults providing alcohol to young people.
- Community norms that tolerate or encourage underage drinking or harmful patterns of alcohol use.
Community acceptance of harmful alcohol use might include treating binge drinking as a normal way to relieve stress, expecting heavy drinking at parties or other events, or tolerating underage drinking. These norms can occur in communities across different income levels and social settings.
- Economic hardship and limited opportunities for young people.
- A family history of alcohol use disorder.
- Beginning alcohol use at an early age.
Some examples of protective factors related to the same behavior include:
- Close and supportive family relationships.
- Good communication between children or adolescents and parents or caregivers.
- Peer support for avoiding underage or harmful alcohol use.
- Clear and consistent family and community expectations that discourage underage and harmful alcohol use.
The Strategic Prevention Framework addresses risk and protective factors through a five-step process.
The Community Tool Box has hundreds of how-to resources that can help communities implement different parts of the Strategic Prevention Framework. Some links to related Toolkits are provided beneath each of the SPF steps below.
Assessment
The process begins by using data and community knowledge to understand local prevention needs, strengths, resources, and conditions. A community planning group should include people with relevant knowledge, experience, and perspectives, including people directly affected by the issue.
Assessment includes such tasks as:
- Identifying and understanding community prevention needs and strengths.
- Identifying existing resources and determining what additional resources may be needed.
- Assessing community readiness.
Related Toolkits:
2. Assessing Community Needs and Resources
3. Analyzing Problems and Goals
Capacity
Developing capacity means building the resources and readiness needed to carry out prevention work. This includes mobilizing people and organizations, strengthening partnerships, identifying financial and other resources, and providing training and technical assistance so that participants have the knowledge and skills to plan, implement, and sustain the effort.
Related Toolkits:
1. Creating and Maintaining Partnerships
8. Increasing Participation and Membership
15. Improving Organizational Management and Development
In this step, community partners develop a plan with goals, objectives, and strategies aimed at the prevention needs identified during assessment. The group may use a logic model or other framework for action, identify evidence-based or evidence-informed programs, policies, and practices that fit local conditions, and determine the resources needed for successful implementation.
Related Toolkits:
4. Developing a Framework or Model of Change
5. Developing Strategic and Action Plans
Implementation
The prevention plan is put into action. Programs, policies, and practices should be implemented with attention to both the evidence supporting them and their fit with the community.
Related Toolkits:
11. Influencing Policy Development
13. Implementing a Social Marketing Effort
Although listed as the fifth step, evaluation takes place throughout the process. Programs, policies, and practices are evaluated to understand how well they were implemented and whether they contributed to the intended outcomes. Evaluation findings are then used to strengthen the effort, reconsider strategies where necessary, and inform the next round of assessment and planning.
Related Toolkits:
Community Relevance and Sustainability
These are the two guiding principles that should be considered throughout all five SPF steps. Community relevance means that prevention decisions reflect local conditions, priorities, cultures, experiences, and perspectives. Sustainability means building the relationships, capacity, resources, and systems needed to maintain effective prevention work over time.
Related Toolkits:
16. Sustaining the Work or Initiative
14. Writing a Grant Application for Funding
9. Enhancing Cultural Competence
Why use the Strategic Prevention Framework?
Given that there are a large number of models available, what are the advantages of using SPF?
- SPF is collaborative and participatory. The framework benefits from involving community partners from the beginning, including people directly affected by the issue. Meaningful participation can strengthen community ownership, support, and the quality of prevention decisions.
- SPF emphasizes the role of the community in prevention. Prevention efforts are stronger when they are based on local conditions and when the people and organizations that make up the community are involved. This agrees with the broader Healthy Communities view that health is a community issue, even when a particular condition affects some groups more than others.
- SPF is flexible and encourages communities to identify locally appropriate solutions. SPF does not prescribe a single prevention program. It provides a planning process that communities can use to select programs, policies, and practices that fit their needs, resources, and circumstances.
- SPF takes a long-term approach by focusing on risk and protective factors that prevention efforts can influence. Breaking a large problem into factors that can actually be addressed can make prevention more manageable and help communities identify practical places to act.
- SPF encourages the use of evidence-based and evidence-informed programs, policies, and practices. Communities can use research evidence along with local data and knowledge to select strategies that fit their prevention priorities.
- SPF is supported by training, technical assistance, and prevention resources. SAMHSA’s Strategic Prevention Technical Assistance Center provides training, technical assistance, and resources to help prevention practitioners understand and apply the SPF.
- SPF’s focus on risk and protective factors can contribute to broader community well-being. Protective factors such as strong family communication, supportive relationships, community connection, and clear expectations can contribute not only to substance use prevention but also to healthy development and stronger communities.
There is a fine line between preventing a harmful condition and promoting a positive one. An effective prevention effort that reduces risk and strengthens protective factors may also help create conditions in which community members are better able to lead healthy and fulfilling lives.
Potential challenges in using SPF
- Limited resources. Thorough assessment, partnership development, planning, implementation, and evaluation all require time and capacity. Communities with fewer financial, staffing, or organizational resources may need to begin on a smaller scale, build partnerships, seek technical assistance, or identify additional funding.
- Balancing fidelity with community fit. It makes sense to use programs and practices supported by evidence rather than reinventing the wheel. At the same time, even strong programs may not fit every community in exactly the same way. Communities should understand which elements of an intervention are essential to its effectiveness and make adaptations thoughtfully and consistently with available implementation guidance.
- Administrative demands. Prevention grants may include substantial requirements for planning, documentation, data collection, performance measurement, and reporting. Smaller organizations may need additional administrative capacity or partnerships to manage those responsibilities.
Some of these challenges are more significant for organizations receiving grant funding, because funders may establish specific program, reporting, and evaluation requirements. Communities that use SPF simply as a planning framework have greater flexibility, but they still need enough time, people, knowledge, and resources to carry out the process effectively.
When should you use the Strategic Prevention Framework?
Prevention, in the ideal, means just that. The best time to start prevention work is before a serious problem becomes deeply established. With its emphasis on risk and protective factors, the framework can help communities prevent substance misuse while also promoting healthy behaviors and environments. In that respect, it is similar to asset development.
The reality in many communities, however, is that issues may not receive sustained attention until they become highly visible or urgent. The best time to embark on a strategic prevention effort may therefore be when the community is ready to turn its attention in that direction.
You can help this process along by assessing the community’s current level of readiness and using appropriate strategies to strengthen awareness, understanding, participation, and support. The first part of a prevention initiative may therefore involve increasing community readiness before a detailed prevention program is developed.
With that said, there are times when SPF might be particularly appropriate:
- When resources and partnerships are available. Resources can include funding, people with prevention experience, community organizations, local sponsors, foundations, public agencies, media and communication partners, volunteers, data, and technical assistance.
- When a community problem has become visible, but before it reaches crisis stage. This may provide an opportunity to focus attention on prevention before most available resources have to be devoted to responding to immediate consequences.
- When a community problem has reached crisis stage. Prevention may be harder to emphasize when immediate needs are urgent, but preventing future harm is still an important part of a long-term response.
- When there is public concern about a population experiencing increased risk, including young people. Prevention can address the factors influencing risk before harmful patterns become established or more serious.
- When community leaders are examining quality of life. Because substance use prevention can involve schools, families, health, public safety, economic conditions, neighborhood environments, and other sectors, it can fit naturally into broader community improvement efforts.
- When a grassroots movement for community improvement is looking for a way to address long-term community issues. A prevention effort can address present concerns while also attempting to improve conditions for future generations.
Who should use the Strategic Prevention Framework?
As with many of the “Who...?” questions in the Community Tool Box, this one not only has more than one answer, but is, in reality, more than one question.
- Who might implement SPF? SPF can be used by state, tribal, territorial, and local agencies; community coalitions; health and human service organizations; schools and universities; prevention providers; and other organizations or partnerships involved in substance use prevention.
SAMHSA continues to support substance use prevention through several funding mechanisms, including Strategic Prevention Framework-related grants and other prevention programs. Specific grant programs, eligibility requirements, and funding opportunities change over time, so organizations seeking funding should consult current SAMHSA funding announcements rather than rely on older grant lists.
Whether or not the effort is federally funded, prevention works best when relevant sectors of the community participate in assessment, planning, implementation, and evaluation. These may include:
- People from populations experiencing increased risk and people with lived experience related to the issue.
- Health and medical professionals.
- Health and human service workers.
- Substance use prevention, treatment, and recovery professionals, along with researchers in the field.
- Law enforcement and public safety representatives.
- Educators.
- Elected and appointed public officials and policymakers at the appropriate level.
- Parents and caregivers.
- Young people.
- Older adults.
- Business and employer representatives.
- Other interested community members.
As stated throughout the Community Tool Box, participatory planning and implementation can help efforts better reflect community needs and strengthen community support. Participation should include not only formal leaders and professionals, but people directly affected by the issue and people whose knowledge comes from lived experience.
Many organizations may use SPF without receiving a specific CSAP or SAMHSA grant. Community-based health and human service organizations, community coalitions, local health departments, schools, universities, tribal organizations, and other groups can use the framework simply to structure prevention work.
- Whom should SPF efforts serve? Prevention efforts can be organized according to three commonly used categories: universal, selective, and indicated. Universal prevention is directed toward a general population that has not been selected on the basis of individual risk. Selective prevention focuses on groups with an elevated level of risk. Indicated prevention focuses on individuals showing early signs or behaviors associated with increased risk but who do not necessarily meet criteria for a substance use disorder.
A typical universal prevention effort might involve community education through schools, media, organizations, workplaces, or other settings. It might provide information about alcohol and other substances, strengthen protective factors, address community norms, or let people know where they can get reliable information and assistance. It might be aimed at a neighborhood, a school system, the whole community, or even a larger geographic area.
Groups served by selective prevention efforts will vary from one community to another. Examples may include:
- Young people experiencing increased risk. Adolescence is a period of continued development, growing independence, social influence, and experimentation. Prevention can help young people develop skills, strengthen protective relationships, understand risks, and delay or avoid substance use.
- People who are pregnant. Prevention efforts can provide accurate, nonjudgmental information and support related to alcohol, tobacco and nicotine, medications, and other substance use during pregnancy. Alcohol use during pregnancy can cause fetal alcohol spectrum disorders, and tobacco, nicotine, and other substance use can also pose risks to pregnancy and fetal development.
- Older adults. Changes associated with aging, isolation, health conditions, medication use, and interactions between medications and alcohol or other substances can create prevention concerns for some older adults. Prevention efforts can increase awareness among older adults, families, caregivers, and professionals.
- People experiencing homelessness. Substance use disorders, mental and physical health concerns, trauma, and housing instability can intersect in complex ways. Prevention and support efforts should avoid assuming that substance use is the cause of homelessness and instead respond to the combination of needs and conditions affecting individuals and communities.
Indicated prevention focuses on people who show early signs, behaviors, or conditions associated with increased risk but who have not necessarily developed a diagnosable disorder. Depending on the setting and program, participants may be identified through schools, health care, families, social services, community programs, or other appropriate referral pathways.
How do you use the Strategic Prevention Framework?
As described above, SPF has five steps. We’ll examine those in more detail here to see how they guide prevention work.
SAMHSA’s Strategic Prevention Technical Assistance Center provides current training, technical assistance, and resources related to the Strategic Prevention Framework, prevention science, evidence-informed programs and policies, and community-based prevention.
Phase 1: Assessment. In the assessment phase, you use data and community knowledge to determine prevention needs, strengths, resources, and relevant risk and protective factors.
- Form a prevention assessment or planning group. Because prevention takes a community perspective, the group should include people and organizations with relevant knowledge, experience, and perspectives. Depending on the issue and community, these might include:
- Law enforcement and public safety
- Education
- Young people
- Courts and justice-system partners
- Civic and community organizations
- Parents and caregivers
- Faith communities
- Older adults
- Businesses and employers
- Human service providers
- Health care
- Military and veteran-serving organizations where relevant
- Colleges and universities
- Racial, ethnic, cultural, and language communities
- Government agencies
- Elected and appointed officials
- Childcare and youth-serving providers
- People with lived experience of substance use, recovery, prevention services, or related community conditions
People directly affected by substance use should not be treated merely as the subjects of prevention efforts. People in recovery and others with lived experience can contribute important knowledge about community conditions, barriers, services, and what prevention messages or strategies may actually be useful.
- Assess community needs and assets. Ideally, the community will conduct an assessment broad enough to understand both its prevention needs and the resources already available. The scale of the assessment should fit the organization’s or coalition’s resources. A smaller community group may need to rely more heavily on partnerships, existing data, volunteers, and focused assessment methods.
Some questions you might try to answer through a community assessment include:
- What patterns of substance use, substance misuse, and related harms are present in the community?
- Which substances are most available and most commonly used?
- What trends are occurring in substance use, availability, and related harms?
- Which populations or groups are experiencing greater risk or harm?
- Are some geographic areas experiencing different conditions or levels of harm?
- Do patterns of substance use differ among populations, age groups, or geographic areas?
- At what ages are particular forms of substance use commonly beginning?
- What prevention efforts, treatment services, recovery supports, policies, and community resources already exist? What is known about their reach and effectiveness?
- Which aspects of substance use and related harm are most important for the community to address?
A community assessment can use several methods. In general, using multiple sources helps produce a more complete picture of community conditions.
- Surveys. Surveys may be conducted in person, by phone, by mail, online, or through other appropriate formats. They can be designed for groups or individuals and can gather information about a wide range of topics.
- Interviews. Interviews may be individual or group, structured, semi-structured, or unstructured, and can be conducted in person, by phone, or through other accessible communication methods.
- Focus groups. A focus group is a guided discussion designed to gather information on a particular topic from a group of participants. Skilled facilitation can help ensure that different participants have opportunities to contribute.
In surveys, interviews, focus groups, and other community engagement, there may be some people you particularly want to hear from. These might include:
- Community leaders – people from different parts of community life whom others look to for leadership, guidance, or trusted information. Some may hold formal leadership positions; others may be respected because of their experience, relationships, or community involvement.
- The population or populations most directly affected by the issue or by the proposed prevention effort.
- People who work with those populations – health and human service professionals, educators, outreach workers, prevention specialists, and others.
- Family members, caregivers, peer-support groups, recovery groups, and other people or organizations connected with those directly affected.
- Policymakers and other people who influence laws, regulations, funding, policies, and community attitudes.
- Researchers and others who have studied substance use or related conditions in the community.
- Observation. Observation can be used in different ways in a community assessment. It might include observing neighborhood conditions and public spaces, documenting the location and concentration of alcohol or tobacco retailers, examining community events and advertising, or participating in authorized ride-alongs or other structured observation with community partners. Observation should be planned in ways that are safe, ethical, and appropriate for the people conducting the assessment.
- Public and administrative records. Federal, state, tribal, territorial, and local agencies may already collect useful demographic, health, behavioral, service-use, school, public safety, and other data. The U.S. Census, SAMHSA, CDC, state and local health agencies, schools, hospitals, and other organizations may all have information relevant to your assessment.
- Assess community readiness. Community readiness is the degree to which a community is prepared to take action on an issue. Once you understand the current level of readiness, you can select strategies that begin there and help the community move forward.
Understanding where the community is and starting from there is extremely important. If community members don’t yet recognize the problem, understand why it matters, or believe that action is possible, you may have difficulty gaining the participation and support needed for a successful prevention effort. Early work may therefore focus on awareness, relationships, community engagement, and readiness.
Tools for examining dimensions and levels of community readiness can be found in Community Readiness and related Community Tool Box sections.
- Determine the prevention need that your effort can realistically influence. There may be several important issues and populations to consider. The questions are where your effort can make a meaningful contribution and what your resources allow you to address. Starting with a focused and manageable priority may help the community build experience and capacity for broader work later.
Phase 2: Capacity.
The community needs both readiness and capacity to carry out prevention successfully. Capacity includes knowledge about local substance use and prevention; people and organizations able to do the work; leadership and partnerships; financial and other resources; community support; and the ability to sustain prevention efforts over time.
This doesn’t mean that everyone in the community has to understand, support, and participate in a prevention effort. Rather, there needs to be enough knowledge, participation, leadership, and support to make meaningful action possible.
To build community capacity:
- Start with your core group. The people involved in assessment and others who have supported prevention from the beginning may provide a foundation for continued planning and implementation. They can remain involved themselves and help bring in others whose knowledge, experience, or relationships are needed.
- Choose or develop a logic model or theory of change to guide your effort. A logic model can expand on the SPF by showing how specific activities are expected to influence risk and protective factors and ultimately contribute to desired outcomes.
- Use what you know about community readiness to communicate about the issue and encourage participation. Depending on what community members already know, communication may focus on the nature of the issue, its local effects, available strengths and resources, or ways people can participate. People with lived experience who choose to share their own stories can be powerful contributors, provided their participation is voluntary and respectful.
If the community is already well aware of the issue, you may be able to concentrate more heavily on building participation and support for planning and implementation. A community advisory board, prevention coalition, or similar group may help coordinate the effort.
- Expand the network of people interested in prevention. As community knowledge and support grow, recruit people whose skills, relationships, experience, or enthusiasm can strengthen the effort.
People can contribute in many different ways – facilitation, outreach, data analysis, youth engagement, communications, curriculum development, logistics, meeting coordination, evaluation, community organizing, or simply a willingness to help. Participation itself can also help people develop new skills and leadership capacity.
Phase 3: Planning.
The planning phase is at least as important as any other. First, it puts the participatory nature of the effort into practice, bringing different kinds of knowledge and experience into decision-making. Second, it creates the structure, organization, and content of the prevention effort itself. Careful planning can prevent a great deal of trouble later.
- Assemble a planning team. This may be the assessment group, include some of its members, or be a somewhat different group. Whatever the arrangement, the team should include the sectors, communities, and experiences relevant to the effort. Representation should be broad enough that people directly affected by the issue have meaningful opportunities to influence decisions.
- Prepare the planning team. Participants may bring very different levels of experience with meetings, group decision-making, planning, prevention science, and the issue itself. Useful preparation may include:
- Ground rules for meetings – respecting participants, creating opportunities for different voices to be heard, listening carefully, focusing on ideas rather than personalities, sharing decision-making, and preventing a few people from dominating.
- Problem-solving and group decision-making methods, including brainstorming, small-group discussion, and other participatory approaches.
- Substance use and related conditions in the community, drawing on assessment findings and other reliable data.
- Risk and protective factors – what they are, how they interact, and how prevention can address them.
- Resources – not only funding, but also volunteer time, community knowledge, relationships, organizational support, communication channels, facilities, data, local expertise, and supportive policies.
- Evidence-based and evidence-informed programs and practices – what the evidence tells you, how to judge fit, what elements need to be implemented faithfully, and when adaptation may be appropriate.
- Analyze local risk and protective factors. A college or university, prevention specialist, public health agency, community organization, technical assistance provider, or other knowledgeable partner may be able to help. Communities with limited resources can still use local data, community knowledge, and available expertise to identify factors that matter most.
Risk and protective factors can operate across multiple levels, including the individual, peer and relationship, family, school or organizational, community, and broader societal environment. Media, policy, economic conditions, culture, and other social conditions can influence local attitudes and behavior as well.
Protective factors may include supportive relationships, bonding and connection, meaningful opportunities, skills, healthy beliefs and expectations, and other conditions that help people and communities thrive.
Developmental assets, which are closely related to protective factors for children and adolescents, can also be considered in terms of external and internal assets.
External assets include:
- Support. Important people in a young person’s life encourage, help, listen to, and respect them.
- Empowerment. Young people have meaningful opportunities to contribute, take responsibility, and influence parts of their own lives and communities.
- Boundaries and expectations. Young people receive clear, reasonable expectations and consistent support.
- Constructive use of time. Young people have opportunities to engage in meaningful, enriching, and productive activities.
Internal assets include:
- Commitment to learning. The young person values learning and has opportunities and support to engage in education and skill development.
- Positive values. The young person develops values that support responsible and caring behavior.
- Social competencies. The young person develops interpersonal, communication, decision-making, and other skills needed to build healthy relationships and navigate daily life.
- Positive identity. The young person develops confidence, a sense of purpose, and a healthy view of themselves and their future.
The goal is to understand how risk and protective factors operate in your community – which factors appear especially important, which can realistically be influenced, and which are most closely connected to the prevention priorities identified through assessment.
- Choose the factors you’ll concentrate on. Select a manageable number. You can’t address everything at once without overextending your resources and diluting your efforts. Concentrate on factors that matter to the problem and that your community can realistically influence.
Trying to reduce the availability of drugs, for instance, may involve more than changing enforcement or attitudes within one neighborhood. Availability may be influenced by neighboring communities, online or informal markets, broader policies, and other conditions. A local strategy should therefore consider both what the community can influence directly and what may require collaboration beyond its boundaries.
- Research and choose evidence-based or evidence-informed approaches that address the risk and protective factors you’ve identified. Research evidence can tell you whether a program, policy, or practice has worked elsewhere and under what circumstances. Community data and experience can then help you judge whether it is a good fit locally.
Prevention approaches can also be thought of as universal, selective, or indicated. Another useful distinction is between strategies that work primarily with individuals and strategies that change the surrounding environment.
Individual-level approaches may help people develop knowledge, attitudes, relationships, coping skills, decision-making skills, or other capacities that support healthy behavior.
Environmental approaches seek to change conditions surrounding people. These may include policy change, enforcement of laws and regulations, changes in organizational practice, communication efforts, changes in the physical or social environment, or strategies aimed at community norms.
Effective community prevention often includes both individual and environmental strategies.
Evidence matters, but so does fit. If an intervention has been shown to work, there is a good reason to understand and preserve the elements responsible for its effectiveness. At the same time, communities differ in language, history, culture, institutions, resources, geography, and other conditions.
The aim is not to change a proven approach simply because you prefer something different, nor to follow a program so rigidly that obvious local realities are ignored. Instead, understand the intervention’s essential components, follow available implementation guidance, and make thoughtful adaptations when necessary to improve community relevance without undermining the elements that make the approach effective.
Reinventing the wheel is unnecessary if you already know the wheel works quite well. But you still need to make sure it fits the road you’re traveling on.
- Create an overall plan for the effort. Strategy includes not just what the program itself will look like, but a number of other elements:
- Vision and mission statements for the effort.
- How you’ll gather the resources you need. How much funding will be needed and where might it come from? How will you recruit staff, volunteers, partners, or other participants?
- The timeline and implementation process. What will happen, by when, and who will take responsibility for what?
- The results you hope to see in both the short and long term.
- How you’ll monitor and evaluate the effort.
Your plan should be detailed enough that it could still be followed even if everyone involved in the planning suddenly decided to retire to a tropical island and left no forwarding address.
- Present the plan to the community and continue building support. Prevention is more likely to be sustained when community members understand the plan, see how it responds to local needs, and have meaningful opportunities to participate.
Phase 4: Implementation.
Now it’s time to put the prevention plan into practice. Implementation will be much easier if planning has been thorough and community partners understand and support the work.
- Hire staff and/or recruit volunteers. Whether an effort uses paid staff, volunteers, community partners, or a combination, it’s important to involve people with the appropriate skills, relationships, experience, and support.
- Follow the implementation plan while remaining responsive to real conditions. Timelines can be affected by staffing, contracting, community events, funding, or other circumstances. A clear plan helps keep the work organized, but implementation should also respond thoughtfully when conditions change.
The same principle applies to the methods, content, and structure of evidence-based programs and practices. Follow the elements that are important to the intervention’s effectiveness, monitor how implementation is going, and make adaptations thoughtfully rather than casually.
- Continue to pay attention to resources. Prevention takes time. Funding may be time-limited, staff and volunteer availability may change, and new needs may arise. Continue building relationships with funders and community partners, documenting results, and looking for ways to sustain effective work.
- Keep the community informed. Use community meetings, local media, websites, social media, newsletters, presentations, events, and other appropriate communication channels to share progress, lessons learned, opportunities to participate, and results.
Phase 5: Evaluation.
Only by monitoring and evaluating your effort can you understand how well it is working and what may need to change or improve. Evaluation should take place throughout the life of the prevention effort.
- Evaluate implementation and process. Did you do what you planned to do? Did activities occur when and how you expected? Did you reach the people or settings you intended to reach? What barriers or unexpected conditions affected implementation?
- Evaluate changes in the factors your strategies are intended to influence. Are the risk or protective factors you targeted changing in the direction you hoped? Are there unexpected effects?
- Evaluate outcomes. Is the community seeing the results it hoped for – such as reduced substance misuse or related harms, increased protective factors, or stronger prevention systems? If not, determine whether the strategy, implementation, selected risk and protective factors, or assumptions behind the plan need to be reconsidered.
Evaluation findings should be reviewed regularly and used to improve the effort. That is the point of evaluation – not simply to prove that something worked or failed, but to learn. Finding a way to make an effort stronger is not an admission of failure. Community conditions change, implementation can improve, and even successful programs can usually learn something from experience.
When you make major changes, communicate them to community partners and participants. Adjustments may require additional funding, volunteers, staff, expertise, communication, or other resources. Involving the community in those decisions can strengthen both the changes themselves and community ownership of the effort.
The Community Tool Box considers evaluation such an important part of any intervention or initiative that it devotes four chapters – 36 through 39 – to it. Those chapters include resources on planning evaluations, gathering information, interpreting findings, and using evaluation to improve community efforts.
SPF does not add a sixth step after evaluation, but regular users of the Tool Box will recognize an important lesson here: keep at it. Sustainability is built into the framework precisely because prevention and community change take time. A positive result does not automatically become permanent. Effective strategies, partnerships, knowledge, and community capacity have to be sustained and adapted as conditions change.
In Summary
SAMHSA’s Strategic Prevention Framework is a structure for planning and carrying out substance use prevention efforts and addressing related behavioral health problems. Its five steps – Assessment, Capacity, Planning, Implementation, and Evaluation – form a dynamic and recurring process rather than a one-time sequence.
Two guiding principles – Community Relevance and Sustainability – should inform all five steps. Community relevance means that prevention decisions are grounded in local data, conditions, priorities, cultures, experiences, and community knowledge. Sustainability means developing the relationships, resources, capacity, and systems needed to continue effective prevention work over time.
The Strategic Prevention Framework also focuses on risk and protective factors. Risk factors are conditions or characteristics that increase the likelihood of harmful outcomes, while protective factors can reduce risk or support healthier development. Neither determines an individual’s future. By identifying locally important risk and protective factors and selecting strategies that address them, communities can focus their resources where they are most likely to make a difference.
The five steps are:
- Assessment – use data and community knowledge to understand prevention needs, strengths, resources, risk and protective factors, and community readiness.
- Capacity – build the partnerships, participation, knowledge, leadership, resources, and readiness needed to act.
- Planning – establish priorities and outcomes and select evidence-based or evidence-informed strategies that fit local needs and conditions.
- Implementation – put the plan into practice with attention to both effective implementation and community relevance.
- Evaluation – examine implementation and outcomes, learn from the results, and use what you learn to improve the effort.
SAMHSA and its Center for Substance Abuse Prevention continue to provide prevention resources, funding opportunities, and technical assistance. Current training and technical assistance for applying the Strategic Prevention Framework are available through SAMHSA’s Strategic Prevention Technical Assistance Center.
Most important, SPF is not simply a way to choose a prevention program. It is a way to understand a community, make decisions based on data and local knowledge, involve the people who have a stake in the work, act deliberately, evaluate what happens, and keep improving over time.
Contributor
Phil Rabinowitz
Resources
Online Resources
Chapter 12: Prevention and Promotion in the "Introduction to Community Psychology" describes historical perspectives on prevention and promotion, the different types of prevention, examples of risk and protective factors, and various aspects of prevention programs and evaluation.
CSAP’s Western Center for the Application of Prevention Technologies. A step-by-step how-to on developing and implementing a prevention program.
Day for Prevention Video 1 - Community Partnerships and Coalition Building. This features a coalition that includes youth in decision-making – critical for an initiative meant to benefit youth.
Information on creating, maintaining, and strengthening effective youth programs.
Michigan’s Approach to A Strategic Prevention Framework, from the Michigan Department of Community Health. This is useful information outside the state of Michigan as well.
NIDA, the National Institute on Drug Abuse, part of the National Institutes of Health.
Prevention information from NIDA.
The Prevention Platform from SAMHSA (Substance Abuse and Mental Health Services Administration)/CSAP’s (Center for Substance Abuse Prevention, a subsidiary of SAMHSA). Technical assistance, funding information, valuable links, tools, etc. The all-purpose build-your-own-prevention-program website. Extremely valuable information.
Strategic Prevention Framework (SPF): Key Elements for Use in Prevention Work.
What is the Strategic Prevention Framework?
___The Strategic Prevention Framework (SPF) outlines a process that an organization, initiative, community, or state can follow in order to prevent and reduce the use and abuse of alcohol, tobacco, and drugs.
___SPF concentrates on eliminating risk factors and strengthening protective factors.
___Risk factors are those elements within an individual or her environment that make her more susceptible to particular negative behaviors or conditions.
___Protective factors are the opposite – those elements within an individual or his environment that make him less susceptible to those negative behaviors or conditions.
___SPF has five phases:
- Assessment
- Capacity
- Planning
- Implementation
- Evaluation
Why use the Strategic Prevention Framework?
___SPF is inclusive and participatory.
___SPF emphasizes the role of the community in prevention.
___SPF is open-ended, and encourages communities to find their own solutions.
___SPF aims to create long-term social change by focusing on risk and protective factors that can be influenced by short- or medium-term prevention efforts.
___SPF provides communities with proven, evidence-based models to choose from.
___SPF provides technical assistance and links to other practitioners and programs.
___SPF’s focus on risk and protective factors can improve the long-term well-being of the community.
Possible Disadvantages to Using SPF
___Limited resources.
___Insistence on the faithful implementation of evidence-based programs.
___Administrative load.
When should you use the Strategic Prevention Framework?
___Before there’s a serious problem.
___When resources are available.
___When a community problem has entered the public consciousness, but before it has reached crisis stage.
___When a community problem has reached the crisis stage.
___When there’s public focus on an at-risk population, particularly youth.
___When there’s a community economic development effort underway and people are looking at the community’s quality of life.
___When a grassroots movement for community improvement has arisen, and is looking for a way to address community issues.
Who should use the Strategic Prevention Framework?
___Members of the population(s) most at risk.
___Medical professionals, particularly those who work directly with at-risk populations.
___Human service workers.
___Alcohol- and drug-treatment professionals, as well as researchers in the field.
___Law enforcement officials.
___Educators.
___Elected and appointed public officials and policy makers at the appropriate level.
___Parents.
___Youth.
___Elders.
___The business community.
___Interested community members.
How do you use the Strategic Prevention Framework?
Phase 1: Assessment
___Form an epidemiological workgroup.
___Assess community needs and assets.
___Assess community readiness.
___Determine the most pressing need that a prevention effort can influence.
Phase 2: Capacity.
___Start with your core group.
___Choose or develop a logic model or theory of practice to guide your effort.
___Use what you know about the community’s level of readiness to publicize the issue and encourage participation.
___Expand the network of community members interested in preventing substance use.
Phase 3: Planning.
___Assemble a planning team.
___Train the planning team.
___Analyze local risk and protective factors.
___Choose the factors you’ll concentrate on.
___Research and choose an evidence-based approach that can be used with the risk and protective factors you’ve settled on.
___Create an overall plan for the effort.
___Present the plan to the community and gather support.
Phase 4: Implementation.
___Hire staff and/or recruit volunteers.
___Stick to your plan for the implementation process.
___Continue to pay attention to resources.
___Keep the community informed.
Phase 5: Evaluation.
___Evaluate the process.
___Evaluate the impact of the program.
___Evaluate the outcomes.
___Use the evaluation results to adjust the program to be more effective.
___Keep at it indefinitely.
Example: Evidence-Based Environmental Strategies to Prevent Underage Drinking Using the Strategic Prevention Framework.
Preventing Underage Drinking: Using Getting To Outcomes™ with the SAMHSA Strategic Prevention Framework to Achieve Results describes 10 environmental strategies for reducing underage drinking that have the strongest evidence base. Each example includes a brief research summary and additional text that describes issues related to planning, implementing, and evaluating the strategy. The examples also include samples of tools, worksheets, or ordinances to facilitate the community’s work.The ten strategies are briefly described below.
- Responsible beverage service is a merchant education program designed to reduce sales to minors and intoxicated adults. It involves media advocacy to promote policy changes, manager training, and server/seller training.
- Alcohol compliance checks are thought to be most effective when they are frequent and well publicized, solicit community support, and involve penalties for the licensed establishment rather than just the server.
- Happy hour restrictions eliminate one of the environments most conducive to overconsumption of alcohol.
- Controls on alcohol outlet location and density reduce the accessibility of alcohol to young people by making it less prevalent in their immediate environment.
- Sobriety/traffic-safety checkpoints, which are very effective in reducing alcohol-related traffi c accidents, injuries, and deaths, are even more effective when combined with a vigorous public awareness campaign.
- Graduated drivers’ licensing laws, which entail clearly specified learner, intermediate, and full license phases, are effective in reducing crashes among teen drivers, but they need to be adequately enforced.
- Social-host liability laws state that adults providing alcohol to minors or those who are obviously intoxicated are legally liable if the person is killed or injured, or kills or injures another person.
- Keg registration is intended to prevent friends or relatives of legal drinking age from buying beer kegs for teen parties. Registration can be achieved in a number of ways, for example, permanent markings on each keg that identify where and when it was purchased or a requirement that keg delivery requests be made in person at the store.
- Restricting sales of alcohol at public events controls the availability of alcohol at gatherings such as concerts, street fairs, and sporting events.
- Increasing taxes on the sale of alcohol leads to reductions in the levels and frequency of drinking and, especially, heavy drinking among youth, as well as lower traffic accident fatality rates and reduced incidence of some types of crime. Several surveys indicate that most Americans support increased alcohol taxes.
For more in-depth information on these evidence-based environmental strategies to prevent underage drinking, please see the full manual Preventing Underage Drinking: Using Getting To Outcomes™ with the SAMHSA Strategic Prevention Framework to Achieve Results. Imm P, Chinman M, Wandersman A, Rosenbloom D, Guckenburg S, Leis R. (2007). Preventing Underage Drinking: Using Getting to Outcomes with the SAMHSA Strategic Prevention Framework to Achieve Results, RAND, TR-403-SAMHSA. Santa Monica, CA: RAND Corporation.
Tool #1: Supports for the Strategic Prevention Framework
Assessment
Toolkit 2: Assessing Community Needs and Resources
Toolkit 3: Analyzing Problems and Goals
Assessing Community Needs and Resources
Analyzing Community Problems and Solutions
An Introduction to the Problem-Solving Process
Defining and Analyzing the Problem
Analying Root Causes of Problems: The "But Why?" Techinique
Information Gathering and Synthesis
Capacity Building
Toolkit 1: Creating and Maintaining Coalitions and Partnerships
Toolkit 6: Building Leadership
Toolkit 8: Increasing Participation and Membership
Toolkit 15: Improving Organizational Management and Development
Our Model of Practice: Building Capacity for Community and System Change
Using Internet-Based Tools to Promote Community Health and Development
Getting Issues on the Public Agenda, especially:
- Communicating Information about Community Health and Development Issues
- Gaining Public Support for Addressing Community Health and Development Issues
- Talking About Risk and Protective Factors Related to Community Issues
Choosing Strategies to Promote Community Health and Development
Communications to Promote Interest
Encouraging Involvement in Community Work, especially:
- Developing a Plan for Increasing Participation in Community Action
- Promoting Participation Among Diverse Groups
- Involving Key Influentials in the Initiative
- Involving People Most Affected by the Problem
Developing an Organizational Structure for the Initiative
Hiring and Training Key Staff of Community Organizations
Recruiting and Training Volunteers
Providing Training and Technical Assistance
Orienting Ideas in Leadership, especially:
- Developing a Plan for Building Leadership
- Styles of Leadership
- Developing a Community Leadership Corps: A Model for Service Learning
- Collaborative Leadership
Group Facilitation and Problem Solving
Working Together for Racial Justice and Inclusion, especially:
- Building Relationships with People from Different Cultures
- Creating Opportunities for Members of Groups to Identify Their Similarities, Differences, and Assets
- Understanding Culture, Social Organization, and Leadership to Enhance Engagement
- Building Inclusive Communities
Planning/Implementation
Toolkit 4: Developing a Framework or Model of Change
Toolkit 5: Developing Strategic and Action Plans
Toolkit 7: Developing an Intervention
Toolkit 8: Increasing Participation and Membership
Toolkit 10: Advocating for Change
Developing a Logic Model or Theory of Change
Generating and Choosing Solutions
Putting Your Solution into Practice
Choosing and Adapting Community Interventions, especially
- Criteria for Choosing Promising Practices and Community Interventions
- Understanding Risk and Protective Factors: Their Use in Selecting Potential Targets and Promising Strategies for Interventions
- Identifying Strategies and Tactics for Reducing Risks
- Adapting Community Interventions for Different Cultures and Communities
Providing Information and Enhancing Skills, especially:
Enhancing Support, Incentives, and Resources, especially:
Modifying Access, Barriers, and Opportunities, especially:
Improving Services, especially:
Chapter 25: Changing Policies, especially:
- Changing Policies: An Overview
- Using Tax Incentives for Support Community Health and Development
- Supporting Local Ordinances to Modify Access to Unhealthy Products and Practices
Building Culturally Competent Organizations
Conducting a Direct Action Campaign
Toolkit 12: Evaluating the Initiative
Our Evaluation Model: Evaluating Comprehensive Community Initiatives
Some Operations in Evaluating Community Intervention
Some Methods for Evaluating Comprehensive Community Initiatives
Using Evaluation to Understand and Improve the Initiative
Maintaining Quality Performance
Sustainability and Cultural Competence
Toolkit 7: Developing an Intervention
Toolkit 9: Enhancing Cultural Competence
Toolkit 16: Sustaining the Work or Initiative
Promoting Participation Among Diverse Groups
Adapting Community Interventions for Different Cultures and Communities
Working Together for Racial Justice and Inclusion
Social Marketing of Successful Components of the Initiative
Planning for Long-Term Institutionalization
Tool #2: CSAP’s Principles of Substance Use Prevention
The principles are divided into six domains: Individual, Family, Peer, School, Community, and Society/Environmental.
Individual Domain
1. Build social and personal skills.
2. Design culturally-sensitive interventions.
3. Cite immediate consequences.
4. Combine information dissemination and media campaigns with other interventions.
5. Provide positive alternatives to help youth in high-risk environments develop personal and social skills in a natural and effective way.
6. Recognize that relationships exist between substance use and a variety of other adolescent health problems.
7. Incorporate problem identification and referral into prevention programs.
8. Provide transportation to prevention programs.
Family Domain
1. Target the entire family.
2. Help develop bonds among parents in programs; provide meals, transportation, and small gifts; sponsor family outings; and ensure cultural sensitivity.
3. Help minority families respond to cultural and racial issues.
4. Develop parenting skills.
5. Emphasize family bonding.
6. Offer sessions where parents and youth learn and practice skills.
7. Train parents to both listen and interact.
8. Train parents to use positive and consistent discipline techniques.
9. Promote new skills in family communication through interactive techniques.
10. Employ strategies to overcome parental resistance to family-based programs.
11. Improve parenting skills and child behavior with intensive support.
12. Improve family functioning through family therapy when indicated.
13. Explore alternative community sponsors and sites for schools.
14. Videotape training and education.
Peer Domain
1. Structure alternative activities and supervise alternative events.
2. Incorporate social and personal skills-building opportunities.
3. Design intensive alternative programs that include a variety of approaches and substantial time commitment.
4. Communicate peer norms against use of alcohol and illicit drugs.
5. Involve youth in the development of alternative programs.
6. Involve youth in peer-led interventions or interventions with peer-led components.
7. Counter the effects of deviant norms and behaviors by creating an environment for youth with behavior problems to interact with other nonproblematic youth.
School Domain
1. Avoid relying solely on knowledge-oriented interventions designed to supply information about negative consequences.
2. Correct misconceptions about the prevalence of use in conjunction with other education approaches.
3. Involve youth in peer-led interventions or interventions with peer-led components.
4. Give students opportunities to practice newly acquired skills through interactive approaches.
5. Help youth retain skills through booster sessions.
6. Involve parents in school-based approaches.
7. Communicate a commitment to substance use prevention in school policies.
Community Domain
1. Develop integrated, comprehensive prevention strategies rather than one-time community-based events.
2. Control the environment around schools and other areas where youth gather.
3. Provide structured time with adults through mentoring.
4. Increase positive attitudes through community service.
5. Achieve greater results with highly involved mentors.
6. Emphasize the costs to employers of workers’ substance use and abuse.
7. Communicate a clear company policy on substance use.
8. Include representatives from every organization that plays a role in fulfilling coalition objectives.
9. Retain active coalition members by providing meaningful rewards.
10. Define specific goals and assign specific responsibility for their achievement to subcommittees and task forces.
11. Ensure planning and clear understanding for coalition effectiveness.
12. Set outcome-based objectives.
13. Support a large number of prevention activities.
14. Organize at the neighborhood level.
15. Assess progress from an outcome-based perspective and make adjustments to the plan of action to meet goals.
16. Involve paid coalition staff as resource providers and facilitators rather than as direct community organizers.
Society/Environmental Domain
1. Develop community awareness and media efforts.
2. Use mass media appropriately.
3. Provide structured time with adults through mentoring.
4. Avoid the use of authority figures.
5. Broadcast messages frequently over an extended period of time.
6. Broadcast messages through multiple channels when the target audience is likely to be viewing or listening.
7. Disseminate information about the hazards of a product or industry that promotes it.
8. Promote replacement of more conspicuous labels.
9. Promote restrictions on tobacco use in public places and private workplaces.
10. Promote clean indoor air laws.
11. Combine beverage server training with law enforcement.
12. Combine beverage servers’ legal liability.
13. Increase the price of alcohol and tobacco through excise taxes.
14. Increase minimum purchase age for alcohol to 21.
15. Limit the location and density of retail alcohol outlets.
16. Employ neighborhood antidrug strategies.
17. Enforce minimum purchase age laws using undercover buying operations.
18. Use community groups to provide positive and negative feedback to merchants.
19. Employ more frequent enforcement operations.
20. Implement “use and lose” laws.
21. Enact deterrence laws and policies for impaired driving.
22. Enforce impaired-driving laws.
23. Combine sobriety checkpoints with positive passive breath sensors.
24. Revoke licenses for impaired driving.
25. Immobilize or impound the vehicles of those convicted of impaired driving.
26. Target underage drivers.
A Health Impact Assessment (HIA) is a tool that helps community leaders, policymakers, planners, and changemakers understand the possible health and safety effects of proposed projects, plans, programs, and policies on community members. An HIA can be a valuable resource for anticipating health effects before important decisions are made. This section explores how to conduct an HIA effectively and use the results to improve community projects, policies, and planning.
What is a Health Impact Assessment?
A consensus reached at a World Health Organization (WHO) meeting held in Gothenburg, Sweden, in 1999 defines HIA as “a combination of procedures, methods, and tools by which a policy, program [a series of projects over time], or project may be judged as to its potential effects on the health of a population, and the distribution of those effects within that population.” In simpler language, it’s a way of finding out whether and how a proposed action or policy may affect the health of people who are in some way exposed to it.
While there is obviously a difference between a single project and a series of projects, for the purposes of this section, we’ll sometimes group them under the term “project.” We’ll consider a project as an activity that has clear physical or practical consequences, as opposed to a policy, which may set guidelines for future action in any number of areas or sectors.
An HIA is intended not to make a decision, but to support decision-making. It helps decision-makers consider options by anticipating the possible health consequences of each. HIAs are adapted to the needs and conditions of different locations and circumstances and can be used at the local, regional, national, and international levels. They have been applied to projects, plans, programs, and policies in such sectors as agriculture, residential development, transportation, mining, industry, energy, and recreation. HIAs can also be useful in areas such as employment, economic development, land use, and urban planning.
The actual practice of an HIA involves one or more practitioners – ideally people with appropriate training and/or experience – reviewing existing research and gathering evidence from people with expertise related to the project or policy, residents and other community members, public officials, health professionals, organizations, and others with relevant knowledge or experience. HIA practitioners may also attend or conduct meetings among different sectors, involve community members in discussions with developers or officials, and otherwise support the process in order to gather as complete a picture as possible of potential health effects and opportunities to promote health.
Ultimately, HIA practitioners prepare findings and recommendations that should be communicated to decision-makers and stakeholders, including people in the community who may be affected. Decision-makers can then use that information to help determine how to proceed.
An HIA may be commissioned by a government agency, policymakers concerned with a proposed project or policy, the organization or contractor carrying out a project, a local or regional government, a community organization, or another interested group, depending upon the circumstances. Regardless of who commissions it, the HIA should be conducted as independently, transparently, and objectively as possible.
HIAs can vary considerably in scope and intensity depending on the time, resources, evidence, and personnel available. Traditionally, they have sometimes been described in terms such as:
- Desktop. A relatively limited HIA that relies primarily on existing research, available data, and consultation with selected stakeholders.
- Rapid. An HIA that combines existing evidence with more direct consultation or field-based assessment and is generally conducted within a relatively limited time frame.
- Comprehensive. A more extensive HIA that seeks a broad range of evidence through literature review, interviews, community engagement, surveys, existing data, and, where appropriate, additional research.
The amount of time required for any of these approaches can vary widely depending on the complexity of the proposal, the information already available, the populations involved, and the decisions that need to be made. What matters most is that the scope of the HIA is appropriate to the decision and that the assessment provides useful information in time for decision-makers to act on it.
The ideal HIA is planned through a participatory process that involves stakeholders and encourages cooperation among the parties involved. In practice, this may require helping government agencies and organizations work across sectors and share information, while creating meaningful opportunities for community members to participate in the process.
Ideally, HIAs are prospective – that is, they look forward. An HIA is usually most useful when it is conducted before a project, plan, program, or policy is implemented, and preferably early enough that findings can influence its design. HIAs may also be conducted while implementation is underway or after a decision has been made, although at that point they function more as tools for identifying effects, informing adjustments, or contributing to future decisions. Where possible, an HIA should begin early enough to influence the decision it is intended to inform.
HIAs are guided by four basic values:
- Democracy. Wherever possible, people and organizations affected by or involved in a proposed action or policy should have meaningful opportunities to participate in the HIA, understand its possible consequences, and contribute their knowledge and perspectives.
- Equity. HIAs should examine how health impacts are distributed across the population, with particular attention to groups that may experience greater risks, barriers, or disadvantages.
- Sustainable development. Attention should be paid to both short- and long-term impacts of a proposed action or policy, including effects that may not be immediately obvious.
We can look at this both as a health issue – Will the safeguards to health that we put in place today still be adequate in 10 or 20 or 100 years? – and as a larger societal issue related not only to individual health, but to the long-term health of the community and society. Do we develop an irrigation system that helps farmers now, but that will cause an aquifer to run dry in ten years? Do we build housing using materials and construction methods that support both environmental sustainability and a healthy living environment over time?
- Ethical use of evidence. Research and evidence used in an HIA should be handled as objectively and transparently as possible. The purpose is not to search only for information that confirms a position already held, but to consider relevant and credible evidence whether or not it supports a preferred outcome.
The ethical use of evidence concerns not only ethics, but also the effectiveness of an HIA. One way of thinking about HIA effectiveness identifies several possibilities:
- Direct effectiveness: A project or policy is modified or reconsidered as a result of the HIA.
- General effectiveness: The HIA is properly conducted and meaningfully considered, even if it does not result in changes to the original decision. Changes may not have been necessary, or decision-makers may have considered the evidence and concluded that another option provided the greater overall benefit.
- Opportunistic effectiveness: The HIA is used primarily to confirm or justify a decision that has already been made, rather than to examine the evidence openly.
- Ineffectiveness: An HIA is conducted but largely ignored, or is conducted so poorly that it provides little useful information.
For an HIA to be genuinely useful, relevant evidence should be considered and presented as completely and accurately as possible. Only then can decision-makers make a truly informed decision. Selecting only evidence that supports a preferred outcome undermines both the ethics and the value of the process.
Bias can come from many directions. Government officials, businesses, community organizations, advocates, researchers, or others may all hold strong views about a proposal. The responsibility of the HIA process is to distinguish advocacy or preference from evidence and to present uncertainty, disagreement, and limitations clearly.
Like most of the other models discussed in this chapter, HIA looks at health from a community perspective. It considers social, economic, environmental, and political conditions, as well as more direct physical influences on health, when examining the potential effects of a proposal.
Factors that may influence health include:
- Individual and biological factors, such as age, genetics, and other personal characteristics.
- Individual behaviors and circumstances, such as physical activity, nutrition, smoking, and other health-related behaviors.
- Social and community networks, including family relationships, friendships, community organizations, and faith communities.
- Living and working conditions, such as education, employment, workplace conditions, water and sanitation, transportation, and housing.
- Broader socioeconomic, cultural, political, and environmental conditions, including income, access to resources and open space, environmental quality, and social conditions.
These factors may act alone, work in combination, or interact in ways that affect the health and well-being of individuals, communities, and whole populations.
This broad view of health is consistent with longstanding public-health approaches to social determinants of health and with the conditions for health described in documents such as WHO’s The Solid Facts and the Ottawa Charter.
Themes discussed in The Solid Facts include:
- The social gradient – differences in resources, opportunity, and health across socioeconomic conditions
- Stress
- Early life
- Social exclusion and social connection
- Work
- Unemployment
- Social support
- Substance use and related harms
- Food
- Transport
The Ottawa Charter identifies basic conditions and resources for health including:
- Peace
- Shelter
- Education
- Food
- Income
- A stable ecosystem
- Sustainable resources
- Social justice
- Equity
Attention to social determinants greatly increases the breadth of what we might consider a health impact. Some impacts are direct – industrial emissions or contaminated water, for example, may contribute to specific health problems. Others are indirect and may be less immediately visible.
Increased traffic resulting from a development may raise noise levels, affect sleep, increase injury risk, or change opportunities for walking and bicycling. A major economic change may affect employment, income, stress, housing stability, or access to services. These effects may then influence health even though they are not medical interventions themselves.
That’s why an HIA can be so important. In the best case, it can help prevent or reduce negative health consequences and strengthen positive ones. Even when a project or policy cannot control every factor involved, identifying possible effects can help decision-makers plan for them, reduce harm where possible, and consider opportunities to improve health.
HIA is now an established approach used in many settings around the world. It may be conducted as a stand-alone process or incorporated into environmental, strategic environmental, social, or other forms of impact assessment. How frequently it is used, whether it is voluntary or required, and how formally it is incorporated into decision-making vary across countries and jurisdictions.
Why would you conduct a Health Impact Assessment?
HIAs, particularly comprehensive ones, can require considerable time, effort, and resources. Why invest in them? There are a variety of answers to this question.
- HIAs can support better decisions. An HIA provides decision-makers with relevant information about the potential health effects of the project or policy they’re considering. Identifying likely effects ahead of time can reduce surprises and make it easier to address problems before they become harder or more expensive to correct.
- HIAs promote cross-sector cooperation. Government agencies and other organizations concerned with health, agriculture, industry, education, transportation, housing, recreation, human services, and other areas may not routinely plan together. An HIA can bring these sectors together around a common decision.
An HIA for a transportation project, for example, might bring together highway engineers, public health officials, environmental organizations, residents near existing and proposed routes, water or utility agencies, farmers or property owners, planners, businesses, and others to examine different aspects of the proposal. Some of the relationships developed through that process may continue after the HIA is complete and support collaboration on future issues.
- HIAs raise the profile of health and health issues, making it more likely that health will be considered in decisions outside the health sector. By bringing health impacts to the attention of government officials, developers, businesses, organizations, and community members, an HIA can reinforce the idea that decisions about transportation, housing, employment, land use, and other areas can also be health decisions.
- HIA supports a participatory approach that values community knowledge and involvement. People affected by a project or policy can contribute information about local conditions, concerns, and priorities and, where possible, participate in planning the HIA and developing recommendations.
Meaningful community participation can increase the amount and variety of knowledge brought to the process, identify issues that might otherwise be missed, strengthen transparency and trust, and make it more likely that people understand how a final decision was reached.
- HIAs can bring people and organizations together. By examining health impacts across different parts of a community and involving people from different sectors and perspectives, an HIA can build relationships among people who might otherwise have little opportunity to work together.
Through a participatory process, an HIA can bring community leaders and advocates together with government agencies, developers, businesses, and others to discuss differences, identify shared concerns, and build relationships that may support collaboration on other projects and policies.
- HIAs promote equity. One of the governing values of HIA is attention to how health effects are distributed. An overall improvement in health can still leave some groups carrying a disproportionate share of negative impacts. An HIA asks not only, “What is the health effect?” but also, “Who experiences the benefit, and who experiences the harm?”
- HIAs can promote healthy conditions and practices. The point of an HIA is not only to identify and prevent negative effects, but also to identify opportunities to strengthen positive ones. A new housing development, for example, might reduce exposure to harmful building materials while also including safe walking and bicycling routes, accessible green space, and other features that support health.
- HIAs can be used in many different situations. HIAs can be adapted for individual local, regional, or national projects; long-term plans; programs; and policy decisions. Because the process is flexible, it can be used in a wide variety of sectors and circumstances.
- Prospective HIAs provide information before a decision is finalized, leaving time to adjust plans. This can help address concerns earlier, reduce avoidable harm, identify opportunities for improvement, and potentially prevent later conflict or costly changes.
- HIAs can promote sustainable development and environmental responsibility. Because the physical environment, climate, natural resources, and community conditions influence health, HIA recommendations may address open space, transportation, energy, pollution, noise, building materials, land use, and other environmental factors.
- HIA is adaptable to the needs of many different groups. Governments can use HIAs to understand potential health consequences of proposed decisions. Contractors and developers can use them to identify health-related risks and opportunities before projects are finalized. Communities and community organizations can use them to make health a more visible part of decisions that affect them. Advocates can use the HIA process to make sure the experiences and needs of groups likely to experience greater effects are considered.
- HIA assists policy development. An HIA helps ensure that health is considered when policies are developed and that possible intended and unintended consequences are examined before implementation.
- HIA can help decision-makers meet impact-assessment requirements. In jurisdictions where laws, regulations, permits, or planning processes require consideration of health or related impacts, HIA methods can help decision-makers gather and organize the information needed.
- HIA recognizes that health is one of several considerations involved in many decisions. Economic, environmental, logistical, social, legal, and other factors may also matter. The purpose of an HIA is to make health consequences visible so they can be considered openly alongside those other factors – including who receives the benefits and who bears the risks.
- HIA is a proactive process intended to strengthen positive outcomes and reduce negative ones. It gives decision-makers an opportunity to consider health and well-being while a project, plan, program, or policy is still being shaped.
When should you conduct a Health Impact Assessment?
As discussed earlier, an HIA may be prospective – conducted before the project or policy is implemented – or may be used concurrently or retrospectively to examine an action already underway or completed. The ideal for decision support is a prospective HIA. Gathering and analyzing information before a decision is finalized makes it more likely that findings can influence the outcome.
The best time to initiate an HIA is therefore during the planning and decision-making process, before implementation has advanced so far that meaningful alternatives are no longer possible. Later assessment can still provide useful information and may lead to corrections or improvements, but changing a project or policy after implementation is generally more difficult than improving it beforehand.
Who should be involved in conducting a Health Impact Assessment?
There are actually two ways to answer this question. The first concerns who should be included in a participatory HIA process. The second concerns who should actually lead and conduct the assessment – a substantial amount of work, some technical and some relational. We’ll look more closely at the second question in the how-to part of the section and focus here on who should be included in the process.
A truly participatory process is one in which relevant stakeholders have meaningful opportunities to contribute rather than being included only symbolically. Depending on the scope of the HIA, stakeholders may help identify concerns, contribute evidence and local knowledge, review findings, participate in planning, and help formulate recommendations.
Stakeholders may include:
- People directly affected by the proposed action or policy. These may include several groups:
- Members of the population a proposed intervention or change is intended to reach, where applicable.
- People living, working, studying, or spending time near a proposed project who may be directly affected by construction, traffic, environmental changes, displacement, noise, or other effects.
- Populations that may experience greater health risks or barriers, such as children, older adults, people with disabilities, people with lower incomes, and communities that have historically been underrepresented in decision-making.
- Residents, community organizations, and officials in the areas where proposed projects or programs would take place.
- Residents and organizations in neighboring communities that could also experience effects, such as changes in traffic, employment, pollution, housing, or use of public resources.
- Those involved in carrying out the proposed actions or policies. These are people and organizations responsible for implementing the project or policy. Some possibilities include:
- Private developers and construction firms
- Local, regional, tribal, state, or national government agencies and officials
- Planners
- Public safety, health, and other public-service providers
- Nonprofit and nongovernmental organizations (NGOs) concerned with the issues or populations affected. These organizations may have direct experience providing services, working with communities, or understanding local conditions. Their knowledge can help identify potential effects that might otherwise be overlooked.
- Advocacy groups. Whether their focus is a particular issue, population, or community, advocacy groups may have relevant evidence, experience, or perspectives and should have opportunities to contribute where appropriate.
- The decision-makers themselves. These are the agencies, developers, planners, officials, boards, or others who control the design or implementation of the proposal. They understand such practical considerations as budgets, timelines, regulatory requirements, and the range of options actually available.
- Government agencies with responsibilities related to the issue or populations involved. Their involvement may be important both for the evidence they hold and for the role they may have in implementing decisions.
- Representatives of other sectors affected by the proposal. An agriculture project, for example, may affect water, transportation, employment, housing, land use, or the environment. Including relevant sectors helps create a fuller picture of possible consequences.
- Public-health and health professionals at the appropriate local, regional, national, or international levels. They can contribute expertise related to health impacts, population health, health data, and the interpretation of health risks and benefits.
- Employers, workers, and labor organizations. People who understand workplace conditions and the practical realities of implementing a project may provide useful information about feasibility, occupational health, and potential effects on workers.
- The commissioner or commissioners of the HIA. These are those who initiate and, in many cases, fund the assessment. They might include a government, developer, organization, agency, or partnership.
- Those who actually conduct the HIA. The practitioners carrying out the assessment are obviously involved in its planning, evidence review, analysis, reporting, and communication.
How do you conduct a Health Impact Assessment?
An HIA has both institutional and practical aspects, and they can’t really be separated. The institutional aspects concern whether decision-makers support the process, how it relates to existing decision-making procedures, how it will be funded, and whether agencies and organizations are willing to cooperate. The practical aspects concern gathering participants, planning the process, obtaining and analyzing evidence, and communicating findings and recommendations.
Institutional aspects of conducting an HIA
- For HIA to become a routine and useful part of decision-making, public officials, agencies, organizations, and other decision-makers need to recognize several basic concepts:
- Health is important enough to be considered in projects and policies that may affect it.
- Health is not only an individual matter, but can be influenced by community, regional, national, and international conditions.
- Health involves more than the absence or treatment of disease and injury; it also includes mental, social, and broader aspects of well-being.
- Social, economic, environmental, and other determinants of health can be important to individual and community well-being.
- Health often crosses the boundaries of any one agency or sector. Understanding health impacts may require collaboration among public health, transportation, housing, environment, planning, education, economic development, and other sectors.
- Good decisions depend on the best and most complete information reasonably available.
- Institutional support can help make HIA more consistent. HIAs can be voluntary or may be incorporated into laws, regulations, planning requirements, permitting processes, or organizational policies. Where HIAs are formally required or routinely used, clear standards can help define when an HIA should be conducted, what it should include, and how affected communities and other stakeholders should be involved.
- HIAs have to be paid for. A reliable way of financing an HIA is important if it is expected to be conducted thoroughly and independently. Funding might come from a public agency, the entity proposing a project, a dedicated public budget, or another appropriate source.
When a developer, corporation, contractor, government agency, or other interested party funds an HIA, safeguards should be in place to protect the independence and credibility of the assessment. Who pays should not determine what the evidence says.
- Government agencies and other sectors often have to collaborate for an HIA to provide a complete picture. A commercial development, for instance, might involve health, environmental quality, transportation, employment, agriculture, housing, utilities, land use, and other sectors.
Agencies and organizations have different mandates and responsibilities, and cooperation does not always happen automatically. An HIA can provide a structure for sharing relevant information and examining how decisions in one sector may affect another.
- Decision-makers and agencies should create meaningful opportunities to hear from people who will be affected. Community involvement can contribute information that professional or administrative sources may not contain, improve transparency, identify potential problems early, and strengthen trust in the process.
Practical aspects of conducting an HIA
There is no single prescribed way to conduct an HIA. Each assessment should be adapted to its context – the proposal, the population and geographic area affected, the sectors involved, available evidence, the time before a decision must be made, and the level of public concern.
Current HIA guidance sometimes divides the process into four, five, or six stages. The differences are largely a matter of whether such activities as recommendations, reporting, monitoring, and evaluation are separated or combined. For consistency with this section, we’ll use five broad stages.
The first task is to determine who will conduct the HIA. Ideally, those responsible should have appropriate HIA training or experience or have access to people who do. Useful backgrounds may include public health, planning, environmental health, social science research, public administration, community development, or related areas.
HIA practitioners also need skills that aren’t simply technical. They should be able to communicate with people from different backgrounds, work across agencies and organizations, understand and evaluate research, facilitate discussion, deal constructively with disagreement, and communicate uncertainty clearly.
Experience matters as well. Working alongside someone who has conducted a successful HIA can provide practical knowledge that is difficult to gain through written guidance alone.
Independence is important. Those conducting an HIA may be funded by or connected to organizations involved in the decision, but the assessment should include safeguards against pressure to reach a particular conclusion. Potential conflicts of interest should be identified and handled transparently.
For this section, HIA consists of five broad stages:
- Screening
- Scoping
- Assessment
- Reporting and recommendations
- Evaluation and follow-up
We’ll look at each separately and describe some general guidelines that can help you understand and carry out the process.
- Screening. A proposed project, plan, program, or policy is examined to determine whether an HIA would be useful. An HIA may not be needed when health effects are negligible, already well understood and appropriately addressed, or when the assessment would arrive too late to influence the decision.
Screening is the first – and sometimes the last – task in the HIA process. Whoever performs the screening should be able to judge the health relevance of the proposal while avoiding conflicts of interest. If the same consultant who would be paid to conduct the HIA also decides whether one is necessary, for example, that potential conflict should be recognized and managed.
- Scoping. Scoping is the planning stage of the HIA. Here, you identify the ways the decision could potentially affect health, the people and groups who may be affected, the health impacts that should be examined, the evidence and expertise needed, the time and resources available, and how the assessment will be conducted. At the end of scoping, you should have a clear plan for the HIA.
As we’ve discussed, there’s no one way to conduct an HIA. What follows is one logical way to structure the scoping process, but it shouldn’t be taken as the only way.
- Using existing knowledge, early evidence, and community concerns, identify possible positive and negative health impacts of the proposed project or policy.
- Determine the sectors, populations, groups, and individuals that need to be consulted or involved.
- Assemble an appropriate group to help plan and guide the HIA, with meaningful participation from people affected by the proposal whenever possible.
An inclusive and participatory process is the ideal. The amount and form of participation may vary with the timeline and scope of the HIA, but a short deadline shouldn’t be used as a reason to ignore the knowledge and concerns of affected communities.
One advantage of a team approach is that it can build relationships across sectors. Those relationships may make the HIA easier to conduct and may also support cooperation in future work.
- Become familiar with the current state of the project or policy and the decisions that remain open. Can the proposal be changed? Are some parts fixed? Are there alternatives? What is the proposal intended to accomplish? What benefits are expected, and for whom? Which populations could experience positive or negative effects?
- Determine what evidence is needed. Different HIAs will need different kinds of information. Some may rely heavily on interviews, local knowledge, and existing data. Others may require environmental monitoring, traffic analysis, epidemiologic evidence, geographic information, or other specialized information.
- Existing evidence. This may include research, population and geographic data, statistics, previous assessments, agency records, planning documents, and other information available from professional publications, libraries, agencies, institutions, or online sources.
HIA practitioners often consider both published research and “gray literature” – useful evidence that has not been formally published in an academic journal. Gray literature might include government reports, internal program evaluations, technical reports, community assessments, planning documents, data collected by organizations, or other credible sources.
- Evidence that needs to be gathered. This might include information about physical conditions, transportation, utilities, proximity to homes or community spaces, local economic and social conditions, or experiences of affected community members. Interviews with community leaders, residents, organizations, workers, and others may provide information not available in existing data.
- Assign responsibilities for each part of the HIA. Everyone should understand their role – planning and oversight, specific research or data tasks, community engagement, meeting participation, interviews, analysis, or other responsibilities – and the time frame involved.
- Assessment. Up to this point, you’ve been planning. Now it’s time to gather and analyze the evidence and estimate the nature, direction, magnitude, likelihood, and distribution of potential health impacts.
- Review existing evidence. Track down and evaluate relevant studies, reports, data, and other available evidence. The reviewer has a responsibility to consider the quality of the evidence and whether conclusions are supported by the methods and data used. Weak or uncertain evidence should not automatically be discarded, but its limitations should be clearly identified.
Key steps in undertaking an objective and methodical review include:
- Using a clear and consistent approach to guide the process
- Being systematic
- Focusing on specific questions
- Assessing the quality and relevance of the evidence
- Analyzing and combining findings
- Presenting clear conclusions, uncertainties, and recommendations
Following these steps supports one of the key values behind HIA: the ethical use of evidence.
- Familiarize yourself with the proposed project or policy. Where appropriate, visit sites and affected areas. Study maps, plans, proposed routes, technical documents, and other relevant materials. Learn about the communities involved, local conditions, connections with neighboring areas, applicable laws and regulations, the goals of the proposal, and the assumptions being made about its expected benefits and costs.
- Learn what the realistic range of options is. Some proposals may be open to major changes or even cancellation. Others may have fewer alternatives. Be clear about which parts of the proposal are fixed, which can change, and whether additional options could reasonably be considered.
- Conduct individual and group interviews, hold meetings, administer surveys, and use other appropriate methods to gather evidence and obtain community input.
People affected by the decision should be kept informed throughout the process. They should know that an HIA is being conducted, who is involved, how they can participate, what questions are being examined, and how findings will be communicated. Transparency helps people understand the process and reduces the likelihood that decisions will appear to be made behind closed doors without their knowledge.
- Gather or compile additional data necessary for a fuller picture of the situation. Where time and resources permit, this might include conducting additional research specifically for the HIA.
- Gather relevant information from agencies, nonprofit organizations, businesses, institutions, research organizations, and other groups with knowledge related to the geographic area, population, sector, or issue under review.
- Assess the potential impacts of the proposed project or policy on affected populations. This is, in some sense, the meat of the HIA. Once the evidence has been gathered, it needs to be analyzed to understand possible positive and negative health effects, who may experience them, how significant they may be, and how certain the available evidence is.
A development or policy that displaces people from a neighborhood and disrupts social networks may affect health through housing instability, stress, loss of social support, or economic change. An industrial development may affect air quality locally or farther away, while also creating employment or other economic opportunities. These effects can point in different directions and may not be distributed evenly across the population.
That is one reason an HIA can be useful. It is not meant to tell decision-makers automatically what to do, but to make the different potential effects visible so that decisions can be made with a fuller understanding of their consequences.
An HIA can also help guide a proposal in a positive direction by identifying alternatives or design choices that strengthen potential health benefits rather than simply reducing harm.
- Determine the potential impacts associated with different options. Predictions will rarely be perfect. Their usefulness depends on the quality of the evidence, the expertise involved, the assumptions made, the amount of uncertainty, and how carefully different perspectives and forms of evidence have been considered.
Some basic questions can help in thinking about options. If the current plan carries a possible negative health impact, can that impact be reduced or eliminated? Are alternatives practical? What do they cost? Who benefits from each option? Who may experience harm? Can a negative effect be turned into a positive one?
Creating a pedestrian-oriented area in a development, for example, might reduce traffic-related injury risk while also supporting walking, physical activity, social interaction, and community connection.
Asking these kinds of questions and weighing the answers provides a base for developing options and recommendations.
- Reporting and recommendations. Once the evidence has been analyzed, findings should be communicated to the people who commissioned the HIA, decision-makers, stakeholders, and affected communities. The report should explain the proposal, the HIA process, evidence, findings, uncertainties, options considered, and recommendations for reducing negative health effects and strengthening positive ones.
Recommendations should follow from the evidence. This means making clear distinctions between evidence, interpretation, and preference; using relevant and credible information; acknowledging uncertainty and conflicting findings; and considering practical issues such as feasibility, resources, timing, and the broader goals of the proposal.
HIA may reveal competing interests or tradeoffs. That is not a failure of the process. Sometimes the evidence does not point to one obvious answer. The HIA’s job is to make the health implications of those choices as clear as possible, including how benefits and harms may be distributed across different groups.
The report should be understandable to the people who will use it. Technical information may need to be included in the complete report, but findings and recommendations should also be communicated in accessible language. People who may be affected by the proposal should be able to understand what was examined, what was found, what uncertainties remain, and how their concerns were considered.
Findings should be presented directly to decision-makers in a way that allows questions, discussion, and clarification.
The report should also be easy for stakeholders and community members to access. Depending on the size and nature of the HIA, that might mean posting the report online, providing summaries through community organizations and libraries, sharing information at public meetings, or using other appropriate communication channels.
It’s also important for everyone – from decision-makers to the general public – to understand that an HIA is not a directive. Decision-makers may accept, modify, or reject recommendations, but the process is most transparent when they explain how the HIA was considered and why particular decisions were made.
- Evaluation and follow-up. The HIA itself should be evaluated to understand how well it was conducted, whether it influenced decision-making, how recommendations were handled, and what could be improved in future assessments. Follow-up can also include monitoring whether agreed-upon recommendations are implemented and, where feasible, examining actual health effects after the decision takes effect.
The HIA process can be evaluated along several lines. How well did it reflect the guiding values of democracy, equity, sustainable development, and ethical use of evidence? How inclusive and participatory was it? Were stakeholders meaningfully involved? Did it encourage cooperation among sectors? Were responsibilities clear?
Did the analysis consider relevant evidence? Did conclusions accurately reflect what the evidence could and could not show? Were social, economic, environmental, and other determinants of health considered? Were the experiences and concerns of affected people taken seriously? Were competing health considerations acknowledged?
Did the recommendations follow logically from the findings? Were they realistic in terms of resources, logistics, law, policy, and feasibility? Did they consider who might experience greater benefits or harms?
Were recommendations adopted or acted upon? If not, why not? If they were, how were they implemented? How useful did decision-makers and community stakeholders find the HIA?
The actual health outcomes of the project or policy may also be monitored, although this may become part of the evaluation of the project or policy itself. Ongoing evaluation can help determine whether original assumptions were accurate and whether recommendations should be revisited or revised.
Conditions, populations, technology, environments, and economic circumstances change, and health effects may change with them. New information can emerge, new risks may appear, and old assumptions may prove incomplete. Continued monitoring and attention to HIA findings can help projects and policies remain responsive to the health and well-being of the communities they are intended to serve.
In Summary
Health Impact Assessment (HIA) is a process for understanding and making recommendations about the possible health impacts of projects, plans, programs, and policies. It draws on scientific evidence, local knowledge, community perspectives, and information from the different sectors involved in a decision.
An HIA is not meant to dictate what decision-makers must do. Rather, it provides information about possible health consequences – positive and negative, direct and indirect – and about how those consequences may be distributed across different populations. Decision-makers can then consider that information alongside the other factors involved in the decision.
HIAs are guided by the values of democracy, equity, sustainable development, and the ethical use of evidence. They work best when they are conducted early enough to influence a decision, when affected communities and other stakeholders can participate meaningfully, and when findings, limitations, and recommendations are communicated transparently.
This section presents the HIA process in five broad stages:
- Screening – determine whether an HIA would be useful.
- Scoping – decide what the HIA will examine, who should be involved, and how the assessment will be carried out.
- Assessment – gather and analyze evidence about potential positive and negative health effects and their distribution.
- Reporting and recommendations – communicate findings and recommend ways to reduce harm and strengthen health benefits.
- Evaluation and follow-up – assess the quality and influence of the HIA and, where appropriate, monitor implementation and health effects over time.
A well-conducted HIA can contribute not only to better-informed projects and policies, but also to stronger communication, cross-sector collaboration, meaningful community participation, greater attention to equity, and decisions that more fully consider the health and well-being of the people they affect.
Resources
Online Resources
APHA's Health Impact Assessment Fact Sheet. A tool to ensure that health and equity are considered in transportation policy and systems.
Health Impact Project offers a full page of assessment case studies from around the United States.
The Chronicles of Health Impact Assessment (CHIA) is an open access online journal. This peer-reviewed periodical has been created with the intent to serve the public health profession and encourage health in all policies. The journal strives to give expression to health impact assessment research and scholarship to serve public health and planning professionals.
Growing the Field of Health Impact Assessment in the United States: An Agenda for Research and Practice. (U. of California, Berkeley, School of Public Health). Andrew L. Dannenberg, MD, MPH, Rajiv Bhatia, MD, MPH, Brian L. Cole, DrPH, Carlos Dora, PhD, Jonathan E. Fielding, MD, MPH, Katherine Kraft, PhD, Diane McClymont-Peace, MS, Jennifer Mindell, MBBS, PhD, FFPH, Chinwe Onyekere, MPH, James A. Roberts, PhD, CEP, Catherine L. Ross, PhD, Candace D. Rutt, PhD, Alex Scott-Samuel, MB, CHB, MCommH & Hugh H. Tilson, MD, DrPH. From the American Journal of Public Health, February 2006, Vol 96, No. 2, pp. 262-270.
A Guide for Health Impact Assessment by the California Department of Public Health.
Health Impact Assessment (HIA) is a key strategy that supports organizations and governments to identify and integrate health-promoting policies and practices so that health becomes a key component in all community decision-making.
The Health Equity Impact Assessment from the Lawrence-Douglas County Health Department is an assessment tool used to identify unintended impacts of an existing policy on equity issues. The pdf version can be accessed here.
Health Impact Assessment and Housing: Guidance for health and housing professionals is a set of issue briefs that highlight ways to integrate the consideration of health into housing policy and projects through the use of HIAs.
Health Impact in the United States. This website offers an interactive map of Health Impact Assessments in several sectors that have been implemented all over the United States.
Health Impact Project's Toolkits and Guides.
Health Inequalities Impact Assessment - An approach to fair and effective policy making: Guidance, tools and templates contains a guidance document (HIIA: An approach to fair and effective policy making), information about legislative requirements, a workbook for workshop participants and a summary version of the workbook, guidance for workshop facilitators and a document with key issues to consider, a process workplanner and templates for the scoping workshop scribe, and the workshop report and the final report, from NHS Health Scotland, a national Health Board working with public, private and third sectors to reduce health inequalities and improve health.
Improving Health in the United States: The Role of Health Impact Assessment. This book from the National Research Council and Committee on Health Impact Assessment, available for free online, offers guidance to officials in the public and private sectors on conducting Health Impact Assessments.
The report presents a six-step framework for conducting Health Impact Assessment of proposed policies, programs, plans, and projects at federal, state, tribal, and local levels, including within the private sector. In addition, the report identifies several challenges to the successful use of Health Impact Assessment, such as balancing the need to provide timely information with the realities of varying data quality, producing quantitative estimates of health effects, and engaging stakeholders. In addition to the guidance on evaluating public health consequences of proposed decisions -- such as those to build a major roadway, plan a city's growth, or develop national agricultural policies -- the report also suggests actions that could minimize adverse health impacts and optimize beneficial ones.
Is Health Impact Assessment Effective in Bringing Community Perspectives to Public Decision-Making? from the PEW Charitable Trusts. Lessons from 4 case studies in California
While geared toward its own region, the Mid-Michigan Health Impact Assessment Tool Kit is available to professional planners and the public and includes documentation that allows users within the region to download, replicate, and adapt HIA as a practice in their communities.
New Guides Help Bring Health Considerations Into Industrial Projects from the PEW Charitable Trusts. Tools can boost community health and businesses’ bottom lines.
UCLA Health Impact Assessment Clearinghouse. UCLA offers several completed HIAs for transportation policies.
U.S. Centers for Disease Control HIA page, with a number of references.
The U.S. Environmental Protection Agency offers case studies, tools, and policies related to Health Impact Assessments.
Wikipedia article on HIA, including a number of references.
The World Health Organization website on HIA.
Print Resources
Wilkinson, Richard & Marmot, Michael (2003). Social determinants of health: the solid facts, 2nd ed. World Health Organization. Regional Office for Europe. https://iris.who.int/handle/10665/326568
Wismar, M., Blau, J., Ernst K., & Figueras, J. (eds.). The Effectiveness of Health Impact Assessment: Scope and limitations of supporting decision-making in Europe. World Health Organization 2007, on behalf of the European Observatory on Health Systems and Policies.
What is a Health Impact Assessment?
___A Health Impact Assessment is a combination of procedures, methods, and tools by which a policy, program [a series of projects over time], or project may be judged as to its potential effects on the health of a population, and the distribution of those effects within that population.
___An HIA is intended not to determine, but to support decision-making.
___An HIA may be conducted as a desktop, rapid, or comprehensive process.
___An HIA may be prospective, concurrent, or retrospective.
___HIA’s guiding values are democracy, equity, sustainability, and the ethical use of evidence.
___HIA takes a community or broader perspective on health, and considers the social, psychological, economic, environmental, and political determinants of health as important as specific health issues in assessing health impacts.
Why conduct a Health Impact Assessment?
___HIAs make for better decisions.
___HIAs promote cross-sectoral cooperation.
___HIAs raise the profile of health and health issues, and make it more likely that they’ll be considered in all circumstances.
___HIA champions a participatory approach that values, includes, and empowers the community.
___HIAs bring the community together.
___HIAs promote equity.
___HIAs promote healthy behaviors and practices.
___HIAs can be used in numerous and varied situations.
___Prospective HIAs provide information before the fact, leaving time to make adjustments in plans.
___HIAs can promote sustainable development and environmental responsibility.
___HIA is adaptable to the needs of many different groups.
___HIA policy makers address policy making requirements.
___HIA recognizes that other factors besides health guide decisions.
___HIA is a proactive process that improves positive outcomes and decreases negative outcomes.
When should you conduct a Health Impact Assessment?
___If possible, HIAs should be conducted before the proposed project or policy is fully planned or implemented, so that it can take advantage of the information the HIA provides.
Who should be involved in conducting a Health Impact Assessment?
___HIAs should involve representatives of all stakeholders.
These include:
___Those who are directly affected by the proposed actions or policies.
___Those who are involved in carrying out the proposed actions or policies.
___Nonprofit and non-governmental organizations (NGOs) concerned with the issues and/or the populations affected.
___Advocacy groups.
___The decision-makers themselves.
___Government agencies that have responsibility for the issues and/or populations in question.
___Representatives of other sectors that are affected by the proposal.
___Health workers at local, national or international levels.
___Employers and unions.
___The commissioner(s) of the HIA – those who set it in motion (and pay for it, in many cases.)
___Those who actually conduct the HIA.
How do you conduct a Health Impact Assessment?
Political aspects of conducting an HIA
___In order for HIA to become common, and particularly for it to be institutionalized, politicians and government agencies have to understand:
- That health is important enough to be integral to any project or policy that can have an impact on it.
- That health is not simply an individual issue, but has to be viewed in a larger – community, regional, national, or international – context, depending on the scope of the project or policy proposed.
- That health is more than the alleviation, elimination, or prevention of disease, injury, or medical conditions, but also includes the promotion, psychological implications, and other aspects of health.
- That the social and other determinants of health are both real and crucially important to creating a healthy community and society.
- That health transcends any one department or ministry – i.e., that more than public health agencies need to be involved in examining the health impacts of a project or policy, and that interdepartmental and inter-sectoral collaboration is necessary in order to fully understand the health impacts of projects or policies.
- That they need the best, most accurate, most nearly complete information possible in order to make good decisions that take health impacts into account.
___HIAs won’t happen with any regularity or quality control unless they’re institutionalized by a legal basis of some sort – a law, an agency regulation, a clear policy, permit requirements, etc..
___HIAs have to be paid for.
___Government agencies have to collaborate for an HIA to be of high quality.
___Government has to be willing to involve, and listen to (and heed) the concerns and advice of those who will be affected.
Practical aspects of conducting an HIA
___Choose people to conduct the HIA.
___HIA practitioners ideally are trained and experienced, or, at the very least, have the professional, interpersonal, and organizational skills needed to conduct an HIA successfully.
___HIA consists of five stages:
- Screening
- Scoping
- Assessment
- Reporting
- Evaluation.
___Screening is the examination of the project or policy to see if an HIA is needed.
___Scoping is the actual planning of the HIA – identifying ways in which the decision in question could potentially affect health (positively or negatively) – the people who might be affected, how impacts should be assessed, whose expert opinion you need to get the full picture, what resources are needed to conduct the HIA, what kinds of evidence should be gathered, etc..
___A general guideline for developing a plan might take these steps:
- Using logic, prior knowledge, and the concerns of the community, make an educated guess about the possible health impacts of the proposed project or policy.
- Determine the sectors, populations, groups, and individuals that need to be consulted and/or drawn into the process.
- Assemble a team from among them, representing all stakeholders, to plan and do the groundwork for the HIA.
- Become familiar with the current state of the project or policy, possible alternatives to current options, and the decisions that can and/or must be made.
- Assign responsibilities for all parts of the HIA.
___Perform the actual assessment.
- Review existing evidence.
- Familiarize yourself with the proposed project or policy.
- Learn what the range of options is.
- Conduct individual and group interviews, hold meetings, administer surveys, etc., to gather other evidence and obtain community input.
- Gather or compile statistics and other evidence currently unavailable which is necessary for a full picture of the situation.
- Gather information available from the various agencies, NGOs, think tanks, businesses, institutions, and other groups whose responsibilities or concerns are directly or indirectly relevant to the HIA or the issue, sector, geographic area, or population potentially affected.
- Assess the impacts of the proposed project or policy on the health of populations affected.
- Determine the impacts that come with different options.
___Compose and deliver an understandable two-part report to all stakeholders and the public, describing the HIA process and conclusions, and making recommendations for maximizing the positive health impacts and minimizing the negative health impacts of the project or policy.
___Evaluate the HIA’s effectiveness.
___Continue to use the HIA conclusions and recommendations to guide the implementation of the project or policy, making adjustments and revisions as necessary to reflect changing conditions or new information.
Example 1: American Public Health Association
The American Public Health Association has collected a variety of case studies that demonstrate how communities of all types and sizes are addressing the intersection of public health and transportation. These Health Impact Assessments offered decision-makers an opportunity to ensure that health and equity were considered when shaping transportation policy and systems. Here are several examples of HIAs conducted to evaluate transportation projects:
Example 2: Health Impact Assessment of a Freeway in San Francisco (California)
PODER (People Organizing to Demand Environmental & Economic Rights) is leading a community-based effort to improve environmental health in the Excelsior neighborhood of San Francisco. Concerns about disproportionate, adverse traffic-related health exposures, including air pollution, traffic noise, and safety hazards led PODER to work with researchers in the San Francisco Department of Public Health’s (SFPDH) Program on Health, Equity and Sustainability and the UC Berkeley School of Public Health (UCB). Together they conducted a community-based health impact assessment (HIA) of traffic and the transportation system in this neighborhood which has led to local governmental action to re-assess truck routes and transportation system design in the neighborhood.
Example 3: Atlanta (Georgia) Beltline Health Impact Assessment
In Atlanta, authorities used a health impact assessment (HIA) to guide plans for a major redevelopment along the city’s beltline. The results of the study encouraged city officials to fund design elements such as improved transit services, access to green space and healthy foods, new opportunities for physical activity, and affordable housing, in response to health considerations.
Example 4: Non-Motorized Transportation Pilot Program (NMTPP)
The Federal Highway Administration (FHWA) funded four communities across the U.S. in an effort to demonstrate the benefits from improved walking and bicycling networks. Some of the outcomes that are tracked include changes in 1) vehicle and transit use; 2) rates of walking and bicycling; and 3) health and environmental measures. The four communities are listed below; additional information is available by clicking the links:
- Marin County, California: Walk Bike Marin
- Minneapolis, Minnesota: Bike Walk Twin Cities
- Sheboygan County, Wisconsin: Non-Motorized Transportation Pilot Project
Example 5: Safe Routes for Seniors (New York)
In 2003, The NYC Department of Transportation partnered with Transportation Alternatives to create the Safe Routes for Seniors campaign, aiming to address the disproportionately high rate of senior pedestrian fatalities in NYC, and encourage senior citizens to walk more. Their recommendations focused on taking into account the sensory and physical changes that occur with age when designing streets and included installing medians and high-visibility crosswalks, repairing and extending curbs and pedestrian ramps, keeping streets as flat as possible, and increasing the time allowed for pedestrians to cross the street. Since the implementation of this program, pedestrian fatalities and crashes in all areas included in the campaign have decreased by 9% to 60%.
Example 6: Bicycle Transportation Alliance (Oregon)
The Bicycle Transportation Alliance strives to create healthy and sustainable communities by promoting the use of bicycles as a mode of transportation, with the idea that this shift will benefit the environment, livability, and community health. The Alliance works through both advocacy and education to achieve this goal. BTA offers biking safety courses in 4th through 7th grade classrooms and pedestrian safety courses made available to both adults and youth. Through these courses students are able to learn about traffic rules, bikes and helmets, and develop informed expectations regarding pedestrian and vehicle behavior in school and pedestrian zones. BTA is also active in promoting Oregon’s Bike + Walk to School Program, which reaches out to children and their families through school districts in an attempt to encourage the safe use of active transportation to and from school.
Example 7: Urban Street Design Guidelines (North Carolina)
Charlotte, NC, has worked to integrate its Urban Street Design Guidelines (USDG) into zoning and subdivision codes, which would require developers to follow them, ensuring a well-connected network of complete streets. USDG allows for flexibility in the implementation of complete streets in order to ensure that each street is completed in the most useful and efficient way possible. At the end of 2009, Charlotte had completed 16 complete streets projects and was in the middle of 18 more. Successes so far include 11 modified intersections (with 10 more planned), 15 new sidewalks (40 more planned), and over 50 miles of bike lanes.
Example 8: PLACE: Policies for Livable, Active Communities and Environments (California)
The PLACE Program was developed by Los Angeles County Public Health Department in 2006 in response to the growing prevalence of chronic conditions associated with the built environment—such as obesity, respiratory illness and diabetes—among LA residents. The program works to initiate policy change that will reduce the number of individuals and communities subject to poor air quality, physical inactivity, and poor nutrition by improving the built environment. In order to do so, PLACE has provided grants to five separate city government and non-profit agencies to help them pursue development projects in their own communities. Previous successes include the creation of a Bicycle and Pedestrian Master Plan as part of a health and wellness component of one city’s General Plan.
Example 9: Health Impact Assessments in the United States
The Health Impact Project offers an interactive map of Health Impact Assessments that have been implemented throughout the United States. You can choose a region of the map and see what projects are occurring in that area, or customize the map by filtering the projects by status, organization type, decision-making level, and sector.
Example 10: Caño Martin Peña Health Impact Assessment (San Juan, Puerto Rico)
The Icahn School of Medicine at Mount Sinai’s Pediatric Environmental Health Specialty Unit in New York City conducted an HIA to inform Puerto Rican policy makers on their decision to fund a comprehensive development plan for improving sanitation infrastructure, as well as dredging and removing heavily polluted sludge from a two-mile stretch of the Caño Martin Peña. The assessment’s purpose is to ensure that public health information and community health concerns are considered in the decision-making process.
Example 11: Madison Heights Health Impact Assessment (Arizona)
This Health Impact Assessment was conducted on the redevelopment of Madison Heights, a public housing unit near Phoenix, Arizona. It examines the potential health effects of the development proposal through access to transportation, access to recreation, youth engagement, crime, and safety.
Example 12: Health Impact Assessment on Liquor License Expansion (Kansas)
The Kansas Health Institute conducted an assessment examining the potential positive and negative health effects of proposed legislation that expands liquor licenses to grocery and convenience stores in Kansas. The study analyzed eight health issues related to this bill including alcohol consumption; alcohol consumption in youth; Driving Under the Influence (DUI) arrests; alcohol-related traffic accidents; alcohol-related traffic deaths; alcohol-related traffic deaths in youth; crime, and Sexually Transmitted Diseases (STDs).
Example 13: The Ohio Housing Finance Agency’s Health Impact Assessment report on affordable housing
This HIA will inform the revision of compliance rules and policies for housing inspections, both within OHFA's state-level compliance standards, and at the federal level. It will also guide decisions on a proposal to improve interagency coordination and streamline the current system for housing inspections on affordable housing units.
Example 14: Shared-use Roosevelt: Unlocking Opportunities
Through this community-oriented project called Shared-use Roosevelt, made possible through a Health Impact Assessment, we see how a neighborhood benefits when diverse partners work together on a common goal: making school district properties accessible to the community. By opening up a vacant lot, a wellness center, and a greenhouse to the public, neighbors are able to come together, families can access healthier food and recreation opportunities, and a neighborhood can build itself up.
Example 15: Kern County’s Land-Use & Transportation Plan
Kern County, California is a central to America’s agriculture industry, but it’s also home to high rates of poverty and poor health outcomes. Rural areas like Lamont face especially high rates of asthma, obesity, cardiovascular disease, and cancer. With support from the Health Impact Project and The California Endowment, the community conducted a health impact assessment (HIA) to inform land use and transportation decisions at the county level.
Example 16: Health Impact Assessment Helps Families Replace Unsafe Manufactured Housing
In Curry County, along Oregon’s southern coast, numerous families live in poverty, and over thirty percent of county residents live in manufactured homes that have exceeded their intended lifespan. Forty percent of the manufactured homes are substandard and didn’t qualify for improvement services provided by the U.S. Department of Housing and Urban Development and the state of Oregon.
County officials recognized that families living in older manufactured homes were suffering more frequently from injuries like falls and from respiratory conditions such as asthma; they decided to launch a health impact assessment to inform a proposed pilot project called the Housing Stock Upgrade Initiative. The initiative would provide lower-cost loans or other funds to make repairing or replacing a manufactured home more affordable to Curry County residents.
Contributed by Lia Thompson, University of Kansas, Community Tool Box Intern.
Example 17: Health Impact Assessment Community Commons Space and Resources
The Community Commons Space is a content library powered by the Community Commons Knowledgebase and hosted by the Institute for People, Place, and Possibility (IP3) aiming to support communities, agencies, and other organizations in taking action to improve public health. While conducting a formal HIA can be costly, the Space seeks to simplify the process of researching existing HIAs so policymakers and community organizers can maximize resources. By building on others’ work and applying previously conducted HIA's results, policies, programs, plans, and projects can move more quickly into implementation.
Housing approximately 400 HIA's (which are searchable and filterable by criteria and geographic location), as well as hundreds of guides, reports, and datasets for the field, the Space seeks to help users consider health, well-being, and equity in all policies and investments, and make good decisions regarding matters that impact people’s health.
Introduction: What is Health Promotion?
Health promotion is defined by the World Health Organization (WHO) as “a process of enabling people to increase control over their health.” This idea is put into practice using participatory approaches, with individuals, organizations, communities, and institutions working together to create conditions that support health and well-being for all.
In its simplest terms, health promotion fosters changes in environments and systems that help promote and protect health. These may include, for example, programs that improve access to health services or policies that support public parks and other spaces for physical activity and social connection.
Health promotion involves a particular way of working together. It is:
- Population-based: Health promotion considers health in terms of the whole population; that is, all the people who share a place, such as a municipality or region, or an experience or characteristic, such as being young, experiencing poverty, or experiencing increased risk for a particular outcome.
- Participatory: Health promotion involves the collaboration of community stakeholders in the selection, planning, implementation, evaluation, and maintenance of health-promoting interventions, policies, and conditions.
- Intersectoral: Health promotion engages different sectors of the community – community members, businesses, government institutions, faith communities, and nongovernmental organizations such as health and human service organizations and social and cultural organizations – in making health-promoting changes in their programs, policies, and practices.
- Sensitive to Context: Health promotion takes into account relevant aspects of the place and time, including history, demographics, past experience, geography, culture, politics, economics, social structure, and other important factors.
- Multi-level: Health promotion operates at many different levels – individual and relationship, organizational, community, and broader system – to achieve population-health goals.
The ultimate goal of health promotion is the continued improvement of health-related conditions and health across the population, with particular attention to people and communities experiencing marginalization, exclusion, or other barriers to health.
Social Determinants of Health—Ottawa Charter and the WHO Commission on Social Determinants of Health
A WHO conference in Ottawa, Canada, in 1986 adopted the Ottawa Charter, a document recognizing that health is not simply the product of medical care or conditions directly related to health. Rather, health is influenced by a complex set of social, economic, and environmental conditions. The Ottawa Charter identified these fundamental conditions and resources for health:
- Peace
- Shelter
- Education
- Food
- Income
- A stable ecosystem
- Sustainable resources
- Social justice
- Equity
In its final report in 2008, the WHO Commission on Social Determinants of Health focused attention on social conditions that contribute to inequities – unfair and avoidable differences in health outcomes. These included:
- Unequal distribution of power, income, goods, and services: People and groups with fewer economic, social, or political resources may experience greater exposure to stressors and health-damaging conditions.
- Social exclusion or marginalization: Some groups – for example, Indigenous Peoples and people experiencing discrimination – may face barriers to social, economic, and material resources that can protect and promote health.
To promote health equity, the WHO Commission recommends:
- Improving daily living conditions. This includes supporting early childhood development and education, expanding access to schooling for people who face barriers, and reducing exposure to harmful conditions such as environmental hazards, inadequate housing, violence, and chronic stress.
- Strengthening social protection. This includes policies and systems that help make a healthy standard of living possible for everyone.
- Health promotion works on the principle that population health is a product not only of addressing specific health needs, such as access to primary health care, but also of addressing broader social determinants. This principle underlies health promotion and continues to inform the work of WHO, PAHO, and other public-health organizations.
What is evidence of health promotion's effectiveness?
In this context, “evidence” refers to information indicating whether and how efforts to promote health are working. Establishing an evidence base for health promotion can present particular challenges:
- Health promotion initiatives can be difficult to document. Health promotion may involve multiple partners working at multiple levels to change programs, policies, practices, environments, and systems. Capturing the full range of what is being done can be challenging.
- Their complexity can make cause and effect difficult to determine. Multiple factors may contribute to multiple, interconnected outcomes, making it difficult to attribute a particular result to one part of an initiative. Evidence may therefore include information showing how multiple environmental, program, policy, and practice changes contributed to population-health outcomes.
- Promising work in lower-resource settings may be underdocumented. Published research has often reflected settings and institutions with greater access to research funding, evaluation capacity, and publication opportunities. As a result, useful health promotion experience from communities and countries with fewer research resources may be less visible in the published literature.
Global Programme on Health Promotion Effectiveness (GPHPE)
The PAHO Documentation Guide grew out of an earlier international effort to strengthen the evidence base for health promotion. With support from WHO, the International Union for Health Promotion and Education (IUHPE) launched the Global Programme on Health Promotion Effectiveness in 2001. Teams from different parts of the world, including the Working Group of the PAHO Regional Initiative to Evaluate the Effectiveness of Health Promotion, worked on methods for documenting and assessing health promotion practice. The PAHO Guide discussed in this section was one of the tools that resulted from that effort.
What is the PAHO Guide for Documenting Health Promotion Initiatives?
The PAHO Documentation Guide's primary purpose is to provide a simple, standard format for documenting health promotion initiatives. The Guide can help create a clearer record of whether and how efforts are working to create conditions that promote health and health equity.
The original PAHO Documentation Guide, developed in 2010, takes the form of a seven-part questionnaire asking for information about a health promotion effort. (For a copy of the PAHO Documentation Guide, please see Tool #1.)
Much promising health promotion work may never be formally documented or analyzed. The Guide was developed to expand available information about how health promotion initiatives work, including efforts in places where research and evaluation resources may be limited. Its use can help: (a) describe health promotion efforts taking place in the Americas and other regions; and (b) analyze the processes used to promote health so that useful lessons can be shared.
The Guide should also benefit those using it. Systematic reflection on practice can lead to the refinement of methods and new ideas for improving the initiative. Engaging community partners as participants in documentation can contribute to a better understanding of what happened and strengthen the influence and capacity of people involved in the effort. Establishing a clear record of what happened, and with what results, can also help others understand and support valuable work.
Answering the questions posed in the Guide may take time and thought, but that reflection can be useful. Thorough documentation can help funders, policymakers, practitioners, community members, and researchers understand health promotion initiatives; help organizations improve their own work; and provide practical examples that can inform similar efforts elsewhere.
Why should you use the Guide?
Answering the questions in the PAHO Documentation Guide will take time for those involved in the initiative, including interviews with stakeholders who have a perspective on the effort. You are busy enough already trying to support this and other activities, so why take the time to create this record of your health promotion initiative?
There are, in fact, a number of good reasons to use the Guide, including:
- Using the Guide can contribute to the evidence base for health promotion. Sharing what has been tried, how it was implemented, and what happened can help practitioners and policymakers learn from experience.
- Using the Guide can contribute to a better understanding of health promotion practice in the Americas, including work in Latin America and the Caribbean that may otherwise receive limited attention in international literature.
- Documenting and sharing information can help you connect with others in the field, in your own country and elsewhere.
- By involving community partners through participatory action research or other participatory methods, you can strengthen participants' skills, knowledge, and influence in the initiative.
- Use of the Guide can result in a careful analysis of your effort, help you to better understand your strengths and identify areas for improvement, and thereby strengthen your work.
- Documentation makes it possible to communicate what you have accomplished to others through reports, websites, publications, presentations, or other formats.
- Describing the accomplishments of your effort can raise your group’s profile and may strengthen opportunities for funding, partnerships, or other support.
Who should use the Guide?
The PAHO Health Promotion Documentation Guide is intended for use by groups conducting initiatives aimed at creating conditions that promote health and health equity. Some efforts may be relatively small programs involving a few organizations in a local community, while others may cover whole states or provinces, regions, or nations. Some initiatives may focus on particular cultural, racial, ethnic, geographic, or other populations, or on groups experiencing increased risk for particular health conditions.
Individuals, organizations, or institutions conducting health promotion initiatives appropriate for documentation might include:
- NGOs (nongovernmental organizations) or CBOs (community-based organizations) engaged in health and/or human service work.
- Local, state or provincial, regional, or national health or human service agencies.
- Ministries, departments, or other government agencies responsible for health.
- Community health advocates and organizers.
- Healthy community, healthy school, and healthy workplace initiatives.
- Faith-based communities and organizations.
- Health Impact Assessment teams.
- Environmental organizations and groups.
- Individuals or organizations working to increase access to safe and affordable housing, including for people experiencing homelessness or living in informal settlements.
- Individuals or organizations working to improve health equity and the health and quality of life of people and communities experiencing marginalization or other barriers.
- Those working to improve living conditions, for instance by increasing access to clean drinking water, safe housing, sanitation, transportation, healthy food, or other resources important to health.
Who in the organization should actually participate in the documentation? It depends. If the work of the initiative is distributed among many people doing different tasks in different sectors of the community, then people with knowledge of those different parts of the effort should be involved in documenting and interpreting it. The discussion may be facilitated by one or two people close to the effort. The person who completes the Guide may be an administrator or a skilled writer who gathers information from others and puts it into the appropriate form.
In a smaller organization, or in an initiative where one person has their finger on the pulse of most of the work, it may make sense for that person to coordinate the documentation. In many cases, a combination of these approaches will work best, with different people contributing to the portions they know most about.
How do you use the Guide?
As explained earlier, the PAHO Documentation Guide takes the form of a questionnaire rather than a manual. By answering its questions and adding whatever material is needed to fully describe and analyze your effort, you can create a record of what was done, why it was done, and what happened. This can help others determine whether lessons from your initiative might be adapted or applied in their own settings. It can also help you understand what is working well and what may need to change to improve community health.
In this section, we’ll look at the questions the Guide asks to help you describe and document your work. The focus is on answering them in a way that provides useful information to others while also helping your organization reflect on its own experience.
The Guide is divided into seven parts that gather information on different aspects of a health promotion initiative. We’ll look at each separately.
CONTACT INFORMATION
This section focuses on documenting the sources of information.
- Submission date: The date on which the questionnaire is being completed or submitted.
- Your contact information: Contact information for the person coordinating or completing the documentation.
- Lead organization: Contact information for the organization with primary responsibility for the initiative.
- Other partners: Contact information for other organizations, institutions, businesses, agencies, community groups, or others involved in or supporting the initiative.
PROGRAMME/PROJECT/INITIATIVE SUMMARY
This section gathers basic information about the project and provides an overview of the initiative.
- Title/Name of Initiative: By what name is the initiative known?
- Purpose(s) or objective(s): What does the initiative set out to do? What is its main focus? For instance, an initiative might aim to increase opportunities for physical activity, improve access to clean drinking water, reduce exposure to environmental hazards, reduce traffic injuries, increase participation in education, or address another condition affecting health.
- Expected outcomes/results: What outcomes or results does the initiative expect to achieve, including both changes in the process and changes in conditions or outcomes?
- Time frame for the initiative: When did the initiative begin? When is it expected to end? If it is ongoing, indicate that and provide any useful explanation.
- Stage of implementation: Indicate whether the initiative is in start-up, in progress, completed, or ongoing.
- Geographic coverage: Describe the country and the state, province, territory, region, municipality, neighborhood, or other geographic areas in which the initiative is being implemented.
- Setting: This might include a school, community, workplace, health care setting, faith community, public space, or another setting where the initiative is being or was conducted.
- Brief description: In narrative form, provide a concise summary of the initiative.
GENERAL CONTEXT
Characteristics of the setting:
- This portion of the Guide asks you to describe the setting before implementation and again during or after the initiative. Comparing these descriptions helps show what conditions were present at the beginning and what may have changed over time.
Specific information requested includes:
- Demography – population characteristics. These may include age, sex or gender, household or family characteristics, urban/rural location, income, race and ethnicity, education, and other relevant information. Who are the people involved in or affected by your initiative? How do their characteristics compare with those of the larger community, and how are those characteristics related to the reason for the initiative?
- Population health profile – life expectancy, infant and maternal health, diseases or health conditions of particular concern, sanitation, nutrition, environmental exposures, and positive indicators of health and well-being. What are the strengths and concerns related to the health of the population? Are there particular health challenges affecting specific populations? Are there local conditions that create barriers to health promotion, such as inadequate sanitation, severe poverty, environmental hazards, violence, lack of access to care, or other conditions? Are there existing conditions or community assets that support health promotion?
- Political context – The nature of government, public support for health promotion, political priorities, and relationships among groups may all affect an initiative. Is health a priority for decision-makers? How do government policies and relationships among different groups affect access to services or health-promoting conditions? Will the political environment influence your work or decisions about how to conduct it? If so, how?
- Socioeconomic conditions – The state of the economy, employment and the labor market, economic inequality, migration or displacement, social protection, housing, income support, and other economic conditions that may affect the initiative and the people involved.
- Sociocultural context – What are the educational, cultural, religious, linguistic, and social characteristics of the population you’re working with? Are there social or cultural conditions that create barriers to participation or health? Are there strengths, traditions, relationships, or community practices that can support the effort? Do particular norms or expectations need to be addressed in order to promote health?
- Community participation – The original Guide refers to this dimension as “Citizenship.” In contemporary use, it can be understood more broadly as the extent to which community members and stakeholders are able and willing to participate in community initiatives. Were stakeholders involved in the different phases of the effort? Which groups participated? How were they involved? Were there barriers to participation, and if so, how were they addressed?
These factors may have a profound effect on how you conduct your effort and how it is experienced by the community. Because context can influence any health promotion initiative, it’s important to describe it carefully so that others can judge whether and how lessons from your initiative might apply in their own settings.
- Why was this initiative started? What influenced the start of the initiative or intervention?
- In response to an unmet need. For instance, a population may have limited access to reliable health information, clean drinking water, nutritious food, safe housing, health services, or other resources.
- In response to a crisis. An industrial or environmental disaster such as the 1986 Chernobyl nuclear accident might demand an effort to address health consequences. The same could be true of a natural disaster such as Hurricane Katrina in 2005, when flooding, contamination, displacement, and disrupted services created major health concerns.
- In response to an opportunity. A new partnership, funding opportunity, policy change, or other opening may make it possible to address an important community health issue.
- In response to a political request. A public official responding to constituent concerns or other political priorities may support a health promotion effort. An issue may also gain attention through an influential report, media coverage, community advocacy, or public pressure.
- In response to community action. Community members may organize themselves around an issue – for example, parents organizing a school traffic-safety effort or residents organizing to improve safety in their neighborhood.
- In response to a funding opportunity. Funding may become available to address a health or community issue.
- Initiated by an individual on behalf of an organization. An individual may help mobilize a community around an initiative supported or promoted by an organization.
- Strategies, models, or frameworks used in the design of the initiative: Identify whether the initiative was guided by any established strategies, models, or frameworks, and briefly describe how their concepts or principles informed the initiative.
FINANCING
These questions attempt to determine the investment, sources of funding, and other resources necessary for implementing the initiative.
- Budget – Some initiatives have a specific budget and others do not. Try to estimate the value of what has been invested or spent to begin the initiative, what is required on an annual basis to maintain it, and the total investment if the initiative has been completed.
- Source of funds – Identify the sources of funding and, where useful, the amounts received through grants, contracts, public funding, donations, or other sources.
- Nonfinancial resources – Resources necessary for successful health promotion extend beyond money. They may include people with technical or training skills, community knowledge and relationships, facilities, transportation, volunteers, donated materials, in-kind contributions, meeting space, media coverage, and other community assets.
- Adequacy of financial resources – Was your budget sufficient to accomplish your goals? If not, explain the challenges or limitations.
- Adequacy of nonfinancial resources – Were available resources, including community assets, sufficient to accomplish the initiative’s goals? If not, explain what was missing or inadequate.
PROCESS/PARTNERSHIPS
The next questions focus on partnerships.
- Key partners and their roles and responsibilities: Identify the partners involved in the initiative and describe their primary roles and responsibilities.
- Evolution of partnerships and roles and responsibilities: Did partnerships or responsibilities change over time? If so, describe how and why.
- New partnerships: Were additional partners brought into the initiative after it began? Who were they, and what led to their involvement?
STRATEGIES
These questions aim to capture the strategies used to carry out the initiative. The original Guide draws largely on health promotion strategies reflected in the Ottawa, Caribbean, and Bangkok charters.
- Strategies used. Identify the strategies used in implementing the initiative and describe how each contributed to the work.
- Participation – How were community members, intended participants, and other partners involved in decision-making and implementation? What did you do to create meaningful participation and shared ownership of the initiative?
- Partnerships/collaboration/intersectoral action – How were working relationships developed among different community sectors – government, businesses, organizations, institutions, NGOs, community leaders, faith communities, and others – in order to implement the initiative? What did you do to encourage collaboration?
- Empowerment/capacity building – How did the initiative strengthen people’s ability to influence the conditions affecting their lives? What knowledge or skills were developed? How did participants and partners increase their ability to carry out the work and pursue desired outcomes?
- Public policy – What formal policies, laws, regulations, organizational procedures, or informal practices affecting the issue were addressed? What did the initiative do to advocate for or help bring about policy change?
- Communications and public relations – How did the initiative provide information, increase awareness, gather information from the people and communities involved, and maintain communication among stakeholders and implementing partners?
- Advocacy – What approaches were used to build support for the initiative, encourage people and organizations to provide resources, present evidence to inform policy, or bring about changes in services, systems, or the physical environment?
- Building leadership – How were people responsible for the initiative organized? What formal or informal structures for decision-making were established? What was your leadership strategy, who participated in leadership, and how were new leaders supported or developed?
- Creating supportive environments – What did you do to create conditions that support the community change you wanted to see? Did you address social norms, access to resources, organizational practices, or features of the physical environment?
- Improved access to resources/services – What changes helped community members gain better access to resources and services? What was done to make programs easier to reach, use, afford, or navigate?
- Challenges the initiative faced – Describe important challenges encountered during the initiative and what was done to address them.
- Additional actions or strategies – Describe any other actions or strategies that were important to implementation and how they affected the initiative, positively or negatively.
OUTCOMES
- Notable achievements/results/outcomes: List or describe the main achievements, results, and outcomes of the initiative.
- Contribution to broader development goals: The original 2010 PAHO Guide asked how an initiative contributed to the Millennium Development Goals (MDGs). Because the MDG period ended in 2015, contemporary documentation should instead consider whether and how the initiative contributes to the United Nations Sustainable Development Goals (SDGs) and other relevant current health and development priorities.
From the Millennium Development Goals to the Sustainable Development Goals
The original PAHO Documentation Guide was developed during the period of the Millennium Development Goals, eight international development goals adopted in 2000 with a target date of 2015. References to the MDGs in the original Guide should therefore be understood in their historical context.
In 2015, United Nations member states adopted the 2030 Agenda for Sustainable Development and its 17 Sustainable Development Goals (SDGs), which took effect in 2016. The SDGs build on the earlier MDGs but address a broader range of social, economic, environmental, and health conditions.
For current documentation, an initiative can identify the SDGs to which it contributes. SDG 3 specifically addresses health and well-being, but health promotion can also contribute to goals related to poverty, food and nutrition, education, gender equality, clean water and sanitation, employment, inequality, sustainable communities, climate, peace and institutions, partnerships, and other determinants of health.
The original Guide also discussed PAHO’s Faces, Voices and Places initiative, adopted in 2006, as an example of a regional initiative connected with the MDGs and social determinants of health. This should now be understood as a historical example from the MDG period rather than as the current global development framework.
Current PAHO health promotion work is aligned with the 2030 Agenda and emphasizes health equity, social participation, intersectoral action, healthy settings, and action on the social determinants of health.
- Changes arising from the initiative: At what levels did the initiative contribute to change? Consider changes involving individuals, groups, organizations, communities, policies, systems, or broader social conditions. Describe the changes and the available evidence supporting them.
- Changes at the individual level. These may include increased skills, knowledge, confidence, leadership, problem-solving ability, or changes in attitudes or behavior.
- Changes in communities. These may include a shift in community attitudes around issues such as harmful alcohol use or domestic violence; increased awareness of community needs or strengths; stronger coalitions, communication networks, or organizing capacity; broader participation in decision-making; development of community leadership; creation of new community resources or assets; or increased commitment to improving quality of life.
- Changes in policy at local, regional, state/provincial, or national levels. These might include new or revised policies, improvements in infrastructure, or changes in organizational procedures and practices.
- Changes at the organizational or institutional level. These may include increased resources devoted to the issue, establishment of a new health promotion function or unit, assignment of staff, stronger partnerships, or incorporation of participatory approaches into routine organizational practice.
- Which change was most important and why? Of the changes identified, which were most significant, and why?
- Sustainability: Does the initiative need to continue in order to maintain its benefits? If so, what was done to sustain or integrate the work into ongoing programs, policies, organizations, systems, or community practices? If it was not sustained, why not?
- Evaluation process: Describe how the initiative was evaluated. How did you learn what worked and what needed to change? What information helped you organize the process, set timelines, and manage implementation? What process or outcome measures were used? How were evaluation findings used to adjust and improve the effort?
- Main lessons learned: What have you learned from the effort as a whole and from its planning, implementation, evaluation, and sustainability? What did you learn about the methods and systems you used, the accuracy of your expectations, and the effectiveness of the initiative? What might you do differently? Which lessons might apply in other settings, and which depend strongly on your particular community or context?
- Recommendations: What would you recommend to improve this or similar initiatives in the future?
- Revising the intervention. How would you change the intervention to make it more effective, equitable, accessible, or efficient? What would you do differently next time?
- Implications for participatory research. How could you involve more stakeholders and participants in the different phases of the process? What support, training, or mentoring might be useful?
- Implications for practice. What approaches appear particularly useful for others pursuing similar outcomes? It is just as important to describe what did not work as what did, since knowing what to avoid or modify can be as useful as knowing what to repeat.
- Communication materials, tools, manuals, protocols, etc.: Identify materials developed to support the initiative that could help others understand or adapt the work, where sharing them is appropriate.
- Photographs and other documentation: Identify photographs or other appropriate materials that help tell the story of the initiative. When sharing images or information about participants, follow applicable consent, privacy, and confidentiality requirements.
In Summary
The PAHO Documentation Guide was developed to help practitioners create a record of the whole of a health promotion effort – its context, planning, design, implementation, partnerships, strategies, outcomes, evaluation, sustainability, and lessons learned. If you answer the questions in the Guide carefully, you can develop a detailed picture of what was done, how it was done, what changed, and what others might learn from the experience.
Although the original Guide was developed in 2010 and contains some references that reflect that period – particularly the Millennium Development Goals – its central purpose remains useful: helping practitioners document and reflect systematically on health promotion practice so that lessons can be shared, initiatives can be improved, and useful approaches can inform work in other communities.
For contemporary use, historical fields should be interpreted in light of current health and development frameworks. In particular, the Sustainable Development Goals and the 2030 Agenda have replaced the Millennium Development Goals as the current global development framework.
Contributor
Originally contributed by the Working Group of the PAHO (Pan American Health Organization) Regional Initiative to Evaluate the Effectiveness of Health Promotion, with participation from WHO/PAHO Collaborating Centers and other public-health partners. The organizational names and affiliations in the original contributor statement reflect the institutions involved at the time the Guide was developed.
Resources
Online Resources
Guidelines for Using PAHO Guide to Document Health Promotion Initiatives.
Faces, Voices, and Places. The PAHO web page for Faces, Voices and Places.
PAHO. The Pan American Health Organization (PAHO), the arm of the World Health Organization in the Americas.
United Nations Development Programme. The United Nations Development Programme web page on the Millennium Development Goals.
Social Determinants of Health. The WHO Commission on the Social Determinants of Health.
Work Group for Community Health and Development. The Work Group for Community Health and Development at the University of Kansas, the developer of the Community Tool Box and a collaborator on the PAHO Guide. The Work Group is a World Health Organization Collaborating Center.
World Health Organization. The World Health Organization (WHO), the health promotion agency of the United Nations.
Print Resource
Health Promotion Effectiveness Working Group. (2008). Guide for Documenting Health Promotion Initiatives. Pan American Health Organization.
Poland, Blake, Krupa, Gene, McCall, Douglas. (2009). Settings for Health Promotion: An Analytic Framework to Guide Intervention Design and Implemenation. Health Promotion Practice.
Introduction: What is health promotion?
___Health promotion is “a process of enabling people to increase control over their health.”
___Health promotion is a way of thinking and working that considers the continual advancement and maintenance of individual and population health to be integral to the functioning of a community.
___Health promotion focuses on the social determinants of health as well as on specific health issues.
___Health promotion is
- Population based
- Participatory
- Intersectoral
- Context-sensitive
- Multi-level
What is the PAHO Guide for Documenting Health Promotion Initiatives?
___The Guide is a seven-part questionnaire, asking for information about your effort.
___The Guide’s purpose is to create a mechanism for the documentation of health promotion initiatives
Why should you use the Guide?
___Using the Guide will contribute to a data base that will advance the field of health promotion.
___Contributing information through use of the guide will allow you to connect with others in the field, both in your own and other countries.
___By involving participants in data collection through participatory action research, you can empower participants in your initiative, and engage them in learning new skills.
__ Use of the Guide will result in a careful analysis of your effort, help you to better understand your strengths and pinpoint areas to improve, and thereby make your work more effective.
___Using the Guide can help you get a new perspective on your effort, and come up with new ideas.
___By documenting your effort through the Guide, you’ll get your work published on the PAHO website, and perhaps in an international journal as well.
___Using the PAHO Guide will enable you to describe the accomplishments of your effort and raise your profile in the community and with funders and other supporters.
___By participating in the use of the Guide and documenting your work, you can help to ensure that health promotion and the healthy community concept become integral to the idea of community health.
Who should use the Guide?
___The Guide is intended for use by any individual, group, or institution conducting an initiative, intervention, or program aimed at the promotion of health or healthy communities in the Americas, including:
- NGOs (non-governmental organizations) or CBOs (community-based organizations) engaged in health and/or human service work
- Local, state or provincial, or national health or human service agencies
- Ministers or Secretaries and ministries or departments of public health at all levels
- Community health activists
- Healthy community initiatives
- Faith communities
- Health Impact Assessment teams
- Environmental groups
- Individuals or organizations concerned with providing affordable housing for marginalized individuals and families, including those who are homeless
- Those working to change environmental conditions (provide or help people gain access to clean drinking water, for instance) in order to eradicate disease
How do you use the Guide?
___Answer all the questions and fill out the charts, thinking carefully about each one.
___Use the resulting description to:
- Submit to PAHO, in order to contribute to the documentation of health promotion efforts in the Americas.
- Gain recognition and credibility in the field.
- Inform the community or region about your work.
- Analyze your program, determining where changes need to be made, what areas should be emphasized and strengthened, and where additional resources are needed.
- Pass on what you have learned – about both what works and what doesn’t – to others who can then replicate (reproduce) your work.
- Present a successful effort as an example of a best practice or best process.
- Convince funders of the effectiveness or potential of your work.
Example #1: Collaborative Action for Community Change and Risk Reduction for Chronic Disease and Health Disparities in Kansas City, Missouri (USA)
Authors: Jerry Schultz, Steve Fawcett, Vicki Collie-Akers
The Kansas City-Chronic Disease Coalition began in 2000 in Kansas City, Missouri, in response to two events: 1) the Centers for Disease Control and Prevention (CDC) request for proposals for the Racial and Ethnic Approaches to Community Health (REACH) 2010, and 2) minority health status assessments released by two organizations that highlighted significant health disparities among Black and Latino residents of Kansas City.
This urban area was characterized by high rates of poverty and few opportunities to engage in healthy behaviors. The Coalition is comprised of health, community and neighborhood organizations; faith communities, business, as well as residents of Kansas City. Over time, the Coalition included Native Americans as one of its target populations; however efforts to reach that population never came to fruition.
The Coalition’s mission is to improve health outcomes for diabetes and cardiovascular diseases (CVD) by promoting access to quality care, healthy environments, and lifestyles through integrated, affordable, culturally sensitive, and accountable community-based health care and prevention services.
It proposes five interrelated phases:
- Collaborative planning and capacity building.
- Targeted action and intervention.
- Community and system changes.
- Widespread behavior change.
- Improving community health outcomes
The Coalition developed a comprehensive action plan that proposed 86 community changes. Through its “Pick Six” program it also provided resources to key partners to support the implementation of six action plan items (e.g., six new or modified programs, policies or practices). Resources included grants, technical support, and program materials.
The Coalition facilitated about 675 community changes between 2001 and 2007. Some examples include: modified clinic operating hours to increase access, adoption of clinical care guidelines, inclusion of health information in neighborhood newsletters, use of church facilities for physical activity, and the development of walking clubs or paths. Findings from the participatory evaluation suggest that the Coalition was an effective catalyst for environmental changes to reduce health disparities related to CVD and diabetes.
Some of the Coalition’s important assets were the wide social network of the first project manager and the development of relationships with a large number of community organizations. However, challenges in implementing mini-grants, including complicated government requirements and internal fiscal management, stressed the relationships that had been established with these organizations. Limited involvement and participation from Latinos (one of the target populations) was also a barrier.
Between 2001 and 2007, the Coalition received large grants as part of the CDC’s REACH 2010 Initiative. A new five-year grant received in 2008 allows for the continuation of this successful initiative and may permit more sustained efforts to address health disparities, with the main adjustment to be made being to develop an effective strategy to engage the Latino community in the initiative.
Example 2: Home Help for the Elderly Program in St. Vincent & the Grenadines
We would like to thank the following individuals who assisted in the preparation of this case study: Carrie Mathews, Juno Lawrence, Patsy Wyllie, Rosita Alexander-Snagg
The Home Help for the Elderly Program, an initiative of the government of St. Vincent & the Grenadines implemented by the Ministry of Social Development, began in August 2002 to improve care and support to elderly population. The initiative intended to benefit persons 60 years and over, those who were isolated and shut in homes, and those with special needs. It included 92 homecare helpers, 2 supervisors, and 1 case worker and it received support from a local church.
The initiative’s mission was to create a supportive environment and a sense of belonging for the elderly while also raising their self-esteem and attending to their basic health and social/emotional needs. It proposed a holistic approach, in which the elderly were assisted with health care and other needs, while the providers were taught about the elderly way of life and how to care for them. The services were provided at no cost to the recipient.
St. Vincent & the Grenadines’ Red Cross provided training in first aid for home helpers. Nurses provided general nursing care and supervised the trainees during their internship. The Ministry of Health provided officers to assist with the training program. Due to the involvement and support of the Ministries, all areas of the country are covered.
Currently, 450 elderly are benefitting from the Initiative, and it is considered to be a cost cutting measure for the government, since it would be more costly if the government were to provide institutional care for this population. Social indicators have changed; community and family response to the elderly has also improved. The elderly reported feeling a sense of comfort and security, and their family members felt comforted knowing that they were being taken care of.
There has been a greater utilization of the health care facilities within districts. The elderly have begun paying more attention to diet and nutrition. Policymakers have gained a better understanding of the profile of the elderly in their society. The training programs have also been a source of employment for the caregivers.
However, there was a lack of male involvement in the project (as home helpers), limited financial and human resources, limited equipment and material, and lack of support from the private sector. Ensuring that the true beneficiaries had access to the program has been a continuous challenge, as well as, ensuring that political interference was kept to a minimum. The Initiative also had no formal documentation and evaluation system.
The initiative contributed to positive changes for the elderly population in St. Vincent & the Grenadines. As the initiative is in the implementation and maintenance stage, evaluation must be considered and this must be an ongoing process. A source to sustain the initiative must also be considered as reliance has been solely on the government.
Example 3: National Wellness Program in St. Vincent & the Grenadines
We would like to thank the following individuals who assisted in the preparation of this case study: Carrie Mathews, Juno Lawrence, Patsy Wyllie, Rosita Alexander-Snagg
Starting in 2006, the Department of Physical Education and Sports in the Ministry of Social Development of St. Vincent & the Grenadines launched the National Wellness Program which was implemented through community groups and institutions. Other participating organizations/institutions included the Ministry of Health & the Environment, Homes for the Aged (Thompson Home, Golden Age Homes), Her Majesty’s Prison, and other community groups in various districts. The initiative was meant to benefit the general population; specifically, individuals who were involved with the participating organizations/institutions.
As chronic non-communicable diseases are a pressing and major problem in St. Vincent & the Grenadines, accounting for 80% of deaths in the country, the initiative’s mission was to sensitize participants about healthy lifestyles and the benefits of participating in regular physical activity. One of the primary aims of this initiative was to change the belief that health is only important when individuals are not well and to make people be more proactive when it comes to their health.
Even though there was no formal monitoring or evaluation system in place, the expansion of the program to other communities has been a positive indication that changes are coming about. Communities reported a heightened awareness about physical activity and expressed an interest in getting involved with the program. There was greater utilization of community resources (e.g. the community centers and recreational sites) and health care facilities within the districts. Positive behavior change was demonstrated by the population’s increased level of physical activity.
The case study reported some challenges such as a lack of male involvement in the project, limited financial and human resources, limited equipment and material, and lack of support from the private sector. In addition, the change in the location for some of the activities has hindered the involvement of some participants. Adequate funding will need to be acquired from other sources.
Example 4: Inuit Tutarvingat (Inuit Centre at NAHO) in Ottawa, Ontario, Canada
We would like to thank the following individuals who assisted in the preparation of this case study: Katherine Minich, Suzanne Jackson
The Inuit Tutarvingat Initiative began in 2000 in response to the Royal Commission on Aboriginal Peoples (RCAP). Participating organizations and institutions included the Metis Centre, First Nations Centre, and the Communications Unit. The Initiative is intended to benefit the Inuit population, which has the poorest health status in the country of Canada. Policy makers, government workers, and the general public are the target audiences for the Initiative.
The main focus of the Initiative is to promote practices that will restore a healthy Inuit lifestyle and improve the health status of the Inuit population through research and dissemination of research results, education and awareness raising, human resource development and sharing information on Inuit-specific health policies and practices. The Initiative seeks these changes at the level of individuals, organizations, community and society.
The Initiative has 5 objectives:
- Improve and promote Inuit health through knowledge-based activities.
- Promote understanding of health issues affecting the Inuit population.
- Facilitate and promote research and develop research partnerships.
- Foster participation of the Inuit population in the delivery of healthcare.
- Affirm and protect Inuit traditional healing practices.
Change in the Inuit community has been difficult to capture as the population is greatly dispersed. Also, because no formal monitoring or evaluation system is in place yet, it is difficult to measure change and results. Very little ethnic data is collected so it is hard to tell how Inuits in general are benefitting. Some products and resources target specialized audiences but the uptake and impact of those resources are not known. Organizational level changes have, however, made going for smaller grants easier for staff.
Some challenges faced by the Initiative include difficulty in the retention of Inuit workers, long upstream population health challenges, and changing governments leading to questions regarding the continuity of funding.
Although evidence of effectiveness has yet to be determined due to a lack of formal monitoring and evaluation the Initiative seems to be headed in the right direction. According to the Initiative, communications have been reaching the target audience, the Centre has gained visibility, and resources/partnerships have been established. However, the Initiative needs to focus on fewer issues with longer and more comprehensive projects and to strengthen partnerships with health and education sectors and to develop target materials. Performance monitoring and evaluation must also be developed and improved.
Example 5: Health-Promoting Schools Initiative in Guyana
We would like to thank the following individuals who assisted in the preparation of this case study: Anthony Hunte, Dionne Broone, Juno Lawrence, Lucy Anderson, Lydia Indira Badal, Preeta Sajwack, Guyana Ministry of Health and Ministry of Education
The Health Promoting Schools Initiative began in 2002 in Guyana to address the growing health and social problems that are related to lifestyles and behavior in the country. Lead organizations included the Guyana Ministry of Health, Guyana Ministry of Education, and the Pan American Health Organization (Guyana). Participating organizations included the Caribbean Council for the Blind, the Ministry of Human Services & Social Security, the Cheddie Jagan Dental Clinic, the Ptolemy Reid Rehabilitation Center, Money Gram, the Ministry of Agriculture, the Ministry of Culture and Youth and Sport, Voluntary Service Organizations (VSO), the Linden Economic Advancement Program (LEAP), the Peace Corps, the Guyana Red Cross, Women Across Difference, the World Bank, and the St. Sidwells Anglican Church.
The Initiative was implemented in nurseries, primary and secondary schools along with the respective communities in which the schools were located. Target groups included Parent-Teacher Associations, Community Improvement Advisory Committees, and school-age children of all levels.
The Initiative aims to create supportive environments that encourage positive change through education and skills training among the various target groups. The mission is ‘to create and maintain the capacity of school communities to build health into all aspects of life at the school and improve the health of children, teachers, parents, guardians and other members of the school community. The Initiative is facilitating primary health services and schools to work together, improving their ability to detect and offer assistance to children and young people in a timely fashion, detaining and preventing the adoption of risky behaviors, such as smoking, consumption of alcoholic beverages, substance use, early and risky sexual practices, and early unwanted pregnancy. Technical support was provided by PAHO and the MOH. The PTA provided the human resources and several international agencies provided financial resources.
According to the Initiative, achievements and results of the Health-Promoting Schools Initiative cannot be described due to the lack of formal monitoring or evaluation systems in place to routinely collect the data that would be needed to substantiate any claims. However, the communities involved have reported some behavioral changes among parents and children.
Challenges varied in the different stages of the Initiative. In the planning stage, there were a lack of formal agreements among relevant stakeholders, a lack of adequate funding, and a lack of skilled human resources. During the implementation stage, there was a lack of formal monitoring systems to track progress and a lack of effective communication strategies to communicate to the public about the initiative and to ensure effective communication among stakeholders.
The effort will continue to be sustained through the School Health Units within the Ministries of Health and Education. Both of these units are responsible for coordinating the activities within each ministry and sharing that information with the other ministry through a small committee.
Example 6: Crooked Creek Quality of Life Initiative (CC QOLI): A Community Development Experience in Indianapolis, Indiana, USA
Authors: Alicia Chadwick with Crooked Creek Northwest Community Development Corporation, Helen W. Lands with Fay Biccard Glick Neighborhood Center at Crooked Creek, Mary Beth Riner with Indiana University School of Nursing, and Marty Rugh with St. Vincent Health.
The purpose of this initiative was to improve the quality of life of residents of a geographically defined neighborhood in an urban mid-western city in the United States. An advisory board provided oversight for a comprehensive assessment conducted by nursing students and that was used for developing a proposal that funded an advisory group appointed by the mayor of the city. Using the PAHO Healthy Municipalities, Cities and Communities model, diverse sectors of the community collaborated to address the conditions responsible for health and well-being. Organizations involved included a hospital, social service agency, housing development agency and university.
The goals of the CC QOLI were to improve the quality of life of Crooked Creek residents through: revitalization of built environments (commercial and community buildings, housing, roads, sidewalks, etc.); new collaborations among health, education and social service organizations; and resident engagement in community improvement. Among the initiatives implemented to achieve these goals were: investments in a housing program for low and moderate income residents; construction of a Family Pavilion to address the civic, social, intergenerational, cultural, and recreational needs of Crooked Creek individuals and families; and a School Health Program for area students.
The Fay Biccard Glick Family Pavilion at Crooked Creek was constructed and now provides a wonderful space for community gatherings, youth and family activities, recreation and an affordable venue for wedding receptions, family reunions, graduation ceremonies, open houses and religious services. The School Health Program moved healthcare delivery beyond traditional hospital walls, and is now part of a broader vision to build healthier communities. School corporations have adopted healthier school policies and are able to address chronic issues of asthma, obesity and absenteeism. Investments in Housing have resulted in completion of three congregate living homes for 12 disabled residents—the most recent using “green” building practices, costly repairs to the homes of 33 elderly homeowners, education of 60 potential homebuyers about the home buying process, and down payment assistance for 12 first-time buyers who purchased homes in Crooked Creek.
The Family Pavilion project experienced some difficulties such as having the contractor walked off the job midway through the project resulting in an eight month delay and cost overruns. Another contractor had to be hired and additional funds were raised in order to complete the project. The School Health Program became more complex when partners realized that the unique nature of each school required interventions to be tailored for each particular school’s student population. The Investments in Housing program found the cost of projects were sustainable only to the degree that the organization continued to successfully compete for public and private funds to underwrite projects.
Some of the lessons learned across initiatives included:
- Collaboration makes individual organizations stronger—a new organization without a track record benefits from partnering with an established organization, which gives others “permission” to be supportive. Established organizations benefit from the energy and entrepreneurial aspects of start-ups.
- Having a good plan based on good data is crucial to securing funding and support.
- Program operators need to ensure senior that leaders (senior executives and board members) stay informed and engaged over time in order to sustain initiatives over the long-term, otherwise they risk being replaced by the next new (and not necessarily better) thing.
Example 7: Health through Participation: the experience of Guarulhos in São Paulo, Brazil
Authors: Rosilda Mendes, Paulo Fernando Capucci, Douglas Brandalise, Emilia Broide. We would also like to thank Jonas Diaz for his help in preparing this case study.
The initiative is taking place in Guarulhos, Sao Paulo, as one of the strategies to deal with problems related to health and living conditions with the aims of promoting and enhancing popular participation and establishing a channel of communication for including popular demands into the development of health policies. The priority project Health Through Participation works through promoting local Forums that are open to the public and that are held every two years. Between 2005 and 2007, a total of 37 Forums were held, bringing together 5,700 representatives of local communities, health professionals, health managers, NGO´s, churches, etc.
The initiative’s main objective is to increase the population’s control over health care and management of public policies related to health, as well as to assist in determining the state of health in specific areas at the lowest possible level of division of local urban space. It began in 2005 with the Health Through Participation Forums held in twenty-two areas of the city in conjunction with the Participatory Budget Forums. In 2007, the Health through Participation Plenary Sessions were held in each of the Health Districts which had been organized as the basis for health management. Since the first Plenary Sessions, approximately 1300 representatives have been elected to comprise local Health Councils for the 65 Basic Health Units, hospitals, and specialized health centres in the municipality. By the end of 2009 14 Forums will be held.
The local Health Councils have broadened their scope of action from acting on local health issues to broader social issues. Action, therefore, has become geared to local day-to-day issues affecting the communities. The Project has led to a change in health policy and related areas of municipal administration. The resulting focus of the discussions on public health policy has been publicly credited to the initiative. Improvements were registered at Basic Health Units with regards to the quality of the care given. In addition, there has been a significant advance in identifying more specific health demands on the part of the population. The fact that the public has taken control of health issues has generated a new trend within the population, with popular complaints giving way to specific proposals for change and greater support from the health sector. The public now understands, for example, the logic of investing in primary care through the Basic Health Units rather than in a greater number of large hospitals. There have been positive changes related to the establishment of mechanisms for participation involving many local actors. However, the Councils have tended to have a certain cliquishness which has hindered fuller social participation.
Among the lessons learned from this experience is the need to guarantee support from local government in order to successfully increase social participation and to improve the planning of activities in order to ensure that the project’s sustainability can be maintained. Budgeting is central to supporting the permanent activities required for the Project, as it is fairly complex and involves many players. What is most important for the Project is that it should not stand apart from local activities and politics. It therefore needs to be open-ended.
Example 8: Healthy Schools Initiative in the Departments of Asunción, Central, Misiones, Itapúa y Cordillera in Paraguay
Authors: Health Promotion Directorate–Ministry of Public Health and Social Wellbeing
The Healthy Schools Initiative started in Paraguay in the decade of 1990, spearheaded by the Ministry of Health with the support of the Pan American Health Organization. The objective was to promote health in the school setting and the integral development of boys and girls within the educational community.
In 2000, a pilot project was implemented in 17 schools distributed throughout urban, peri-urban and rural areas of the Departments of Central, Cordillera y Misiones. At each selected school a Management Committee comprised of school authorities, parents, students, local authorities and representatives of organizations and local institutions was formed. The 17 schools focused their action on four areas: primary health care, infrastructure, training, and participatory projects. Although this effort started with great impetus, it was not possible to sustain it overtime. However, it created a fertile ground that allowed some initiatives to be maintained within the framework of Healthy Schools and at times it catalyzed the beginning of new processes.
In October 2008, the authorities of the new government re-launched the Healthy Schools initiative, in a joint project between the Ministries of Health and Education. A data assessment was conducted to jointly analyze and generate a consensus on the criteria for accreditation. Strategic partnerships were established with organizations such as the program VIDA (cardiovascular disease prevention), and with international agencies such as UNICEF, UNDP and UNFPA. Actions undertaken at this stage have emphasized a strong and consistent interest of all stakeholders. It should be pointed out that the Ministry of Education and Culture has modified the “Technical High School Education in Health” curriculum, reorienting it toward health promotion, and thereby contributing to the process of implementing the Healthy Schools Initiatives.
One of the challenges of this initiative has been that numerous experiences in school health describe themselves as a Healthy Schools or `Health-promoting Schools` yet there are no uniform criteria established for its designation. These experiences are promoted by different sectors: the municipality, health districts, local government, and the education community. The current objective is to unify the Strategy by developing criteria for accreditation that guides institutions in the development of lines of action, complemented by a monitoring system. The current goal is to develop a unified strategy at 40 selected schools in 5 Regions. A baseline will be developed, along with a system for continuous and systematic data collection and analysis.
Some difficulties included (1) limited resources and the dispersion of efforts of the Health Promotion Directorate, which made it difficult to carry out a sustained process and (2) the lack of coordination within the Ministry of Health’s programs that hindered integrated action based on common objectives.
Lessons learned included the need for systematic data collection and analysis, dissemination of information among the main stakeholders so that results are assessed, and the need for community empowerment (local governments and other social actors) in order to avoid processes to remain inconclusive.
To facilitate the collective construction of Healthy Schools will help social actors to identify protective factors and stimulate effective responses. Responsibility should be assumed mainly by governmental institutions, linking efforts with other institutions working in this area. The Healthy Schools Strategy creates an opportunity for the school setting to be transformed into a space that fosters the social production of health.
Example 9: Promotion of Healthy Settings and Lifestyles at Primary Schools of Four Mexican States
Authors: Luz Arenas Monreal, Pastor Bonilla Fernández, Cristina Caballero García, Elba Abril, Héctor Hernández P., Sofía Cuevas B.
In 2006 the National Institute of Public Health (INSP) of Mexico initiated the project Promotion of Healthy Settings in Primary Schools in four Mexican States, in collaboration with the Health Services of the States of Guerrero and Jalisco, the Center for Research on Food and Development, and public schools of the states of Morelos, Jalisco, Guerrero, and Sonora. This project was financed by the National Science and Technology Board. It used an integrated approach to improve physical, emotional and social environment for school-aged children and addressed problems affecting this population such as overweight, obesity, addictions, environmental degradation, and family and social violence.
Initially, focus groups were conducted with teachers of the four States to help identify health determinants (living, work, and education conditions; physical environment; psychosocial factors; social and family support networks; etc.) that affected the populations in the areas where the initiative would take place. The main characteristics found among the families of the schoolchildren were: low social class, low educational level among parents, poverty, and migration to the United States. In the first phase, baseline measurement data were collected: weight/age, weight/height, age/height, prevalence of caries and smoking with the following results: coexistence of malnutrition and overweight or obesity among children of all participating schools, high prevalence of cavities, and a significant percentage of children who currently smoke and/or consume alcoholic beverages.
In the second phase, educational interventions were carried out in topics such as: self-esteem and the culture of peace, environmental protection and care, smoking prevention, and nutrition and hygiene. As a result, increases were observed in knowledge related to healthy food and hygiene as well as improvements in skills related to waste separation and care of natural resources. Teachers reported a decrease in violence and an increase in the use of more peaceful ways of resolving conflicts among schoolchildren. Two health committees were formed: one of children and another of parents. Links were established between the schools and local health centers to facilitate the children’s access to services.
The children had difficulty in applying outside of the school setting what they had learned through the initiative, which highlighted the limitations of school-centered initiatives that do not include the community as a whole. There were also difficulties in influencing agencies responsible for the development of public policies (sale of healthy food in schools and its vicinity) in the States of Guerrero and Morelos. In the States of Jalisco and Sonora, where regulations of food sale within the schools were already in place, the initiative managed to raise awareness of families about healthy food consumption.
This project contributed to the inclusion of more integrated health promotion approaches to initiatives taken by the INSP, such as promoting the establishment of a research group on Promotion of Healthy Lifestyles.
Example 10: The Community Mental Health Movement of Bom Jardim, Fortaleza, Brazil
We would like to thank Maria Gabriela Curubeto Godoy for her assistance in preparing this case study.
The Community Mental Health Movement of Bom Jardim, in Fortaleza, Brazil aims to provide services to people with various types of mental illnesses in order to improve their integration into the community and promote individual, group and social empowerment. It is implemented in 22 community centers of 5 neighborhoods located in the “Greater Bom Jardim” area of the municipality of Fortaleza. The initiative focuses on vulnerable, at-risk families, living in extreme poverty. This population is characterized by a low level of education, unemployment, lack of opportunities and low self-esteem.
The initiative started when local church leadership and missionaries working in the region formed a volunteer group to provide shelter and counseling to the population that at that time did not have any access to mental health services. Initially, efforts to include the local government were fruitless. However, with a change of government in 2005, the initiative gained more recognition and momentum, which resulted in the establishments of alliances and an increased flow of resources to expand actions and services. Some of the stakeholders currently involved in the initiative include local and state health departments, indigenous populations, local universities, the private sector, NGOs working with delinquent youth and the PETI Program (Program to Eradicate Child Labor).
The initiative incorporated various strategies to achieve its goals. Community therapy groups were established, as well as other groups aimed at facilitating personal therapeutic processes within collective actions (bio-dance, therapy through art, self-esteem support groups, etc.). Massotherapy, reiki, breathing and relaxation workshops and sessions were offered. Theater and music events were scheduled in public places as a way to the community to take ownership of places that had been dominated by drug trafficking and violence. Various cultural and arts activities were offered, free of charge, to all community members (music, language, painting and theater classes). A community garden and pharmacy were established and professional training was offered to young people. Lastly, efforts were put in place to integrate people with mental illnesses into these activities in order to support a process to decrease stigma attached to mental health problems and to support de-institutionalization of these patients.
Positive outcomes have been reported from this initiative. The general community attitude towards dealing with underserved populations has shifted from a personal to a collective and social perspective. The community’s identity has improved, with those living in Bom Jardim showing pride in their neighborhood, when prior to the initiative they would describe it as ugly and violent. A network has been established to help community members to take better care of themselves. New links have been established with other stakeholders working in the community and with the private sector. Community youth have reported greater motivation to attain a higher education level and stigma related to psychological problems has decreased. The initiative has also received national recognition and various national and regional awards.
Some of the challenges included changes in government that created delays and uncertainty about the initiative’s continuity, difficulty to maintain and increase resources as the initiative expanded, and resistance from other institutions to collaborate with the initiative’s activities.
There is considerable social stigma attached mental illnesses, especially when it is related to underserved and poor populations. This experience demonstrated the viability of empowering, improving social capital and expanding therapeutic and educational activities for these populations. It also promoted a new ways of viewing mental health issues that was inclusive and transformative.
Example 11: Faces, Voices and Places initiative in the municipality of Corredores, Costa Rica
We would like to thank the following individuals and organizations who assisted in the preparation of this case study: Gerardo Galvis, Idalí Ledesman, Sandra Murillo, Xinia Bustamante, the local health team of the city of Neilly, Corredores Food Security Council.
The Faces, Voices and Places (FVP) initiative in Corredores, Costa Rica, started in 2006 as part of a larger initiative that was launched in 1998 to improve food security and nutrition in the region. In Corredores, the initiative also focused on water and sanitation. It involved the Ministry of Health, municipal government, local schools, Paso Canoas market, the Association of Rural Aqueducts, INCAP/PAHO, local health services, community groups, and the local Food Security Committee. A FVP office was established in the municipality to facilitate coordination, implementation and follow-up of activities. The community organization in place allowed for a greater commitment from all those involved to work collaboratively.
The Initiative worked with women, indigenous populations and children in various projects such as food cultivation and bread-making. Schoolchildren were involved in the design and implementation of recycling programs within schools. A community garden was established in two indigenous communities with food production aimed at providing for the population and for sale. Training and resources were offered to those working with solid waste disposal (gloves, appropriate attire) and a local committee of solid waste disposal workers was establish to improve capacity and give more dignity to this important job that contributed to local development and environmental sustainability.
The initiative promoted greater awareness of issues related to food security and nutrition, not only at a household level but also at community level. Infant mortality rates have decreased in Corredores since the beginning of this initiative, which was attributed to increased population awareness and education. All mothers now receive prenatal care regardless of their social situation. A higher level of community empowerment was also observed, with members demonstrating more confidence to identify problems and jointly discuss solutions. Health professionals also reported feeling more motivated to work with the community.
Working within the framework of the FVP initiative helped to attract national attention to this region of the country, resulting in higher commitment and resources available to work with these vulnerable communities and populations. Working with issues related to food security, water and sanitation also helped to identify and have an influence on other issues important to the community, such as environmental degradation and intra-family violence. As a result, the initiative shifted towards a focus on the determinants of health, bringing together various institutions and sectors and highlighting their roles in community wellbeing.
Lack of good management at the national level and among some of the institutions involved was highlighted as a significant challenge. Lack of follow-up from technical personnel at the national level, mostly caused by the remote location of the municipality caused some difficulties. The high level of children dropping out of school to work in the fields also hindered the success of the initiative although there were some efforts by school directors to keep children in schools.
By addressing various determinants of health, this initiative successfully improved the community’s quality of life by empowering women to be more independent and to play a more proactive role at the individual, family and community level; improving access to and the quality of food; and improving family income. It helped to strengthen social cohesion and the community’s capacity to organize itself and be involved in the solutions to their own problems. This experience highlights the importance of going beyond identifying the problems affecting a community, to also understanding their roots and the population’s capacity to make decisions and act individually and collectively.
Example 12: Early Detection of Breast Cancer through Mobile Mammography Services in Uruguay
We would like to thank the following individuals who assisted in the preparation of this case study: Adriana Serra, Elena Garcia Martinez, Maria Isabel Ressio Charvet, Mariana Perera, Mario Gonzalez, Rosana Díaz Rus
The Mobile Mammography Services, which is part of the Early Detection of Breast Cancer Program coordinated by the Honorary Commission to Fight Cancer, was launched in 2003 in four municipalities of the state of Colonia, Uruguay (Juan Lacaze, Colonia Valdense, Nueva Helvencia, and Rosario). It aimed at improving early detection of malignant tumors, as well at improving self-care and self breast exams among women in these municipalities. Mammography services were not available to women living in this remote area of the country prior to this initiative, which required them to travel to the state’s capital for services. This disproportionately affected women from poorer sectors of the community.
Various local stakeholders were involved in the planning stage of the initiative through the establishment of a Local Committee in each of the municipalities selected. This Local Committee raised money to cover the costs of bringing the mobile clinic to the communities and to pay for the health professionals that were staffing it. Community members also offered to transport women who could not get to the mobile clinic on their own, either due to the distance or to having physical disabilities. Due to the limited availability of the mobile services in each community, the emphasis was primarily on women who were 40 years or older, who lived in poorer neighborhoods, and who did not have regular access to health services.
Of the approximately 10,500 women over 40 years old living in these municipalities, the initiative managed to conduct a mammogram on 5,392, which was around 51% of this population group. Demand for services was high. Even though 100% of the appointments available were scheduled, each municipality still had a long waiting list of users who would have liked to have been seen. As a result, two permanent mammogram machines were installed in two of the localities included in this initiative. Even though these services are now only available in private clinics, it came about as a result of the population’s demands for services.
The initiative initially encountered some resistance. Some women were not well acquainted with mammography, which led them to be fearful and anxious of undergoing the examination. It was important to explain to them the science behind the exam and make sure they understood how beneficial it was to undergo. As a result, an informational campaign was created and delivered by local leaders through the media to address the main concerns of the population in regards to mammogram exams.
The initiative also successfully raised awareness of breast cancer through a continuous campaign aimed at improving women’s knowledge about their bodies and their rights. Although this improved women’s self care and awareness about breast cancer, it also created some challenges for the initiative to respond to the demand for services generated by this increased knowledge.
The municipalities included in this initiative had a high level of organization and community participation, which greatly contributed to the successful implementation and planning of the activities. Nevertheless, there were important rivalries among these sites, which created difficulties to establishing networks and collaborative links.
The initiative also resulted in the development of two important policies, one that allows women to take one day off per year to have a mammogram, and another one that offers free mammograms for women aged 40-59 every two years.
Example 13: Azucarlito “Free of Tobacco Smoke Workplace” Initiative in Uruguay
We would like to thank the following individuals who assisted in the preparation of this case study: Adriana Serra, Elena Garcia Martinez, Maria Isabel Ressio Charvet, Mariana Perera, Mario Gonzalez, Rosana Díaz Rus
The Azucarlito “Smoke-free Building” was launched in 2002 as an initiative to maintain a smoke-free work environment in a sugar factory in Paysandú, Uruguay. It started in response to an interest expressed by the factory management and a group of employees to work in a free of tobacco smoke setting. An initial baseline determined that 10% of the factory’s workers were smokers. Smoking cessation programs previously put in place to help staff quit the habit had not been effective.
Initially, activities aimed at improving knowledge about the negative consequences of smoking and the positive benefits of keeping spaces free of tobacco smoke. Also discussed were the distinctions between “active smokers” and “passive smokers.” Groups were set up to discuss individual and collective responsibilities for everyone’s health, which were facilitated by a doctor and a health promotion specialist. Smoking cessation support groups were established. Finally, a policy was implemented from the top management level declaring Azucarlito a “Smoke-free Workplace”, and outlining sanctions that would be applied to those who did not abide by the new rules.
The initiative resulted in many staff members quitting smoking while others significantly reduced the number of cigarettes smoked per day. The initiative gained media attention, which promoted Azucarlito as the “First Free of Tobacco Smoke Workplace” in the country and motivated other organizations to launch their own “Free of Tobacco Smoke Workplace” initiatives.
Leadership and coordination from a community organizer from the Honorary Commission to Fight Cancer was central to the success of the Initiative along with broad participation and support from all levels within the company. The Azucarlito Company had an expressed commitment to protect its workers’ health, which generated support from high levels of management within the company. Leadership from one manager in particular, who was an ex-smoker and who suffered serious health consequences as a result of his habit, was also highlighted as a crucial factor for the success of the experience. Workers also actively participated in all phases of the initiative. Some of the challenges included resistance to participating in the initiative’s activities and programs from smokers within the company, particularly those in higher levels of management.
The Azucarlito “Smoke-Free” initiative established an important and innovative model for health promotion programs and policies in Uruguay. The experience received national recognition and was replicated in various institutions. It also served as a model for the development of the National Decree 268/05, which prohibits smoking in all enclosed spaces in the country as part of the National “100% Spaces Free of Tobacco Smoke” initiative.
Example 14: Making the Rivera Town Council a Free of Tobacco Smoke Workplace in Uruguay
We would like to thank the following individuals who assisted in the preparation of this case study: Adriana Serra, Elena Garcia Martinez, Maria Isabel Ressio Charvet, Mariana Perera, Mario Gonzalez, Rosana Díaz Rus
The “Rivera Town Council Free of Tobacco Smoke” Initiative was launched in 2004 with the aim of transforming the main building of the municipality of Rivera’s Town Council into a workplace free of tobacco smoke. The initiative was designed and implemented by the Town Council’s staff and a coordinator from the Honorary Commission to Fight Cancer. Collaboration also took place with the radio program “Entre Todos” (“Among all of us”), which helped to disseminate information about the initiative and its results to the general population.
Initially, a working group named “Grupo Pro Calidad de Vida” (Group of Quality of Life), comprised of staff and managers from various departments of the Town Council was formed. They were given an office space with access to telephone, computer, printers and the Internet. The working group met regularly to discuss decisions and activities related to the Initiative. In the course of the Project, this group changed in line with the needs of the initiative’s various tasks and phases. The group’s diversity and the high level of commitment and participation from its members were highlighted as one of the main factors affecting the success of the initiative.
One of the main contributions from this group was the drafting of an internal policy regarding smoking in the workplace. This policy, once approved, led to the creation of areas designated for smoking and it transformed the Rivera Town Council into the first Town Council 100% Free of Tobacco Smoke in Uruguay. Smoking cessation programs were also implemented and made available to all staff. The initiative was officially recognized by the Mayor’s office and the city’s legislature approved a change in the municipal statute to support it. Involvement of the mayor in the activities increased during the course of the initiative. Local labor unions also supported the efforts.
An awareness campaign was developed to share information about the magnitude of the problem and the risks of first and second hand smoking to those working in the building. This was done through presentations and workshops with an oncologist and university professors, posters, stickers and other promotional materials such as mouse pads. Ashtrays were also placed in strategic places with reminders for people to deposit their cigarettes before entering the premises.
One of the initial challenges was the fact that tobacco smoke contamination at the workplace was not seen as a problem by staff, management and even health services. As awareness increased due to the Initiative’s efforts, the issue began to be perceived as a problem that needed to be addressed. A positive effect was also noticed on the perception by the local health services staff about how tobacco smoke affected the population’s health as a result of the Initiative. This led to the support of the health services to the initiative’s activities and greater promotion of local public policies to combat tobacco smoke contamination in the workplace.
One important factor hindering the success of this Initiative was the lack of will by some staff members to discontinue smoking at work. The policy aimed at making smokers either quit their tobacco usage or limit their tobacco consumption to non-work related areas. However, it required intense and constant enforcement in order to significantly curtail the tobacco smoke contamination in the workplace.
The Initiative has been sustainable and it managed to maintain a good level of participation in order to secure the results obtained. The level of tobacco smoke contamination in the building has decreased along with the number of smokers among the staff. The non-smoking policy in the workplace is well established and respected. Currently, the working group is focusing on documenting the experience in order to better disseminate its results and lessons learned to the community and health professionals.
Example 15: Community Promotion, Prevention and Education for Cardiovascular Health in Tala, Uruguay
We would like to thank the following individuals who assisted in the preparation of this case study: Adriana Serra, Elena Garcia Martinez, Maria Isabel Ressio Charvet, Mariana Perera, Mario Gonzalez, Rosana Díaz Rus
This community-based initiative, implemented since 2002 in the municipality of Tala, Canelones, aimed at promoting a better understanding of a holistic concept of health and to promoting the adoption of healthy lifestyles. It involved the local government, community organizations, public and private health services, rural and urban schools, local churches, the Honorary Commission for Cardiovascular Health, academia, sports organizations, health professionals, community health workers and community leaders. Initially, a baseline was taken to assess the population’s profile and the major problems affecting it. It demonstrated an aging population that suffered from a high prevalence of preventable conditions. These were mainly caused by changes in eating habits, sedentary lifestyle, alcoholism, smoking, high consumption of psychoactive drugs, and deterioration of social, economic and environmental conditions affecting cardiovascular health. Unemployment was particularly high, especially among the rural population. Health services focused almost exclusively on providing treatment, with very little promotion, prevention and education activities.
Activities included various activities such as a broad media campaign about the importance of healthy lifestyles, the incorporation of health teams in schools, the establishment of community groups and capacity-building activities. A series of projects sprung up from this initial effort (proper waste disposal, vector control, prevention of STDs, substance use and domestic violence, etc.), all under the same strategic line of action and with a focus on the most vulnerable population groups and those with specific cardiovascular risks (obesity, diabetes, addictions, etc.).
Some of the results observed included: increased awareness among health professionals regarding the importance of promoting healthy lifestyles and better understanding of health promotion strategies and mechanisms; greater acceptance of efforts conducted in a participatory manner and with the community; increased knowledge and healthy habits among adolescents and the elderly; greater participation and less isolation of the elderly population; better understanding of issues related to school health with the implementation of a more efficient follow-up and referral system; and the establishment of community health groups such as “Adultos en Movimiento“ (“Adults in Movement”) that works to prevent domestic violence.
One important factor supporting the Initiative was a change in the national government that took place in 2005. This led to an increase in technological developments and a greater emphasis on health issues in the media. It also led to a structural change in the health system, which now geared itself more towards health promotion and education, and strengthened primary health care strategies. This led to the inclusion of various social actors at the local level in the decision-making process, which greatly facilitated the planning and implementation of the initiative. This, in turn, generated greater interest and commitment on the part of the community with the Initiative.
Tool # 1: PAHO Guide for Documenting Health Promotion Initiatives
The PAHO Documentation Guide is a seven -part questionnaire that asks for information about your health promotion effort. The PAHO Documentation Guide’s primary purpose is to create a simple, standard format to help support documentation of health promotion initiatives. Use of the PAHO Guide will expand available indications about whether and how efforts are working to create conditions that promote health and health equity.
```html
Introduction
Mobilizing for Action through Planning and Partnerships (MAPP) is a framework for community health assessment and improvement planning developed by the National Association of County and City Health Officials (NACCHO) with support from the Centers for Disease Control and Prevention (CDC). MAPP outlines a three-phase process for communities to assess their public health needs and resources through a community health assessment (CHA), prioritize issues for improvement, and develop a collective community health improvement plan (CHIP) to address priorities and achieve health equity. The goal of MAPP is to achieve health equity, defined as “the assurance of the conditions for optimal health for all people (Jones, 2014).” MAPP has tools to examine the root causes of health inequities and social determinants of health to understand what is behind health inequities. It requires cross-sector collaboration among organizations to address these drivers, and broad engagement of community members for a community-owned process.
How to Access MAPP 2.0
MAPP 2.0 includes the following materials which are available for free download at Mobilizing for Action through Planning and Partnerships (MAPP) - NACCHO
- MAPP 2.0 User’s Handbook
- Starting Point Assessment
- Community Partner Assessment
- Community Status Assessment
- Community Context Assessment
- Power Primer
- Supplemental Tools: A downloadable folder of editable documents to use throughout MAPP
What is MAPP 2.0?
Mobilizing for Action through Planning and Partnerships (MAPP) is a framework for community health assessment and improvement planning. Through a three-phase process with unique tools and assessments, MAPP helps communities assess their public health needs and resources, prioritize issues for improvement, and develop collaborative community-wide strategies to achieve health equity.
History Of MAPP
MAPP was originally developed in 2001 by the National Association of County and City Health Officials (NACCHO) with support from the Centers for Disease Control and Prevention (CDC) as a framework for assessing and addressing community health needs with active community involvement. After a national evaluation of MAPP in 2019 and feedback from MAPP users, MAPP was updated to “MAPP 2.0” in 2023. MAPP 2.0 is grounded in a set of foundational principles promoting health equity and community engagement throughout the entire MAPP process. Read more about the history of MAPP in the MAPP Blueprint Executive Summary (PDF) (NACCHO, 2020), which outlines the history of MAPP and the original recommendations for MAPP’s redesign.
Why is MAPP Used?
MAPP is used to systematically identify what the most pressing issues are affecting population health at the community level and to make an actionable, realistic plan for how those issues can be addressed through the collective efforts of organizations and agencies across the entire community.
Addressing Health Equity through MAPP
The goal of MAPP is to achieve health equity, which is “the assurance of the conditions for optimal health for all people (Jones, 2014).” To achieve health equity, communities need to explore what root causes are driving health inequities — “differences in the distribution of disease, illness, and death that are systematic and unjust, actionable, and associated with imbalances in political power. (Whitehead, 1992).” MAPP helps communities explore what factors and conditions contribute to these unjust differences in health outcomes.
MAPP includes a reference tool, the Health Equity Action Spectrum, to explain the different kinds of factors that contribute to poor health outcomes:
- Health outcomes and behaviors (right): These can be measured to understand a community's current health status. This includes rates of illness, disease, and death, as well as the prevalence of healthy and unhealthy behaviors, such as exercising regularly or smoking tobacco.
- Social determinants of health (middle): These are living and working conditions in the community that contribute to the health outcomes and behaviors on the right. In this model, social determinants of health include service conditions, physical conditions, social conditions, and economic conditions. See examples in the graphic below.
- Root causes (left): The root causes of inequity are the many underlying factors, such as a society’s norms and values, culture, institutions, narratives, etc., that perpetuate discriminatory belief systems and ideologies.

Example: Redlining
Redlining can be defined as “a discriminatory practice that consists of the systematic denial of services such as mortgages, insurance loans, and other financial services to residents of certain areas, based on their race or ethnicity (Cornell Law School Legal Information Institute, n.d.).” This housing policy “blocked Black households and other communities of color from accessing home mortgages – and as a result homeownership – for decades (Gerken et al., 2023).” This was during a time of suburbanization, so Black households were left to stay in central cities while the population declined and investment in public services declined. In this example, this institution represents a “mechanism of power” influenced by, and perpetuating, racism. This, in turn, leads to residents of color experiencing poorer housing quality, healthcare access, and/or economic stability (the social determinants of health), resulting in inequitable health outcomes among those racial and ethnic groups who were discriminated against.
These root causes of inequity must be confronted, understood, and resolved. MAPP helps communities assess the health status of their community and take action to address the underlying factors to see positive change in population health.
The Foundational Principles of MAPP
The Foundational Principles were developed during the redesign of MAPP to MAPP 2.0 as the guiding values for all updates to the framework. Each step and tool of MAPP 2.0, the current version of MAPP, is grounded in these foundational principles:
- Equity: Encourages shared exploration of and community action to address the social injustices that create and maintain inequities.
- Flexible: Meets the needs of diverse MAPP communities through an adaptable framework.
- Continuous: Promotes continuous learning and improvement through multiple cycles of community assessment, planning, action, and evaluation.
- Community Power: Builds community power to ensure those most impacted by inequities are those who guide the process.
- Inclusion: Fosters belonging by identifying and removing barriers to community participation.
- Trusted Relationships: Builds connection and trust by honoring the knowledge, expertise, and voice of community members and stakeholders.
- Data and Community Informed Action: Identifies priorities, strategies, and action plans based in data of community needs.
- Strategic Collaboration and Alignment: Creates a strategy to improve community health that aligns the missions, goals, resources, and reach of partners across sectors.
- Full Spectrum Actions: Encourages community improvement through approaches addressing root cause, social determinants of health, and health outcomes that enable health and well-being for all.
Read the full definitions of the Foundational Principles in the MAPP 2.0 Handbook (PDF), available at Mobilizing for Action through Planning and Partnerships (MAPP) - NACCHO
When Should You Use MAPP?
MAPP is an appropriate framework to use for projects designed to assess health needs of a community and develop an actionable plan to address them with collaboration of agencies, organizations, groups, and individuals across the community.
There are certain circumstances that may indicate that a community health improvement process using MAPP would be beneficial:
- When there is an interest in exploring root causes of inequity. More sectors are continually becoming interested in understanding how social and systemic factors influence the well-being of the public. This can be seen in public health, education, healthcare, economic development, food security, and more. If shared root causes are coming to the attention of multiple sectors in the community, it may be helpful to explore them together.
- When there’s been an issue or crisis that resulted in lessons learned. When an epidemic, pandemic, community-wide infectious disease outbreak, or natural disaster occurs, the community may be interested in evaluating its public health system as it strives toward a healthy community.
- When it is mandated. Some municipalities or organizations may be required by the local, state, or federal government, or another authorizing body, to complete health improvement activities. These scenarios might prompt an organization to consider MAPP.
- When there’s money available for public health improvement. State, federal, and international agencies, as well as private foundations, may sometimes offer grants to conduct a process such as MAPP. Note that, with full community participation, a MAPP process could be conducted without outside funding.
- See the Tool Box section on Chapter 42, Section 4. Applying for a Grant and Chapter 42. Section 5. Writing a Grant
- When strategic planning across the community is needed for a specific public health priority. Although MAPP is intended to assess community health broadly, it can be adapted to guide a community-wide strategic planning process for a specific health priority. Current MAPP supplements can help guide this process to adapt MAPP for promoting healthy aging (pdf) and brain health (pdf).
MAPP is an adaptable framework, meaning that the guidance, assessments, and tools can be modified to fit the specific needs of a community. For example, one community might use MAPP assessment tools for their entire community health assessment, while another may use the quantitative Community Status Assessment and the qualitative Community Context Assessment as written, but develop their own survey tool to use in place of the Community Partner Assessment (a mixed-methods tool that engages members of the local public health system to identify how well they are working together to achieve health equity). MAPP is used by cities and counties, regions (e.g., multiple counties working together on one CHI process), states, and Tribes.
Who is Involved?
MAPP is implemented by the entire local public health system, which includes all organizations, agencies, and groups that contribute to population health including those in education, transportation, urban planning, agriculture, and more. The social determinants of health and root causes of inequity, which drive differences in health behaviors and outcomes, cut across many aspects of our lives and require investment of many sectors to be improved. The “Local Public Health System Jellybean Diagram” below depicts this diverse network. The community at the center illustrates that public health is about the community’s health and not the work of any one organization.

The following groups might be involved in MAPP to widely represent the community and the factors that contribute to community health:
- Community members: Remember that “the community” is at the center of the local public health system. The purpose of a CHIP process is to improve community health, so MAPP should actively involve community members to contribute their perspectives on how MAPP is implemented, their top health priorities, and the factors that contribute to and hinder community members’ opportunity for optimal health.
- Members of the local public health system:
- Local, state, or Tribal health department: The local health department, in line with recommendations from Public Health 3.0, can act as a convenor of partners across the community to collaboratively address challenges. Local health departments are frequently leaders of MAPP processes, although it could be led by others.
- Community-based organizations (CBOs): CBOs who offer health and non-health related services to the community should be involved in the MAPP process because of their proximity to community members and understanding of needs of specific populations. Residents may have more trust in CBOs than in government agencies or healthcare entities, so they provide a critical connection to community members, particularly people and communities most directly affected by health inequities.
- Health centers, including federally qualified health centers (FQHCs): Health centers provide valuable services to community members and increase access to care for many. They can provide valuable information about community needs and may offer insightful data about the region they serve. Health centers complete needs assessments every three years and may be interested in collaborating with other agencies through MAPP to complete their assessment.
- Nonprofit hospitals: Nonprofit hospitals can be important community health partners and may contribute data, programs, resources, and expertise to the MAPP process. They are important partners in MAPP due to their broad community reach, understanding of community needs through their community health needs assessment data, and potential ability to support future programming because of the CHIP.
- Organizations who contribute to the social determinants of health include the following. See NACCHO’s toolkit, Using Healthy People 2030 to Develop Multisector Partnerships, for information about partnerships across the SDOH and how to use Healthy People 2030 objectives to address community issues:
- Health care access and quality (e.g., social services organizations, public insurance)
- Food security (e.g., food banks, supplemental nutrition programs (WIC))
- Neighborhood and built environment (e.g., parks and recreation, transportation)
- Education (e.g., department of education, community colleges)
- Economic stability (e.g., housing agencies, unemployment support)
- Community power-building organizations: These groups are sometimes called “grassroots” organizations, “community organizers,” or “base-building groups.” They advocate for the needs of the community and needed changes, including those outside of government (Lead Local, n.d.).
- Resource contributors: Philanthropies, local foundations, grantors, or local businesses who can contribute resources such as funding to support staff time and purchasing of materials.
Different Agencies can use MAPP to Meet Accreditation Requirements and Organizational Standards
Different types of healthcare and public health organizations may complete community health assessments to meet accreditation, program, or federal requirements, and MAPP can help support those processes:
- Health departments pursuing or maintaining PHAB accreditation complete community, state, or Tribal health assessment and improvement planning activities as part of accreditation or reaccreditation requirements (The Public Health Accreditation Board is the national accrediting body for public health in the U.S.) See the MAPP 2.0 and PHAB Version 2022 Crosswalk (PDF) for information on how MAPP can be used to meet the most updated PHAB accreditation standards and measures.
- Health centers complete or update a needs assessment of their service area every three years (Requiring body: Bureau of Primary Health Care (BPHC) within the Health Resources and Services Administration (HRSA)), requirements).
- Nonprofit hospitals complete a community health needs assessment (CHNA) and develop a plan to address the needs every three years to maintain their 501(c)(3) nonprofit status (Authority: Internal Revenue Service (IRS)), requirements.
Who Is Involved?
Engaging Community Members
The purpose of MAPP is to improve the health of residents within a community, so residents should be engaged in MAPP from the very beginning. Community members do contribute to MAPP by engaging in the assessments and highlighting health needs and resources available to address them, but they also contribute to implementing the process itself. Community members should be made aware of MAPP as a process that they can become involved in, whether it be in a leadership position to set the direction for the process, help design the assessments, or contribute to selecting priorities for the community health improvement plan. MAPP begins with a “Stakeholder and Power Analysis” to assess who in the community should be involved in MAPP based on whether the process will impact them (e.g., through a new program or initiative to address inequities resulting from the CHIP), and their knowledge of community needs.
Engaging partners across sectors
Organizations, agencies, people, and groups across the local public health system should be actively involved in MAPP. No one agency or sector can improve population health alone – it requires the investment of many different people across all sectors within the community who can provide insight on what gets in the way of health, what resources can be used or acquired to improve health, and what actions can be taken to improve conditions that contribute to health and serve the community. Partners become engaged in all areas and steps of MAPP, including serving on the leadership committees, on the Assessment Design Team that implements the community health assessment process, or the Priority Issue Sub-committees that carry out the actions of the community health improvement plan.
Conducting a community health assessment (CHA) of needs and resources
Conducting the community health assessment involves determining what the assessment will measure, how the tools will gather that information, and how the data will be analyzed to uncover community health priorities. The community health assessment brings together qualitative data in the form of direct interactions with community members through interviews, focus groups, town halls, or other methods; quantitative data, or information that can be counted, from existing (secondary) sources or by gathering new (primary) data; and an assessment of the local public health system itself to identify opportunities to better work together to achieve health equity. The leadership committees, partners, and community members are all involved in this process.
Developing a community health improvement plan (CHIP) to address needs
After conducting the community health assessment, partners and community members analyze the data of the three assessments through “data triangulation” and use a set of criteria to uncover the community health issues and determine which will be included in the community health improvement plan (the “priority issues”). Those included in the CHIP will be the focus of future actions, initiatives, or programs to work toward improvement. Developing the CHIP involves creating a set of goals and objectives for each priority issue to outline what progress is expected within the next 3–5 (or more) years and working with organizations across the community to determine what actions will be taken by those organizations to make improvements. This might involve starting up new programs, improving existing programs, collecting new data about services, or reallocating resources from one initiative to another.
Continuous Quality Improvement
MAPP involves principles and activities of continuous quality improvement to enhance how the MAPP process itself is implemented and to improve effectiveness of the community health programs that are implemented because of MAPP.
The Three-Phased Process
MAPP outlines a three-phase process with steps and tools grounded in the Foundational Principles to complete these activities, described in the sections below.
- Phase I: Build the Community Health Improvement Foundation
- Phase II: Tell the Community Story
- Phase III: Continuously Improve the Community
MAPP, and community health improvement, is a cyclical process. When Phase III of one cycle is finished, Phase I of the next cycle begins to revisit community and partnership engagement, evaluate what could be improved in the process from the last cycle, and prepare for an updated assessment.

How do you MAPP?
Phase I - Build the Community Health Improvement Foundation
Phase I includes activities that build commitment and ownership among a wide variety of participants to set the stage for the rest of MAPP. This phase includes building relationships with community members and organizations, so the people involved in MAPP represent the entire community.
The goals of Phase I are to:
- Involve community members who represent populations experiencing inequities to guide and participate in MAPP planning
- Build strategic relationships with new and existing partners to engage throughout MAPP
- Establish the MAPP Core Group and Steering Committee that represent the community
- Develop a shared understanding of MAPP and the community’s vision for the future
- Evaluate what resources are available and needed to achieve MAPP’s goals effectively
- Create workgroups to build the infrastructure for CHI
There are eight steps within Phase I, described below.
Step 1: Do a Stakeholder and Power Analysis. MAPP begins with a Stakeholder and Power Analysis to create a list of potential people and groups to involve in MAPP based on an understanding of who could be affected by MAPP and who could have an impact on its success. The resulting list of groups and individuals is referenced throughout the rest of MAPP when opportunities arise to engage more people, and helps the community engage a wide array of community groups, community members, organizations, and agencies.
Example: City of Milwaukee’s Stakeholder and Power Analysis
The City of Milwaukee Health Department implemented the Stakeholder and Power Analysis as part of their 2023-2028 MKE Elevate community health improvement planning process. They utilized the MAPP planning spreadsheet and created an interview guide to conduct three interviews with community leaders. The interviews helped to uncover how the stakeholders might impact or be impacted by the MAPP process, deepened relationships with those stakeholders, and resulted in two of the three joining the MKE Elevate Steering Committee. This activity also resulted in a list of additional key stakeholders and a power analysis to help prioritize who to engage in the CHIP process. After priority issues were selected, the power analysis was repeated to inform specific strategies.
Step 2: Establish or Revisit CHIP Leadership Structures. Using the results of the Stakeholder and Power Analysis, convene the two committees who facilitate MAPP:
- Core Group: This is a small group of 2-3 individuals who manage the daily administration of MAPP (e.g., managing timelines, partner roles, funding, etc.)
- Steering Committee: A larger group of 10-20 individuals who include organizations across the local public health system and community members who provide direction to the MAPP process, similar to a board of directors.
Step 3: Engage and Orient the Steering Committee. The Steering Committee should be introduced or re-introduced to the MAPP process with each new MAPP cycle. Their orientation includes an overview of the MAPP process, opportunities for their participation, and health equity concepts. The Steering Committee develops a mission statement for their work together and values to guide how that work is done.
For example, a Steering Committee’s mission statement might be, "To better the health of county residents by building relationships, promoting healthy living, and advocating for lasting improvements across the community.”
Step 4: Establish Administrative Structures for MAPP. The community decides how the MAPP process will be administered, including how the logistics, funding, and partners are managed. For example, the Steering Committee could remain an informal coalition of partners, or they could become a formalized nonprofit organization with 501(c)(3) status to open more opportunities to receive funding. Guidance for arranging the administration, with insights on pros and cons of the various models, is included.
Step 5: Develop the Community Vision. The community vision is the long-term (10-15 year), aspirational goal for the community’s health. The vision is established through a facilitated, collaborative workshop among partners and community members. The vision statement depicts what the community is working toward through iterative MAPP cycles. The vision should be shared widely and recognized at each MAPP event.
For example, the community vision might be, “Our vision for a healthy future is a community in which every person can thrive physically, mentally, spiritually.”
Step 6: Do the Starting Point Assessment. The Starting Point Assessment (SPA) is a tool for continuous quality improvement. The SPA is used to assess performance in past MAPP cycles and set goals for improvement in the current cycle. The SPA explores six domains of a MAPP process: community engagement, partnerships, data and assessments, community health improvement plan priorities, leadership support for health equity, and resources and skills available. The Steering Committee uses the assessment questions and suggested metrics to assess those activities from their last MAPP cycle and set goals for improvement in the current cycle.
Step 7: Identify CHI Infrastructure Priorities and Develop Workgroups. The Steering Committee reviews the results of the Starting Point Assessment and prioritizes 2-5 continuous quality improvement goals for sub-committees called CHI Infrastructure Workgroups to address in the current cycle. For example, the community might create two CHI Infrastructure workgroups, with one dedicated to improving how community members are engaged throughout MAPP, and the other working to identify sustainable funding opportunities for the community health improvement work.
Step 8: Develop the Workplan and Budget. At this stage, the leadership committees have been formed, the vision for MAPP is set, and priorities to improve the current cycle are identified. The Steering Committee and Core Group can now build the workplan of key activities and budget to support them for the remaining two Phases of MAPP.
Phase II - Tell the Community Story
Phase II is all about collecting data to tell the story of the community’s health and well-being. Guidance and activities within this phase support communities in conducting a community health (needs) assessment (CH[N]A) by exploring health outcomes and behaviors, social determinants of health (SDOH), and root causes among all sub-populations within the community.
The goals of Phase II are to:
- Engage the community in developing a comprehensive and timely CH[N]A
- Identify the top population health priorities and health inequities in the community, including their root causes
There are six steps within Phase II, described below.
Step 1: Form the Assessment Design Team. Phase II begins with forming the Assessment Design Team (ADT), which is a diverse team representative of the community that brings various areas of expertise and resources to coordinating the design, implementation, and interpretation of the three MAPP assessments. Having one team that is responsible for, and can participate in, all aspects of Phase II, ensures communities can easily find connections through the spectrum of indicators (from downstream to upstream) and use these connections to describe the extent of the health issues in their communities.
Step 2: Design the Assessment Process. Once the ADT is formed, they will identify guiding questions that the community is looking to answer through the CH[N]A. These guiding questions will inform the assessments and help the community understand what “big picture” information to collect. Once the guiding questions are chosen, the ADT will determine how data answers these guiding questions, identify current resources and activities that can be leveraged to help the community collect data, and refine the CHI workplan to note which order the assessments will be completed in.
Step 3: Do the Three Assessments. The three MAPP assessments are an essential component of Phase II, as they support communities in gathering data and information from several perspectives including qualitative and quantitative sources to deepen their understanding of health inequities. This involves examining a range of indicators, including health outcomes and behaviors, SDOH, and root causes of health, or systems of power, privilege, and oppression. The ADT works with a broad network of sectors and partners to guide their community through an analysis of historical and structural factors that reveal the root causes of inequity, while also ensuring that rich views and strengths-based data from lived experience is included.
The three MAPP assessments are described briefly below, but more detailed information regarding each assessment can be found in the below sections. Click the title of the assessment to jump to the detailed assessment overview.
The Community Partner Assessment (CPA) is used to understand partners’ individual systems, processes and capacities, and the collective capacity as a network to address health inequities.
The Community Status Assessment (CSA) collects quantitative data on demographics, health status, and health inequities and highlights inequities related to health outcomes and behaviors, SDOH, and systems of power, privilege, and oppression.
The Community Context Assessment (CCA) collects qualitative data on the insights, expertise, and views of people directly affected by inequities to understand the community’s strengths, assets, and culture.
Step 4: Triangulate Data, Identify Themes, and Develop Issue Statements. After the three MAPP assessments are conducted, the ADT will work with key influencers, partners, and community members to identify cross-cutting themes that are supported by the assessment findings through a data triangulation process. Issue statements will be developed for each, cross-cutting them to identify and summarize why and how the issue occurs, how serious it is, and its outcomes and impacts.
Step 5: Develop Issue Profiles through Root Cause Analysis. Issue profiles are 1–2-page documents for each cross-cutting theme, or issue, that connect the status of the community’s health and well-being to potential strategies. They are used in the community’s full CH[N]A report to highlight key aspects of community health revealed by the data, when prioritizing which issues the CHIP will focus on, and when creating community partner profiles for the chosen priority issues in Phase III. Conducting a root-cause analysis, such as a Fishbone Diagram or 5 Whys, of each issue will help build out the components of an issue profile, as a root-cause analysis can help reveal the systems of power, privilege, and oppression that might be impacting health outcomes in a community.
Example from the Field: Johnson County Public Health in Johnson County, Iowa (Healthy JoCo) involved many key influencers, partners, and community members in their data triangulation process, which resulted in 13 issue profiles. They hosted a “Theme Matching Day” where key influencers, partners, and community members were asked to review data collected from the three assessments to develop themes that aligned with the following categories: health behaviors and health outcomes; social determinants of health; systems of power, privilege, and oppression; and community strengths and organizational capacity. Participants were able to visually see and organize the data along these categories and it allowed the group to identify gaps in the data. Healthy JoCo also conducted a community-wide survey to involve the broader community in this theming process in which participants were able to review the data and create their own themes within these categories. From the in person “Theme Matching Day” and the community-wide thematic survey, JoCo created 13 issue profiles that included the definition and summary, issue statement, prevalence and trends, equity, contributing factors, and community input and thoughts for all identified issues. JoCo used an online platform to share these issue profiles with their community. Visit the HealthyJoCo webpage for more information.
Step 6: Share CH[N]A Findings. Many communities will develop a written CH[N]A report, which allows them to include sections that align with assessment requirements for different requiring bodies such as PHAB, IRS, and HRSA. In addition to sharing a written report, communities should also consider sharing methods and platforms that can be updated annually and easily understood by community members. This includes online data dashboards, online summary reports, community presentations, or an interactive website.
The Three Assessments
Below are detailed overviews of the three assessment tools that make up the MAPP 2.0 community health assessment. These are conducted earlier in Phase II.
Community Partner Assessment
The Community Partner Assessment (CPA) is designed to assess both the individual and collective capacities of community partners to improve health equity and strengthen the local public health system. In this assessment, organizations examine how they contribute to, or inhibit, progress toward health equity through a survey of each organization in the local public health system and a series of discussion meetings to consider opportunities for improvement in addressing systemic health inequities.
The CPA has five goals:
- Describe why community partnerships are critical to community health improvement (CHI) and how to build or strengthen relationships with community partners and organizations
- Name the specific roles of each community partner to support the local public health system (LPHS) and engage communities experiencing inequities produced by systems
- Assess each MAPP partner’s capacities, skills, and strengths to improve community health, health equity, and advance MAPP goals
- Document the landscape of MAPP community partners, including grassroots and community power-building organizations, to summarize collective strengths and opportunities for improvement
- Identify whom else to involve in MAPP and ways to improve community partnerships, engagement, and power-building
To achieve these goals, the CPA includes guidance to facilitate an orientation meeting for partners, a survey to gather information about the local public health system, and a series of discussion meetings to reflect on the findings and identify opportunities for improvement.
- Orientation Meetings: The process begins with two orientation meetings for members of the local public health system who are invited to participate in the CPA. The meetings create a foundation for collaboration by introducing the purpose of the CPA and fostering trust among partners. These sessions clarify how different organizations contribute to public health, build consensus on shared values, and ensure that all voices are heard before moving into data collection and analysis.
- CPA Survey: The survey gathers data about organizational capacities, roles, and relationships between members of the local public health system to assess the strengths and gaps of the system. The survey is distributed to all participating organizations. The CPA findings are summarized into accessible and actionable results that provide a strong foundation for partner discussions and decision-making. Organize findings into “What’s working,” “What needs improvement,” and “Who else should be involved?” If qualitative responses are included, pull powerful quotes to highlight key insights
- Partner discussion meetings: Following the survey, the partners are engaged in facilitated conversations and activities to process survey findings, explore systemic challenges, and foster a collaborative approach to health equity. These conversations further build trust, challenge existing power dynamics among partners, and strengthen their commitment to advancing health equity. The discussions build a deeper understanding of how community partners can work together and lead to actionable strategies for improving public health systems.
Tips to Encourage Survey Participation
Surveys can feel like a burden to busy partners. Use these tips to increase participation:
• Frame participation as a benefit and highlight how the data will be used
• Ensure survey questions are concise and relevant
• Offer multiple ways to complete the survey (online, paper, or interviews)
• Set clear deadlines, but allow room for flexibility if needed
• Send personal reminders to complete the survey
Results of the CPA survey and discussion meetings are summarized in a final report of key findings and themes (e.g., LPHS strengths, capacities, and challenges advancing equity), and recommendations to guide public health decision-making. A draft of the report should be shared with partners for feedback and revisions, published as part of the comprehensive community health assessment.
Community Status Assessment
The Community Status Assessment (CSA) is a quantitative tool used to collect data about the demographics, health status, and health inequities of a community. It helps a community move upstream and identify inequities beyond health outcomes and behaviors, including their association with the SDOH and systems of power, privilege, and oppression.
The CSA helps a community answer the following questions:
- What does the status of your community look like, including health, socioeconomic, environmental, and quality-of-life outcomes?
- What populations experience inequities across health, socioeconomic, environmental, and quality-of-life outcomes?
- How do systems influence outcomes?
To answer these questions, the CSA encourages communities to identify and select indicators across levels of influence: individual, family, organizational, community, policy, and systems. Indicators are measures that describe community conditions (e.g., poverty rate, insecure housing rate, food insecurity, life expectancy at birth, heart disease mortality rate) now and over time. Identifying indicators that represent health status, behaviors, and outcomes; SDOH; and systems of power, privilege, and oppression will help tell the full story of the community, including the root causes of inequities impacting the community.
Example Indicators
These are some examples of indicators across the Health Equity Action Spectrum:
- Health status: Life expectancy, poor mental health days, unhealthy physical days, self-reported fair/poor health
- Disease/injury: Heart disease prevalence, diabetes prevalence, STI infection rate, nonfatal injury
- Health behaviors: Physical inactivity, adolescent birth rate, alcohol use, smoking and tobacco use
- Mortality: Infant mortality rate, maternal mortality rate, drug overdose deaths
Social Determinants of Health:
- Neighborhood and Built Environment: Air quality, walkability index
- Economic stability: Children in poverty, living wage, unemployment
- Social and community context: Social associations, violent crime
- Healthcare access and quality: Access to primary care, uninsured
- Education access and quality: High-school students who left school before graduating, preschool enrollment
- Systems of power, privilege, and oppression: Residential segregation, eviction rate, voter turnout, police officers, employment-population ratio
For more examples of these indicators, see the CSA Indicator Matrix within the CSA tool.
Communities are encouraged to identify and collect two types of data on their chosen indicators:
- Primary data – Data collected by the researcher (e.g., community-wide survey)
- Secondary data – Existing data or data collected by someone else (e.g., Census Data)
This allows for an opportunity for communities to identify data that they and their partners have already collected (secondary data) on the chosen indicators and then create a data collection plan to collect primary data to fill in any data gaps that are left after identifying available secondary data.
As the CSA is a community-driven assessment, it is important that community members are involved in all aspects to ensure that this assessment reflects them and the community’s unique characteristics. Community members should be involved in determining the purpose of the CSA; identifying indicators to inform the CSA; data collection, organization, analysis, and interpretation; and presenting and sharing the results of the CSA.
Example from the Field: A Tribal community in the Great Plains offers an example of a community-centered approach to data collection in a rural, reservation-based context. Tribal health administrators worked with an external institute to collect data on adoption programs in the Tribal community. They traveled to communities within the reservation and talked to birth mothers who had placed children for adoption. Before each visit, they promoted the project and shared when they would be there through flyers, radio, and local newspapers. They centered local voices by working with a student who lived on the reservation and helped interview birth mothers. They brought a meal to the community during visits. This respectful strategy led to successful data collection.
Community Context Assessment
The Community Context Assessment (CCA) is a qualitative tool to gather community members’ perspectives on the factors that contribute to their health. The CCA explores three domains:
- Community Strengths and Assets: Skills, abilities, and gifts within community members that contribute to the community’s health. For example, creativity and art, education and support of others’ education, communication skills, and healing practices.
- Built Environment: Human-made, physical aspects of the community that contribute to, or hinder, health. For example, housing, green space, public art, bike lanes, public bathrooms, and public transportation.
- Forces of Change: Events that have happened in the past are happening now, or could happen in the future that impact the community’s health. They include trends over time (an aging population or climate change), factors specific to the community (rurality, presence of immigration detention centers), or events (a major employer leaving or coming to the community, a natural disaster).
The CCA employs qualitative methods to gather community insights on these domains. Qualitative methods gather non-numerical data and may include focus groups, key informant interviews, windshield or walking surveys, community dialogues, town halls, archival research and analysis, policy analysis, or photovoice.
The CCA is aimed at gathering insights from community members who are most directly affected by health inequities so that they can provide insight into what may be contributing to those inequities. This will help the community prioritize the most pressing issues for community members who are most directly affected by inequities, and identify solutions to those issues that are relevant to them.
Phase III - Continuously Improve the Community
Overview
Phase III is the culmination of the MAPP 2.0 process, where the strategic groundwork established in earlier phases is transformed into actionable efforts. This phase focuses on developing and implementing a Community Health Improvement Plan (CHIP), a three-to-five-year roadmap to address key public health priorities. The CHIP emphasizes equity by targeting the root causes of health inequities and leveraging social determinants of health (SDOH) to create sustainable change. With community collaboration at its core, Phase III ensures that public health improvement efforts are inclusive, data-driven, and continuously refined through methods like continuous quality improvement (CQI) and rapid cycle improvement.
By emphasizing shared goals and partnerships, this phase sets the stage for collective action and accountability. Communities examine where they are, where they want to be, and how they will achieve their vision. Transformational approaches are prioritized to shift systemic inequities, and strategies are tailored to maximize impact and sustainability. Throughout this process, Phase III keeps equity at the forefront by involving diverse stakeholders and ensuring that resources and actions align with the needs of those most affected by health inequities.
Step 1: Prioritize Issues for the CHIP: The first step in Phase III is prioritizing the strategic issues identified during Phase II. Communities select three to five critical issues that reflect their vision and address the most pressing health challenges. Prioritization is guided by a facilitated process (e.g., multi-voting, prioritization matrices) and criteria such as the issue’s relevance to community members, its magnitude and urgency, the availability of solutions, and the potential for upstream interventions to address root causes. This step ensures resources are directed toward manageable goals, maximizing the potential for meaningful change.
Example from the Field: Lawrence-Douglas County Public Health, KS had 14 issues from their CHA. From this number, they prioritized 6 issues for their 2024-2028 CHIP. This included two sustaining issues—safe and affordable housing and behavioral health— from past cycles and 4 new emerging issues: Access to Health Services, Birth Outcomes, Food Security and Jobs, living wage, poverty.
Step 2: Conduct Power Analysis on Each Issue. Once priorities are established, a power analysis is conducted to identify the systems, organizations, and individuals influencing each issue. This analysis helps uncover the factors perpetuating problems, as well as opportunities to build influence among those most impacted. Stakeholders are categorized based on their level of power and support for addressing the issue, creating a strategic map for engagement.
For instance, when addressing housing insecurity, a power analysis might reveal that local policymakers and housing developers hold significant influence over zoning and resource allocation. At the same time, community-based organizations may be strong allies but lack decision-making power. Engaging high-power supporters, shifting power to underrepresented community members, and finding common ground with people who hold differing perspectives will be important for making progress. The Stakeholder and Power Analysis from Phase I can be referenced here, and a power mapping exercise is used to visualize these relationships and guide targeted outreach and collaboration.
Step 3: Form Priority Issue Subcommittees. Effective implementation of the CHIP relies on forming subcommittees dedicated to each priority issue. These groups consist of community members, partners, and stakeholders who bring diverse expertise and lived experiences. Subcommittees develop goals, strategies, and action plans while fostering accountability throughout the process.
Membership selection is informed by the Stakeholder and Power Analysis in Phase I, as well as power mapping from Phase III, Step 2. For example, a subcommittee addressing mental health inequities might include public health officials, mental health providers, advocacy groups, and residents from communities with limited access to resources and services. Each subcommittee is guided by a chair who facilitates meetings, tracks progress and ensures alignment with the overall CHIP. By involving those directly impacted by the issues, subcommittees build trust, strengthen partnerships, and ensure the CHIP reflects community priorities.
Step 4: Create Community Partner Profiles. To achieve health equity and ensure the success of the CHIP, Phase III emphasizes the strategic alignment of community partners. Partners are critical for implementing the CHIP effectively. This step involves creating comprehensive profiles for each partner, capturing their values, mission, resources, and programmatic efforts related to the identified priority issues. The profiles provide a structured way to understand how each organization’s work aligns with the goals and priorities of the CHIP. Information collected includes organizational missions, resources available to support CHIP activities (e.g., funding for community engagement, meeting spaces, data-sharing capacities, or technical expertise), current programs (e.g. current advocacy efforts), and the populations they serve.
Step 5: Develop Shared Goals and Long-Term Measures. Subcommittees work collaboratively to establish broad, long-term goals for each priority issue, supported by shared measures that track progress. Goals should be transformational, aiming to address systemic inequities and achieve the community’s vision. For example, a goal to improve access to healthcare might focus on reducing transportation barriers and increasing provider availability in rural areas.
Shared measures provide a framework for accountability and collective impact. These metrics, such as the percentage of uninsured residents or the availability of public transit options, are agreed upon by all partners to ensure alignment and transparency. Subcommittees use assessment data, issue profiles, and community strengths to inform their decisions, ensuring goals are achievable and grounded in evidence.
Transactional vs Transformational Goals
As you form goals, it is important to think about whether your approach is transactional or transformational. Transactional goals address immediate needs but don’t change the conditions that created the problem. Transformational goals shift policies, systems, and power structures to create lasting change.
An example of this goal shift, related to diabetes is:
- Transactional: Increase access to diabetes management program.
- Transformational: Change food policies to make fresh, healthy food affordable, and accessible in every neighborhood
This shift focuses on moving from short-term, individual interventions, like increasing access to programs, to addressing root causes through systemic changes, such as altering policies to make healthy food accessible for all.
Step 6: Select CHIP Strategies. Strategies are the actions communities take to achieve their goals. These may include policy changes, programmatic interventions, or system-level reforms. Communities prioritize strategies based on their feasibility, impact, and alignment with equity principles. For instance, addressing food insecurity might involve creating a local food hub, advocating for policy changes to support urban agriculture, or expanding food assistance programs.
To ensure success, communities use tools like rapid cycle improvement (Plan-Do-Study-Act) to test and refine strategies. Evidence-based practices and community-driven solutions are prioritized to ensure relevance and effectiveness. Subcommittees also consider the barriers to implementation, such as resource constraints or opposition, and develop plans to address them.
Example from the Field: County of San Luis Obispo Public Health Department, CA implemented a health equity-centered SDOH-level strategy to address farm workers’ health. During the COVID-19 pandemic, they convened a task force of representatives who serve the Latinx/Mixteco communities to advise the LHD on its response and to share information with the community about COVID-19 testing, vaccines, and recovery. This task force, which has simultaneous Spanish and English interpretation, continues to meet monthly and has expanded its scope to share resources and include other topics of interest to the farm worker, Latinx, and Mixteco communities including a focus on other diseases including MPX, Valley Fever, and Heat Stroke/Exhaustion, and issues such as mental health resources, especially for youth; housing, and unemployment benefits.
Step 7: Develop CQI Action Plans. Action planning is a cornerstone of Phase III, translating goals and strategies into detailed steps that guide implementation. Plans include specific objectives, timelines, and responsibilities, ensuring all participants are accountable. Continuous quality improvement (CQI) cycles are embedded in this process to allow for regular evaluation and adaptation.
For example, an action plan to reduce childhood obesity might include objectives like increasing physical activity in schools, launching community education campaigns, and expanding access to healthy foods. Each objective is tied to measurable outcomes, such as the percentage of children meeting physical activity guidelines. CQI cycles help track progress, identify challenges, and refine interventions to maximize impact.
Step 8: Monitor and Evaluate the CHIP. The final component of Phase III is monitoring and sustaining the CHIP. Regular evaluations ensure strategies are implemented as intended and are achieving their desired outcomes. Communities track process metrics, such as the number of participants in a new program, and outcome metrics, like changes in health indicators.
This step emphasizes transparency and community involvement. Sharing progress through dashboards, reports, or public meetings keeps stakeholders informed and engaged. For instance, a community might host quarterly forums to update residents on CHIP activities and gather feedback. By continuously monitoring and adapting the CHIP, communities ensure their efforts remain responsive to changing needs and priorities.
Conclusion
Phase III represents the culmination of the MAPP process, where planning becomes action. By prioritizing equity, fostering collaboration, and using data-driven approaches, communities create sustainable systems of health improvement. This phase empowers local health departments and their partners to address root causes, elevate underrepresented community voices, and achieve their shared vision of a healthier future.
A Cyclical Process
MAPP, and community health improvement, is a cyclical process. As the community health improvement plan is being implemented, the community will look toward starting up their next Phase I to prepare for an updated community health assessment. Each cycle of MAPP should build upon the last, incorporating lessons learned about how to facilitate the process, who to engage and how, and how to ground the process and vision in equity.
Power Primer
The Power Primer is an optional supplemental tool to MAPP. The Power Primer explains why and how to address power dynamics within MAPP, acknowledge societal power imbalances as a root cause of health inequities, and support building community power throughout MAPP and community health improvement. It is intended for communities who have an established understanding of health equity and how to assess and address health inequities. These communities can use the Power Primer to confront power dynamics within their own MAPP process, to better support building the power of community members as they are involved in MAPP.
The Power Primer is based on the Power Framework, which presents a cycle of seven Power Practices for the Steering Committee and key partners in MAPP to complete:
- Process: Unpack personal and organizational power and privilege by reflecting on experiences of power, privilege, and oppression as individuals, and to name power dynamics within the organization(s).
- Form: Build a container for your work to challenge existing group dynamics and prioritize relationships, trust, and authenticity in your work with each other to unpack and understand power.
- Study: Learn about the community’s histories to understand why and how inequities came to be.
- Build: Grow relationships with communities and new partners.
- Share: Practice power sharing with partners and communities, letting go of historic or status quo practices that have maintained power and advantage for some.
- Strategize and Act: Implement, amplify, and invest in community-identified priorities and solutions.
- Evolve: Reflect on process, outcomes, accountability, and sustainability of the MAPP and CHI process, and implementation of these power practices.
The Power Primer includes suggested activities for each of the seven Power Practices to be used throughout MAPP. Download the Power Primer (PDF) via the NACCHO Toolbox.
In Summary
Mobilizing for Action through Planning and Partnerships (MAPP) is an effective process for community health improvement that has been tested and informed by public health practitioners nationwide for over twenty years. The most updated version, MAPP 2.0, centers principles of health equity and community engagement. MAPP engages individuals, organizations, agencies, and groups across the community to identify their top health priorities and address them through a collective action plan. It can be used any time there is a pressing health priority that requires broad community investment or a desire from partners across sectors to address shared, underlying root causes of inequities.
Additional Resources
The following resources may be helpful to communities implementing MAPP:
- NACCHO’s MAPP Webpage includes links to the following:
- Downloadable MAPP materials: Access the MAPP 2.0 Handbook and all supplemental tools to the framework mentioned above
- Training information: Details about in-person trainings that walk through the entire MAPP 2.0 process
- Technical assistance: Guidance to request technical assistance from NACCHO’s MAPP team
- Supplemental resources: Tools that provide information about how to integrate MAPP with specific public health focus areas (e.g., this guide to Explore Healthy Aging Data through Community Health Improvement (PDF), developed with Trust for America’s Health), or align MAPP with other public health frameworks, (e.g., this MAPP 2.0 and PHAB Version 2022 Crosswalk (PDF) that aligns MAPP 2.0 with public health accreditation standards and measures)
- MAPP Network Virtual Community: The MAPP Network is a virtual community for individuals and organizations who are interested in the MAPP framework for community health improvement. It offers:
- Tool Repository: Reference materials and templates for your CHI process
- Discussions: Open forum discussion boards
- Strategy Bank: Community health improvement plan activities from local health departments and their communities
- Example CHIPs: Example MAPP community health improvement plan.
- CHI Webinar Warehouse: Recommended CHI and MAPP 2.0 virtual recorded sessions
- Asynchronous Trainings: Eleven (11) pre-recorded overviews of each phase and tool of MAPP 2.0
- Examples from the Field: Story Bank of MAPP communities’ experiences using the framework
- Email mapp@naccho.org with questions and to request technical assistance
Resources
Online Resources
Cornell Law School Legal Information Institute article on Redlining.
Achieving Healthier Communities through MAPP: A User’s Handbook (PDF) by the National Association of County & City Health Officials.
Assessing the legacies of historical redlining: Correlations with measures of modern housing instability (PDF). Investigate how historical redlining patterns are linked to current housing instability risks.
Atlantic County Community Health Improvement Plan (PDF). This information may also be useful outside of Atlantic County, New Jersey.
Lead Local's Glossary provides definitions and resources on the topics related to community organizing, advocacy, and research.
The MAPP section of the website of NACCHO, the National Association of County and City Health Officials, co-developer with the U.S. Centers for Disease Control and Prevention, of the MAPP model. The website includes numerous tools for communities engaged in MAPP, many of them specific to individual MAPP phases and activities. Among these tools are illustrated guides that can be used to provide information to the community and participants in the process.
A Strategic Approach to Community Health Improvement (PDF) is an especially good field guide.
Print Resources
Jones CP. Systems of power, axes of inequity: parallels, intersections, braiding the strands [published correction appears in Med Care. 2014 Dec;52(12):1068]. Med Care. 2014;52(10 Suppl 3):S71-S75. doi:10.1097/MLR.0000000000000216
Jones CP. Systems of power, axes of inequity: parallels, intersections, braiding the strands [published correction appears in Med Care. 2014 Dec;52(12):1068]. Med Care. 2014;52(10 Suppl 3):S71-S75. doi:10.1097/MLR.0000000000000216
Whitehead M. The concepts and principles of equity and health. Int J Health Serv. 1992;22(3):429-445. doi:10.2190/986L-LHQ6-2VTE-YRRN
___What is MAPP 2.0?
- Mobilizing for Action through Planning and Partnerships (MAPP) is a framework for community health assessment and improvement planning to achieve health equity.
- MAPP 2.0 was developed as an update to MAPP 1.0 in 2023 in response to a national evaluation. It centers principles of health equity and community engagement and offers a more streamlined process to community health improvement.
___MAPP’s foundational principles are:
- Equity: Encourages shared exploration of and community action to address the social injustices that create and maintain inequities.
- Flexible: Meets the needs of diverse MAPP communities through an adaptable framework.
- Continuous: Promotes continuous learning and improvement through multiple cycles of community assessment, planning, action, and evaluation.
- Community Power: Builds community power to ensure those most impacted by inequities are those who guide the process.
- Inclusion: Fosters belonging by identifying and removing barriers to community participation.
- Trusted Relationships: Builds connection and trust by honoring the knowledge, expertise, and voice of community members and stakeholders.
- Data and Community Informed Action: Identifies priorities, strategies, and action plans based in data of community needs.
- Strategic Collaboration and Alignment: Creates a strategy to improve community health that aligns the missions, goals, resources, and reach of partners across sectors.
- Full Spectrum Actions: Encourages community improvement through approaches addressing root cause, social determinants of health, and health outcomes that enable health and well-being for all.
___MAPP’s three phases are:
- Phase I: Build the Community Health Improvement Foundation
- Phase II: Tell the Community Story
- Phase III: Continuously Improve the Community
Why use MAPP?
___MAPP is used to systematically identify what the most pressing issues are affecting population health at the community level and to make an actionable, realistic plan for how those issues can be addressed through the collective efforts of organizations and agencies across the entire community.
___The goal of MAPP is to achieve health equity, which is “the assurance of the conditions for optimal health for all people”2. MAPP helps communities explore what factors and conditions contribute to unjust differences in health outcomes
Who should take part in and use the MAPP process?
-
MAPP is implemented by community members and the entire local public health system including:
___Local, state, or Tribal health department
___Community based organizations (CBOs)
___Health centers, including federally qualified health centers
___Non-profit hospitals
___Organizations who contribute to the social determinants of health including:
___Health care access and quality (e.g., social services organizations, public insurance)
___Food security (e.g., food banks, supplemental nutrition programs (WIC))
___Neighborhood and built environment (e.g. parks and recreation, transportation)
___Education (e.g., department of education, community colleges)
___Economic stability (e.g., housing agencies, unemployment support)
___Community power building organizations
___Resource contributors
When might you employ a MAPP process?
___MAPP is best suited for guiding a broad strategic planning process that engages organizations and groups across the community, or in the following scenarios:
___When there is an interest in exploring root causes of inequity
___When there’s been an issue or crisis that resulted in lessons learned
___When it is mandated for the municipality (e.g, by the state for the county) or for the organization (e.g., non-profit hospital)
___ When there’s money available for public health improvement
___When strategic planning across the community is needed for a specific public health priority
How do you conduct a MAPP process?
-
Phase I: Build the Community Health Improvement Foundation
___Do a Stakeholder and Power Analysis
___Establish or Revisit CHI Leadership Structures
___Engage and Orient the Steering Committee
___Establish Administrative Structures for MAPP
___Develop the Community Vision
___Do the Starting Point Assessment
___Identify CHI Infrastructure Priorities and Develop Workgroups
___Develop the Workplan and Budget
-
Phase II: Tell the Community Story
___Form the Assessment Design Team
___Design the Assessment Process
___Do the Three Assessments
___Implement the Community Partner Assessment (CPA)
___Implement the Community Status Assessment (CSA)
___Implement the Community Context Assessment (CCA)
___Triangulate Data, Identify Themes, and Develop Issue Statements.
___Develop Issue Profiles through Root Cause Analysis
___Share CH[N]A Findings
-
Phase III: Continuously Improve the Community
___Prioritize Issues for the CHIP
___Conduct Power Analysis on Each Issue
___Form Priority Issue Subcommittees.
___Create Community Partner Profiles
___Develop Shared Goals and Long-Term Measures
___Select CHIP Strategies
___Develop CQI Action Plans
___Monitor and Evaluate the CHIP
- (Optional) Implement the Power Primer supplement that explains why and how to address power dynamics within MAPP, acknowledge societal power imbalances as a root cause of health inequities, and support building community power throughout MAPP and community health improvement
Example #1: Multnomah County Health Department
This is an example from the National Association of County and City Health Officials (NACCHO) website.
People with disabilities make up 16% of the total population of Multnomah County, Oregon. The Multnomah County Health Department (MCHD) and its community partners were interested in promoting health and well-being for these 115,000 county residents with disabilities. Working with the National Association of City and County Health Officials (NACCHO), the partners conducted the MAPP process to begin working toward this community goal.
Phase 1, Organize:
The Multnomah County Health Department (MCHD) partnered with several community organizations with funding from NACCHO.
Some of the community partners included:
- Oregon Health & Science University's Center of Excellence in Women's Health.
- Vocational Rehabilitation.
- Multnomah County Aging & Disability Services.
- City of Portland.
- State Independent Living Center.
- CareOregon.
- Center on Community Accessibility.
- Portland State University.
- AMHSA Advisory Council Member.
- Disability Arts and Cultural Program.
- Office of Emergency Management.
- Department of Human Services: Seniors & People with Disabilities, Arthritis Program, Oregon Asthma Program, & Tobacco Prevention Education
Phase 2, Vision:
The partnership worked together to brainstorm and decide upon a common vision: health and wellbeing for those with disabilities in Multnomah County.
They decided that their purpose was to "help the Health Department begin to address the health promotion needs of people with disabilities in their clinics and community.”
Phase 3, Assessments:
The Multnomah County Health Department (MCHD) Community Capacitation Center (CCC) created a Steering Committee that was divided into three subcommittees. With support from the MCHD Assessment and Evaluation Unit, the first subcommittee conducted a sample survey of health department clients with disabilities.
These surveys were based on stakeholder feedback and the existing literature on health promotion programming for people with disabilities. They were conducted in the waiting rooms of six primary care clinics operated by the Multnomah County Health Department. Survey staff (Health Department staff and public health/nursing students) approached all adult clients after they checked in and asked whether they would be interested in completing the survey. Surveys in Spanish were available at all locations, and Spanish-speaking staff were available at some locations to facilitate. The surveys were self-administered when possible and read to participants when wanted or needed.
Because survey takers were self-selected (not a random sample), findings cannot be generalized to the larger population of primary care clients seeking care at the Health Department and prevalence rates of disabilities cannot be determined from the survey results. The findings do speak for the group of clients responding, however, and can be used to inform future planning steps.
Of the total 144 surveys completed by individuals seeking health care in one of the Health Department's primary care clinics, 69 identified themselves as having a disability based on inclusion criteria.
The following findings are for these 69 respondents:
- 64% reported having a condition that greatly limits basic physical activities, such as walking, climbing, reaching, lifting, or carrying.
- 62% reported having a condition that results in difficulties with learning, remembering, or concentrating.
- 61% reported having a condition resulting in difficulties with working at a job or business.
- 58% reported a recurring condition that limits their ability to conduct basic daily activities.
- 41% reported difficulties with going outside the home alone to shop or visit a doctor’s office.
- 38% reported a mental health condition that limits basic daily activities.
- 33% reported a disability that limits functions such as learning, understanding or processing information.
- 32% reported difficulties with dressing, bathing, or getting around the houses.
- 25% reported deafness or a severe hearing loss.
- 92% wanted to know about health promotion activities, information, and support when these become available.
- 65% were interested in sharing their opinions and thoughts and/or becoming involved with future planning of health promotion activities for people with disabilities.
These summaries were made from the findings:
- Respondents wanted more information from their health care providers about treatments for specific conditions and about prevention and general health.
- Respondents were interested in a wide array of health promotion activities and supports, including help with stress reduction, cooking classes, help finding employment, and resource information.
- Lack of money was the most commonly cited barrier to taking care of one’s health.
- The majority of respondents were satisfied with the information and treatment they are currently receiving, but would like to get even more from their doctors, social services, and case managers.
- Respondents reported being eager to participate in future planning activities and to get together with other people to participate in health promotion activities.
Phase 4, Strategic Issues:
The results of the survey were incorporated into the health promotion summit, the product of the second subcommittee. The summit focused on the notion that people with disabilities constitute a community, and that public health professionals should relate to them as a community.
Possible strategic issues:
- How can people with disabilities become more involved in the health promotion of their own community?
- How can those people working in public health, health providers, and people with disabilities work together to develop health promotion efforts?
- How can people with disabilities receive more information from their health care providers about prevention and general health?
- How can the lack of money be overcome as a barrier to taking care of health issues?
Phase 5, Goals/Strategies:
The committees decided on these strategies:
- Identify and survey health department clients with disabilities to support the planning and implementation of health promotion programming for this community.
- Develop a voluntary registry of people with disabilities in order to be able to provide appropriate services in the event of an emergency.
- Convene a summit for people with disabilities and providers of services for people with disabilities to establish a long-term agenda for health promotion programming.
Phase 6, Action Cycle:
The third subcommittee is working to develop a voluntary registry to alert emergency response workers to community members with disabilities. The success of this project is dependent on approaching health promotion in the disability community in the same way it approaches health promotion in other communities, by working in partnership with leaders and members of the disability community and focusing on the underlying social determinants of health.
The Multnomah County Health Department used the MAPP tool to find out what issues were being faced by those with disabilities within the community and what the community could do about the issues. They developed a vision and mission, assessed the community, identified problems and potential strategies, and created an action plan. The partnership members are currently still working on the action cycle phase of the process but have made progress in providing health services and health promotion programming for community members with disabilities.
Please see the Multnomah County Health Department for further information.
Example #2: Richland County Public Health Department
In 2007, the Richland County Public Health Department decided to engage the Richland County community in the Mobilizing Action through Partnership and Planning (MAPP) process.
Organize for Success/Partnership Development
A partnership was formed between the Richland County Public Health Department, the Communities in Action Steering Committee and staff, and many other interested and active organizations, agencies, coalitions, and individuals in Richland County. One especially important partner was the AmeriCorps*VISTA program. Much of the information collection was done by AmeriCorps*VISTA members along with volunteers from the Richland County community.
Visioning
Richland County wishes to “cultivate individual and community involvement in all aspects of our health, safety, and wellness by empowering people to capitalize on available resources to achieve our highest quality of life.” Their goal is to begin a community building process to make Richland County into the healthiest community possible, where the definition of healthy community includes social circumstances, environmental conditions, economic development, and country/cities growth policies.
Assessment (links to assessments and results following each explanation)
First, demographic and other statistical information was collected about the physical health of the Richland County residents: Community Health Assessment.
- A County Windshield Survey was also conducted. AmeriCore*VISTA members were taken on car tours of each town in Richland County guided by two residents from each town. Discussion topics included health, environment, youth, seniors, local business, housing, protection, transportation/road conditions, and safety. City of Sidney Windshield Survey.
- Several methods were used approaches were taken to learn about the broad array of issues that matter to people in the community.
- A County Telephone Survey was conducted by the University of Montana’s Bureau of Business and Economic Research, which contacted a random sampling of residents. The topics chosen by area groups for this survey included local housing, business, volunteerism, and the importance of a local school system to their community. Richland County Telephone Survey.
- To assess the views of youth, the young people of the community were given a chance to voice their opinions on what they liked and what they would change about their communities. They used a methodology called PhotoVoice. Youth were given disposable cameras and asked to take photos of the positive areas of their community and the areas that needed improvement: Richland County PhotoVoice slideshow. For more information on Photovoice.
- The views of the elderly were also assessed. Focus groups were formed to address senior citizens’ accessibility to physical activity. Seniors were asked to comment on what forms of exercise were currently available to them, what barriers existed that prevented physical activity, and what changes and programs they would like implemented in the future. Richland County Senior Focus Group.
- Written surveys were given out to Richland County residents inquiring about their views on various environmental health topics. The top concerns that surfaced from this survey were: illegal drugs and alcohol use, road safety and unsafe drivers, crime and domestic violence, oil/gas development, water and air quality, and the quality of medical facilities. Environmental Health in Richland County.
- Finally, a Local Public Health System Assessment was conducted using the Local Public Health System Performance Assessment Instrument. This instrument evaluated the performance and implementation of ten essential services that the community should do: monitor health status; diagnose and investigate health problems; inform, educate and empower people; develop policies and plans; link people to needed personal health services; assure a competent workforce; evaluate effectiveness, accessibility, and quality of services; and research for new insights and innovative solutions. These ten essential services are guidelines for the optimal performance of the public health system. Richland County Local Public Health System Assessment. For more information on the Ten Essential Services.
- In an effort to look to the future, a Forces of Change assessment was performed by members of the organization in charge of this effort, the Communities In Action Steering Committee. This was a brainstorming activity that looked at potential forces of change in the community and the potential threats and opportunities created from each change. Some examples of these factors include political or legislative changes, demographic shifts, or changes in availability of natural resources. Richland County Forces of Change Assessment.
Strategic Issues, Goals/Strategies, Action Cycle
The Richland County Health Department and its partners have not yet completed these steps. The Health Department reports, “With the list of concerns now compiled, community members must next identify strategic issues to determine which issues are the most critical for Richland County to address. Once these critical issues have been identified, community members will help to formulate goals and strategies to address these identified issues. After this is completed, the necessary steps to reach our goals can be put into motion.
Example #3: Chicago Partnership
This is an example from the National Association of County and City Health Officials (NACCHO) website.
The Chicago Partnership was created in orderto improve the Chicago Department of Public Health. The Partnership engaged many different stakeholders in its efforts, from health department workers and medical providers to religious leaders and philanthropists.
- Phase 1, Organize: First, an advisory committee with representation from the health department, the business community, the board of health, and a health policy/advocacy organization was formed. This committee was in charge of identifying stakeholders and deciding who should be included as members of the partnership. They appointed members from the public hospital, community health centers, governmental agencies with ties to public health, the religious and business communities, health advocacy organizations, philanthropy, and academia.
- Link to Chicago Partnership MAPP Phase 1 on NACCHO website
- Phase 2, Vision: To develop a vision, members were asked to describe what they thought would be important components of the ideal public health system for Chicago. They were asked to consider:
- Past public health successes in Chicago.
- Their organization's capability to contribute to public health.
- Health conditions facing Chicago residents.
- Guiding principles and assumptions adopted for the planning process.
The members' input was categorized into three areas:
- Who would the system serve.
- What would the system do?
- How would the system function?
At the next meeting, the partnership members discussed these questions and decided on their vision for local public health:
"A responsive, sustainable public health system that, through cooperative efforts, planning and policy development, a broad focus on health promotion and disease prevention, and shared leadership and accountability, is positioned to respond to current and future public health challenges, and protects and promotes the health and well-being of all Chicago communities, residents, and visitors, particularly the most disadvantaged."
During this visioning process, input by the department of public health was limited, which helped expand the role of nongovernmental partners. In the end, the process resulted in a vision that could be embraced by all partners. The group agreed to periodically review and potentially revise this vision to align it with the progress and development of the overall assessment and intervention process.
Link to Chicago Partnership MAPP Phase 2 on NACCHO website
Phase 3, Assessments:
- Community Health Status Assessment: The Chicago Partnership compiled the Chicago Health Profile, which included data pertaining to:
- Demographic and socioeconomic indicators.
- Health status indicators.
- Health perceptions and health-related behaviors.
- Social and environmental factors.
- Healthcare delivery and access to care.
- This information was collected from the U.S. Census, vital records and reportable diseases records (maintained by the Public Health Department), hospital discharge data, adult and youth behavior risk factor surveys, violent crimes records from the police department, and a recently completed broad-scale survey of Chicagoans.
- Based on these data, the staff wrote up a narrative report that was reviewed and discussed at the next Partnership meeting. Members were encouraged to voice their opinions and recommend changes. The staff then condensed the findings of the Chicago Health Profile into a seven-page summary and presented it at the September 1999 meeting.
Some important findings:
- Significant health status disparities exist by race/ethnicity and by gender.
- The city experienced a 12 percent decrease in available jobs from 1992 to 1997, with a slow growth in new jobs from 1997 to 1999.
- Mortality rates overall were declining, but hospitalizations for related conditions were up.
- Infant mortality rates continued to decline, despite no decreases in low weight births.
- Despite significant progress in recent years, incidence of most types of sexually transmitted infections had increased in the past year.
- Most Chicagoans had some source of regular medical care; most of the insured, however, were not covered for wellness services.
- At the meeting, the partnership discussed the data found in the assessment and what it meant. It was decided that the decreasing mortality rates (including infant deaths) and rise in hospitalizations, along with the lack of improvement in low birth weight, suggested that while advances were being made in medical intervention, more work was needed in the area of primary prevention.
Link to Chicago Partnership MAPP Phase 3a on NACCHO website
Community Themes and Strengths Assessment: Since much of the Chicago Partnership's focus was on the systems and policy level, it was deemed important to engage partners at the community level to develop a strengthened public health system. The partnership contracted with four existing community-based partnerships that each focused on a specific region of Chicago. These organizations already had the experience and expertise for engaging the resources and assets of their respective communities. The local partnerships each conducted a series of three community forums. The first forum set focused on providing information, and the second and third forums gathered input on strategic issues and Partnership strategies.
During the first set of forums, community members discussed their perceptions about:
- Priority health and public health issues.
- Barriers to the delivery of local public health services.
- Elements for successful community-based health improvement efforts
- .Systems-level changes needed to support local public health improvement efforts
The local community-based partnerships reported the results back to the Chicago Partnership. Forum participants identified pressing health problems, including substance use, violence, cancer, hypertension, diabetes, and asthma. Some of the identified barriers to health were poor transportation access, language or other cultural barriers, and poor healthcare coverage. Resources identified included parks, community diversity, and relationships with neighbors. The community members made suggestions for system improvements, including greater community involvement in local planning, more free or affordable housing and health care services, better communication, greater collaboration, increased police presence, increased trust within the community, greater numbers of community resource centers for information sharing, and stronger public health leadership.
These findings, consistent with the partnership's vision, were presented and discussed at the next Chicago Partnership meeting.
Link to Chicago Partnership MAPP Phase 3b on NACCHO website
- Forces of Change assessment: Members of the Partnership each completed a worksheet identifying forces and trends in public health as well as possible threats and opportunities resulting from those forces and trends. When the worksheets were analyzed, over 75 forces and trends had been identified. Partnership staff consolidated the submissions into one worksheet, without changing the writers' wordings. The input was grouped into 11 broad categories, allowing the partnership to identify which forces were concerning to the most members.
- The Chicago Partnership debated the forces and trends identified in the document, offering additions and challenging assumptions. After much deliberation, including an extra three-hour meeting scheduled just for that purpose, the forces and trends identified were consolidated into eight main categories:
- Lack of public health constituency Shifting funding streams and focus.
- Governmental role in public health.
- Health status disparities.
- Healthcare system changes.
- Emerging public health issues.The aging population.Economic development
Once the group had reached consensus on the content and organization of the worksheet document, a narrative was drafted to reflect the details of the discussion process. When the narrative had been reviewed and revised, it was included in the final public health systems improvement plan.
Link to Chicago Partnership MAPP Phase 3c on NACCHO website
- Local Public Health System Assessment: A committee was formed to assess the extent to which Chicago organizations contributed to public health, specifically by providing the Ten Essential Public Health Services (CDC). and see Ten Essential Public Health Services. The Systems Assessment Committee considered public health and related government agencies, community health centers, hospitals, policy and advocacy organizations, coalitions, educational institutions, social service providers, philanthropy organizations, businesses, and religious communities, and made a list of specific providers from each of these areas.
- The next step was to formulate a survey to determine which of the 10 essential services the agencies were providing and to collect examples of the ways they delivered those services. This survey was distributed to more than 150 agencies. Forty-eight responses were received. Partnership staff organized the responses by arena and service provided. Then it was noted how many and which of the 10 essential services were provided in which areas of the city.
- It was found that almost all of the essential services were provided in almost all areas of the city. This led to the conclusion that while Chicago has many resources, the issue may be how those resources are being used. Furthermore, some public health services were being provided deliberately and others were being provided incidentally. These incidentally provided services would be improved by being better incorporated into the systemas this would strengthen the direction of their efforts and make them more accessible to the community.
- The committee members agreed that a more refined analytic framework would be needed to better understand the contributions being made to the development of the public health system, but for the time being, the information from the surveys would be useful in characterizing the existing system.
In addition to this survey, an extensive review was conducted of public health mandates in the City Municipal Code.
The review showed that the municipal code played three roles:
- Laid out the administrative structure for governmental public health.
- Empowered the Department of Public Health and its board to establish standards for public health protection.
- Authorized the department to actively enforce the rules and regulations designed to assure those standards
These mandates were then compared with and incorporated into the essential public health services. Most fell under diagnosis and investigation of health problems, enforcement of laws and regulations, and policy and plan development.
The third and final component of the public health system assessment involved mapping the geographic locations of existing community-based health improvement partnerships onto a map of Chicago. This revealed that 16 of Chicago's 77 formally designated community areas are served by seven existing partnerships. The other 61 community areas are not served.
Link to Chicago Partnership MAPP Phase 3d on NACCHO website
Phase 4, Identifying Strategic Issues: The Chicago Partnership needed to come up with a list of possible strategic issues to achieve the vision for public health in Chicago. First, the partnership reminded members of five key points that had surfaced from the work completed so far that should be kept in mind for the strategizing portion:
- Vision for Chicago's Public Health System.
- Health Profile.
- Community Forums.
- Analysis of Trends and Forces.
- Public Health System Assessment
Members were asked to consider the findings individually and discuss them in groups in an effort to identify the big and reoccurring issues. Six possible strategic issues were considered and critiqued. Each of the six issues were debated and questioned as to how well it fit with the partnership's vision and captured the findings of the assessments that had been conducted.
Some major changes and new wordings were adopted to better link the strategies to the vision and assessment findings, and these final strategic issues were adopted:
- How can governmental public health agencies demonstrate more effective leadership in areas of policy development, assessment, and assurance?
- How can the Partnership strengthen coordination among public health partners?
- How can Chicago's public health community and its partners eliminate racial/ethnic, gender, and social class disparities in health status?
- How can the public health community ensure that the general public has access to personal healthcare services?
- How can the partnership foster the development of sustainable community-based partnerships to increase the community's voice in systems planning, program development, policy, and advocacy
- How can the public health community most effectively:
- Foster the sharing of data and other information between agencies,
- Group information and resources in the most useful manner, and
- Disseminate information to the public and other users?
Link to Chicago Partnership MAPP Phase 4 on NACCHO website
Phase 5, Goals/Strategies: This involved developing broad areas of action to address the identified strategic issues. The partnership brainstormed and identified strategies with the PEARL criteria that would address the identified strategic issues. (See below for more information about the PEARL criteria.)
Each member was given six blank index cards and asked to write down what they viewed as the most important strategies. Then, using a round-robin approach, members took turns reading their priority strategies and staff then taped the cards to the wall. During this process, members were allowed only to raise issues of clarification.
Once all of the suggested strategies had been placed on the wall, members discussed, consolidated, and then organized the strategies into logical clusters. When the two groups had each completed this exercise, the larger partnership reconvened and considered all of the strategies together. At this point, further consolidation occurred.
Throughout the strategy development process, members were asked to consider their proposed strategies against the following set of PEARL criteria:
- Propriety: Does the strategy address the issues identified? Is it technically workable?
- Economical: Is the strategy cost-effective? Does it make financial sense?
- Acceptability: Is the strategy acceptable to the community and other stakeholders?
- Resources: Are there resources to implement the strategy?
- Legality/Legitimacy: Does the group have the legal authority to implement the strategy? Is it a legitimate function of the proposed implementers and consistent with their mission?
At the meeting's conclusion, the partnership had identified a set of 20 strategies and organized them into the following seven action areas:
- Creating the public health system through partnership development.
- Setting Chicago's public health policy agenda.
- Building community capacity and constituency.
- Strengthening the public health workforce.
- Strengthening the system through information.
- Advancing the public health agenda through research.
- Getting the word out: marketing public health messages
The strategies in these areas served as the basis for the partnership's priority-setting and more specific action-planning activities.
Link to Chicago Partnership Phase 5 on NACCHO website
Phase 6, Action Cycle: Out of the 20 total strategies developed, two fundamental strategies were chosen to focus on first:
1) the development of a network of community-based coalitions, and 2) the creation of a coordinated citywide policy agenda for public health in Chicago.
The strategy of developing a network of community-based coalitions was chosen because of Chicago’s large and diverse nature. The Chicago Partnership could not possibly represent all of the city's communities, but the partnership believed that additional community participation was essential. To ensure that the need for community participation was met, an organized structure was needed. The partnership submitted a funding request to the Kellogg Foundation to initiate work on this strategy.
The second strategy – to develop a coordinated citywide public policy agenda -- was chosen because policy was an area in which most of the partners had a stake and the partnership already had resources needed to take action.
The Committee on Community Partnerships and the Policy Committee were created to address these strategies. At each committee's first meeting, members talked about additional organizations and/or individuals who would be important to involve in the effort.
For example, citywide and other large agencies with resources in multiple communities (such as the city's workforce development office and the community health ministry) were invited to serve on the Committee on Community Partnerships. Policy representatives from a range of agencies, including labor and adolescent health, were invited to serve on the Policy Committee. With membership expanded, the efforts of each committee focused on the development of more specific action plans, including committee member assignments and timelines.
A third committee, the Implementation Committee, comprised solely of formal partnership members, was convened to consider the feasibility of the 18 remaining strategies to be addressed. At the initial meetings, members rated the strategies on levels of need and feasibility and are in the process of making recommendations to the partnership as to where effort should be placed next.
Two additional committees would be formed by the end of the year. A Coordinating Committee would consider the operations of the partnership, including membership issues and the work of the various committees. A working group would also be formed to promote the partnership and its strategic plan.
The project planner at the Department of Public Health staffs the committees. Additional in-kind staff support is provided to the Policy Committee by the department's director of policy and legislative affairs.
Evaluation activities consisted of monitoring implementation of strategies. It was anticipated that evaluation plans would need to be developed separately as each strategy was addressed. However, the Chicago Partnership has not yet reported on the methods of evaluation they have used so far.
Link to Chicago Partnership MAPP Phase 6 on NACCHO website
Through a comprehensive MAPP Process, the Chicago Partnership was able to engage diverse community stakeholders in identifying community needs, creating a partnership, prioritizing issues to address, creating action plans, taking action, and evaluating their efforts.
For a thorough report of the work done by the Chicago Partnership, please see the pdf file: Chicago Plan for Public Health System Improvement 2006-2011 (Aug. 2006)
Tool #1: Tip Sheet—The Visioning Process
This tool is an example of the tools available on the NACCHO/MAPP website.
The following is a useful method for structuring community visioning. A similar approach can be used with a committee visioning process. The process details the development of a shared vision, as well as common values.
Preparations
Select a site that can readily accommodate 40-100 persons. Set up the room with participants seated in a circle. This encourages participation by all persons in attendance. Invitations should be clear and be sent in a timely manner to avoid confusion. Care should be taken to ensure that the time and place facilitate broad attendance. Carefully consider the venue and schedule and how it will accommodate participants with differing schedules or lifestyles.
Key individuals to support the visioning process include: 1) a facilitator who can effectively manage the large group process in a neutral way (see Tip Sheet — Facilitation within the MAPP Process); and 2) one or two note-takers to record the discussion. Recording is a task that should not be assigned or undertaken lightly. The recorder(s) should be skillful at organizing and synthesizing material and should strive to capture the exact wording — to the extent possible — used by participants. You may also want to designate some individuals to act as observers; these individuals can assure everything is on track and can provide suggestions to the facilitator if needed.
Welcome/Introduction
Set the tone of the visioning session by greeting participants when they arrive, arranging for clear signage, and offering light refreshments. Helping people feel comfortable upon arrival and communicating to participants the importance of their presence can go a long way toward building trust and commitment.
The facilitator or a MAPP Committee representative should open the meeting with an explanation of MAPP and why a visioning process is important. The list of benefits cited in the MAPP Visioning guidance can be a useful reference. Be sure to emphasize that the goal is to create a shared vision for the community and not a vision for any one organization.
Building Rapport/Icebreaker
After the introduction, a small amount of time should be dedicated to building rapport among the participants. Everyone in the room should be given a chance to introduce themselves. Consider having participants engage in icebreaker exercises; these can help to ease tension in the room and get everyone comfortable. Icebreaker activities might include the following.
- As people introduce themselves, ask them to state their expectation for the meeting. They can also be asked to state a "fun fact" about themselves, to help ease the tension.
- Since all of the participants may not know each other well, participants can be divided into groups of 2-4 to "chat" for 10 minutes, then return to the larger group to introduce each other.
Vision Brainstorming and Development
Once participants are comfortable with the topic and with each other, the dialogue should be moved toward discussing a vision for the community. Questions should be formulated beforehand to drive this discussion.
Useful visioning questions might include:
- What does a healthy Anywhere County mean to you?
- What are important characteristics of a healthy community for all who live, work, and play here? and
- How do you envision the local public health system in the next five or ten years?
Responses to these questions should focus on broad concepts; not details. Responses can be collected through brainstorming activities or by writing ideas down and then sharing them. The group can be organized to gather information through small group processes, or the questions can be addressed by the group as a whole.
Possible approaches for brainstorming include:
- Ask each person to write down what they believe about healthy communities. Then ask participants to pair up, share their thoughts, and develop a joint list. Participants should clarify each other's ideas and discuss any conflicting information. Then each pair can join another pair and repeat the process. The process is repeated until the entire group is back together.
- Ask each participant to write down their ideas. Then, in round-robin fashion, go around the room, posting all ideas on a flip chart (this can be shortened by limiting the number of ideas offered). After all ideas are shared, the group discusses and organizes them.
- Distribute small pieces of paper and ask participants to write down their ideas — one idea on each piece of paper. Then have participants tape their ideas to a wall. A small group then moves the ideas around until common ideas are grouped together. List and discuss the common ideas.
Values Brainstorming and Development
Once many ideas have been gathered and there is consensus about the concepts contained in a community vision, the group can move on to identifying common values (this may be done in the second part of the first session, or during a second session). It is strongly recommended that the actual drafting of the vision statement be done by a small task force or staff group.
The values brainstorming process should be similar and can use the same brainstorming techniques.
Questions to elicit thoughts on common values include:
- Taking into consideration the shared vision that has been developed, what are the key behaviors that will be required of the local public health system partners, the community, and others in the next five to ten years to achieve the vision?
- What type of working environment or climate is necessary to support participants in performing the above behaviors and in achieving the vision?
Closing the Session /Check-out
At the end of each session, the facilitator should ensure that everyone is comfortable with the results of the session. Give participants a chance to make final comments or express concerns about the results or the process. This helps to ensure that participants leave the session without feeling frustrated and may also improve future group processes. Close the meeting with a discussion of next steps. Discuss the need for and timing of future meetings. Make sure everyone understands the next steps and how follow-up will occur.
Follow-up to the Session
After the visioning session, a small group should compile the results and draft statements for the shared vision and common values. The draft statements should be presented to the visioning group participants (through a follow-up session or through other mechanisms). Participants should be given a chance to make minor adjustments.
Once everyone is satisfied with the vision and values, each should be formally adopted. The statements should then be kept alive through the remainder of the MAPP process. All MAPP materials, such as brochures, leaflets, and reports, should include the statements. References to vision and values statements should be made at the beginning of each MAPP committee meeting.
return to top
Tool # 2: Matrix of Organized Participation and Roles within Each Phase of MAPP
```html

MAP-IT (Mobilize, Assess, Plan, Implement, Track) is a step-by-step method for creating healthy communities. MAP-IT was used as an implementation framework for Healthy People 2020 and continues to provide a practical structure for planning and evaluating community health efforts. Using MAP-IT can help public health professionals and community changemakers develop a plan tailored to a community's needs and assets. This section describes the MAP-IT framework and provides a basis for using it in plans to improve community health.
What is MAP-IT?
MAP-IT (Mobilize, Assess, Plan, Implement, Track) is a framework that can be used to plan and evaluate public health interventions in a community. Both experienced and newer public health professionals and community partners can use the steps in MAP-IT to help create healthier communities. This process involves time, effort, and a series of steps to “map out” the path toward desired change in a community. Keep in mind that there is no single “right” way to follow this approach, and some steps may need to be revisited more than once. Using MAP-IT, a coalition can develop a structured plan tailored to a specific community's needs, priorities, and assets.
- Mobilize individuals and organizations that care about the health of your community into a coalition.
- Assess the areas of greatest need in your community, as well as the resources and other strengths that you can tap into to address those areas.
- Plan your approach: start with a vision of where you want to be as a community; then add strategies and action steps to help you achieve that vision.
- Implement your plan using concrete action steps that can be monitored and will make a difference.
- Track your progress over time.

Why Use the MAP-IT approach?
- It involves stakeholders and community members, helping create a broadly supported and community-owned effort.
- It assesses assets as well as needs and looks for ways to use them.
- Assessment helps the effort begin with community data, knowledge, experiences, and existing resources rather than assumptions about what is needed.
- It produces a comprehensive and specific plan, with reasonable timelines, assigned responsibility, clear objectives, and well-defined action steps related to an overall strategy.
- It incorporates evaluation from the beginning, allowing adjustments when necessary.
How do you use the MAP-IT approach?
Step 1: Mobilize
The first step in the MAP-IT process is to mobilize key individuals and organizations into a coalition. Look for partners who have a stake in creating healthy communities and who will contribute to the process. Aim for broad representation.
Most communities already have health departments and other government agencies involved in public health services. Many communities also have coalitions of individuals and organizations that have come together to address specific issues, such as neighborhood safety. These groups may represent different interests, experiences, and resources related to issues that are important to the health of the entire community. A coalition will often work with the health department and other health organizations in the community. However, it can also help mobilize a wider range of community resources to address health issues.
It is typically easier to engage potential coalition members around issues that are already of special concern to the community. Successful community coalitions have been built around issues such as:
- Substance use
- HIV/AIDS
- Pregnancies among adolescents
- Maternal and child health
- Environmental health
- Domestic violence
- Neighborhood crime and safety
Once coalition members have been identified, roles for partners should be defined and responsibilities assigned. This will help keep partners invested in the coalition. Partners can help facilitate community input through meetings, events, or advisory groups. They can also develop and present education and training programs, lead fundraising and policy initiatives, and provide technical assistance in planning or evaluation. At this stage, plan to identify:
- The vision and mission of the coalition.
- The reason for bringing people together.
- The people and perspectives that should be represented.
- Potential partners in the community, such as organizations and businesses.
One of the biggest challenges in creating a healthy community coalition is sustaining members' involvement in the process. This challenge can be addressed in part by agreeing as early as possible on a vision for the community.
Creating a vision: The vision should originate from the community's most important needs, values, strengths, and goals. It should describe the coalition's ideal direction for the community and reflect the goals of coalition members and community participants. Creating a vision early on can strengthen members' commitment to the long-term process and allow the group to enter the next stage with a shared sense of purpose.
Organizing a Coalition (PDF): Before you begin contacting potential partners, it is important to know exactly what you are asking of them. Here are a few questions to consider beforehand.
- How many members do you want, and what types of skills, knowledge, or experience should be represented?
- What is the expected time commitment? (How many hours per month for how long?)
- Will members be expected to represent their agencies, communities, or constituencies?
- Which populations and perspectives should be represented?
- Where, when, and how often will you meet?
- Will the meetings be open or closed?
- Who will be the coalition leader(s)? Will they be appointed or elected?
- Who are your strongest allies?
- How will you recognize members' contributions and efforts?
Brainstorm Potential Partners: Who are likely stakeholders? You'll want as broad a group as possible, with representation from people and sectors throughout the community that have an interest either in the issue itself or in building a healthy community. It's generally an advantage to involve many different groups and community sectors. The more meaningful participation you have in planning for and addressing the issue, the more knowledge and ideas can be brought to the process, and the more community support the effort may have.
Some obvious possibilities include:
- People directly affected by the issue.
- Health and human service organizations that work directly with the issue or serve people affected by it.
- People whose jobs or lives may be affected by an effort directed at the issue – law enforcement officers or teachers, for example, in the case of an initiative addressing youth violence.
- The business community or specific businesses that have an interest.
- Local media and communication partners.
Historical Mobilization Example:
Minnesota formed the Minnesota Health Improvement Partnership, a group of individuals representing a broad range of public and private organizations, including local health departments. The group was charged with developing Healthy Minnesotans: Public Health Improvement Goals for 2004. Although this example reflects an earlier Healthy People era, it illustrates the MAP-IT principle of bringing different sectors together around shared community health goals.
Step 2: Assess
The next step in the MAP-IT approach is to assess both community needs and assets (resources). This helps identify needs based on available data and community knowledge rather than assumptions and provides a sense of what can realistically be done with the resources and strengths available. Plan to address the questions of who is affected and how, what resources are available, and what additional resources may be needed. When coalition members work together to set priorities and allocate resources for those priorities, they are more likely to remain involved in the process and work toward measurable results.
The coalition should set priorities by identifying what community members and key stakeholders see as the most important issues. Consider feasibility, effectiveness, equity, and measurability in determining priorities. The current Healthy People 2030 objectives can provide a useful national reference point across a wide range of health, well-being, and community conditions. Setting priorities should be a collaborative process in which coalition members and community participants determine which issues require immediate attention and which can be addressed later.
This may be a good time to discuss the determinants of health. Health and quality of life are influenced by conditions at the individual, community, institutional, and societal levels. Social determinants of health are one important part of that picture.
Healthy People 2030 groups social determinants of health into five broad domains:
Economic Stability
Education Access and Quality
Health Care Access and Quality
Neighborhood and Built Environment
Social and Community ContextWithin these domains are conditions such as employment and income, education, access to health care, housing, transportation, access to nutritious food, discrimination, violence, environmental conditions, social support, and civic participation. These conditions can influence opportunities for health and well-being in a community.
Health outcomes are rarely shaped by only one factor. Effective community health efforts often consider several interacting conditions rather than focusing only on individual behavior or a single program.
Which of these conditions are important to the health of your community, and in what ways? Are there areas in which your coalition can help create change?
Whenever possible, gather and evaluate available information about major health issues in the community. When needed data are not available, the coalition may need to begin collecting local or state data to develop a more complete picture of community needs and assets. Data gathered during the assessment phase can serve as baseline data – information collected before a new program or intervention begins. Baseline data make it possible to compare later findings and track whether conditions are changing over time. Documentation of progress can also help the coalition explain its work and make decisions about what should happen next.
A number of data sources may be available. The U.S. Census Bureau provides population, housing, social, and economic information through sources such as the decennial census and the American Community Survey, with data available at different geographic levels. States, counties, municipalities, tribal governments, and local agencies may also collect information about health and community conditions. Federal agencies such as the Centers for Disease Control and Prevention, the National Institutes of Health, and the U.S. Department of Health and Human Services provide additional data. Local hospitals, human service organizations, school systems, public safety agencies, universities, and other institutions may also have useful information and may be willing to share it for assessment purposes.
Evaluators, researchers, data specialists, or other knowledgeable partners from a university, health department, government agency, or community organization may be able to help with data analysis and measurement.
While it can be helpful to have an external evaluator, not all communities have the resources to hire a consultant or work with a university or agency evaluator. A coalition may also conduct parts or all of its own evaluation, provided it has appropriate methods and support.
Resources: Once a community's needs have been assessed, develop a list of strengths, assets, and resources within the community. Resources go beyond money – every community has nonfinancial resources that can contribute to addressing areas of concern, including:
- Technology
- Communication networks and channels
- Infrastructure, such as food retailers, roads, parks, public transportation, housing, and meeting or office space
- Professional and community expertise
- Data
- Community-based organizations, such as local businesses, service organizations, faith communities, and community groups and leaders
- Community institutions – schools, colleges and universities, libraries, arts and cultural organizations, and sports and recreation facilities
The value of working with strong community-based organizations should not be underestimated. These groups can be vital to the success of community efforts because of their knowledge of community conditions, relationships, strengths, and priorities.
Historical Assessment Example:
Kansas used its Healthy Kansas 2000 Steering Committee to identify priority health issues by examining health data, seeking expert opinions, inviting public comments, and conducting an opinion survey of residents. Kansas used a consensus process to narrow its objectives to seven priority health areas and four risk factors. The health areas included alcohol and other substance use disorders, cancer, heart disease, HIV and other sexually transmitted infections (STIs), infectious diseases and immunizations, injuries and violence, and maternal and infant health. The focal risk factors were lack of access to preventive care, tobacco use, poor nutrition, and lack of physical activity. Although the specific goals belonged to an earlier planning period, the example illustrates the MAP-IT principle of using multiple sources of information and community input to establish priorities.
Step 3: Plan
Once priorities have been set and data have been gathered, an action plan is needed with concrete steps and deadlines. For helpful tips, visit Toolkit 4: Developing a Framework or Model of Change. In the planning phase, use the vision as a guide and include clear objectives for achieving it. Objectives should be specific to each issue or community and should describe what is expected to change, what is needed to achieve that change, and how progress will be measured. A plan of action should include:
- Action steps.
- Assignment of responsibility.
- Information collection.
- A feasible timeline.
When setting objectives, remember to state exactly what is to be achieved: what is expected to change, by how much, and by when. The objectives should be challenging yet realistic. Include a target when appropriate – the desired amount of change within a particular period of time, often reflected by a number, rate, or percentage. Healthy People establishes national objectives over a ten-year period, but shorter time frames may be more appropriate for local coalition goals.
Remember that every target needs a baseline – where you are now, or the first data point against which future progress will be compared. Identify strategies for reaching each objective. Action steps may be developed independently or as part of an overall strategy. Start by examining promising, evidence-based, or evidence-informed approaches and interventions, and engage coalition members and community participants in developing strategies. Strategies can serve as umbrellas under which different coalition members contribute to the same goal. Remember to include ongoing data collection and monitoring in the action plan.
The action plan also needs to indicate who will be responsible for overseeing and following up on specific action steps. Assigning specific people or organizations to clearly defined and agreed-upon roles can help move the plan forward. It can also help coalition members understand how their work contributes to the overall vision for the community.
Finally, be realistic when planning the timeline. Consider how much time will be necessary to complete each part of the plan, as well as the schedules and capacity of coalition members and community partners.
Historical Planning Example:
As part of efforts related to year 2000 health objectives, the Rhode Island Department of Health initiated the Worksite Wellness Council of Rhode Island. The effort focused on increasing health promotion and disease prevention activities in workplaces, where many adults spent a substantial part of their day. The State Wellness Council entered into an agreement with the Wellness Council of America (WELCOA) as part of its effort to increase participation in worksite wellness activities. Although the specific targets reflected an earlier planning period, the example illustrates how MAP-IT planning can connect broad goals with defined strategies, partnerships, and measurable targets.
Step 4: Implement
Once the action plan is established, coalition members can begin implementing the strategies and action steps identified in the plan. Coalition members should work on the tasks assigned to them according to the agreed-upon timeline. Monitoring, or routine tracking of implementation, is important during this stage. For example, if the action plan calls for weekly reports on a particular topic, monitoring can show whether those reports are occurring as planned.
Remember that monitoring is most effective when it is planned before an initiative begins so that it can take place throughout the life of the effort. To monitor progress, identify appropriate indicators – the measures you'll use to examine process, performance, and outcomes. These will show you (indicate) whether you're doing what you planned and how well it is working. Paying attention to the indicators can also help you understand why something may not be working as expected and provide information for making improvements.
Consider identifying a point of contact or coordinating group to help manage the process and ensure that agreed-upon tasks move forward. At the same time, share responsibilities across coalition members. Periodically bring in new partners when additional perspectives or skills are needed, and check in regularly with existing partners to hear suggestions and concerns. Communication among partners and staff involved in the effort is one of the keys to effective implementation.
And don't neglect the value of communication about your effort within the community. Get the word out by developing a communication plan, and use community events, meetings, presentations, and other appropriate channels to share progress and recognize accomplishments and partners.
Be aware that implementing action plans to improve community health may take longer than expected. Patience, communication, and continued attention to the community's goals can help coalition members and partners remain engaged throughout the process.
Historical Implementation Example:
North Carolina established the Office of Healthy Carolinians to help support its Healthy People-related community health improvement work. Staff provided counties with support and training, including coalition-building assistance, and participating counties conducted assessments and implemented action plans. This example reflects an earlier state initiative, but it illustrates the MAP-IT principle of supporting local groups as they move from assessment and planning into action.
Step 5: Track
In the last phase of the MAP-IT process, plan regular evaluations to measure and track progress over time. Tracking includes analyzing information and reporting on progress. Note the extent to which the plan was followed, changes that were made during implementation, and whether objectives and goals were reached.
Evaluation and tracking are important to the long-term success of the coalition's efforts. Consider partnering with a university, public health agency, research organization, community data partner, or state health statistics program if additional help with data collection or analysis is needed. Some things to consider when evaluating data over time include:
- Data Quality: Check for consistency and standardization in data collection, analysis, and question wording.
- Limitations of Self-Reported Data: When relying on self-reported information, such as physical activity, income, or other behaviors and conditions, consider the possibility of recall, response, and other forms of self-report bias.
- Data Validity and Reliability: Changes in survey questions, definitions, or data collection systems may affect comparisons over time. Seek statistical or evaluation expertise when needed.
- Data Availability: Data may not be collected or released on the same schedule for every indicator.
Remember to share progress and lessons learned with the community. When the data show meaningful progress, communicate it through appropriate community channels. Local media and other communication partners can help share results, while community meetings, websites, newsletters, and other methods can keep participants and residents informed throughout the effort.
Historical Tracking Example:
For its 1996 and 1999 updates to New Jersey's year 2000 objectives, state statistical and program staff assessed progress and analyzed trends. Based on those analyses, staff categorized each objective and subobjective as “likely to be achieved,” “unlikely to be achieved,” or “uncertain.” Although the objectives themselves are historical, the example illustrates an important MAP-IT principle: regularly examine progress and use the findings to understand whether goals are on track.
In Summary
MAP-IT – Mobilize, Assess, Plan, Implement, and Track – provides a practical structure for developing and evaluating community health initiatives. It was used as an implementation framework for Healthy People 2020 and continues to be used as a community planning approach. The five steps encourage communities to build broad partnerships, understand needs and assets, create a specific plan, put that plan into action, and continually examine progress.
Healthy People 2030 is now the current national Healthy People initiative. Its objectives, health-equity goals, and increased emphasis on social determinants of health can serve as current reference points for communities using MAP-IT, while the MAP-IT process itself remains the same: mobilize people and organizations, assess community needs and strengths, plan collaboratively, implement concrete actions, and track what happens over time.
```
Resources
Online Resources
Brainstorm: Community Assets (PDF): A checklist to assist you in determining community assets that are available.
Coalition Self-Assessment (PDF): An anonymous coalition self-assessment that allows members to rate the group and its staff, leaders, and members on a variety of factors important to the effective functioning of a coalition
Communication Plan Template (PDF): A template to assist you in creating an effective communication plan for your effort.
Defining Terms (PDF): Provides clear definitions of many of the terms – vision, baseline data, etc. – you might use in discussing your plan.
Healthy People 2020, a joint effort between the U.S. Department of Health and Human Services, along with representatives from the Departments of Agriculture, Education, Housing and Urban Development, Justice, Interior, and Veterans’ Affairs, as well as the Environmental Protection Agency, works to set objectives for the health of the nation. They provide the MAP-IT framework for Implementation, as well as many other useful pages.
Measuring Progress (PDF): Helpful formulas for quantitatively measuring your progress.
Organizing a Coalition (PDF): Provides a list of important questions to consider before organizing a coalition, in a printable format that allows you to fill out answers to the questions and/or distribute them to a planning group.
Potential Health Measures (PDF): Possible indicators to consider measuring to track your initiative's progress.
Prioritizing Issues (PDF): An exercise that will assist you in determining which issues it is most important for your effort to undertake.
Setting Targets for Objectives (PDF): A page providing national and state standards and other helpful guidelines to assist you in setting reasonable goals for your initiative.
What is MAP-IT?
___MAP-IT is a framework that can be used to plan and evaluate public health interventions in a community.
___MAP-IT has five steps:
- Mobilize individuals and organizations that care about the health of your community into a coalition.
- Assess the areas of greatest need in your community, as well as the resources and other strengths that you can tap into to address those areas.
- Plan your approach: start with a vision of where you want to be as a community; then add strategies and action steps to help you achieve that vision.
- Implement your plan using concrete action steps that can be monitored and will make a difference.
- Track your progress over time.
Why use MAP-IT?
___It involves all stakeholders, making for a widely-supported and community-owned effort.
___It assesses assets as well as needs, and looks for ways to use them.
___Assessment means that the effort will start from the reality of the community, rather than from some preconceived idea of what’s necessary or what resources are available.
___It produces a comprehensive and specific plan, with reasonable timelines, assigned responsibility, clear objectives, and well-defined action steps related to an overall strategy.
___It incorporates evaluation from the beginning, allowing adjustment when necessary.
How do you use MAP-IT?
Mobilize
___Consider what you want coalition partners to do and how the coalition might be organized.
___Brainstorm potential partners.
___Recruit coalition members.
___Create a vision for the coalition.
Assess
___Collect locally available data about resources and needs.
___Collect information from public and archival sources.
___Determine what issues are most important to community residents and key stakeholders.
___Identify community assets, including people, skills, capacity and capacity building, space, organizations and institutions, knowledge, funds, etc.
___Based on data and community priorities, prioritize needs by consensus.
___Establish baseline data
Plan
___Choose the issue(s) the initiative will work on.
___Set clear objectives.
___For each objective, develop an action plan that includes:
- A strategy and tactics
- A timeline with reasonable time targets for each phase of the strategy
- The responsible parties and their roles and tasks
- Indicators and/or other measures of progress
Implement
___Identify an individual or organization to serve as the coordinating point for the implementation of the initiative.
___Make sure that everyone involved knows what’s going on and what everyone else is doing.
___Use the media and other channels to inform the community about the work of the initiative.
Track
___Start your evaluation and monitoring at the very beginning of your initiative, if possible.
___Set up a system for gathering data.
___Consider:
- Data Quality
- Limitations of self-reported data
- Data validity and reliability
- Data availability
___Organize and analyze data on a regular basis, so that you can make appropriate adjustments in your work as time goes on.
___Share progress and successes with the community.
Example 1: MAP-IT in Action: A Local School Board Addresses Underage Drinking
Mobilize
Mrs. King, the head of the school board, has been answering phone calls nonstop for the past 2 days. Parents of high school students have been calling to ask what the school board is going to do about a number of underage drinking incidents at school events. The incidents were recently written up in the local paper. Mrs. King calls the other school board members, and they all agree to hold an emergency meeting.
Before the meeting, Mrs. King contacts school board members in surrounding towns to find out how they have addressed underage drinking in their schools.
After a long, sometimes heated discussion, the school board agrees to add a unit on alcohol abuse to the school’s curriculum. They decide that Mrs. King and Mr. Brown, another school board member, will lead the process of selecting, implementing, and evaluating a new unit on alcohol use.
Assess
Mrs. King and Mr. Brown decide that first they need to gather local, county, and State data to better understand the scope of the problem. They look at the Healthy People 2020 website and find the Substance Abuse topic area objective SA-13.1 Reduce the proportion of adolescents reporting use of alcohol or any illicit drugs during the past 30 days. The national measure for that objective comes from the National Household Survey on Drug Abuse (NHSDA). The national data stated that 18.3 percent of adolescents ages 12 to 17 reported use of alcohol or illicit drug in the past 30 days in 2008. The national goal is to reduce that number to 16.5 percent. Mrs. King and Mr. Brown are able to review the NHSDA data for their State and find that the State’s baseline is 15 percent.. It is clear to them that underage drinking is a public health priority.
Mrs. King and Mr. Brown also decide that the school board should hold meetings with students, parents, police, and local business owners to determine the causes of underage alcohol use, especially binge drinking. From these meetings, they find that peer pressure, easy access to alcohol, and perceived lack of consequences are reported by each group. After gathering this information, the school board requests curricula for review that address the causes of underage alcohol use. The school board makes a point to only request curricula that are evidence and science based.
Plan
Mrs. King and Mr. Brown present the school board with 3 curricula that address the causes of alcohol abuse in their community. The school board discusses the pros and cons of each and selects one that best meets their learning objectives as well as time and budget requirements. They pick 2 teachers who are well liked by the students and certified in health education to teach the course. Working with the teachers and administrators, the school board finds time in the school schedule for the course. Mrs. King and Mr. Brown work with another school board member with evaluation experience to create an evaluation plan. They decide that a pre- and post-test should be given to students. The evaluations will be collected and entered by a teacher’s aide familiar with data entry software. The same school board member who created the evaluation plan will analyze the data.
Implement
The school board sends the 2 teachers to training on the new curriculum, and they start teaching the course when the new semester begins. A volunteer student advisory group is formed to give the teachers additional feedback on the curriculum. The group meets periodically during the semester to discuss ways to make the course more relevant to their peers. The teachers give out a pre-test on the first day of class and a post-test on the last day of the curriculum.
Track
Mrs. King and Mr. Brown collect attendance records for the course, review the student evaluation data, and monitor local police reports for alcohol-related incidents. The first group of students to complete the course reports binge drinking less often on their post-test.
They also collect informal data, such as teachers’ perceptions of students’ attitudes toward alcohol use and students’ requests for more alcohol-free school-sponsored events.
Mrs. King and Mr. Brown contact the director of the State Bureau of Substance Abuse to inform her of the community’s efforts. The State health official agrees to stay in touch and to alert them to possible funding opportunities in the future. They also brainstorm other potential funding sources, such as fundraising and partnering with local businesses.
The entire school board knows that it will be a challenge to keep momentum for this program going, especially if the issue is not in the news and budgets are cut. They hope that because students, parents, and other community members were involved in the assessment process, they will remain committed to offering alcohol abuse prevention education at the high school.
Example 2: MAP-IT in Action: Employees Organize to Improve Workplace Wellness
Mobilize
Linda recently had a mild heart attack and was out of work for 3 months. She returns to work and discusses her experience with a few coworkers. They are all surprised to learn that heart disease is the leading cause of death in both men and women. Linda shares information with them about the simple changes she’s making to help prevent another heart attack, such as going for walks during lunch and using less salt when she cooks.
Linda and her coworkers believe that other company employees need to know about their risk of heart disease and how to prevent it. They contact the company’s human resources (HR) department for a meeting to talk about ways to share health information with other employees. At the meeting, they all decide to form a workplace wellness committee, which will look into programs for improving employees’ well-being.
Assess
The workplace wellness committee first conducts an environmental scan to see what information exists and what, if any, wellness programs are available to employees. They find a few prepackaged programs from their health insurance company, but they require someone at their workplace to manage them. The group then meets and reviews data on sick days and short-term disability leave. They decide that they need more company-specific information on why employees are missing work and what types of wellness programs would help them.
They create an anonymous, brief online survey and send it out to the entire company. Out of 175 employees, they receive over 80 responses. Seventy-five percent of employees respond that they exercise sometimes or never. The main reason they stay home is because they (or their children) have a cold or flu. Nearly all of the employees selected “stress” as the top health issue they want the committee to address. With this and other information the committee receives from the survey, they are able to prioritize the top 3 issues for the program to address: exercise, cold and flu prevention, and stress.
Plan
Although Linda and her coworkers wanted to focus on heart disease, they come to the agreement that the committee should address the top issues from the survey results. The workplace wellness committee decides that they will try increasing employees’ physical activity during this quarter, which is directly linked with decreasing heart disease risk. Based on the success of that program, the workplace wellness committee will address a different priority topic each quarter.
Through their health insurance provider, they find a “small steps” program that they think would work in their company. The program encourages adults to get the recommended 30 minutes of daily physical activity by incorporating 10 minutes of movement 3 times throughout the day. They develop communication, implementation, and evaluation plans. Each plan has a specific timeline and person responsible for ensuring the completion of each activity.
To gain support from the company’s management, the committee puts together a report highlighting the Healthy People 2020 objectives related to workplace wellness. They find Physical Activity topic area developmental objective 12: Increase the proportion of employed adults who have access to and participate in employer-based exercise facilities and exercise programs. The committee also finds two relevant developmental objectives from Educational and Community-Based Programs: objective 8: Increase the proportion of worksites that offer an employee health promotion program to their employees, and objective 9: Increase the proportion of employees who participate in employer-sponsored health promotion activities. Although developmental objectives do not yet have national baseline data, they do have a confirmed, nationally representative data source that the committee could use to inform their own data collection.
Management is enthusiastic about the prospect of being “ahead of the curve” in the area of workplace wellness, and the marketing department is interested in using the potential positive public relations angle to attract clients and new employees.
Implement
The workplace wellness committee implements the “small steps” program, which encourages employees to take 10-minute breaks throughout the day to do physical activity. The program encourages simple, inexpensive activities like taking the stairs instead of the elevator and starting walking clubs during the lunch break. Linda posts flyers on the elevators to encourage coworkers to use the stairs and in the stairwells to congratulate employees on their small steps. The walking clubs are led by a different workplace wellness committee member each day, and employees are reminded about the walks on their time sheets and over the announcement system.
Track
At the end of the quarter, the workplace wellness committee sends a follow-up survey to see if employees participated in lunchtime walks or report using the stairs more often. The survey also asks questions about the tone and style of the committee’s “small steps” messages in addition to the same questions about health from the first survey. This time they have more than 100 responses. All employees report knowing about the campaign, and most have a positive opinion about it. Fifty percent of employees report going on at least 1 lunchtime walk, and 35 percent report going on 5 or more lunchtime walks. There was not a significant change in the number of employees who reported they sometime or never exercise, but the committee hopes to ask the questions each quarter to see if they can track small improvements over time.
The workplace wellness committee knows that they will need to stay focused and active for the program to continue. Even with the support of management and HR, it will take leaders from the committee to continue to advocate for corporate support of wellness programs.
Example 3: MAP-IT in Action: A County Health Department Addresses Lead Poisoning
Mobilize
Rob works for the Springfield County Health Department and was recently put in charge of their Lead Poisoning Prevention Program (LPPP). After looking at trend data, Rob sees that rates have not decreased in Springfield County as quickly as the rest of the State. He also reviews national data in Healthy People 2020 and finds that the county’s rates are higher than the national baseline and target measures. Rob contacts his State’s Healthy People Coordinator to learn more about statewide efforts to meet the environmental health objectives in Healthy People 2020. Rob then does a brief environmental scan to see what the best practices are for lead poisoning prevention and what actions similar communities have taken to address the problem.
After his initial research, Rob decides that the LPPP needs to take a new approach and brings together key stakeholders in the county to help develop a plan. He invites county representatives from housing, environmental health, and education and local public health commissioners to form the Springfield County Lead Poisoning Prevention Task Force.
Assess
Rob and the task force hold a day-long strategic planning meeting. The first half of the day is dedicated to going through data. They review data sources identified in the Environmental Health Healthy People 2020 section. There they find objective 8: Eliminate elevated blood lead levels in children. After reviewing the data for their State, they find that their county has the highest rates of childhood lead poisoning in the State; out of all children under age 6 who are tested, 5.2 percent have elevated blood lead levels. The national average is 4.4 percent, while the State average is 2.1 percent, with some counties reporting no cases of elevated blood lead levels.
While doing their assessment, the task force also finds that the county’s childhood asthma rates are 4 percent higher than the State average. They think that the lead prevention plan they develop may be able to also address some environmental causes and triggers of asthma.
The new public health commissioner from Franklin identified his city as having the most cases of elevated blood lead levels in the county, most of which are concentrated in 1 area with a number of large public housing units. Best practices in lead poisoning prevention suggest that the county health department should focus on high-rate areas, particularly public housing units and economically disadvantaged neighborhoods with houses built before 1978 (the year lead was removed from paint).
Plan
During the afternoon of the strategic planning meeting, the task force agrees that they need to address elevated blood lead levels by improving the physical environment of the housing units. They also agree to include evidence-based interventions that will reduce rates of asthma.
Rob contacts a community-based organization (CBO) that has a long history of working with the public housing units and asks them to help develop a plan for the project. Rob works with other members of the county health department and Franklin city government to develop a proposal for the U.S. Department of Housing and Urban Development (HUD). The CBO signs a letter of support agreeing to collaborate on the project if funding is awarded.
They propose a pilot program that would remove lead paint and install air filters in the public housing units. The pilot program would also train some of the unemployed residents to assist in the renovations. They are able to link their proposal directly to national and State Healthy People 2020 objectives in both Respiratory Diseases and Environmental Health topic areas.
In addition to tracking blood lead levels, they decide to also monitor childhood asthma rates to see if they decline as a result of their focus on reducing dust and improving air quality.
HUD awards them funding for the project and notes their use of supporting data as a reason they were funded.
Implement
The CBO is excited about the project and is responsible for communicating with residents about the improvements, responding to any concerns they may have, and supervising the training and employment component of the project.
Rob is responsible for overseeing the entire project and works closely with contractors to ensure the work is completed correctly. Lead paint is removed, and air filters are installed throughout the public housing units over a 2-year period.
Track
Rob carefully tracks the project’s progress and collects formal and informal data to measure the project’s impact. Elevated blood lead levels reported to the county health department are 0.75 percent lower after the project than before the improvements were made. Residents self-report feeling sick less often and having fewer asthma attacks. As a result of the project, residents also report high levels of satisfaction with the condition of their housing unit and the management of the public housing complex overall.
Rob hopes that by carefully tracking and evaluating the project, the county health department will receive funding to expand the project to all public housing units in the county. He expects that it may be difficult to continue funding the program through public grants, so he also contacts local and national businesses and private foundations that may be able to provide funding.
Rob works hard to keep the CBO and the local residents involved in the project, establishing “train-the-trainer” programs with residents in nearby public housing units and hosting ongoing community meetings and events.
Tool # 1 - Organizing a Coalition (PDF)
Healthy People 2020 provides a list of important questions to consider before organizing a coalition, in a printable format that allows you to fill out answers to the questions and/or distribute them to a planning group.
Tool # 2 - Brainstorm: Potential Partners (PDF)
A checklist from Healthy People 2020 that will help you think of all possibilities for potential partners for your effort.
Tool # 3 - Prioritizing Issues (PDF)
Healthy People 2020 provides an exercise that will assist you in determining which issues it is most important for your effort to undertake.
Tool # 4 - Brainstorm: Community Assets (PDF)
A checklist from Healthy People 2020 to assist you in determining community assets that are available.
Tool # 5 - Setting Targets for Objectives (PDF)
Healthy People 2020 provides national and state standards and other helpful guidelines to assist you in setting reasonable goals for your initiative.
Tool # 6 - Defining Terms (PDF)
This page from Healthy People 2020 provides clear definitions of many of the terms – vision, baseline data, etc. – you might use in discussing your plan.
Tool # 7 - Potential Health Measures (PDF)
Healthy People 2020 provides a list of some possible indicators to consider measuring to track your initiative's progress.
Tool # 8 - Coalition Self-Assessment (PDF)
This anonymous coalition self-assessment from Healthy People 2020 allows members to rate the group and its staff, leaders, and members on a variety of factors important to the effective functioning of a coalition
Tool # 9 - Communication Plan Template (PDF)
A template from Healthy People 2020 to assist you in creating an effective communication plan for your effort.
Tool # 10 - Measuring Progress (PDF)
Healthy People 2020 provides helpful formulas for quantitatively measuring your progress.
```html
-
What is the Take Action Cycle?
-
Why use the Take Action Cycle?
-
When should you use the Take Action Cycle?
-
Who should use the Take Action Cycle?
-
How do you use the Take Action Cycle?
What is the Take Action Cycle?
The health and well-being of a community depend on many different factors – ranging from health behaviors, education, and employment to health care, housing, transportation, the environment, and broader community conditions. County Health Rankings & Roadmaps (CHR&R), a program of the University of Wisconsin Population Health Institute, provides data and tools that help communities understand how long and how well people are living and the conditions that shape health.
CHR&R no longer assigns each county an individual rank. Instead, counties are placed into national Health Groups based on similarities and meaningful differences in Population Health and Well-being and Community Conditions. These data can help communities identify strengths, challenges, and opportunities for action.
But understanding community health data is only one part of improving health. The CHR&R Action Center provides guidance and tools that communities can use to move from information to action. The Take Action process can help groups work together to create healthier and more equitable places to live, learn, work, play, and thrive.
The current Take Action process includes seven interconnected components – Work Together, Assess Needs & Resources, Focus on What's Important, Choose Effective Policies & Programs, Communicate, Act on What's Important, and Evaluate Actions.
Why use the Take Action approach?
The Take Action approach recognizes that every community has its own strengths, resources, needs, relationships, and capacity for change. Community health improvement efforts may therefore begin at different points in the process rather than following one rigid sequence.
Each component provides guidance and tools for groups working to improve health. Improving community health requires people from different sectors to work together on a variety of activities, and the Take Action approach provides a structure for building partnerships, understanding community conditions, setting priorities, selecting strategies, taking action, communicating effectively, and evaluating progress.
When should you use the Take Action Cycle?
Use the Take Action process to start, strengthen, or improve a community health initiative. Because it is cyclical, you can enter the process at the point that best fits your current work and return to earlier steps as conditions, information, partnerships, or priorities change.
Who should use the Take Action Cycle?
The Take Action process can involve people from business, health care, public health, education, government, elected boards, advocacy organizations, faith communities, nonprofit and community-based organizations, philanthropy, community development, and other sectors. Most importantly, it should meaningfully involve community members, particularly people directly affected by the conditions or issues the effort is intended to address.
How do you use the Take Action Cycle?
The Take Action process is a guide for turning a vision of a healthier community into action. It helps communities use data, evidence, community knowledge, relationships, and available resources to guide health improvement efforts. The components are connected and may be revisited as the work develops.

Work Together
Everyone has a role to play in improving the health of communities. As you move from data to action, it is important to engage community members and partners from different sectors. Working together with a shared vision can produce better results than working separately.
Reach out to people and organizations that have an interest in improving health or are directly affected by the issues involved. Build a contact list that helps you identify people from different sectors, communities, and networks who might contribute. Consider their interests and motivations: How might improved community health connect with their goals? Who has relationships with or influence on the people and organizations whose decisions will affect the work?
Your multi-sector team should include people directly affected by the conditions or issues you are addressing. Their knowledge and lived experience can provide perspectives that may not be available through organizations or data alone. Consider whether the team reflects the racial, cultural, socioeconomic, geographic, age, disability, and other forms of diversity relevant to your community and initiative.
As you build your team and recruit participants, ask people to help identify others who should be involved. Recruitment is an ongoing process; continue asking, “Who else should we be talking to?” Use stakeholder analysis and other coalition-building tools to consider whose perspectives, knowledge, relationships, resources, and influence are important to the effort.
Once you have brought together a group of people interested in improving community health, build a shared understanding of the issues and conditions affecting health. A useful starting point is the current University of Wisconsin Population Health Institute Model of Health, which examines Population Health and Well-being, Community Conditions, Societal Rules, and Power. The model can help groups think more broadly about how community conditions are created and how they influence health.
When developing your group's vision and mission statements, make sure the brainstorming process is participatory and provides meaningful opportunities for people to contribute their ideas.
Once you have engaged core partners and established a shared vision and mission, consider the structure and leadership of the group. Organizational Structure: An Overview provides guidance for deciding what type of structure may work best. Questions might include: How will decisions be made? How will leadership be structured? Who will serve in leadership roles? How will community members participate in decisions? Will the same people oversee each part of the improvement process?
Assess Needs & Resources
Once you have assembled people who are interested in community health improvement and have explored how to work together, take stock of your community's needs, resources, strengths, and assets.
County Health Rankings & Roadmaps provides county and state data that can serve as one starting point for understanding health and community conditions. CHR&R currently provides Health Groups and data across measures organized within the University of Wisconsin Population Health Institute Model of Health. Reviewing these data over time can help identify strengths, challenges, patterns, and questions that need further investigation.
Your community can be defined geographically – for example, a neighborhood, city, county, region, state, or Tribal community – or around a population or shared experience relevant to your initiative. Before beginning an assessment, define the community in a way that is useful for your goals. Developing a Plan for Identifying Local Needs and Resources describes what community needs and resources are and how to identify them, while Understanding and Describing the Community provides additional guidance for understanding community context.
It is important to assess strengths and assets as well as needs. As you work through the Take Action process, look for ways to build on existing relationships, organizations, skills, knowledge, facilities, programs, policies, and other community resources rather than focusing only on problems or gaps.
Another tool that may be useful as you assess your community is Mobilizing for Action through Planning and Partnerships (MAPP), a community health assessment and improvement planning framework developed by the National Association of County and City Health Officials with support from the Centers for Disease Control and Prevention.
Once you have determined what you want to know about your community, identify the specific measures or categories of measures that can help answer those questions, along with possible data sources. As you select indicators, consider whether they are relevant, available, accurate, useful, and practical to collect.
Some common places to find useful information include:
- Federal government data, such as Census Bureau and public health data.
- Assessments or studies conducted by local, Tribal, state, or regional government agencies.
- Assessments or studies conducted by other organizations. Hospitals, health and human service organizations, community-based organizations, Chambers of Commerce, foundations, and other groups may conduct community assessments and may be willing to share findings.
- Studies conducted by researchers at colleges, universities, research organizations, or other institutions.
- Knowledge and lived experience shared directly by community members.
Existing information may not answer all of your questions, and your team may need to collect its own data. There are many ways to collect qualitative and quantitative information, and using multiple methods can provide a fuller picture of community conditions.
If organizations involved in your assessment are also using the process to meet federal, accreditation, or organizational requirements, coordinate the work where possible.
Community Health Needs Assessments: Charitable hospital organizations subject to federal requirements generally conduct a community health needs assessment at least once every three years and adopt an implementation strategy addressing identified needs. Collaboration can reduce duplication and broaden community participation.
Public Health Accreditation: Health departments pursuing or maintaining accreditation through the Public Health Accreditation Board may use community health assessment and improvement planning activities as part of meeting applicable accreditation requirements.
Once you've collected and analyzed your data, communicate the findings in accessible ways – through community presentations or forums, fact sheets, dashboards, websites, social media, newsletters, local media, or other appropriate channels. Sharing findings can help community members understand the issues, contribute their interpretations, and participate in decisions about what happens next.
Focus on What's Important
Once you've examined your community's needs, strengths, resources, and conditions, decide which issues or opportunities to address. Taking time to set priorities helps ensure that limited community resources are directed toward areas where focused action can make a meaningful difference.
Working with a multi-sector group brings different perspectives to the process. That makes the group stronger, but it can also make choosing priorities more complicated. A skilled, neutral facilitator can help guide priority-setting while making sure different voices have meaningful opportunities to be heard. A facilitator does not necessarily have to come from outside the group; what matters is that the person can guide the process fairly.
As you begin priority-setting, it may help to focus your group on a guiding question. Reviewing your vision and mission statements can provide a starting point. Key ideas or values in those statements can help shape the question you use to examine potential priorities.
Once you have a guiding question, brainstorm possible priorities. Ask participants what they see as the most important issues based on community knowledge, lived experience, and the data that have been reviewed. As you consider possible priorities, look beyond immediate symptoms and examine the underlying conditions or root causes contributing to the issue.
The number of priorities you select will depend on available resources, capacity, and other work already underway in the community. It may be useful to prepare a summary of the information gathered through your assessment. Matching the number of priorities to your team's ability to act is important. Choosing a manageable number of priorities and making meaningful progress may be more effective than selecting so many that resources become spread too thin.
There are a variety of processes for selecting priorities. Before choosing one, agree on the criteria you will use to judge possible issues. Criteria express the values, standards, and practical considerations your team will use when making choices and establishing priorities.
In addition to formal priority-setting methods, gather input from community members. This might include forums, presentations, conversations with community organizations, surveys, interviews, focus groups, or other forms of engagement.
Once your group has identified possible priorities, gathered community input, and reviewed how the issues fit your criteria and assessment findings, finalize the priorities. This can be done through consensus, voting, a prioritization matrix, or another transparent decision-making process.
Review the resulting priorities as a group. Do they reflect the available data and community experience? Do they make sense to community members directly affected by the issues? Are the priorities realistic enough for the community to act on? Before moving forward, make sure there is meaningful community understanding and support.
Communicate the priorities and the reasons behind them to decision-makers, partners, community members, and others whose support or involvement may affect the work.
Choose Effective Policies & Programs
Once you have decided which priority issues to address, choose policies, programs, practices, or systems changes that offer a reasonable opportunity for success.
You may already have identified some possible approaches, but it is worth examining them more closely. Rather than selecting something simply because another community uses it, consider both the evidence supporting the approach and how well it fits your community's needs, strengths, resources, history, and conditions. Communities may also develop new approaches where existing strategies do not adequately address local needs.
As you research potential strategies, you will encounter different kinds of evidence, including systematic reviews, peer-reviewed studies, expert recommendations, evaluation findings, and community experience. Terms such as evidence-based, evidence-informed, promising practice, and model program may be defined differently by different organizations. As a team, discuss what kinds of evidence will inform your decisions.
County Health Rankings & Roadmaps' What Works for Health is a searchable resource of evidence-informed strategies. Strategies include information about expected benefits, evidence ratings, implementation considerations, and potential effects on disparities.
In addition to evidence of effectiveness, consider community context:
- Are there political, legal, organizational, or practical conditions that might make a strategy more or less feasible?
- What is your community's readiness for the policy, program, or other strategy you are considering?
- The Community Readiness Model can help assess how prepared a community is to address a particular issue.
- Does your community have the people, relationships, funding, expertise, and other resources needed to implement and evaluate the strategy?
- Can you build on resources and assets already available?
- Will you need to identify additional funding or other support?
Policies and programs may sometimes need thoughtful adaptation to fit local circumstances. If no two communities are exactly alike, strategies may not look exactly alike in every setting either. At the same time, adaptations should preserve the elements that are important to a strategy's effectiveness.
As you make your selection, consider a balance of strategies. Some manageable short-term actions may help build momentum while the community also works toward more complex, long-term policy, systems, or environmental changes.
To help choose an appropriate policy, program, or strategy, consider:
- Does the strategy meet the criteria established by your group?
- Does implementation require a particular organizational structure or lead organization? If so, is that capacity available?
- What evidence suggests that the strategy can contribute to the outcomes you want?
- Which parts of the strategy are essential, and what adaptations might be appropriate for your community?
- What resources are available or can be developed to support implementation?
- How well does the strategy fit the community's context, values, priorities, and needs? What engagement may be necessary to build understanding and support?
- How will you know whether the strategy is successful in your community?
Communicate
Communication is important throughout the Take Action process, not simply after decisions have been made. Effective communication can help people understand community conditions, contribute to decisions, build support, participate in implementation, and learn from results.
Begin by identifying the purpose of your communication. What do you want people to understand, feel, discuss, or do? Then identify the people you need to reach and the people or organizations they trust as messengers.
A communication plan might include:
- Identifying the purpose of your communication.
- Identifying the people and groups you need to reach.
- Planning and designing clear, accurate, and accessible messages.
- Considering the resources available for communication.
- Planning for challenges, misinformation, or unexpected events.
- Selecting appropriate communication channels and trusted messengers.
- Creating specific communication action steps.
- Evaluating whether your communication is reaching people and producing the intended response.
Communication should also involve listening. Community members, particularly people directly affected by health inequities or by the proposed changes, should have opportunities to respond, ask questions, raise concerns, and contribute knowledge throughout the process.
Depending on your audience and purpose, communication methods might include community meetings, websites, email, social media, video, local news media, radio, printed materials, presentations, or direct conversations. The most appropriate methods will vary by community.
Stories can help people understand why an issue matters, but they should be used responsibly. Combine personal experience with relevant evidence and respect participants' consent, privacy, and dignity.
Act on What's Important
Once you've selected a policy, program, or other strategy, the next step is implementation. Build on community strengths, use available resources, and respond to local needs and conditions.
One of the first steps is to define exactly what you want to accomplish and why. Taking time to do this will make it easier to communicate about and advocate for the approach you are proposing.
You may want to use a visual tool to describe the strategy and how it is expected to contribute to long-term results:
- Logic models can help explain what you expect to accomplish and how activities are connected with outcomes.
- A theory of change describes the conditions and steps expected to contribute to a long-term goal.
- Strategy maps can show relationships among broad strategic objectives.
Some changes may already have strong support and identified funding. Others may require additional advocacy, policy change, partnership development, or resource-building. When this is the case, identify the people and organizations with the authority, influence, relationships, or resources needed to move the strategy forward.
Who do you need to influence?
Stakeholder and power-mapping tools can help identify who influences a policy or systems decision, who is directly affected by it, and what relationships may help move the issue forward.
Who are your allies?
Stakeholder and ally analysis can help identify people and organizations that care about the issue, have relevant expertise, or can contribute relationships, credibility, resources, or other forms of support.
Who holds different perspectives?
Identifying people who hold differing perspectives can help you understand their concerns, interests, influence, and reasons for supporting or opposing a proposed approach. Understanding those perspectives can help identify areas of disagreement as well as possible areas of common ground.
Create a specific action plan for implementing the strategy. Action plans describe how the community will accomplish its goals by identifying specific activities, responsible people or organizations, timelines, resources, and measures of progress.
As you begin action planning, move from the broad goal to specific and measurable objectives and then to concrete action steps. Objectives should make clear what is expected to change, how progress will be measured, and the time period involved.
An important part of implementation is creating a realistic budget and resource plan. Planning and Writing an Annual Budget provides guidance on developing a budget. If available resources are not enough to carry out the plan, consider fundraising, grant funding, partnerships, in-kind support, shared staffing, or adjustments to the scale and timing of activities.
Some useful principles for securing resources include:
- Plan ahead and understand your specific needs.
- Identify resources already available to the effort.
- If applying for external funding:
- Understand the funder's goals, priorities, and requirements.
- Describe clearly what success will look like and how it will be measured.
- Explain how effective work can be sustained beyond the initial funding period.
Once you have an action plan and resources to guide the work, begin implementation. Continue evaluating whether additional partners, community members, or expertise are needed. If people oppose or question the approach, try to understand the reasons for their concerns and address them accurately and respectfully.
Be aware of applicable rules related to lobbying and advocacy, particularly when public employees, government resources, grant funds, or tax-exempt organizations are involved.
As the work continues, recognize progress and capture lessons learned. After major activities, take time to reflect on what worked, what did not, and why. Recognize the contributions of people and organizations involved in the effort.
Monitor implementation using the measures established in your goals and action plan so that you can communicate progress to community members, partners, funders, and decision-makers. Communicating Information to Funders for Support and Accountability provides additional guidance.
Document the work – including challenges, adjustments, and lessons learned – so that your own community and others can learn from the experience. Participatory approaches such as Photovoice may also help community members document conditions and tell the story of change.
To help sustain successful changes, develop a long-term accountability plan addressing partnerships, organizational responsibility, communication, staffing, funding, and continued monitoring. As conditions change, revisit whether the measures you are using still provide useful information. If not, adjust them and document what you learn.
Evaluate Actions
Evaluation is an important part of community health improvement. It can help you understand whether the initiative is being implemented as intended, whether it is contributing to desired changes, where improvements are needed, and how resources are being used.
Although Evaluate Actions appears as one component of the Take Action process, evaluation should occur throughout community health improvement.
- As you move through the Take Action process, evaluation will serve different purposes.
- As you Work Together, evaluate how well the partnership is functioning and whether people who should be involved have meaningful opportunities to participate.
- As you Assess Needs & Resources, identify measures that can establish a baseline and track conditions over time.
- As you Choose Effective Policies & Programs, use available evidence and evaluation findings to understand what approaches may fit the community.
- As you Communicate, assess whether messages are reaching people, being understood, and creating opportunities for meaningful participation.
- As you Act on What's Important, use evaluation to improve implementation and examine the effects of the selected strategy.
There are several ways evaluation can be used:
- To gain insight (formative evaluation).
- Assess community interest, knowledge, readiness, or concerns related to a proposed policy or program, and use that information in planning.
- Identify challenges and opportunities related to the strategy and use that information to improve planning and advocacy.
- To improve a policy or program (process evaluation).
- Monitor implementation and use the findings to improve activities, procedures, or other parts of the effort.
- Gather feedback from people participating in or directly affected by the effort and use that information to improve content, access, implementation, or communication.
- To evaluate effects and outcomes.
- Measure progress on outcome indicators and use the results to strengthen the strategy and support accountability.
- Examine how benefits and outcomes are distributed among different populations and communities, particularly those most directly affected by the issue.
- Use findings to be accountable to community members, partners, funders, and decision-makers.
- As you decide how and when evaluation will be used, consider:
- What do community members and other stakeholders want to know? How will they use the information?
- What does the community need and want to know?
- What information do funders or other accountable organizations require?
Determine who will participate in the evaluation. Evaluation is often strongest when people with different forms of knowledge – including community members, program participants, staff, partners, and people with evaluation expertise – help develop and interpret the process. An outside evaluator may also be useful when appropriate and feasible.
As with the larger community health improvement process, engage stakeholders in developing the evaluation plan. Different groups may have different questions about the policy or program and different ideas about what meaningful success looks like.
The work done during implementation should help shape the evaluation. Ask: What did you set out to accomplish? Why did you select this policy or program? What activities did you carry out? What changes did you expect to see? Which questions are most important to answer?
If you have not developed a logic model or theory of change, take time to clarify what the strategy is expected to accomplish and why. Consider short-, medium-, and long-term goals. Long-term health outcomes may take years to change, so shorter-term measures can help show whether the conditions expected to lead to those outcomes are changing.
Once you have determined the goals and evaluation questions, identify indicators – specific process, impact, or outcome measures – and appropriate data sources.
Process measures describe activities and implementation and help determine whether the initiative is being carried out as intended.
Examples include:
- Participation: number and range of participants, frequency of participation, and continuity of involvement.
- Communication: reach and engagement through community meetings, media coverage, newsletters, email, social media, or other communication channels.
- Activities: number and type of meetings, workshops, services, policy discussions, outreach activities, or other planned actions completed.
- Policy or systems implementation: measures showing whether agreed-upon policies, procedures, or system changes are actually being carried out.
Impact and outcome measures examine changes associated with the work of the initiative.
Examples include:
- Participant-level indicators, such as changes in knowledge, skills, access, behavior, or perceptions relevant to the initiative.
- Community-level indicators, such as changes in community conditions, access to resources, policies, systems, environments, or relevant population health outcomes.
As you select indicators, consider whether they are useful, accurate, available, practical to collect, and relevant to your evaluation questions.
Decide where the data will come from. Sources may include people, documents, administrative records, observations, surveys, interviews, focus groups, or existing data systems. Consider whether information collected during the Assess Needs & Resources step can provide useful baseline or follow-up data. Strong evaluations often combine qualitative and quantitative information while keeping the amount of data collection realistic.
Before collecting data, determine what kinds of changes you reasonably expect for each indicator and over what period of time. Benchmarks should be meaningful and realistic while still reflecting the change the initiative is trying to achieve.
Some tips to make the data collection process go smoothly:
- Train people who will collect or manage the data.
- Schedule data collection activities and pilot methods when appropriate so the process can be improved before full implementation.
- Track and organize data as it is collected, and protect privacy and confidentiality where required.
- Collect information that has a clear purpose and plan for how it will be used.
- Check in throughout data collection to identify what is working, what could be improved, and whether the original evaluation questions are being answered.
- Periodically review data quality.
- Do the data adequately represent the people, communities, and experiences relevant to the initiative, including groups that might otherwise be underrepresented?
- Are you measuring the short-, medium-, and long-term changes that are relevant to the strategy?
- Are the findings plausible when compared with other data and community knowledge? If not, consider whether the sampling or data collection methods need to be examined.
- Develop a system for analyzing the data: What will be reviewed, by whom, and how often?
- Develop a system for sharing findings with community members and other stakeholders.
Using the data collection and analysis system you established, monitor progress toward short-, medium-, and long-term goals. Evaluation results can inform decisions about continuing, expanding, modifying, or ending a policy or program. Return to the original assessment and problem definition and ask whether the work is affecting the conditions you set out to change.
Sharing results is an important part of evaluation. Different audiences may need different forms of reporting. Evaluation findings can guide decisions about future implementation, explain what the initiative accomplished, support accountability, help funders and partners understand the work, allow other communities to learn from your experience, and contribute to knowledge about what works and under what conditions.
In Summary
County Health Rankings & Roadmaps provides data and evidence-informed resources that communities can use to understand population health and well-being and the conditions that shape health. Beginning in 2025, CHR&R replaced individual county rankings with national Health Groups, allowing communities to examine similarities and differences without treating community health as a competition between counties.
The Take Action process offers a practical way to turn that information into community action. Its current components are Work Together, Assess Needs & Resources, Focus on What's Important, Choose Effective Policies & Programs, Communicate, Act on What's Important, and Evaluate Actions.
These components are not meant to be followed as a rigid one-time sequence. Communities can begin where they are, revisit earlier work when circumstances change, and use data, evidence, community knowledge, relationships, communication, and ongoing evaluation to strengthen their efforts over time.
```
Resources
Online Resources
Board Development Profile (PDF) provides questions for recruiting additional board members and a template for identifying the assets they bring.
Checklist for Ensuring Effective Evaluation Reports (PDF from the CDC’s Program Evaluation Framework) includes format and content considerations for developing your evaluation report.
Checklist for Sharing Positions and Other Resources (from the Community Tool Box) can help you evaluate how to share resources, including people, time, technology, facilities, training, technical assistance, and money.
Capture Attention! Inspire Action! (from the Wisconsin Clearinghouse for Prevention Resources) provides tips for giving a presentation or talking to someone you need to persuade.
Channeling Change: Making Collective Impact Work (from the Stanford Social Innovation Review) is a follow up to the popular Collective Impact article by the same authors. Its focus is on answering commonly asked questions: How do we begin? How do we create alignment? How do we sustain the initiative?
Collaboration Multiplier (from Prevention Institute) can help you identify where you need additional expertise and resources.
Collective Impact (from the Stanford Social Innovation Review) discusses the five conditions for communities’ collective success.
Community Assessment Tools (PDF from Rotary International) provides detailed descriptions, planning tips and, in some cases, samples for several types of assessment.
Community Commons is a website designed for communities to learn and share from and with each other.
Community Health Status Assessment answers the following questions: How healthy are our residents? What does the health status of our community look like?
Community Themes and Strengths Assessment answers the following questions: What is important to our community? How is quality of life perceived in our community? And what assets do we have that can be used to improve community health?
Community Health Partnerships: Tools and Information for Development and Support (PDF from the National Business Coalition on Health and the Community Coalitions Health Institute) provides specific suggestions for talking with potential partners from the business sector (p. 20).
County Health Rankings & Roadmaps Searching the Evidence
Developing Effective Coalitions: An Eight Step Guide provides a helpful framework establishing the structure for your coalition.
Developing Facilitation Skills (from the Community Tool Box) can help you understand how to conduct meetings so that everyone stays on task and engaged.
Gathering Credible Evidence (from the CDC’s Program Evaluation Framework) explains the role of this step in the evaluation process and provides guidance on related activities.
Governance is Governance (PDF from Independent Sector) describes the functions, roles, responsibilities, and leadership dynamics between a board of directors and executive director.
Forces of Change Assessment answers the following questions: What is occurring or might occur that affects the health of our community or the local public health system? What specific threats or opportunities are generated by these
A Handbook for Participatory Community Assessments (PDF from the Alameda County Public Health Department) walks through the process the department undertook with two neighborhood groups to conduct participatory community assessments. The handbook includes detailed information about developing partners and preparing for an assessment, pp. 1-27.
Inclusivity Checklist (from the Community Tool Box) can help you look at the issues of inclusivity and diversity across a wide range of collaboration activities.
Local Public Health System Assessment answers the following questions: What are the components, activities, competencies and capacities of our local public health system? How are the essential services being provided to our community?
occurrences?
The Nonprofit Social Media Decision Guide (from Idealware) describes how to best use social media to achieve your goals. (Complete a free online registration at bottom of page to access the guide.)
Point-K: Tell Me More! (from Innovation Network) is a free searchable resource database focused on resources for evaluation and capacity building. More than 300 reports, articles, tip sheets, and how-tos. (You will need to register first.)
Program Development & Evaluation Logic Models (from University of Wisconsin-Extension) includes tools for drafting logic models, and examples like Reducing Underage Drinking.
Program Manager’s Guide to Evaluation from the Department of Health and Human Services. Chapter 2: What is Program Evaluation lays out the advantages and disadvantages for different types of evaluation teams. Chapter 3: Who Should Conduct Your Evaluation? provides an overview of program evaluation including the basic questions answered by an evaluation and what is involved in conducting an evaluation. Chapter 4: How Do You Hire and Manage an Outside Evaluator? provides guidance for the logistics of finding and managing an outside evaluator.
Prioritizing Issues Exercise (from Healthy People 2020) is a two-page exercise designed to help the group decide on which issue(s) to focus.
Priority Setting Process Checklist (from The Health Communication Unit) presents a priority-setting checklist that can be used as you prepare for a priority-setting process, or as a reflection tool, after you’ve determined your priorities. The checklist considers data gathering, meaningful stakeholder participation, time, resources, and decision making.
Priority Setting Exercise (PDF example adapted from Thurston County Public Health and Social Services, Washington) worksheet follows a customized version of the Criteria Weighting Method. It is a useful exercise to adapt after assessing community needs and resources.
Roles and Job Descriptions (PDF from Coalitions Work) includes sample descriptions, duties and responsibilities, and qualifications that can be adapted for staff, volunteer leaders and members.
Tools and Checklists for Conducting Effective Meetings (from the Community Tool Box) provides a number of checklists for facilitating, documenting and evaluating meetings.
Theory of Change: A Practical Tool for Action, Results and Learning (from Organizational Research Services) describes a process for developing a theory of change for a community, pp. 18-24.
Strategic Issues Overview (from the National Association of County & City Health Officials) is an overview of the phase of the Mobilizing for Action through Planning and Partnerships (MAPP) process, during which participants develop an ordered list of the most important issues facing the community. This step-by-step overview will help users prepare for and begin distilling the data they’ve gathered into priorities.
A Sustainability Planning Guide for Healthy Communities (from CDC) helps public and community health professionals develop a sustainability plan and learn key sustainability approaches.
Your Board and Fundraising: An Introductory Course (from Alliance for Nonprofit Management) provides a one-hour recorded webinar aimed at helping you think through the process of getting your board involved with fundraising.
What Drives Health (from the Robert Wood Johnson Foundation) discusses how social factors like education, income, work, and housing can affect health directly and indirectly.
What is the Take Action Cycle?
___The Take Action cycle provides a way to transform information from County Health Rankings about your county’s status into action to improve your area’s health.
___The Take Action cycle has six steps
- Work Together
- Assess Needs & Resources
- Focus on What’s Important
- Choose Effective Policies & Programs
- Act on What’s Important
- Evaluate Actions
Why use the Take Action Cycle?
___Each component of the Take Action Cycle offers tailored guidance and tools for groups undertaking health improvement efforts
___The Take Action Cycle is designed with the knowledge that each community has different resources and a unique situation, and thus encourages starting at whatever point in the cycle is most relevant for your community
___The Take Action Cycle provides information on how to encourage diverse stakeholders to work towards the same goal
When should you use the Take Action Cycle?
___When you are starting an initiative
___When you are expanding an initiative
___When you are trying to improve an initiative
___Each step of the Take Action Cycle includes comprehensive guidance and links to specific tools, making it adaptable to your initiative’s needs at every stage
Who should use the Take Action Cycle?
___Stakeholders from a wide variety of sectors, including:
- Business
- Health care
- Public health
- Education
- Government
- Advocacy
- Faith-based organizations
- Non-profit organizations
___Anyone who cares about or is affected by the many factors that influence community health
How do you use the Take Action Cycle?
___The Take Action Cycle is a guide to transforming your vision of a healthy community into a reality, providing you with ways to use the information and resources you have to spur action and change
___Visit the Roadmaps to Health Action Center, and click on various components of the cycle for tailored tools and guidance.
___If you’re not sure where to begin, click on Getting Started, and answer some basic questions about your initiative to find the best place to start and the most relevant tools
___There are six phases of the Take Action Cycle
- Work Together
- Visit the Work Together section to determine how to engage people from diverse sectors who have an interest in community health
- Develop vision and mission statements to guide your work
- Assess Needs & Resources
- Visit the Assess Needs & Resources section to determine where to direct your efforts
- Get your County Snapshot by selecting your state and then your county from the Health Rankings section of the site
- Review the County Health Rankings model for additional information you might want to gather about your community
- Brainstorm community assets, resources, and needs
- Identify specific measures, or community-level indicators, that will answer your questions and help you determine a baseline to measure your progress against
- Focus on What’s Important
- Visit the Focus on What’s Important section for guidance on selecting priority issues to focus on
- Have your group brainstorm priority issues
- Solicit feedback from the community
- Determine whether the issues you have selected fit with your criteria and the results of your community assessment
- Come to a consensus on the priority issues that your initiative will address
- Choose Effective Policies & Programs
- Visit the Choose Effective Policies & Programs section to determine how best to address your priority issues
- Research different programs and policies to determine which ones have been demonstrated to work in situations similar to yours
- Visit What Works for Health to browse through a database of evidence-based programs and policies
- Consider your community’s context and readiness for implementing specific programs or policies
- Act on What’s Important
- Visit the Act on What’s Important section for guidance on implementing your chosen program or policy
- Define exactly what you want to achieve using a logic model, theory of change, strategy map, or similar tool
- Determine who you want to influence, who your allies are, and who your opponents are
- Use social media and other communication channels to spread your message
- Create a specific action plan for implementing your program or policy
- Make sure your goals are Specific, Measureable, Achievable, Realistic, Time-determined (SMART)
- Create a thorough budget
- Implement your program, continuing to monitor the process using the community-level indicators you chose previously
- Communicate your progress to stakeholders, funders, and the community
- Document your methods and strategies
- Develop a long-term sustainability plan that addresses policies, partnerships, organizational strategies, communications plans, and funding
- Evaluate actions
- Visit the Evaluate Actions sections for guidance on using evaluation to improve your initiative
- Evaluation should be conducted throughout the program, not just at the end
- Evaluation can have several purposes
- To gain insight (formative evaluation)
- To improve a policy or program (process evaluation)
- To evaluate program effects (impact, results, or outcome evaluation)
- Determine who will do the evaluation
- Using your initial plan, determine what goals you will evaluate and what indicators/measures you will use
- Process measures are activities that take place during the initiative that help you determine how well things are going
- Impact measures explain the overall impact that occurs as a result of your actions
- Outcome measures highlight the changes that happen in the community as a result of the work done by your initiative
- Once you have determined the indicators/measures you will use, choose where/how you will collect this data
- Monitor progress toward your short-, medium- and long-term goals.
- You can use your evaluation results to make recommendations for continuing, expanding, redesigning or abandoning your policy or program. Go back to your initial assessment and problem definition and determine whether your efforts are impacting the problem you set out to address.
Numerous counties across the nation are already sharing stories of how the County Health Rankings have spurred cross-sector collaboration to improve community health. Below are a few of the stories from the County Health Rankings website, and you can view more or contribute your own.
Example 1: Never Giving Up: Addressing Drug Addiction in Scott County, Indiana
Carolyn King, Scott County Health Outcomes Task Chair for the Scott County Partnership Scott, Indiana - Snapshot
What would you do if the county you’d lived in and loved for many decades was ranked the least healthy county in your state for three years running? What if just days after this year’s Rankings release Reuter News Service began investigating why your county has the highest rate of prescription drug deaths in a six county area? This is the situation faced by the people of Scott County, Indiana. It would be understandable if their response was to give up in frustration, but that’s far from the reality.
Located in the beautiful rolling hills of southeastern Indiana, Scott County has suffered from decades of generational poverty with all its associated problems: isolation, depression, poor diet, tobacco use, colorectal cancer, child abuse, teen pregnancy. According to the 2012 County Health Rankings the rate of premature death in Scott County is much higher than the state average. “We die too young here and people don’t feel well,” says Carolyn King, Scott County Health Outcomes Task Chair for the Scott County Partnership. But a passionate group of people from every sector has been working together to turn things around and they’re in it for the long haul. According to Ms. King, “People care deeply here. The level of partnership and collaboration is exceptional.”
Today, besides the Scott County Partnership, a 40 member coalition called CEASe (Coalition to Eliminate Abuse of Substances of Scott County), a local coordinating council for drug prevention, which includes law enforcement, healthcare, education, community leaders, and others, is addressing the prescription drug abuse problem. CEASe worked with the local hospital and doctors to change prescribing practices. Formerly, people coming to the emergency room could get 10 day prescriptions for pain medication. Now, narcotic prescriptions are only written for 3 days at a time, and doctors are committed to blood level checks and reviewing patients’ prescription use history. Ms. King says, “We’re all on board together around this."
Much has been accomplished in spite of limited state and local funding. To promote positive health, the Health Outcomes Task Force started a Facebook site and published “Feeling Good Scott County” describing their numerous health initiatives, including colorectal cancer screening, a community garden, enhancements to the local Farmer’s Market, and replacing deep fat fryers at local schools with healthy options.
CEASe is addressing strategies around tobacco prevention, underage drinking and the new narcotic prescription policies at the local ER. For example, a local faith-based leader began “New Creation Addiction Ministry” to help former addicts find employment and stay sober. Fortunately, because there is so much activity around these and other issues, some funds are beginning to flow into the community. For example, a local not-for-profit recently received a large grant to address health and educational issues for pregnant and parenting teens. “Because we’re stirring the pot,” says Ms. King, “many agencies are getting grants.” It isn’t going far enough yet, but in the meantime, much has been accomplished simply through the power of people working together on a common vision of a healthier community. “We have much to do to address health disparity due to high poverty, but we are willing to tackle all issues in a creative fashion,” affirms Ms. King. Though change takes time and the annual Rankings results don’t reflect results quickly, Ms. King and the others on her team are encouraged by the way the community is pulling together around health in a positive way.
Example 2: In San Bernardino, CA, County Health Department Takes Lead to Improve Area's Poor Health Ranking
Evelyn Trevino, program coordinator for San Bernardino County Healthy Communities | San Bernardino, California - Snapshot
The 2011 County Health Rankings ranked San Bernardino County—which spans more than 20,000 square miles and a population of more than 2 million—50th out of 56 California counties in health factors like physical environment, social and economic factors, health behaviors and clinical care. The city of San Bernardino alone faces significant public health challenges, with a lower life expectancy, a higher homicide rate, and fewer parks and healthy food options than the rest of the state. Many other communities throughout the county share similar challenges associated with the county’s high poverty and unemployment levels, and its vast geography makes it difficult for many residents to reach centralized services.
But initial disappointment over its low ranking didn’t prevent the San Bernardino County Health Department from seeing the County Health Rankings as an opportunity to strengthen its current health improvement initiatives and persuade policymakers of the need for change. In fact, by clearly showing where the county ranks on various health measures, the Rankings have helped inform the health department’s six-year drive to get every community in the county to launch a Healthy Communities initiative aimed at ensuring that all residents have the opportunity to live a healthy life.
“The County Health Rankings are a terrific tool for us to take to policymakers because we can show that the status quo isn’t sufficient,” said Evelyn Trevino, program coordinator for San Bernardino County Healthy Communities. “It motivates support and action. We use it to get the message out.”
To date, 17 of the county’s 24 jurisdictions are at some stage of implementing a Healthy City initiative locally. Three partner cities have updated their general plans to include health as a guiding principle. Others have enacted healthy city resolutions; changed zoning policies to allow community gardens and farmers markets to flourish; improved safe routes to schools and campus vending machine standards; and established after-school programs, walking clubs and cooking classes for local residents.
The health department jump starts this engagement by offering $100,000 annually in seed grants to communities that want to join the effort. Among this year’s four grant recipients is a small group of unincorporated mountain towns that applied together through a local non-profit to create new and more attractive places for walking, biking and playing. Although many children ride buses to school, getting safely to and from bus stops is an issue. A Safe Routes to School program addressing the unique needs in these mountain communities could greatly impact the safety of children and drivers.
“City and county leaders have accepted the challenge to improve the county’s health ranking,” Trevino said. “The movement in San Bernardino County for cities to become partners in community health is amazing and inspiring. Thanks to the tremendous political will for creating healthier environments and choices for our residents, I am very hopeful that we will see our ranking improve.”
Example 3: Detroit, MI: Joy-Southfield Neighborhood Unites to Tackle Chronic Disease, Poverty, and Other Barriers to Health
Dr. David Law, executive director of the Joy-Southfield Community Development Corporation | Wayne, Michigan - Snapshot
Detroit, MI, is one of the most racially segregated cities in the country, with high crime, poverty and unemployment; poor public transportation; and vast food deserts that prevent residents from easily accessing healthy foods. In 2011, the County Health Rankings ranked Wayne County—where Detroit is located—81 out of 82 counties in Michigan for health outcomes and dead last for health factors.
But Detroit is also a very resilient city, where people know how to tackle complex challenges. For example, residents of the Joy-Southfield neighborhood have drawn upon the Rankings to help transform their corner of Detroit into a hub of activities aimed at improving community health.
“Once I got over the shock and anger of the County Health Rankings, I said ‘thank you’ because now we have a rational argument for obtaining grants and resources for addressing the root causes of poor health,” said Dr. David Law, executive director of the Joy-Southfield Community Development Corporation.
The Joy-Southfield Community Development Corporation (JSCDC) has operated in the neighborhood since 2001, initially offering sorely needed healthcare services to low-income, uninsured residents. However, after treating a number of common medical problems stemming from high rates of chronic disease, like diabetes and high blood pressure, the organization decided to expand its work to include more programs aimed at preventing community members from getting sick in the first place.
“Poor health in this country isn’t for lack of resources; it’s about investing in prevention,” Law said. “If we do a better job of preventing disease, health system reform will pay for itself. And preventing disease requires more than providing universal access to healthcare - we also need to address social and environmental factors that limit healthy options.”
The JSCDC has developed what Law calls an “ecological approach to promoting health equity,” that addresses each of the four factors measured by the County Health Rankings: health behaviors, clinical care, social and economic factors and physical environment. For example, several community groups and funders have already collaborated to empower youth through mentoring and community garden projects; renovate vacant properties to attract new businesses; improve community safety; provide job training and foreclosure prevention services; and educate the community about prevention and chronic disease management.
Law says the County Health Rankings data allows JSCDC and their numerous collaborators to focus their resources and engage local residents. Since 2010, JSCDC has used the County Health Rankings to leverage more than $500,000 in grant support, while also acquiring more strategic partners.
“Detroiters are not naïve about the complexity and depth of the challenges they face,” Law said. “At the same time, Detroit residents are extremely resilient and resourceful. Systematic and incremental transformation of this community is underway. It may take time, but when it comes to the Rankings, we’ll be ‘movin’ on up.’”
Example 4: PedNet Coalition Works to Improve Health Through Public Transit
Michelle Windmoeller, assistant director of the PedNet Coalition and Roadmaps Grant manager | Boone, Missouri - Snapshot
Home to the University of Missouri, Columbia is considered one of the state’s most livable cities, with a number of educational, economic and cultural opportunities available. It is also the seat of Boone County, which ranked well according to the 2011 County Health Rankings—10th out of 114 counties in Missouri for health outcomes and 2nd for health factors.
But with an eye toward further improvement, a local coalition has started to tackle one of Columbia’s greatest obstacles to health: reliable public transportation. Recent budget cuts have forced the city to raise bus fares and reduce routes, making it harder for many low-income residents to get to work and school, to grocery stores selling healthy foods and to health clinics located across town.
Education, employment, and access to healthy foods and health care services are all important determinants of health. That’s why PedNet—a coalition of community members, business representatives, schools and agencies seeking to increase active living in Columbia—and its partners, including the Central Missouri Community Action and the Columbia/Boone County Department of Public Health and Human Services, are using a Roadmaps to Health Community Grant from the Robert Wood Johnson Foundation to raise public awareness about the economic and health tolls of cutting bus services.
In addition to supporting a campaign that has engaged local university students to advocate for better transportation options, the partnership will use a tool called a health impact assessment to demonstrate to decision makers the connection between expanded public transit options, employment and health. The long-term goal is to create a transit authority with a dedicated tax base that ultimately triples public transportation services in Columbia by 2014, helping all residents lead healthier lives.
“A reliable, efficient public transportation system makes it easier for low-income workers to obtain and keep employment,” said Michelle Windmoeller, assistant director of the PedNet Coalition and Roadmaps Grant manager. “Studies have shown that improvement in employment and economic factors has a positive impact on health.”
Example 5: Rockingham County, North Carolina establishes task force to identify the root causes of its poor health rankings, develops recommendations
Rockingham, North Carolina - Snapshot
Rockingham County, dubbed as North Carolina’s North Star, is nestled at the tip of the Northern Piedmont Triad region and cradled by the foothills of the Blue Ridge Mountains. Though Rockingham County is mostly rural (county size – 572 square miles with a population of approximately 93,063), its communities still offer small-town living balanced with 21st century amenities.
The 2010 County Health Rankings revealed that Rockingham County ranked in the lower half of the state except for the area of physical environment where it ranked 48th out of 100 counties. Rockingham County ranked 71st out of 100 North Carolina counties in health outcomes and 85th out of 100 counties in the area of health factors.
In response to the 2010 County Health Rankings, the Rockingham County Department of Public Health in North Carolina immediately began to identify ways that the community could mobilize to address the issues facing their citizens. On April 26, 2010, the Rockingham County Board of County Commissioners officially appointed members to the Rockingham County Community Health Task Force, including community leaders from education, business, health, human services, as well as elected city and county officials.
The charge to the Health Task Force was to examine the 2010 County Health Rankings, identify the root causes of the poor health rankings, and develop recommendations for community action directed at improving health outcomes and health factors affecting Rockingham County residents.
The Task Force identified several common themes for action: health behaviors, education, jobs, and access to health care. The Task Force then developed recommendations related to these themes to improve the health of Rockingham County and presented a summary report to the Board of County Commissioners. In their report they state that, “the health status of Rockingham County residents is directly impacted by individual behavior, education and economic status, the physical and social environment, and access to quality healthcare. It is the position of the Rockingham County Community Health Task Force that positive improvements in these critical areas will result in the improved health status of county residents.”
Rockingham County is working hard to improve the health of county residents.
A great deal of effort has taken place to respond to the themes and actions recommended. These efforts include but are not limited to the following activities:
- Introduction of new health department website – Rockingham County, North Carolina Department of Public Health: Not only is the new website more user-friendly and aesthetically appealing, it provides a wealth of up-to-date health information and resources. Through the aid of social media, health and wellness information is right at the resident’s fingertips.
- Creation of the Rockingham County Healthcare Alliance: Funding pursuit for a new Federally Qualified Health Center.
- Recipient of the Project Connect -- Communities Supporting Young Families Grant: Increase access to health care for uninsured pregnant or parenting females between the ages of 13-24.
- Recipient of the Susan G. Komen for the Cure Community Grant: Eliminate breast cancer and medical isolation encountered by women who live in rural counties. Increase breast cancer awareness and education for African American women and increase visibility of free services for women who are medically-underserved.
- Rockingham County Healthy Carolinians Partnership: Working with the Cooperative Extension, WIC/Nutrition Program and the Local Food Coalition by providing a farmer’s market located at the health department during the days WIC vouchers are distributed (providing access to local fresh fruits and vegetables for WIC clients); collaborating with the Rockingham County School System to reduce childhood obesity through the In-School Prevention of Obesity & Disease program; working with the Rockingham County Public Libraries by providing county-wide presentations to promote and raise the awareness of healthy lifestyles and behaviors; and offering Zumba fitness sessions to county employees and family members to increase structured weekly physical activity.
- Recently conducted competitiveness survey: Provided through collaboration between Rockingham County Partnership for Economic & Tourism Development and UNC-Kenan-Flagler Business School to evaluate Rockingham County’s ability to compete in the new economy by assessing the strengths, weaknesses, opportunities, and threats inherent in its existing stock of polity, financial, physical, human, cultural, and social capital.
- Community Health Assessment: Rockingham County Department of Public Health is preparing to conduct a Community Health Assessment which will provide a wealth of county health, education, employment and overall needs/resource information.
According to Glenn L. Martin, Rockingham County Health Director, "The County Health Rankings allowed Rockingham County leaders the ability to clearly see and understand the connection between the population’s level of education, economic status and their health status. We learned that while the challenges facing our county were inter-related, so were the solutions."
Tool # 1: County Health Rankings Webinars
County Health Rankings offers numerous webinars on a variety of topics, including “Rankings 101,” “Putting County Health Rankings Into Action,” “Rankings Methodology and New Measures,” “County Health Rankings – Special In-depth Topics,” “County Health Roadmaps,” and “Take Action Cycle Webinar Series.”
Tool # 2: County Health Rankings and Roadmaps What Works for Health
What Works for Health is an easy-to-use, searchable menu of policies and programs focusing on factors that make communities healthier places to live, learn, work and play. You can choose a health factor of interest (i.e. tobacco use, employment, access to health care, environmental quality) and browse through the evidence ratings for particular programs, policies, or system changes that address the particular health factor of interest.
Together, the County Health Rankings & Roadmaps and the new What Works for Health give you a profile of your county’s health, guidance to take action, and information on evidence-informed strategies that can make your community a healthier place.
```html
“A compassionate city is an uncomfortable city! A city that is uncomfortable when anyone is homeless or hungry. Uncomfortable if every child isn’t loved and given rich opportunities to grow and thrive. Uncomfortable when as a community we don’t treat our neighbors as we would wish to be treated.”
― Karen Armstrong, Founder of the global movement, The Charter for Compassion
A GLOBAL MOVEMENT FOR COMPASSION
What Difference Can Compassion Make?
Motivated by the ancient and universal “golden rule” to treat others as you would like to be treated, communities of people across the globe have committed to making compassion a driving force with a measurable impact on community life and on the well-being of all members of a community. The concern of people in these communities is driven by the idea that beneath the conflict, inequity, and indifference of our world societies, there runs a deep river of compassion, a vast aquifer of loving kindness waiting to be tapped, yearning to be released into action that will alleviate suffering wherever it exists. In addition, a growing body of research has examined the role of compassion in building and maintaining healthy, resilient, and caring enterprises, institutions, and communities.
Since Karen Armstrong received the TED Prize in 2008 and worked with other influential scholars and leaders to develop the Charter for Compassion, the document has become central to a global movement and an organization, the Charter for Compassion. Since the launch, the Charter has been building a worldwide network of individuals, partners, and communities of every size who share a kinship inspired by the idea that compassionate actions—the actions that are the result of our deep concern for our world and all its inhabitants—are not only possible but crucial to the well-being of our species, our environment, and the planet.
The Charter for Compassion envisions a richly diverse “network of networks,” with people from many parts of community life who will bring compassion to everything they do, and who will take responsibility for igniting the compassion of the general community to care for each other and for the well-being of all members of the community from birth through childhood, adolescence, and adulthood to old age and death.
What Is a Compassionate Community?
Human beings are social animals. We live and work and socialize together in communities that exist in diverse cultures and climates throughout the Earth. Within each of these communities, from Mongolia to Mogadishu to Managua to Minnesota, human beings experience compassion for others, relieving pain and suffering for their families, for their neighbors, for their communities. But the structure of modern society—of nation states and mega-cities and a world population of billions—can often thwart and distort this natural desire to be compassionate. The sense of disconnection can become so pervasive that unkindness, indifference, and selfishness may appear as the norm; compassion, kindness, and caring as the outliers.
In a Compassionate Community, the needs of the inhabitants of that community are recognized and taken seriously, the well-being of the entire community is a priority, and all people and living things are treated with respect. More simply, in a Compassionate Community, people are motivated by compassion to take responsibility for and care for each other. A community where compassion is fully alive can be a thriving, resilient community whose members are moved by empathy to take compassionate action, are able to confront crises with innovative solutions, are confident in navigating changes in the economy and the environment, and are resilient enough to respond to and recover from disasters and other major challenges.
Although the early work of the Charter was focused on building a network of cities, it soon became evident that communities both larger and smaller than cities wanted to join the global movement in which compassion is at the heart of a community’s activities. The Charter’s network of Compassionate Communities has included cities, towns, villages, neighborhoods, islands, states, provinces, counties, regions, and countries.
No single community in the world is a Compassionate Community in any abstract or formal sense, just as no community is devoid of compassion. Each community will find its own path to establishing compassion as a driving and motivating force, and each will conduct its own evaluation of what is “uncomfortable” in that community’s unique culture—that is, those issues that cause pain and suffering to members of the community. For one community that discomfort may be youth violence or suicide among young people. Another community may discover that a portion of its community—perhaps immigrants, people experiencing homelessness, or LGBTQ+ community members—has been marginalized, harassed, or even physically threatened. Yet another community may be concerned about the needs of children living or working on the streets, including children who have lost parents or caregivers.
The Charter’s Compassionate Communities program is not a certificate program that simply offers a seal of approval, nor does it subscribe to a single definition of a Compassionate Community. Instead, the Charter invites communities of all sizes to bring compassion to life in practical, specific ways through compassion-driven actions—in neighborhoods, businesses, schools and colleges, health care, the arts, local government, environmental work, community organizations, faith communities, and other settings.
What Are the Steps for Creating a Compassionate Community?
Any individual, group, or organization that recognizes the need for greater compassion in a community is encouraged to begin the process for creating a Compassionate Community. While the Charter does not prescribe any one path, it does recommend a collaborative process that brings together people with different backgrounds, experiences, roles, and perspectives so that the voices within the community can be heard and significant issues can be addressed.
Compassionate Communities have often begun their work by identifying the issues that are troubling the community and need to be addressed through compassionate action. For example, a community may discover a significant issue related to social justice—for women, for immigrants, or for another group experiencing marginalization. Other communities may want to address issues of substance use and related harms, gang violence, inequitable access to health care, or the effects of environmental racism. Others may decide to work to empower young people or to educate their communities about the need for compassion in addressing environmental issues.
A FRAMEWORK FOR GETTING STARTED
The Charter for Compassion has developed a four-part model or framework for building a Compassionate Community. In many ways, the model is similar to other models for organizing a community-building effort. The objectives of various efforts are usually related to the well-being of the community, e.g., improved health care, decreased crime, increased assets for youth, economic improvement, and increased resilience. The Charter, too, is interested in the well-being of communities and applauds all of these efforts since many of them do indeed address pain and suffering within the community.
The difference in the Charter’s model may be understood as a difference in breadth of perspective and intention. Those working to create Compassionate Communities are moved through empathy to compassionate action—a desire to address pain and suffering wherever it occurs—not only in their own communities but in all communities and for all living beings everywhere. That perspective is perhaps best articulated by His Holiness the Dalai Lama:
“When we are motivated by compassion and wisdom, the results of our actions benefit everyone, not just our individual selves or some immediate convenience. When we are able to recognize and forgive ignorant actions of the past, we gain strength to constructively solve the problems of the present.”
― Dalai Lama XIV
Grounded in the concepts of the Charter for Compassion, this model is intended to guide your process, and to provide a place to begin. It can and should be adapted to the unique circumstances of any community that seeks to become a Compassionate Community. Each of the four broad phases includes more specific steps along with stories and examples that you may find helpful and even inspiring. Depending on the community, its particular issues, and available resources, this process may take one or more years. There is no quick fix to transforming a neighborhood, city, town, or region.
The Charter currently describes four broad phases:
The current framework includes ten suggested steps across those four phases. The steps are meant as a guide, not as a rigid formula.

PHASE 1: DISCOVER
The first phase involves discovery and assessment. What is the current situation related to compassion, and what assets can we draw on as we work toward a more compassionate community?
Step 1: Bring together people who are open to identifying “discomforts” in your community—those issues that are causing pain and suffering to individuals or groups or the entire community—which can be addressed and relieved through compassionate action.
Perhaps you are part of your community’s local government, or you may work in social services or health care, and you have wished that something more could be done to resolve the difficulties facing people in your community—for example, people experiencing homelessness, isolated or depressed older adults, an immigrant population, or youth who are pressured to be part of a gang culture.
Maybe you work with the community’s youth as an educator, a counselor, or in recreational services, and you have recognized both the promise of youth as well as the difficulties they face in our rapidly changing world. Or, you may be a community member who has deep concerns about the safety, the health, or the emotional well-being of other groups of community members—people with disabilities, orphaned or abandoned children, people with mental health conditions, or racial or ethnic groups who are confronted by discrimination.
You may be concerned about the transport of hazardous materials through your area, or about increasing air pollution or the lack of clean water in your community. Or you may be an observer who has recognized other issues that cause suffering in your community. Perhaps you have been motivated by your concern to identify possible ways to relieve suffering—quality, affordable childcare; anti-bullying programs in schools; or compassionate care for veterans in your city or town or neighborhood.
All of these issues are what author Karen Armstrong means when she talks about those issues that are “uncomfortable” for a community and therefore in need of compassionate action in order to provide for the well-being of all community members.
Some Examples of Issues and Actions in Compassionate Communities
- In one example, when Rev. Shayna Lester, a volunteer chaplain at the California Institution for Women, heard about the Compassion Games, she knew she had to bring the idea to the incarcerated women. Immediately the women responded and self-organized. They appointed leadership, created “games,” and agreed on how they would account for their points. They coined the term “Compassionistas” and came up with games like: walk away from gossip; do a kind deed for another; let another go ahead of you in line; share magazines, food, and personal items.
- The Forgiveness Project, a UK-based charity, uses storytelling to explore forgiveness, reconciliation, restorative practices, and responses to crime and violence through the experiences of people who have been harmed and people who have caused harm.
One useful Charter resource for beginning this kind of exploration is its material on Determining Issues. Other helpful resources from the Community Tool Box are listed below at the end of Phase One.
Step 2: Find out what is already being done, or has been done, to address issues in your community, learn what has worked and not worked, and recognize and acknowledge those successes.
Even if you, as an individual, have already identified the major challenges and “discomforts” of your community, your initiative will benefit from some investigative work alongside others who care about the community. Discover who else is working to improve your community, and working to provide a place of well-being. Recognize and acknowledge that work, and invite those people to join you in creating a Compassionate Community. Key words here are: recognizing and appreciating work that has been and is being done.
The Dutch Compassion Movement in The Netherlands provides a wonderful historical example and model related to this step:
In the Dutch Compassion Movement, city and community initiatives and partners were organized under a charity trust originally called Handvest voor Compassie. In 2013, the organization decided to design a project to find out how various groups in the greater Amsterdam area were going about handling complex social issues. They wanted to produce a book to showcase how local problems were being handled and to provide the impetus for other groups to follow suit, locally and throughout the country.
In early 2014, the Amsterdam project resulted in the publication of De Ander (meaning “The Other”), a book that recorded more than 50 stories about how social service organizations were dealing with complex issues, including challenges arising as Amsterdam became home to people from increasingly diverse backgrounds.
De Ander presents heart-warming stories of conflict addressed between families, neighbors, and among ethnic groups. For example, it showcases the story of a group of medical students working to reform health care delivery processes, an education organization working to teach mediation skills to young people, and groups helping children of immigrants learn about their families’ cultures while also navigating life between cultures.
Step 3: Invite people to join you in assessing your community. Include community leaders as well as those informal leaders of other community constituencies who can give voice to the needs, strengths, and experiences of the community.
During Phase One of creating a Compassionate Community, it may be helpful to bring together community leaders and influencers to discover, assess, and evaluate the community’s existing strengths as well as those challenges that need to be addressed. You may find people in formal leadership positions—for example, in local government or health care or education—who can make valuable contributions to your initiative or may already be addressing the issues you have identified. You may also invite more informal leaders, for example, those people who have influence in their neighborhoods, faith groups, cultural communities, or other community networks.
Together, you can discuss what it means for a community to take care of all community members—and to relieve pain and suffering wherever it exists in your community. You may find it useful to provide presentations that inform people about the community’s current opportunities and challenges. In a collaborative and inclusive discussion, you will gain a clearer picture of what is good about your community and where compassionate action is working—those will be strengths to build on—and together you can discover the issues that are causing pain and suffering to some individuals or groups—those are the places where the community is vulnerable and in need of compassionate action.
Each community will find its own way to explore how compassion can bring well-being to all community members. As one example, Pakistani journalist Naween Mangi started the Ali Hasan Mangi Memorial Trust in memory of her grandfather, whom she describes as “compulsively compassionate.” The Trust worked with residents of Khairo Dero, a village in southern Pakistan, on such needs as clean water, sanitation, housing, education, income-generating opportunities, and health care.
As the work developed, Mangi and others sought to make compassion a part of village life and a practice rather than simply an idea. The community began holding regular activities exploring how to live compassionately. Some of the activities included:
- Readings from the Charter for Compassion and group discussions.
- Readings from Karen Armstrong’s Letter to Pakistan and Twelve Steps to a Compassionate Life.
- Short plays developed and performed by village children on the theme of compassion.
- Drawing competitions about compassion.
- A “Compassion Counter,” where adults and children could record their acts of compassion.
- “Compassionate Living Days,” marked by cultural performances, plays, and speeches about how community members could treat one another as they themselves would like to be treated.
RESOURCES
Determining Issues
Partners and members of the Charter for Compassion have developed a Determining Issues resource that communities can use to reflect on and discuss a broad range of community concerns. The current resource includes 21 topics with related questions. The list and questions may not be exhaustive, but they can provide a good place to begin. The resource can help you:
- Discover the community’s strengths—which can be celebrated and serve as a foundation for further building a Compassionate Community.
- Discover the “discomforts and fears”—those challenges and issues that bring pain and suffering to individuals or groups in the community.
- Assist in understanding the big picture in your community so your initiative can focus on the most significant issues for compassionate action.
Community Tool Box Resources -- for Discover
Toolkit 2: Assessing Community Needs and Resources
Chapter 3: Assessing Community Needs and Resources
- Section 1. Developing a Plan for Assessing Local Needs and Resources
- Section 2. Understanding and Describing the Community
- Section 3. Conducting Public Forums and Listening Sessions
- Section 4. Collecting Information About the Problem
- Section 6: Conducting Focus Groups
- Section 8: Identifying Community Assets and Resources
- Section 10: Conducting Concerns Surveys
- Section 12: Conducting Interviews
- Section 20: Implementing Photovoice In Your Community
Community Tool Box Coalition-Building Resources
- Toolkit: Creating and Maintaining Partnerships
- Chapter 7, Section 2: Promoting Participation Among Diverse Groups
- Chapter 7, Section 6: Involving Key Influentials in the Initiative
- Chapter 7, Section 8: Identifying and Analyzing Stakeholders and Their Interests
- Chapter 7, Section 7: Involving People Most Affected by the Problem
PHASE 2: COMMIT
After a period of discovery and assessment, it is necessary to focus efforts and ensure commitment.
Step 4: Analyze challenges and opportunities from information gathered during the Discover phase. Then choose an initial focus, perhaps one to four of the most significant areas that are of importance to the community and that could benefit by being addressed through compassionate action.
Your group may easily agree on the significant challenges facing your community. But just as likely, you may find some disagreement about what issues you should focus on first. If you have an inclusive group, and if you’ve done your homework in Phase One, your group will have a pretty clear picture of what is going on in your community. You should know not only what the problems are but also what is currently being done to address those problems. Take the time to consider and evaluate the impact of each challenge on the community and to develop information that will help you to prioritize action plans.
Group discussion may include questions about where and how your group can make the most positive impact—alleviating pain and suffering—given your current resources. For example, once the group has a list of what it believes to be significant issues, it might ask the following questions about each of the issues, to help the group decide what is most important now and to plan and prioritize next steps.
- What is the most significant challenge facing our community?
- How do we know this is a significant challenge?
- Who is suffering as long as this issue is not resolved?
- Who is currently helping to alleviate this issue?
- What do we know about the causes of this issue?
- What can we learn from other communities that have faced this challenge?
- How might we engage others who have been working with this issue to help inform our own work?
- What resources—time, people, funding, partnerships—would we need to address this challenge?
- How can we ensure that our intentions and actions are driven by compassion?
- What difference can we make?
- What impact will our actions have on our broader community?
Step 5: Based upon prioritized choices, create a plan to move forward including specific short-term and long-term objectives, action plans, and anticipated outcomes. Plan purposeful, measurable actions toward fulfilling your objectives with designated responsibilities and appropriate time frames.
Below, in the Resources section, you will find some useful ideas and guidelines for planning and for deciding on what to do next. These guidelines can help you decide, for example, whether to work through existing channels to affect policy, work to gain wide community awareness and support, focus on funding to enhance current programs, and/or create and launch a new initiative of your own.
Your group may decide to lend its support to an existing group that is addressing some aspect of a particular problem instead of creating a new program. For example, if homelessness is viewed as a significant challenge and an interfaith group or an NGO currently provides meals to people experiencing homelessness on a regular basis, your group may want to help enlist volunteers, increase food donations, or begin a community garden to assist the group in its efforts. Or you may choose to work with the existing group by providing some related benefit—job counseling, clothing, childcare, mental health services, housing assistance, or other support.
When you are motivated by compassion—a heartfelt empathy for those who are suffering that moves you to care about and take action for the well-being of all members of your community—you become part of the growing global compassion movement. Whether you are an individual or part of a group organized to create a Compassionate Community, you can connect with others through the Charter’s international network.
As your compassionate action group grows, you may want to seek the support of organizations in your community that also care about the well-being of the community. Building partnerships can expand and strengthen your initiative, extend ownership, increase perspective, and bring new information, funding, in-kind resources, relationships, and other support to your work.
The Charter’s global work, once organized through a larger set of sectors, is now organized around seven interdependent pillars:
- Arts, Music, + Gratitude
- Education + Wisdom
- Environmental Stewardship + Respect
- Health + Compassion
- Justice + Integrity
- Play, Courage, + Innovation
- Spirituality, Love, + Hope
Step 6: Make a formal and public commitment to the concepts contained in the Charter for Compassion—by proclamation, resolution, a completed action plan, or another form appropriate to your community.
The Charter for Compassion does not prescribe what your group should do and how to do it. It does not provide a simple seal of approval or dictate one path for every community. Instead, it provides encouragement, information, resources, and opportunities to connect with the global movement for compassion. When your group has completed an assessment and created an action plan, it may be time to make a more formal and public commitment.
For example, your community may make a proclamation or a resolution within your local government, or organizations within the community may make their own formal commitments. Then share what you are doing so that other communities around the globe can learn from you—and so that you can learn from them.
RESOURCES
Community Tool Box Resources -- for Commit
- Toolkit 3: Analyzing Problems and Goals
- Toolkit 5: Developing Strategic and Action Plans
- Chapter 8: Developing a Strategic Plan
- Toolkit 7: Developing an Intervention
- Toolkit 8: Increasing Participation and Membership
PHASE 3: BUILD
After establishing a focus and commitment, the next phase involves building momentum and putting compassionate action into practice to create a more compassionate community.
Step 7: Build momentum by involving other community members, linking to community events, and inviting nearby communities to participate. Educate the broader community about what it means to become a Compassionate Community, and acknowledge the acts of compassion that are already working within your community.
By now, you have established a core leadership team that is diverse and inclusive. You have assessed your community’s strengths and vulnerabilities in order to determine what challenges need to be addressed first. You have made a plan for putting compassion into action, focusing on one or more issues that are causing pain or suffering to some group of people within your community.
Now it’s time to bring in as many community members as possible—let them know your plan, gain their support, and build momentum toward the well-being of the entire community. Celebrate and communicate the compassion that is the wellspring of your plans!
Depending on the size and resources of your community, you will discover various channels for communicating your plan and enthusiasm to the community. For example, you might launch your effort at a community event—which might be combined with a festival, concert, gathering, or some other celebration.
You could contact leaders in various parts of your community, or those in nearby communities, to build a base of support. Offer to provide presentations for community organizations and groups that may be interested in joining in to address the issue you have identified. If your plan includes the need for funds, this may be the time to gain the support of local businesses, community organizations, faith groups, foundations, and individuals who recognize the need for action.
And then it’s time to get to work, to put your plans into action. It may be helpful at times to “pilot” a particular activity on a small scale to understand whether you are meeting your objectives. Setting both short-term and long-term objectives—and continually monitoring and evaluating them—will also be helpful, as that will allow you to make adjustments, remain flexible, and create new strategies when necessary.
Step 8: Communicate within the community on a regular basis—through meetings, emails, articles, social media, presentations, and whatever other means are appropriate—to keep people informed and energized.
Maintaining enthusiasm and energy is important to the success of your project. Regular meetings, emails, articles in local media, postings on social media, presentations, and whatever other means you have to communicate your actions to the community can help keep the work visible and bring further support to your compassionate actions.
Communication should flow in both directions. Keep people informed, but also continue to listen. Community members should have opportunities to ask questions, offer ideas, raise concerns, and tell you what they are seeing and experiencing as the initiative moves forward.
Step 9: Reach out to share globally—for example, by building relationships with a community in another part of the country or world.
Karen Armstrong has spoken of her hope that Compassionate Cities and Communities can help break down the divisions of a polarized world by building relationships across geographic, political, cultural, and other boundaries.
At some point, your community may be ready to reach out its hands with compassion to another community—perhaps a city or town or neighborhood that is not far from you, has similar challenges, and could benefit from a partnership with you. Or you may be inspired to reach across the planet to people living in a city or town or neighborhood in another country or on another continent to find a mutually beneficial partnership founded on the concept of compassion for everyone, everywhere in the world.
These relationships need not involve one community teaching another how to be compassionate. They can be relationships of mutual exchange: communities sharing problems, successes, stories, resources, mistakes, and ideas, and helping one another continue the work.
RESOURCES
Community Tool Box Resources -- for Build
- Toolkit 8: Increasing Participation and Membership
- Chapter 4: Getting Issues on the Public Agenda
- Chapter 6: Promoting Interest in Community Issues
- Chapter 42, Section 1: Developing a Plan for Financial Sustainability
- Chapter 42, Section 3: Developing a Committee to Help with Financial Sustainability
- Chapter 46: Planning for Long-Term Institutionalization
PHASE 4: EVALUATE
As the movement unfolds, it will be important to evaluate what is happening in the community as a result and to plan for adjustments. It is also critical to plan for sustainability—a compassionate community is not built in a day.
Step 10: Monitor and measure your progress, and continue planning. Celebrate successes; learn from unsuccessful efforts and adjust subsequent actions accordingly. Then share your experiences and your stories with the Charter community and with others who can learn from what you have done.
Remember that the Charter website includes resources to assist you—stories of other communities’ efforts and successes, readings and learning opportunities about compassionate action, and connections to other communities and organizations that may lend support to your efforts. Evaluation is an essential and ongoing aspect of your work.
In addition, in the Resources section below, you will find several ideas for developing an evaluation plan and for evaluating your initiative, which can be found in the Community Tool Box.
Maintaining enthusiasm and energy is also important to the success and sustainability of your project. Continue communicating with the community as you evaluate your work. Regular meetings, emails, articles in local media, social media, presentations, reports, and whatever other means you have to communicate your actions can help sustain the work and bring further support to your compassionate actions.
At this point, you and those who have collaborated with you may have made a positive difference in your community. You have worked hard to develop a spirit of compassion within the community, and you have established processes or programs intended to relieve suffering. You have evaluated the work to learn how effective it has been, and you have adjusted and expanded your plans to keep working toward your vision of a Compassionate Community. Perhaps you have even reached out to share your experiences with other communities that want to build Compassionate Communities. Congratulations!
Now you will need to take some time to think about how to sustain the spirit of compassion that has stirred your community to take action, as well as many of the actions themselves. Your aim here should be to ensure that your work will continue to be helpful to other individuals and groups. You may decide that a pilot program that was successful should be expanded and carried forward. And often, you may wish to find or create a local structure—a more permanent group or organization—so that the substance of your work can continue.
For example, you may have established a program to provide quality, affordable childcare for families who would not otherwise have access to such care. Your evaluation and analysis have shown that both children and their families have benefited. You develop a plan to expand the program. So that may mean that you have to seek greater funding—from individuals, government, foundations, or other organizations. It may happen that your childcare program becomes part of an existing organization or system that can help sustain it.
In addition to financial stability, you may also want to consider how best to communicate the outcomes of your work—providing data and statistics but also giving voice to gratitude and the sense of “elevation” that can be felt by people who experience compassionate action and by those who have been moved to perform compassionate acts.
And finally, you will know that the work you have done and that you continue to do is not an isolated act, but rather a flowing stream which flows into the ever-increasing rivers of compassion, which in turn become a sea of compassion—for all living things and for our planet.
RESOURCES
Community Tool Box Resources -- for Evaluation
- Choosing Questions and Planning the Evaluation
- Developing a Framework or Model of Change
- Developing an Evaluation Plan
- Evaluating the Initiative
- Some Methods for Evaluating Comprehensive Community Initiatives
Community Tool Box Resources -- for Communication
- Developing a Plan for Communication
- Promoting Interest in Community Issues
- Preparing Press Releases
- Preparing Guest Columns and Editorials
Community Tool Box Resources -- for Sustainability
- Developing a Plan for Financial Sustainability
- Developing a Committee to Help with Financial Sustainability
- Not enough money to sustain the program or initiative.
- Planning for Long-Term Institutionalization
- Sustaining the Work or Initiative
```
Contributor
Barbara A. Kerr
Resources
Online Resources
Berger, Rony. Building a Resilient and Compassionate Community.
Chapter 13: Stress and Coping in the "Introduction to Community Psychology" details stress, its different forms, coping, coping strategies and styles, and how individuals and communities become resilient.
Doty, James R. Science and Compassion.
Print Resources
Barber, B. R., (2014). If Mayors Ruled the World: Dysfunctional Nations, Rising Cities.
Bullard, R. D., (2007). Growing Smarter: Achieving Livable Communities, Environmental Justice and Regional Equity (The MIT Press).
Glaeser, E., ( 2012). Triumph of the City.
Gyatso, T., (2003). His Holiness the Dalai Lama. The Compassionate Life. Somerville, MA: Wisdom Publications.
Hanleybrown, Fy, John K., & Mark K., (January 26 2012) .Channeling Change: Making Collective Impact Work, Stanford Social Innovation, #20.
Keltner, D., Jason M., & Jeremy A.,S. (2010). The Compassionate Instinct: The Science of Human Goodness (W.W. Norton and Company).
Minkler, M. (1997). Community Organizing (Rutgers University Press, 1 edition).
Staples, L. (2004). Roots to Power: A Manual for Grassroots Organizing (Praeger, 2 edition).
Szakos, K. L., (2007). We Make Change: Community Organizers Talk About What They Do and Why (Vanderbilt University Press).
TED Books. (2013). City 2.1: The Habitat of the Future and How to Get There.
```html
What broader factors determine whether people in a community are healthy? What accounts for differences in health outcomes among people in different groups, communities, and countries?
The health of a community – and its people – is dependent on a number of social, political, economic, and environmental conditions.
Social determinants of health refer to the conditions in which people are born, grow, live, work, and age, as well as their access to power, money, and resources. These conditions can support or limit the health and well-being of a community or population. Differences in these conditions can contribute to differences in health outcomes across groups. For instance, people in racial and ethnic groups that experience discrimination may face poorer health when they are more:
- exposed to hazards through inadequate housing or unsafe working conditions
- affected by limited access to quality education and other resources
- likely to experience adverse consequences because of limited access to adequate services
In 2008, the Commission on Social Determinants of Health published its final report, Closing the Gap: Health Equity Through Action on the Social Determinants of Health. The report reminds us: “Social justice is a matter of life and death. It affects the way people live, their consequent chance of illness, and their risk of premature death… Achieving health equity within a generation is achievable, it is the right thing to do, and now is the right time to do it.”
Throughout the world, there are efforts to address social determinants of health. For instance, in the United States, Healthy People 2030 includes an overarching goal to create social, physical, and economic environments that support the full potential for health and well-being for all. Globally, the Rio Political Declaration on Social Determinants of Health (2011) reaffirmed the commitment to take action on social determinants of health. Key action areas include improving governance, community participation, attention to health inequities, and monitoring progress.
To achieve this vision will require a whole community approach in which different sectors—health, education, housing, labor, justice, transportation, agriculture, and the environment—all work together to assure conditions for health. To be successful, this approach requires changes at the levels of individuals, relationships, communities, and broader systems. It requires environmental, economic, and policy strategies along with individual behavioral change and health services. The approach also requires developing partnerships among different groups including public health, community organizations, education, government, business, and civil society.
Health equity and health disparities. A basic principle of public health is that all people have a right to health. Health disparities are measurable differences in health outcomes among groups. Many disparities affect groups that have experienced marginalization or exclusion because of socioeconomic status, race or ethnicity, sexual orientation, gender, disability, geographic location, or some combination of these. People in these groups may also have less access to the conditions that support health and well-being; for instance, nutritious food, quality housing, quality education, safe neighborhoods, and freedom from racism and other forms of discrimination. When differences in health are unfair, avoidable, or remediable and are shaped by the unequal distribution of these conditions, they are health inequities.
Health inequities are unfair and avoidable or remediable differences in health among groups. Health equity, then, means creating conditions in which everyone has a fair opportunity to attain their full potential for health and well-being. Or, as the Collective Impact Forum states, adapted from Urban Strategies Council, "Equity is fairness and justice achieved through systematically assessing disparities in opportunities, outcomes, and representation and redressing [those] disparities through targeted actions."
Overwhelmed by the scale of the Sustainable Development Goals? Check out the United Nations’ Lazy Person’s Guide to Saving the World for some doable steps you can take to make an impact.

What do we mean by developing an initiative to address social determinants of health?
Many communities embark on initiatives aimed at improving the health of community members. Generally, they are intended to change individual behavior by offering opportunities and information that make it easier for people to quit smoking, get more exercise, eat healthier foods, or obtain health screenings for various diseases. Although these efforts can certainly lead to good outcomes, they often don’t address the social determinants that are at least partially responsible for positive or negative health conditions.
In this section, we’re presenting ideas adapted from the 2008 U.S. Centers for Disease Control and Prevention resource Promoting Health Equity: A Resource to Help Communities Address Social Determinants of Health. The model promotes inclusiveness, community participation, careful assessment and planning, implementation, evaluation, and maintenance of effort. In other words, it is in many ways similar to the other models for community health and development in this chapter. The major difference is that it suggests how to influence health and health-related issues by addressing their social determinants. Although the CDC resource is an older one, its seven-phase planning process remains useful as a way to organize community action; current terminology and examples should be interpreted in light of more recent public health guidance.
This model also aims to promote health equity, since that is the ultimate goal. In most communities and most societies, some people have better access to health care and health resources and live in healthier environments than others. As a result, they are generally healthier and longer-lived than those with fewer advantages. In many cases, these differences are caused, at least partially, by social conditions – income, education, discrimination, politics, and geography – rather than by genes or luck.
When conditions for health are unequal, these are health inequalities. When these conditions are unjustly distributed, the result is health inequity. By effectively addressing the social determinants of health, we can create a healthier community, and improve the quality of life for all.
Why develop a social determinants of health initiative in your community?
- Such initiatives use a participatory process that involves all sectors of the community. Involvement by individuals, groups, and organizations from all backgrounds and sectors of the community leads to community ownership. When affected groups are involved in the planning, implementation, and evaluation, the effort can best meet the needs of the community.
- Aiming at social determinants gets at the root causes of inequity. Social determinants, such as income inequality, underlie many different problems in health and development. You can address their results, but unless you address the determinants directly, your effort isn’t likely to have long-term effects.
- A social determinants effort addresses social change through the development of greater equity. Greater equity can support longer, healthier lives and stronger social ties, while reducing unfair differences in the conditions that shape health.
- It helps create community partnerships that can endure, and be directed to other issues as well. The base of community collaboration and leadership that’s built through this effort can carry over to build community resources and address other concerns.
- A social determinants effort uses the knowledge of those most affected, as well as that of others in the community. It takes advantage of the accumulated wisdom of the community.
- Such an effort educates the community about health inequity and its consequences. Many community members, even some in the partnership that coordinates the effort, may not be aware of the level and consequences of health inequity in the community. By drawing attention to and explaining these issues, the initiative can help the community understand and deal with them whenever and in whatever forms they arise.
- As a result, a social determinants initiative can help to create a fairer, more equitable community that deals with discrimination and other equity issues. Once the community understands social determinants and the results of inequity, and sees how dealing with these factors can improve the quality of life, it may be more willing to address persistent barriers to equity, such as discrimination, that it has been unable or unwilling to address before.
- A participatory effort can build new community leadership. By including in the partnership people who might not normally be in such a position, the effort can encourage new leadership, and prepare the community to continue efforts into the next generation.
How to take action to address social determinants of health
The link between social determinants of health—including social, economic, environmental, and structural conditions—and health outcomes is widely recognized in public health. It is also well understood that the inequitable distribution of these conditions across populations is a major contributor to persistent health disparities and inequities.
So... you understand social determinants of health (SDOH) and their relationship to health outcomes and health equity. And you see ways that social determinants can be changed in your community to improve health and the quality of life for everyone. How do you go about making those changes?
What follows is step-by-step guidance for implementing an initiative to do just that. Be aware that these steps are only a guideline. All communities are different, and what works well in one might not work in another. Although these steps are arranged in the order they might logically be taken, in some cases it might make more sense to change the order, or to act on more than one step at a time.
Some parts of the guideline are important in all cases, however. The formation of a partnership that incorporates people from all sectors of the community – particularly those who experience health inequities and other forms of inequity – is crucial if the process is to lead to long-term social change. Focusing on SDOH, as well as careful planning and evaluation are also necessary.
Perhaps most important is maintaining and building on successes. Too many initiatives founder after their initial success because everyone thinks the problem is solved, and that the changes will ride on their own momentum indefinitely. A neglected house will eventually fall down, and a neglected initiative will do the same, only much more quickly. With that caution in mind, let’s get to work.
The figure below, adapted from the 2008 CDC resource, outlines seven phases and related steps in addressing social determinants of health in your community. By clicking on the phase, you can skip to ideas and resources for implementing related steps.
Figure: CDC Phases of a Social Determinants of Health Initiative
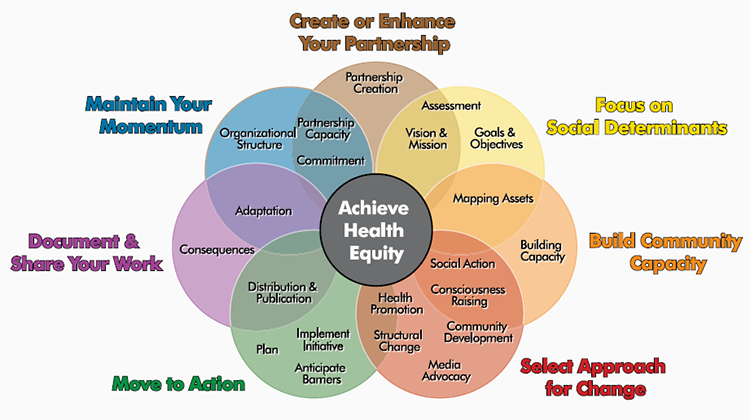
Phase 1: Create or Enhance Your Partnership
The foundation for a successful initiative is the development of a multi-sector partnership. This alliance is responsible for conceiving, planning, implementing, evaluating, and maintaining the effort over time. A partnership is an intentional relationship between two or more parties (individuals, groups, or organizations) committed to pursuing an agenda or goal of mutual benefit. It is essential to build partnerships to address social determinants of health because no one group—whether health care providers, public health practitioners, community organizations, or community members—can accomplish all the tasks required to change the social, economic, environmental, and structural conditions that affect health. Partnerships are necessary to:
- Increase understanding of a community’s needs and assets.
- Improve public policies and health systems.
- Engage new issues without having sole responsibility for addressing them.
- Develop widespread public support for issues or actions.
- Share or develop the necessary resources for taking action and problem solving.
- Minimize duplication of effort and services.
- Recruit participants from diverse backgrounds and with diverse experiences.
- Promote community-wide change through multiple approaches.
- Gain community members’ trust in a broad-based coalition of partners.
The first step toward creating a successful partnership is to assemble a group of interested community members and organizations to discuss ideas and concerns for the community. You may choose to work within existing partnerships that have helpful knowledge and experience. Existing groups, however, may not address the social determinants of health or include people or organizations from the community who can inform initiatives to address social determinants. Therefore, you might wish to invite others to join your efforts, particularly those who have insight into or experience harm from the political, social, economic, and environmental conditions in your community.
Listening to the voices of people and organizations in the community who experience inequitable distribution of resources can help to build a strong partnership to address social determinants. This can be strengthened by ties to diverse groups in your community and involvement of relevant sectors of your community (e.g., government, education, business, public services, faith, funding agencies). To identify who should be involved, it helps to consider how your community is defined.
Define your community. A community is essentially a group of people who have something in common and who see themselves, or are seen by others, as part of that group. It’s most often thought of as a geographic area – a neighborhood, a town, a city, or a village, for example. Shared experience can also define a community including:
- Socioeconomic status or class. This can shape people’s access to resources, opportunities, and influence in their environment.
- Employment, trade or profession. Some jobs may expose workers to unhealthy conditions that lead to community health issues.
- Ethnicity or race. Patterns of discrimination are often directed toward particular groups.
- Culture. This may be related to geography, racial or ethnic heritage, or religion. It involves a particular way of seeing the world, and, often, particular practices that go with that view.
- Groups that may experience social exclusion or unequal access to resources and opportunity, such as women in settings where gender inequity limits access or participation.
Once you’ve clarified the physical and/or social boundaries of the community you’re working with, it will be easier to determine who from that community needs to be involved.
Determine who should be included in the partnership. Start with those who are obvious and/or who have the largest networks, and ask them to help you identify others. Be sure that your initial group is diverse enough, and that you have enough knowledge of the community, so that important perspectives are not left out. Some people you ask may choose not to participate, and some groups may go unrepresented no matter how hard you try, but it’s important to make a serious and sincere effort to involve everyone.
Those who might be included, depending on the initiative, are:
- People directly affected by health inequities and the social determinants that contribute to them.
- Local government officials, including those concerned with health and well-being.
- Health workers and organizations (e.g., those in hospitals, clinics).
- Human service organizations, especially those that serve the population or community most directly affected.
- The business community.
- Environmental groups or agencies.
- Community advocates and advocacy organizations.
- Educators at all levels.
- Faith communities.
- Funding agencies and foundations.
- Interested individuals, particularly those who might have relevant experience, skills, or relationships.
The people and groups identified should reflect the diversity of the community, including gender, race, ethnicity, age, income, sexual orientation, and other dimensions of social exclusion.
Contact potential partners and invite them to participate. Once you’ve identified some of the individuals and groups needed to make up the partnership, you have to recruit them. In general, the best way to do this is through personal outreach. For individuals, that may mean sharing a meal together, meeting face to face, talking by phone or video, or meeting with several people in a group. For larger groups and organizations, talking to a regular gathering of the board and/or staff might be the best approach, perhaps after meeting with the director or board chair. As you bring people on board, you can ask them to recruit others that they know.
In general, people are more likely to respond to those whom they know and trust. If you can engage a few particularly respected individuals, others will become interested because they trust those people’s judgment. Once you’ve signed up a core group, it’s more likely that the rest of the members will fall into place.
Choose a facilitator. Your partnership will need someone to run meetings, help to resolve conflicts, and generally hold things together. This could be a partnership member or, if the partnership has the resources and the need, someone hired from outside the community. In either case, it should probably be someone who is seen as neutral (having no bias toward or against one group or another), fair, ethical, open to new ideas, and flexible. The facilitator might be only that, or might be seen, both within and outside the partnership, as the leader of the initiative. If so, that person should be collaborative, encouraging and safeguarding the partnership’s participatory process, and facilitating problem solving.
Establish guiding principles for the partnership. What are the principles the partnership is firmly committed to, regardless of what the initiative chooses to address and how it chooses to address it? A collaborative process? Treating every person and idea respectfully, even when there’s disagreement? A focus on social determinants? The basic principles, if they’re worked out and recorded at the beginning, will make the work easier down the road. They’ll provide the foundation for the vision and mission statements that come later, and they’ll also provide the framework within which the partnership will operate, reminding members what they’re there for, and structuring how they treat one another. Guiding principles provide security for partnership members: the principles show that they’re all on the same track, and that no one will be treated unfairly or excluded by the process. (See Tool #1 below for examples of guiding principles.)
Phase 2: Focus Your Partnership on Social Determinants
This step is about assessing community resources and challenges. If the purpose of an assessment is to identify a particular health condition and treat it, the assessment will take a different shape than it will if its focus is to identify the social determinants underlying that condition. An assessment that emphasizes social determinants will prepare the partnership to make changes that aim at the root causes of the condition, and thereby diminish or eliminate it.
Assess social determinants. Your first decision here is to consider what you want to assess. You have a choice in how to approach your assessment:
- You may start with disparities in health, such as high rates of infant mortality among some groups, and try to determine what social determinants influence them.
- You may start with major social determinants, such as income inequality or education levels, and consider how they affect health.
Remember that social determinants can have either positive or negative effects on health. Discrimination and poverty generally have negative effects; by contrast, a healthy environment and access to quality educational opportunities usually have a positive influence. You may choose to address social determinants by reducing negative conditions or by strengthening positive ones.
Identifying social determinants is an exercise in critical thinking. What are the real conditions or issues that influence health in the community? Are there environmental health threats, and, if so, whom do they most affect? Why? Are the adverse effects concentrated in geographic areas, and, if so, how did that come to happen? (Are more people with lower incomes exposed to environmental health threats because polluting industries or hazardous facilities are disproportionately located in communities with fewer economic resources, for example?) Are there economic and political factors that influence those conditions or issues? (E.g., Does a polluting industry – a coal mine, a paper mill – also provide many of the jobs in the community?)
There is rarely a simple causal relationship between particular social determinants, such as inequality and social exclusion, and particular health issues. It can take some detective work and very careful analysis to determine the multiple and inter-related contributors to a health or social problem.
- Survey community partners and others to determine concerns, needs and resources in the community. If you’ve assembled a truly representative group, partnership members and the networks they’re connected to should be the best sources of information about the real concerns of the community. They may interpret health much more broadly than public health officials or medical professionals do; for instance, as related to economic hardship and housing conditions. They may also have knowledge of assets and resources that aren’t immediately apparent to those from outside the community or neighborhood.
- Think about the types of information that will be useful for understanding your community. A combination of the many available information sources may provide the most nearly complete perspective of the community. In general, it is useful to consider sources in the scientific literature as well as local, state, and national online data systems. The following existing sources of information may be of use:
- Morbidity/mortality. To the extent possible, it may be useful to examine community-level indicators (e.g., infant mortality, injuries) data by race, income, or other characteristics to better understand how social determinants could be influencing health disparities in your community. Some examples: the National Health and Nutrition Examination Survey data (NHANES), National Health Interview Survey data (NHIS), and National Vital Statistics System data (NVSS).
- Behavioral factors. Various groups in your community might have different rates of health-related risk behaviors. Even if you wish to focus on the social determinants of health, it may be useful to have information about health-related behaviors among different groups in your community. These data may be important in understanding the extent to which social determinants influence health behaviors and health outcomes. For example, you can visit the Behavioral Risk Factor Surveillance System (BRFSS).
- Social indicator data. A number of sources can give information on various social, economic, and environmental conditions in your community, including employment, education, housing, transportation, and parks and recreation. It may be useful to have a researcher or other partner familiar with how to access and work with such data through online data systems or other sources. The benefit of these data is that they provide information about places or communities on a wide variety of indicators. For example, these data sources may provide information on employment, housing, environmental hazards, education, income, transportation, and other community conditions. Current federal, state, Tribal, and local data systems, including the U.S. Census, can provide useful information for understanding social determinants in your community.
Each of the data sources described above may be helpful for determining the best starting point to understand how social determinants contribute to health disparities and inequities in your community. By reflecting on them together, you may gain a better sense of the specific social determinants you want to address. For example, your community may have high rates of morbidity and mortality associated with cardiovascular disease and diabetes, along with lower rates of fruit and vegetable consumption in areas with fewer grocery stores. These findings might lead your partners to consider supporting farmers’ markets and improving access to fresh fruits and vegetables through community markets.
- Determine what information you need to collect to better understand your community.
- Review of existing data sources. Public records and archival data – census figures, data from public health and other research studies, community reports, housing authority data, public assistance records, employment records, etc. This category also includes information related to laws, regulations, local bylaws, budget data, and other such information.
- Surveys and results of previous surveys.
- Brainstorming with the partnership and community groups.
- Qualitative interviews and focus groups. Individual and group interviews with community residents, giving their subjective answers to a series of carefully thought out, open-ended questions about the community.
- Photovoice. A participatory method in which community members use photographs, and often accompanying discussion or narrative, to document and communicate community conditions and experiences.
- Community observations and audits. Observing various aspects or areas of the community is a way to understand community members’ lives and the circumstances in which they live them, as well as how they interact with one another. Community audits are formal observations of how well various services are working and how responsive government and other sectors are to community needs.
- Concept mapping. This is a general method that can be used to help individuals or groups to describe their ideas about a topic in a pictorial form.
- Health Impact Assessment. A Health Impact Assessment (HIA) is a study of the impact on community health of a planned project, development, or action on the part of government or some other party that conducts operations on a large scale – a major corporation, real estate developer, transportation company, etc.
- Appreciative inquiry. Appreciative inquiry (AI) is a change strategy that identifies existing strengths (rather than problems) in a community, group, or system and then actively builds on these strengths to envision and plan for a desired outcome.
Surveys, interviews, focus groups and other methods give you insight into community members’ perceptions and what they know and think about various conditions and issues. Existing data sources, such as archival records and observation, provide a portrait of the community in its current condition.
- Develop a work plan for the assessment that identifies tasks to accomplish, partner roles and responsibilities, and a time frame for completion. A work plan should encompass:
- The information to be collected and the questions you want to answer.
- Your data-gathering resources. That includes people, expertise and skills, funds (at least some of those people may have to be paid, equipment and supplies may have to be bought), computer time, etc. You may be able to expand your ability to gather data by using help from outside the partnership.
- How you’ll find the answers to your questions (data sources and data-gathering methods.)
- Who will examine what data sources.
- A flexible timeline for reporting back to the partnership.
- Collect and organize information so it can be shared with all partners, community organizations, and community members. Focus on the data that are most useful to your partnership, and try to organize information in relevant ways – by question, by population, by geographic area, by particular conditions – and present it in appropriate forms – written reports, charts, slide shows – so that it can be understood by everyone, no matter how they learn best. You might want to compare your data and reports with those of other communities.
- With information gathered and summarized, partners can prioritize issues to address. Deciding on priorities should involve all partners, so that everyone’s concerns are addressed. Some questions to consider:
- Which social determinants, such as exposure to hazards and stress through inadequate housing, affect the most people or have the greatest influence in the community? Why?
- Which determinants seem to influence which conditions? Which affect the largest number of health conditions and social issues?
- Which have the greatest effect on equity?
- Which are feasible to address with the resources available? Perhaps you can’t address climate change on a global scale, but you may be able to affect local air pollution or surface temperature, for example.
- There are four basic principles or lessons learned that others who have conducted community assessments have found helpful in guiding this process:
- Be clear about the purposes of the assessment. Make choices about the methods you will use, what information will be shared, who the information will be shared with, and how it will be communicated.
- No matter how much time is available to the partnership, there will never be enough time to examine everything.
- Make intentional and open choices about what to assess and what not to assess.
- Be sure the assessment promotes the interests of the community members and that findings are not used against them.
- Once you have conducted your community assessment, this information can be helpful in determining priority areas to focus on, setting goals and objectives for your program or intervention, and determining a baseline to assess the progress you are making toward achieving your desired outcomes.
Develop a vision and mission. Clear vision and mission statements are crucial to the success of any initiative. It is particularly important for them to be developed through a participatory process, and that you take whatever time is necessary to craft wording that everyone can support. The time taken for this process will be well worth it for its contribution to the cohesion and focus of the partnership.
Your partnership’s vision -- such as “health for all” or “safe and caring communities” -- is what you want the community to look like when everything you hope to accomplish has been achieved.
Your partnership’s mission statement includes the essential “why” (e.g., “Achieving health for all…”) and essential “what” (e.g., “through policy advocacy and collaborative action”). It focuses the effort to realize the vision. In simplest terms, your mission statement describes the essential work of your initiative.
Your vision and mission statements should be as short and to the point as possible. They should fit together: carrying out the mission should lead to fulfillment of the vision. (See Chapter 8, Section 2, Proclaiming Your Dream: Developing Vision and Mission Statements.)
Identify and prioritize goals and objectives. An initiative planning model can be very useful as you identify your goals, objectives, and action steps. This model can be used to inform your planning process by guiding your community to understand current needs and to plan for the future. To develop an initiative planning model, outline your overall long-term goal and a series of objectives that will help move you toward achieving this ultimate goal. These objectives can be used to identify the specific action steps necessary to create change and benchmarks to determine your progress. In developing this model, be sure to include who will be responsible for each action step and the time frame for the steps’ completion.
Combined into a model or framework, these goals, objectives, and action steps provide the sequence of necessary actions. From this information, you and your partners can prioritize activities according to the timeline laid out in the plan. For example, community awareness and support may be needed before you can secure resources to create structural changes. In addressing social determinants of health, you may decide to focus on one specific determinant (e.g., housing, racism) within an initiative or specific health outcomes, such as asthma or heart disease, and the social determinants that influence them.
Your goal is the long-term outcome your partnership is striving toward. Objectives are the stops along the road that lead toward that goal. If, for instance, your goal is providing access to healthy food for everyone, an objective might be to persuade at least one merchant in each neighborhood to devote a certain amount more shelf space to affordable fruits and vegetables within the next six months.
In identifying and prioritizing objectives, an important consideration is to set up your partnership for success at the beginning. Early objectives should be challenging enough so that meeting them takes work, but reachable enough so that the chances of success are great. If the first objectives are met, later setbacks won’t feel too difficult to overcome. If the partnership starts off with failure, partners may get discouraged, and the effort could wither.
Phase 3: Build Community Capacity to Address Social Determinants
“Community capacity” refers to the resources, infrastructures, relationships, and operations that enable a community to create change and improvement.
Assess community capacity. Assessing community capacity involves identifying existing community strengths that can be mobilized to address the social, economic, environmental, and structural conditions affecting health equity. In general, you should look at the places (e.g., parks, libraries) and organizations where assets are found. These will likely be located in different sectors of the community: education, health care, business, housing, transportation, faith communities, social services, civic and volunteer groups, local government, and nongovernmental organizations. It is also important to identify the nature of the relationships across these sectors (e.g., norms, values), with the community (e.g., civic participation), and among various groups within the community (e.g., distribution of power, trust).
Build community capacity. Once people and organizations in the community have a common understanding of social determinants, they can work to improve the conditions that affect the health of all its members. Much of the work to increase community capacity relies on processes that you will develop working in and with your community. The following recommendations provide some guidance for developing these processes.
- Encourage broad community participation in planning, organizing and implementing community health efforts. One way to do this is to start with existing social groups such as those in schools, workplaces, service organizations, volunteer organizations, and places of worship. Individuals within these groups often share a sense of belonging with other group members and have some trust in the processes that the group uses to reach its goals. These are critical to the meaningful participation of individuals in group projects. Participation of these groups can enhance current and future collaboration.
- Identify existing social ties and relationships and use them to support participation by people and organizations. Share information and work to build unity and solidarity among community members most directly affected and among social groups.
- Identify useful assets of people and organizations in the community. These assets may include experience with the issue and its consequences or the ability to facilitate meetings or mobilize people and efforts. It may involve the ability to provide funding, space, and other necessities for carrying out the project. These may also involve spiritual assets such as compassion.
- Conduct regular conversations to share information with community members and engage them in making decisions through consensus-based and collaborative processes. Build on existing social networks such as the social ties already found in workplaces, schools, places of worship, and cultural organizations. Continue creating meaningful opportunities for different community voices to be heard and for people’s interests and needs to be considered.
Ensure that your group’s leaders are representative of the community and that they understand its assets and needs. They need to be able to engage all community representatives in identifying problems and devising solutions that will have broad support. You should also establish mechanisms to ensure that leadership roles and responsibilities are widely shared. These may include mentoring new leaders or creating bylaws that require periodic changes in leadership. Attempt to understand how the beliefs, perspectives, and histories of people and organizations in the community influence their willingness to participate in efforts to change community conditions and encourage them to consider alternative ways of thinking.
Phase 4: Select Your Approach to Create Change
Now it’s time to develop interventions to address social determinants of health. These may include programs or policy initiatives intended to move your community closer to your vision. There are a number of approaches you might use. In general, they are complementary; using them in some combination increases the likelihood that changes will lead to the desired goal.
This step describes six approaches or strategies for changing community conditions that others have found useful: consciousness raising, community development, social action, health promotion, media advocacy, and policy change. The best approach depends on your situation, what your partnership wants to accomplish, and how well the strategies fit your situation. In some cases, the decision to incorporate certain approaches may be partially determined by funding guidelines or other restrictions based on work already occurring in your community or organization.
Consciousness raising. Consciousness raising—sometimes described today as building critical awareness—is a process through which people come together to discuss the relationship between individual or group experiences or concerns and the social or structural factors that influence them. It can be useful in creating a partnership to increase community-wide support for addressing specific health inequities and their root causes.
This approach is useful for helping people with different relationships to the issue develop a common understanding of concerns, stimulating discussion and motivating partners to address them. Consciousness raising is a good approach when some people in a group do not see or understand how social and structural factors influence health inequities. It also helps individuals and groups identify specific social determinants or structural factors to develop goals and objectives for change. In addition, this approach can help the partnership frame issues in ways that bring groups together for action rather than creating unnecessary divisions that lessen the ability to create change.
Methods used to raise consciousness typically generate discussion by asking individuals to share their experiences. This can be done in listening sessions presenting hypothetical vignettes or situations. This can be done by having the group discuss responses to a picture or photograph, or reading a story or poem. Encourage critical reflection by asking individuals to describe what they saw or heard as the major issue, followed by asking “but why does this happen?” or “why is this the situation?”
Community (locality) development. Community development is a set of processes or efforts to create community change at the local level. It involves strengthening social ties, increasing awareness of issues affecting the community, and enhancing community member participation in addressing these issues.
This involves bringing together individuals affected by a particular health inequity so they can cultivate a shared group identity and develop a specific set of processes for addressing their common purpose. Though all work in this field should be participatory, community development is unique in that those who experience the problem are the leaders in addressing it. Those most affected by health inequity and the social determinants that lead to it are in control of changing the situation. This approach is in accordance with the Ottawa Charter, a 1986 document drafted by the World Health Organization at a meeting in Ottawa, Canada, that lays out the basis for a SDOH approach.
Community development seeks to enhance or establish a group of individuals who work together to create changes in health or the social determinants of health. In community development approaches, capacity building is paramount: the goal is to use the community’s capabilities and strengths to increase community control. As this suggests, the process of community problem solving is seen as the process of health promotion. Building and using existing capacities for problem solving can improve health equity, both directly and indirectly.
This approach may sound similar to community capacity building. But, community development specifically seeks to establish and enhance the power of those most affected by inequity, rather than just creating enhanced community capacity for planning or program implementation.
Community development may be useful when you first develop a partnership or later when the partnership has accomplished other goals. The process encourages partners to develop a shared group identity that relies on understanding, trust, acceptance of differences, and cohesive relationships. This goes beyond other partnership-building activities described earlier, such as inviting stakeholders, identifying social and health inequities in the community, deciding on a shared vision and mission. This approach may be particularly useful when an existing partnership decides to use a more participatory approach, as opposed to one that relies on public health or other experts taking the lead.
In community development efforts, community members lead the initiative. Others, such as public health practitioners, researchers, and community organizers, can assist community members by supporting group processes for problem solving and consensus building. It is important to ensure that the models and processes suggested by outsiders can be modified by community members as needed. It also could be helpful to engage community members in consciousness-raising processes before, or as part of, community development efforts to increase their awareness of the social determinants of health.
In addition to representatives from the community, partnerships should include community agencies or organizations that will be asked to help implement change. Organizations are more likely to take part in changing social determinants of health if they have been included in the discussions and have worked with the community from the start, rather than just being asked to implement a solution designed by others.
Social action. Social action is an approach that focuses on altering social relationships and/or resources available to address health inequities. This strategy spotlights how social factors can affect people’s health and how inequities in the social determinants of health can be influenced. Social action often includes activities that explicitly highlight an issue. For example, a group of community members might join together to light a candle for each person in their community injured by an alcohol-impaired driver in the past five years as a way to encourage the enforcement of laws that prohibit driving while under the influence of alcohol.
Social action may use a continuum of direct action tactics from requesting accountability to public demonstrations.
Social action can be used to help raise awareness of issues and to increase community participation in efforts to address them. For instance, it can be especially useful at the beginning of change efforts since media attention can help get people’s attention when other approaches have failed. Although this strategy can help define and bring attention to a problem, it does not necessarily identify effective solutions.
Practitioners can take part in social action in a variety of ways. For example, they can provide current, relevant information and data to help develop the messages conveyed through social action activities. They can also help identify appropriate audiences for a particular message (e.g., an elected official, the public at large). Practitioners can assist the partnership in determining how to convey the message from the data to the audience in a way that will capture its attention. This is usually a public action involving a large number of people. Because the intent of social action is to influence public opinion, it is often useful to organize media coverage of the event and ensure that public officials are aware of it.
Health promotion. Health promotion refers to the process of people working together to create conditions that improve health and well-being for all members of the community or prevent illness through changes in environments, policies, practices, and behavior. It includes efforts to reach individuals or families, activities in the workplace to reach employees, and community initiatives focused on larger populations. Traditionally, health promotion in the United States has focused on changing individual knowledge, attitudes, and skills to encourage particular behaviors. Health promotion efforts may also include organizational, policy, or environmental changes that facilitate positive health outcomes. These health promotion efforts are more likely to address social determinants of health, such as increased access to quality fruits and vegetables through development of community gardens or reduced exposure to environmental toxins through policies supporting improved air quality.
In many low- and middle-income settings, health promotion efforts often focus directly on social determinants. For instance, they may work to assure access to primary education, the availability of clean water and sanitation, or social protection for people experiencing poverty.
Within community settings, it is not unusual for organizations and individuals to want to focus on the behavioral determinants of health such as healthy nutrition or physical activity. However, even when the effort focuses on a particular health or risk behavior, it is useful to incorporate program elements that address social determinants. For example, educating people about the health benefits of eating fruits and vegetables is important. However, people must have access to affordable produce if they are to incorporate it into their diets. Thus, increasing access to affordable food (the social determinant), in conjunction with knowledge and skill development, is more likely to create the desired change in behavior and thus the improvement in health outcomes.
Health promotion efforts may attempt to improve health by creating change at the level of individuals, relationships, organizations, communities, or society. For example, an intervention aimed at altering individuals’ knowledge, skills, attitudes, or behaviors might include educating community members on the benefits of physical activity. Because the costs of exercise facilities might constitute a barrier for many people, your health promotion effort might address social determinants by working with a local recreational facility to lower fees or provide more affordable access. Similarly, your efforts to improve healthy nutrition might work with local government officials to increase access to healthy food options through tax and zoning policies that encourage the development of full-service grocery stores in neighborhoods where they are lacking.
When working to incorporate changes in social determinants into health promotion programs, it is important to:
- Consider the amount and quality of the existing social ties among individuals and organizations and how new social ties or relationships can be created and supported.
- Consider the physical or built environment, including:
- The availability of safe neighborhoods and sidewalks in good repair for walking.
- Access to affordable recreational facilities such as gyms and soccer fields.
- Access to grocery stores with affordable fresh fruits and vegetables.
- Consider the availability of resources (e.g., transportation, jobs, housing, and schools).
- Work with partner organizations to provide opportunities for economic development, including safe jobs with living wages.
- Strengthen cultural responsiveness and humility among health educators and increase access to language and interpretation services.
- Use participatory approaches to work with community members and different sectors of the community to create these changes in the environment.
Media advocacy. Media advocacy refers to the strategic use of print, broadcast, digital, and social media to encourage social, economic, or environmental change. It can reach large populations and capture the attention of decision-makers who influence policy. Media campaigns may use newspapers, radio, television, social media, websites, video, billboards, posters, brochures, and other communication channels. Historically, mass media campaigns in public health have often focused on encouraging individual behavior change such as reducing tobacco use or underage drinking. Alternatively, media advocacy can be designed to influence change in norms, policies, and collective responses by the community to inequities.
Mass media campaigns have been used to increase public understanding of specific health issues, such as how individuals can change their own or their loved ones’ behavior to improve health outcomes. To address social determinants of health, it is important to shift the focus to also address broader social, economic, and environmental conditions. This type of media advocacy helps to reframe public health concerns as the result of community rather than individual causes. This can help initiate collective community responses to create change. Media campaigns are most useful when high visibility is desired and public debate or discussion is useful in reframing the issue to focus on broader social change.
Begin planning a media campaign by referring to your partnership’s vision and mission. Decide on the goals and objectives of your media campaign and identify the main audience for the message such as the general public or elected and appointed officials.
Once you have chosen your audience, consider inviting media or communications representatives to become involved with the planning, implementation, and evaluation of your media campaign. In addition, consider the most appropriate communication channel—given your audience—for delivering your message and, when useful, include people with experience using that channel in your partnership. Media and communication channels may include television, newspapers, radio, billboards, websites, social media, online community forums, email, video, podcasts, or public information forums such as news releases, special events, and town meetings.
In addition to discrete media spots, the message must be part of an ongoing community dialogue to be effective. This can be done through letters to the editor, editorials, and public hearings or community meetings.
Next, plan your message. Identify the community health problem and offer solutions. Consider how to frame the problem and the solution to attract the interest of your audience and ensure the message is culturally sensitive. For example, if your objective is to increase access to health care and screenings, you may want to direct your media campaign toward local decision-makers, health planners, and other influential individuals or organizations in the community. Messages may emphasize increased funding for health screenings, expansion of existing transportation or service routes, improved hours of operation, or other changes that assure access to health services in the community.
Be sure to frame your message in a way that moves the focus for change away from individual behavior and toward social, economic, or environmental conditions. Work with local media representatives to learn how to develop a marketable story, create sound bites, and determine who will be the public spokesperson. Additional points to keep in mind:
- Messages should be simple and clear. State the issue and why the intended audience should be concerned. Provide potential solutions, be powerful and compelling, and speak directly to your audience.
- Be sure your data are accurate, up-to-date, and easy to understand.
- Develop a media list and become familiar with local media. Find out which reporters cover which issues. Think about the audience each media outlet (e.g., newspaper, radio station) reaches.
- Work with media specialists so that your message is in the proper format for the media outlets you have chosen.
- Piggyback onto breaking news by highlighting local stories related to health and social issues.
(See Tool #2 for an outline of how to run a media campaign and references to more detailed Tool Box information.)
Policy and environmental change. Achieving community-level improvement in health and health equity typically requires changes in policies and environmental conditions. This requires active participation of people and organizations in the community and key decision-makers from different sectors. Local decision-makers include elected and appointed officials, institutional or organizational leaders, and other individuals or groups involved in policy making in your community. Your partnership may focus on changes in policy (e.g., zoning regulations, tax policies, and worksite or school policies) and other conditions that affect health (e.g., equal access to education, employment, recreation facilities, and healthy food).
A policy is a plan or course of action intended to influence and determine decisions, actions, and rules or regulations that govern our collective daily life. Policies can be created and enforced by organizations, businesses and corporations, communities, or government at local, Tribal, state, or federal levels. One purpose of creating new or changing existing policies is to change the social determinants that influence health equity (e.g., tax incentives for the food service industry to provide healthy foods, or education-finance policies intended to support more equitable access to public education).
The environment includes physical facilities (e.g., roads, sanitation, schools, parks) and structural and cultural amenities (e.g., benches, streetlights, recycling bins, public art). It also includes the social environment – economic and social conditions. Changing the environment requires informed decision making about urban design, land use, transportation, and political and social systems and their relationships to health outcomes.
Changing policy and/or the environment is useful when you want to promote health and health equity. People and organizations in the community may consider using policy change to affect whole groups of people. Policy changes can be designed to influence individual behavior (e.g., smoke-free policies), organizational practices (e.g., flexible work-time policies), or community conditions (e.g., housing codes that reduce exposure to hazards). Policy changes can also affect the built environment, such as zoning related to new grocery stores or fast-food restaurants, maintenance of sidewalks and streetscapes, or architectural design features such as public plazas with signage communicating the history and culture of the community.
Your partners can be active players in the policy-making process by educating decision-makers about how changes to policy or the environment can promote health equity. For example, they can provide current data on health and social determinants, information about existing policies, or examples of policies that have worked well in other communities. They can also help by identifying key decision-makers to contact based on their interest in the issue or their position on certain decision-making bodies (e.g., committees, boards).
Your partnership may also consider engaging in policy change by connecting to larger organizations that can help define concerns and develop potential solutions. A well-structured, well-positioned organization can support policy change by defining a problem that affects many individuals or communities (e.g., consumer legislation, air quality). It can help unite voices and actions to create change, and assist local organizations in finding resources and support for their work. Some groups may work directly on health-related topics (e.g., land-use policies to increase parks and greenways), whereas others may work on policies that influence the social determinants of health even if they are not explicitly focused on health (e.g., housing, early childhood development).
If you’re a tax-exempt U.S. organization or receive government funds, different legal and grant-related rules may apply to lobbying and political activity. Be sure to find out which rules apply to your organization, funding source, and proposed activities.
Selecting your approach. Which approach or combination of approaches to addressing social determinants is right for your effort? Here are some factors to consider as you make that decision:
- The experience and expertise of your partners.
- The nature of the social determinants you plan to address.
- The availability of financial and other resources.
- Funding restrictions or guidelines for the initiative.
- The existence of policies that are not being enforced.
- Whether you are working to create change at community or organizational levels.
- The political and social buy-in of the community.
- The relative success or failure of similar approaches in the past.
Mold your approach to your situation – your resources, knowledge and experience of partners, community history, etc. Don’t be afraid to modify an approach, or to try something new if you have good reason to think it might work. If you settle on a combination of approaches, think about the advantages and disadvantages of using them at the same time or in sequence – resources needed, one approach paving the way for the next, etc. The important thing is that the group agrees on the best way to proceed.
Document your decision-making process to help develop support for the selected approach. Remember to consider new partners who can support your use of different approaches. Be willing to modify your approach as you track your successes and challenges. This is the learning-from-doing model.
Phase 5: Move to Action
Now it’s time to get moving, by creating and carrying out a plan to reach your goals.
Assemble a planning team. This may include members of the partnership, as well as others recruited for their experience, perspective, special skills, or expertise. Be sure to include people from the groups most directly affected by the social determinants addressed by the initiative. After the planning group has been organized, it should meet to determine what action steps are necessary. Once these steps have been developed, agree on specific roles and responsibilities for partners and devise a timeline for all action steps. (See Chapter 18, Section 2, Participatory Approaches to Planning Community Intervention.)
Develop your action plan. An action plan describes the specific steps necessary to meet clearly defined goals and objectives. Begin to develop an action plan as soon as your partnership’s vision, goals, objectives, and approaches have been determined. An action plan will help keep you on track toward achieving your goals and tell the community that you’re making progress. Keep in mind, however, that you may need to modify your action plan to meet changing conditions in your community over time. To be effective, an action plan should include the following key elements:
- Your partnership’s goals and objectives.
- Who is responsible for which activities.
- The time frame for completion of activities.
- How you will assess progress.
- How you will assess impacts and outcomes.
- Describes each action step clearly and specifically. The plan should be easy to understand and in a format useful to all partners.
- Assigns responsibilities (who will do what) for each action step.
- Provides a timeline and deadlines for completion of the action steps.
- Outlines what resources – both existing and needed – will be necessary to successfully implement each action step, including finances, staff, space, and equipment.
- Includes a list of other community members who may be potential collaborators and involves them in your project as necessary. This may also help increase community awareness of your project.
Implement your plan. This is it – the point where you actually put all your planning into effect. Some helpful guidelines include:
- Secure any needed resources. Be sure that your group has a backup plan in case promised resources are not provided or in case additional resources become necessary.
- Be sure everyone is familiar with the whole plan, with their own role, and with the deadlines to meet.
- Take time to celebrate what has been accomplished and to publicly recognize what people have contributed.
Coordination is crucial for successful implementation. You can’t do something as complicated as running an initiative without a person or small group keeping track of everything and making sure that the appropriate things get done at the appropriate times.
- Anticipate challenges; consider how to address them before they happen. Challenges might include:
- Maintaining effective communication. The effort must assure that partners and other group members are communicating effectively with one another and the community, and that everyone gets both general information about the effort and whatever specific information they need. Because your partnership will likely include groups that do not normally work together, clear and respectful communication is essential. (See Chapter 15, Section 4, Promoting Internal Communication for more on communication.)
- Dealing with conflict among partnership members – turf issues, jealousy, disputes over funding, differences of opinion about strategy, perceived or real power imbalances, etc. Conflict and power imbalances, if handled well, can lead to enhanced collaboration and understanding about how differences in power can influence health.
- Adhering to partnership principles. If this is a problem, review each principle and determine challenges to adherence. Post the principles at each partnership meeting and review and revise them as needed.
- Addressing partners’ unrealistic expectations about the amount of their time the initiative will consume, the timing and magnitude of results, funding that they expect will come their way, etc. (Setting numerous achievable short-term goals can help task-oriented partners deal with the inefficiencies of process related to collaborative action.)
- Resolving conflicts between partners’ roles in the effort and their obligations to their own organizations – time conflicts, competition for funding or positions, etc.
You can help prevent conflicts from damaging the partnership by encouraging members to openly discuss actual or potential conflicts, modifying the action plan if necessary and feasible, and ensuring that community members help define the actions most appropriate for their communities. Other problems your partnership may need to address include members’ perception that the partnership threatens their autonomy, disagreement about community needs, and conflicts over funding decisions. Other potential challenges include lack of consensus about membership criteria or coalition structure, lack of leadership, competing interests, and failure to include relevant constituencies. To overcome these problems, the members of the partnership must work together to identify expected challenges, prepare for unexpected challenges, agree to disagree, and create strategies to overcome both expected and unexpected challenges. If challenges prohibit progress of the partnership, it may be useful to seek assistance from an outside consultant or mediator.
Phase 6: Document and Share Your Work
From the beginning of your effort, you should also be evaluating your work, both to document it for your partnership, your community, and others who might want to try something similar, and to find out where you need to make changes in order to be as effective as possible. That means you have to keep careful records of everything you do, and of all that happens as part of the initiative.
There are three areas to evaluate:
- Process. Your initiative most likely used key processes to advance its effort—for instance, assessing community assets and needs, collaborative planning, and implementation of the activities. What did you do to form and run the effort? Did everything go as planned? Were there unintended or unforeseen actions or consequences, and how did they affect the effort?
- Impact. What immediate or intermediate changes resulted from the effort? Did access, awareness, behavior, policy, community conditions, organizational practice, or another factor change in the direction you expected? How close did you come to meeting your objectives?
- Outcomes. What were the longer-term results of what you did? Did the social determinants you aimed at change in the ways you’d hoped? Did health inequities or related health outcomes change? Did your work bring the community closer to your vision of a healthy community for all?
Evaluate your efforts. Your evaluation should be organized at the very beginning of the initiative, so that you’ll record information about the formation of the partnership and the first stages of planning as they happen. The first step is to formulate evaluation questions that reflect what you want the evaluation to tell you. Then, you should structure the evaluation, using the form, tools, and methods that will best answer the questions you have chosen. An important element is the participatory nature of the evaluation, as well as of the rest of the process. To the extent possible, partners should be involved in formulating evaluation questions, choosing methods, taking part in the evaluation, analyzing the results, determining adjustments to be made, and presenting what you’ve learned to the community.
Some evaluation questions you might want to answer:
- How well is your partnership working? This is about process. How did you put the partnership together? Were you able to get all the key people, groups, and sectors involved? How well have partners worked together? How good was your communication? What about the partnership has worked well? What were major challenges? Were they overcome, and how? If not, what were the results? How would you deal with them in the future?
- How has the partnership related to the community? What resources have been helpful? What is still needed?
- How well has your action plan worked? Did you do what you initially planned? If you made changes along the way, what were they and why did you make them? If there were unintended changes, what caused them? (Common causes are delays in funding or hiring, difficulties in obtaining space, and emergencies that make it difficult or impossible to carry out certain parts of the plan, such as a key person falling ill.)
- Are your partners making progress toward their goals (outcome evaluation) and objectives (impact evaluation)? Review records, meeting minutes, etc. to document what people actually did to make things happen.
- If you were starting this whole process over, what would you do differently?
- What were the intended consequences of your actions?
- What were the unintended consequences (positive or negative)?
Link your evaluation to your community assessment and action plan. This may seem obvious, but it is sometimes difficult to remember that all of these elements of the initiative should fit together. Your action plan should address issues and their social determinants identified by your community assessment, and your evaluation should tell you how well it did so. Formulate objectives as milestones along the road to achieving long-term goals, and help partners and community members understand that realizing the overall vision is a long process. Their expectations have to be aimed at attaining milestones, rather than quickly reaching the end of the journey.
Carefully record what you do. This will enable others to reproduce what works in the initiative and know what to expect if they take the same actions you’ve taken.
Share your work. Your initiative should communicate the findings and lessons learned to others in the field. You should share general information with others – for instance, about what was effective and what wasn’t, how your process worked, ways to increase participation, the outcomes, and how long things take to accomplish. Some communication methods you can use include:
- Newsletters
- Presentations to the community at large and to various organizations
- Websites and email lists
- Social media and other digital platforms
- Media stories and press conferences
- Presentations at conferences
- Informal networks, word of mouth
- Flyers/brochures
Phase 7: Maintain Momentum
No matter how successful your initial efforts have been, you’re not done yet. To effect real social change, which is, after all, what changing social determinants is about, you have to keep at it for the long term.
Remain flexible and dynamic. Dynamic organizations continually change, both in response to changes in the environment and to incorporate new and better methods and approaches. Organizations, initiatives, and movements that aren’t dynamic are dead. No matter how good your work is, it can always be better. Never be afraid to test out new ideas or to abandon old truths and traditions if they don’t work anymore. It’s the best way to keep your work fresh, and to make sure that everyone maintains enthusiasm for it. A willingness to adapt (e.g., to abandon strategies that don’t work and to try new unconventional strategies) will help your group sustain its work over time and ultimately accomplish its goals. Some ways to keep flexible and dynamic:
- Continue to monitor changes in the community and broader environment such as changes in population, political trends, health information and possibilities, etc., and adjust accordingly.
- Continue to monitor and evaluate your work, and adjust as needed.
- Add new partners as old ones leave for other jobs or localities or retire; add new partners as circumstances change (new organizations that should be involved, for example, or individuals with valuable skills).
- Change methods, approaches, and process as you gain more insight into what you’re doing.
Change is often difficult for people. To keep from losing valuable partners during periods of transition, you may need to make a special effort to convince them of both the importance of modifying the group’s focus and their continued value to the group, rather than allowing them to feel they are being replaced. It can also be helpful to create subcommittees through which some members of your group engage in new ventures while others continue to carry out ongoing activities and to focus on building and maintaining relationships during group meetings. The latter is particularly important as new members join the group.
Combat fatigue and burnout. Social change is hard work. It often involves dealing with injustice and human tragedy on a daily basis, and its results may be slow in coming. People and organizations get tired, and the temptation to quit can grow strong. It’s important to recognize the possibility of fatigue and burnout, and to make sure to address them in various ways.
- Be aware of community history. Some partners and community members may have made several past attempts to create changes in community health or in social, economic, and environmental conditions, and may feel that their energy and efforts were in vain.
- Continue to strive for maximum participation and diversity.
- Celebrate successes. Hold regular social gatherings, and commemorate anniversaries and other important milestones.
- Honor partners for their work, or for simply persisting – you don’t need a specific occasion. Be liberal with praise and with recognition of the effort that people put into their work. Honor people and organizations both publicly and privately.
Barbara Corey, the longtime former coordinator of the North Quabbin Community Coalition in Massachusetts (USA), constantly sent postcards to Coalition and task force members, thanking them for their work. Whenever she had a spare moment, she’d write a note to someone she’d met with, or who had played an important (or even not so important) role in a community effort. The result was that people kept volunteering and remained connected, both to the Coalition itself and to its goals and ideals.
Sustain the partnership and the work. The work of addressing social determinants can be a long process. Funders get tired just as partners do, and the community may also lose interest in the partnership. If you’re going to realize your vision, you have to find ways to keep the work going. Some important ideas for sustainability:
- Develop a formal organizational structure when the group is ready. Two possibilities:
- A government-authorized organization. Structuring your partnership as an organization that has been authorized by executive or legislative action of state or local government might increase your group’s credibility in the community. This could give it the legal authority and fiscal status to conduct certain activities.
- A community network or coalition. This form of organizational structure may allow you to more accurately identify community needs and to gain greater community support for your group’s activities. In addition, structuring your group in this way could allow you the flexibility to engage in a variety of activities without being restricted by any one organization’s rules and regulations. If your group is organized in this fashion, it might be useful to have a memorandum of understanding that outlines the expectations of each partner. It can also be helpful to establish bylaws for more formal partner interactions.
- Create local awareness of and support for the partnership.
- Bring in new partners.
- Ensure that all members are participating in partnership activities.
- Encourage shared leadership and decision making, and foster new community leadership.
- Develop a strong sense of group identity.
- Increase community awareness and understanding of the initiative.
- Help partners develop the skills and resources necessary to carry out the initiative.
- Build the initiative on existing efforts when possible.
- Identify potential funding opportunities, such as grants from government agencies or foundations. If you are part of an unincorporated coalition, you may need to find a fiscal agent or partner that will permit you to access these funding streams.
- Reflect on mission, goals, and objectives to determine necessary changes.
- Revisit your partnership principles often and revise them as necessary.
- Change strategies as necessary and appropriate.
It’s easy, once routines are established, to let things slide. In fact, for a community change effort to be successful, it has to maintain its momentum indefinitely. It must be sustained for as long as it takes for the ideas, processes, and practices to be integrated into the community. There was a time when fire departments, police departments, and public libraries were new and radical ideas. Now, their presence is the norm in many parts of the world. Until social and health equity become the norm, until all of us are healthy, our job is not done.
In Summary
Addressing social determinants is an important strategy for working toward healthier and more just communities. This cross-cutting approach is more comprehensive than narrower efforts to address particular health issues such as violence, diabetes, or infant mortality. By working together to change the unequal exposures, vulnerabilities, resources, and consequences that produce health inequities, we can help assure conditions for health and well-being for all.
We encourage the reproduction of this material, but ask that you credit the Community Tool Box: /.
Adapted from Promoting Health Equity: A Resource to Help Communities Address Social Determinants of Health, a 2008 resource developed with support from the Centers for Disease Control and Prevention, U.S. Department of Health and Human Services. The seven-phase framework in this section reflects that resource; terminology and examples have been updated where needed for contemporary use.
Contributor
Laura K. Brennan Ramirez, PhD, MPH
Elizabeth A. Baker, PhD, MPH
Marilyn Metzler, RN
Stephen Fawcett, Edits/additional contributions
Phil Rabinowitz, Edits/additional contributions
Resources
Online Resources
Action: SDH: an electronic discussion platform, which aims to stimulate debate and share experiences of improving health equity through addressing the social determinants of health.
Actively Addressing Systemic Racism Using a Behavioral Community Approach - a journal article from Behavior and Social Issues.
Advancing Health Equity: A Guide to Language, Narrative and Concepts is a free pdf guide from the American Medical Association.
Assessing Meaningful Community Engagement is a 2022 article appearing on the National Academy of Medicine website
California Mortality and the Healthy Places Index is a 2024 Healthy Places Index study that highlights that improving community conditions such as housing, transportation, and environmental quality could prevent up to 24% of deaths annually in California, including 72% of COVID-19 fatalities. The findings underscore the need to address systemic inequities and integrate social determinants of health into public health strategies.
Can Hospitals Heal America's Communities? from Democracy Collaborative illuminates the possibilities of hospitals and health systems healing America’s communities and explores how “all in for mission” is the emerging healthcare model.
CDC's Health Equity Page features a number of articles, while the CDC's Health Equity Library and Research Guide provides further resources for researching health equity.
Chapter 16: Behavioral Community Approaches in the "Introduction to Community Psychology" outlines how large, complicated problems can be broken down into smaller ones, the importance of studying and bringing about change in observable behaviors, and how behavioral approaches are used in Community Psychology.
City of Baltimore Health Commissioner, Leana Wen - In this video, APHA TV sits down with the City of Baltimore Health Commissioner, Leana Wen, to discuss how the city is improving community health by addressing the underlying social determinants of health.
The Community Engagement Framework is a resource by the New York City Department of Health and Mental Hygiene. The simple flexible framework offers a way to standardize and refine community engagement efforts across organizations.
DETERMINE: An EU Consortium for Action on the Socio-Economic Determinants of Health. This Portal is a tool to promote health equity amongst different socio-economic groups. Here, you can find information on policies and interventions to promote health equity within and between countries via the socio-economic determinants of health.
Equity, social determinants, and public health programmes edited by Erik Blas and Anand Sivasankara Kurup. World Health Organization Department of Ethics, Equity, Trade and Human Rights and Priority Public Health Conditions Knowledge Network of the Commission on Social Determinants of Health.
Essentials of SDH Online Course. Open to all audiences, this 10-hour fully automated, self-directed online course is offered in both English and Spanish, and includes a Portable Offline Version.
BALLE's field guide, The Future of Health is Local, gives health care providers actionable tools and examples on how to align the non-clinical assets of their organizations – such as procurement, employment, and investment – with local economic development strategies to improve human health and revitalize local communities.
Getting to Equity in Obesity Prevention Toolkit - This toolkit from the Council on Black Health addresses the need to include an equity component in the planning and implementation of policy, systems, and environmental change approaches (PSE) undertaken to curb adverse trends in obesity and related health consequences.
The Global Health Politics Podcast, Season 3, Episode 5, features Monica Wang discussing The Collective Cure, a community-driven approach to addressing health inequities through collective action, relationship-building, and systems change.
HealthEquityGuide.org is a website with a set of strategic practices that health departments can apply to more meaningfully and comprehensively advance health equity.
Health Equity Animated: Equity vs. Equality from the Center for Prevention in Minnesota explores the difference between the needs of various communities, and how addressing those specific needs requires specific solutions.
Healthy Neighborhoods Study, based in Boston, is the largest resident-driven, participatory action research project in the US about neighborhood change processes, like gentrification and climate change, and their impact on health.
Healthy People, 2020. Social determinants of health.
This ColorCode “Housing Is Health Care” podcast delves into how housing — and today’s housing crisis — intersects with health. It also explores how racial discrimination has played a part in causing this crisis, as well as present-day housing segregation on Long Island.
Infographic: The ABC of SDH is a free poster-size infographic for all audiences.

The Lazy Person's Guide to Saving the World is from the United Nations and features 17 sustainable development goals to transform our world.
This Local Health Department Organization Self-Assessment for Addressing Health Inequities Toolkit and Guide to Implementation from the Bay Area Regional Heath Inequities Initiative
This downloadable National Sexual Violence Resource Center pdf covers the history of the movement to end sexual violence
No Justice, No Peace of Mind and Body: The Health Impacts of Housing Insecurity for Black Women from The Nonprofit Quarterly.
Pew Charitable Trusts provides an article about holistic approaches made by partnerships to promote healthy birth outcomes.
PrevenTN, a project of the Tennessee Coalition to End Domestic and Sexual Violence, provides several resources and toolkits for those looking to work to end domestic and sexual violence
Promoting Health Equity: A Resource to Help Communities Address Social Determinants of Health by Laura K. Brennan Ramirez, PhD, MPH; Elizabeth A. Baker, PhD, MPH; Marilyn Metzler, RN. Social Determinants of Health Workgroup at the Centers for Disease Control, U.S. Department of Health and Human Services.
The Research Methods Knowledge Base is a wide-ranging compendium of information on research methods.
Rio Political Declaration on Social Determinants of Health (2011).
SDH-Net Virtual Learning Platform is open to all audiences but especially helpful to researchers. This platform offers online and classroom-based courses, methodological documents, repository, infographic, and guides.
SDH Repository of Resources contains over 250 SDH resources including audio, video, pictures, and documents in English, Spanish, and Portuguese.
Seven Vital Conditions for Health and Well-Being is a useful framework for conceptualizing holistic well-being and the conditions that give rise to it, as well as identifying levers for community change and improvement.
Social Determinants of Health is a video from the World Health Organization (WHO).
Social Determinants of Health (SDOH) Training Plan from the TRAIN Learning Network provides over a dozen hours of training over the foundational concepts and their applications to various issues.
Social Determinants of Health and Older Adults covers new resources made available by health.gov specifically focusing on the health of older adults.
Social Determinants of Health in Rural Communities Toolkit by the Rural Health Information Hub organizes evidence-based models and resources to support the implementation of programs that address the social determinants of health (SDOH) in rural communities across the United States.
The Sustainable Development Goals Guide is a preliminary guide on how to "get started" with implementing the Sustainable Development Goals.
Targeted Universalism by the Othering & Belonging Institute at UC Berkeley explores a policy framework that sets universal goals for social well-being while implementing targeted strategies to address disparities among different groups.
Transformational Community Engagement to Advance Health Equity is a report with case studies from the Robert Wood Johnson Foundation.
What is Healthy Equity? This three-minute motion graphic video explains how social, economic, and environmental conditions can create health inequities and how these inequities can affect health disparities.
What is Privilege? A video from BFMP at Buzzfeed.
Why Community Power Is Fundamental to Advancing Racial and Health Equity from the National Academy of Medicine.
Working Upstream: Skills for Social Change - a resource guide for developing a course on advocacy for public health.
Print Resources
Commission on Social Determinants of Health. Closing the Gap: Health Equity Through Action on the Social Determinants of Health, Final Report of the Commission on Social Determinants of health. Geneva, World Health Organization, 2008.
Metzler, Marilyn, Mary Amuyunzu-Nyamongo, Alok Mukhopadhyay, and Ligia de Salazar. (2007.) “Community Interventions on Social Determinants of Health: Focusing the Evidence.” In McQueen, D and C. Jones C, editors. Global Perspectives on Health Promotion Effectiveness. New York: Springer.
Poland, Blake, Koch, Andrew, Graham, Heather, Syed, Saddaf. (2008). Addressing the Determinants of Health Together: A Resource Guide for Hospital-Community Collaboration. Dalla Lana School of Public Health, University of Toronto.
Poland, Blake, Krupa, Gene, McCall, Douglas. (2009). Settings for Health Promotion: An Analytic Framework to Guide Intervention Design and Implemenation. Health Promotion Practice.
Ramirez, Laura K. Brennan, PhD, Baker, Elizabeth A., MPH, PhD, Metzler, Marilyn, RN. Promoting Health Equity: A Resource to Help Communities Address Social Determinants of Health. Social Determinants of Health Workgroup at the Centers for Disease Control and Prevention. Department of Health and Human Services.
Solar, Orielle, Irwin, Alec. (2010). A conceptual framework for action on the social determinants of health. Social Determinants of health Discussion Paper 2 (Policy and Practice). World Health Organization: Geneva.
What are social determinants of health and health equity?
__ The social determinants of health are the factors in the society that support or act as barriers to the health of an individual, population, or community.
__ Health equity is when everyone has the opportunity to “attain their full health potential” and no one is “disadvantaged from achieving this potential because of their social position or other socially determined circumstance.”
What do we mean by developing a social determinants of health initiative in your community?
__ By addressing social determinants of health, rather than (or in addition to) focusing on specific health problems or issues, you can get at the root causes of the problem and create long-term change.
Why develop a social determinants of health initiative in your community?
__ A social determinants of health initiative demands a participatory process that involves all sectors of the community.
__ Aiming at social determinants helps to get at the root causes of inequity.
__ A social determinants effort addresses social change through the development of greater equity.
__ A social determinants initiative creates community partnerships that can endure, and be directed to other issues as well.
__ A social determinants effort uses the knowledge of those most affected, as well as others in the community.
__ Such an effort educates the community about health inequity and inequity in general.
__ As a result, a social determinants initiative can help to create a fairer, more equitable community that deals with discrimination and other equity issues.
__ A participatory social determinants effort can create new community leaders.
How do you develop a social determinants of health initiative?
Step 1: Assemble your partnership
__ Define your community.
__ Determine who should be included in the partnership.
__ Contact potential partners and convince them to participate.
__ Choose a facilitator.
__ Establish guiding principles for the partnership.
Step 2: Focus your partnership on social determinants of health
__ Assess social determinants.
__ Develop a vision and mission.
__ Identify and prioritize goals and objectives.
Step 3: Building capacity to address social determinants of health
__ “Community capacity” refers to the resources, infrastructures, relationships, and operations that enable a community to create change – community assets, in other words.
__ Assess community capacity.
__ Build community capacity.
- Develop a shared language and common understanding among partners and community members of how social determinants influence health.
- Involve as many people, organizations, and sectors as possible in the planning and implementation of your initiative.
- Identify and use existing social networks and relationships to inform more people and involve them in the initiative.
- Identify useful assets that community members and organizations can bring to the effort.
- Share information with the community about social determinants, the results of your assessments, and the vision and mission of your initiative.
Step 4: Selecting your approach to create change
__ Consciousness raising.
__ Community (locality) development.
__ Social action.
__ Health promotion.
__ Media advocacy.
__ Policy and environmental change.
Step 5: Planning for action
__ Assemble a planning team.
__ Develop your action plan.
__ Implement your plan.
Step 6: Assessing your progress
__ Evaluate process.
__ Evaluate impact.
__ Evaluate outcomes.
__ Evaluate your efforts.
- Formulate evaluation question
- Structure the evaluation.
- Make the evaluation as participatory as possible.
__ Link your evaluation to your community assessment and action plan.
__ Share your work.
Step 7: Maintain momentum
__ Remain flexible and dynamic.
__ Combat fatigue and burnout.
__ Sustain the partnership and the work.
__ Keep at it indefinitely.
Example #1: Creating Healthy Child Development at the Mitumba Informal Settlement, Nairobi, Kenya
Mary Amuyunzu- Nyamongo, African Institute for Health and Development
Urban informal settlements, more commonly referred to as “slums,” are home to almost one billion people globally, including one-third of those living in cities in developing regions. Such settlements provide some of the harshest conditions found in any collective living arrangement due to overcrowding, poor sanitation, and minimal access to essential resources. These conditions also result in stigmatization, social isolation, and discrimination. In Africa, people in urban settlements experience more morbidity and mortality than rural residents and have less access to health services. Children are hit hardest by these conditions, with under-five mortality 35% higher among children in Nairobi settlements than among children in rural Kenya.
Mitumba, a Kiswahili term meaning “second hand” or “used,” is a Nairobi settlement of approximately 18,000 people established in 1992. Mitumba is smaller than other Nairobi settlements and consequently has received little attention or support from governmental or other organizations. In 2006, the African Institute for Health & Development (AIHD), with support from the U.S. Centers for Disease Control and Prevention, established a partnership with residents of Mitumba to undertake a pilot project to promote healthy child development. AIHD is a Nairobi-based non-governmental organization (NGO) with multidisciplinary staff including anthropologists, sociologists, economists, and education specialists established in 2004 to conduct research, training, and advocacy on health and development issues.
The goal of the Mitumba project is to facilitate empowerment processes with mothers of under-five children to improve health; these include increased access to health information, safety, and early child development opportunities. The project follows general principles of community-based participatory research (CBPR), fully engaging mothers of under-five children, community health workers, and community leaders throughout the entire project period. CBPR goes beyond simply educating people, which usually involves interventions imposed on communities by outsiders, to an approach inspired by the Brazilian community organizer Paulo Freire. In his 1968 work, Pedagogy of the Oppressed, Freire describes a process which actively involves community members and organizations in developing the capacity to improve their own political and economic circumstances, as well as their health and well-being. Communities are encouraged to take control of their situations and to collectively improve them through cycles of planning, action, and evaluative reflection. The rationale here is that the beneficiaries must drive the improvement and promotion of their own health with effective and sustainable strategies if significant long-term change is to take place.
To help all residents and AIHD gain clarity about living conditions in Mitumba, a 10-day social mapping project was conducted with youth and adults to understand community resources and boundaries. Mothers took part in surveys and focus group discussions to identify community conditions and norms affecting maternal and child health. In interviews, key informants provided insight into community issues and challenges. Participatory processes informed the design of the questionnaires as well as efforts to assure respondents of confidentiality.
The findings revealed that Mitumba has three narrow roads passable by car during non-rainy seasons, six narrow paths for foot traffic, four churches, one school, and no health facilities. Housing structures are small and crowded: in 68% of the households, 3 to 5 people share a single 10' _ 10' room for both cooking and sleeping; only occasionally does the living space include a toilet. Most houses are made of metal sheeting and plastic, and have dirt floors. Water, available from community taps, is purchased at high prices and is mostly unclean because the vendors who supply the water use low quality pipes. Toilets, constructed by landlords, are shared by large numbers of people, poorly maintained, and often full. Children are not allowed to use them because of these conditions and because the holes are too big, creating safety concerns. Consequently, most children eliminate their waste on the open ground, causing serious sanitation problems. The sole community school in Mitumba has six classrooms, none of which has doors, windows, desks or books. The nearby city council school does not accept children from settlements. Some children attend private schools but most families cannot afford the fees.
Some 65% of the mothers in Mitumba have received primary education and 35% a secondary education. Most residents engage in casual labor in industrial areas or construction sites. Women work in nearby wealthy households, although more than half were unemployed at the time of the baseline study. Poor economic conditions limit access to safe, affordable child care when mothers work or run errands. Young children (0–3 years) are usually left with neighbors who are not obligated to feed or clean them; older children (3–5 years) are usually left outside of the locked house. Children are often seen looking for food, loitering around neighboring houses, or sleeping on the ground when their mothers are away. Mothers reported that the major concerns facing young children include lack of food (20%) and diseases (42%), including malaria, respiratory infections, and diarrhea and vomiting. Due to lack of access to health services and limited economic resources, mothers stated that when their children are sick they frequently rely on chemists (pharmacies) and drug vendors who often sell inadequate or inappropriate remedies. Thus, 20% of households reported at least one child having died.
With this information, organizers held a consensus-building forum with mothers to identify and prioritize their needs and to enable them to think of homegrown, practical approaches they could adopt and implement without stretching their scarce resources. The community decided upon three initiatives: establishing a day care center (the core project), soliciting support for the community school, and working with youth to enhance their ongoing activities and to open new horizons for them. Together, these initiatives support the overall goal of improved child health while also increasing skills and capacities among various groups in the community.
For example, the mothers stated that they wanted their children nurtured in a home environment staffed by older mothers with experience and training in child care and development. They identified two such mothers from the community, potential locations, and determined how much they could afford per child. The community members and AIHD jointly planned the intervention. They included a signed memorandum of understanding that defined roles and responsibilities for each group, in order to develop commitment and to safeguard against potential misunderstandings. They constructed the day care by refurbishing and expanding an existing facility.
The floors were cemented, fences added, and walls painted with bright colors and murals of story book characters. Fifteen mothers attended a training session to learn how to make toys and other items needed for the center. Additional sessions focused on nutrition, developmental needs and health and safety issues. Within a few weeks, the day care center reached full capacity, with 20 children, and the partnership began discussing the development of additional centers.
Additional Activities
Community members also stressed the importance of education for the growth of individuals, communities, and the nation at large. Current educational conditions in Mitumba make it difficult for the children to learn and thus fully participate in the world. During meetings with community members, the school chairman, and teachers, the partnership identified the need to: construct a fence around the school to ensure safety; obtain access to desks, textbooks, and writing materials; secure windows and doors; and pipe water in for personal hygiene and food preparation. The group developed a proposal to seek city council sponsorship.
Another serious problem in Mitumba is the lack of employment for youth which contributes to alcoholism, drug abuse, prostitution, and single parenthood. Using an approach similar to that adopted by the mothers, a partnership was established with
Tuff Gong, a community youth group in existence since 2004 that has been involved in environmental cleanliness, HIV and AIDS education, and football activities. Members started monthly cleanups but no longer have the equipment necessary to continue, and the partnership is seeking funds to support their activities. Evaluation activities for the pilot phase of the Mitumba project include review of the registers used to record implementation activities, before and after photography, periodic informal discussions with the community members, and end-of-project surveys.
(Lightly edited from “Community Interventions on Social Determinants of Health: Focusing the Evidence,” by Marilyn Metzler, Mary Amuyunzu-Nyamongo, Alok Mukhopadhyay, and Ligia de Salazar. In McQueen, D and C. Jones C, editors. Global Perspectives on Health Promotion Effectiveness. New York: Springer, 2007.)
Example #2: Addressing Social Determinants of Health in Baltimore
Baltimore Health Commissioner Leana Wen tells how the city is improving community health by addressing the underlying social determinants of health.
Example #3: Rolling Hills Apartments: Weaving Together Opportunities for Healthier Lives for a Diverse Immigrant Community

Twin Cities LISC, a local community development financial institution, has partnered with local organizations and city agencies to create quality affordable housing with improved healthcare access, including constructing a Federally Qualified Health Center. LISC also employed community health advocates to weave together the isolated health-related efforts in the neighborhood of focus into a cohesive health agenda. More specifically, they connect and help support existing efforts, identify and help address gaps, and facilitate the conversations and activities that sustain collaboration.
Learn how social determinants of health are being addressed to build healthier lives for immigrants in St. Paul, Minnesota in this Community Close-Up from the Building Healthy Places Network.
Contributed by Lia Thompson, University of Kansas, Community Tool Box Intern.
Example #4: Community Development 2.0—Collective Impact Focuses a Neighborhood Strategy for Health
The East Bay Asian Local Development Corporation (EBALDC) has built health into its strategic plan, and in the neighborhood revitalization work of The San Pablo Collaborative (SPARC), convened by EBALDC, health is the first priority. The San Pablo Area Revitalization Corridor neighborhood that stretches between downtown Oakland and Emeryville is considered to be one of the poorest and most disadvantaged areas of Oakland, California. Life expectancy in this area is up to 20 years lower than the neighboring area, Oakland Hills. SPARC works tirelessly to address the physical, social and economic factors-“social determinants”- that shape residents’ health in the San Pablo Avenue Corridor. SPARC partners work collectively in order to create an overall healthier environment for residents throughout the neighborhood. The California Hotel has been successfully preserved as affordable housing and a grocery store has been brought to this long abandoned neighborhood.
Learn how social determinants of health are being addressed to build healthier lives for the most disadvantaged areas of Oakland, California in this Community Close-Up from the Building Healthy Places Network.
Contributed by Lia Thompson, University of Kansas, Community Tool Box Intern.
Example #5: Community Health and Literacy Center, South Philadelphia, PA: A Hospital Partners with a City to Develop a Health, Literacy and Recreation Hub

Learn how social determinants of health are being addressed to build healthier lives by building a new, shared facility that would better serve the diverse residents of South Philly in this Community Close-Up from the Building Healthy Places Network.
Example #6: Columbia Parc at the Bayou District-New Orleans, LA: Holistic Redevelopment to Bring Lasting Change to a Distressed Neighborhood

Learn how social determinants of health are being addressed to build healthier lives, where mixed income housing, new schools, and a sustaining economic anchor completely transformed a once-struggling neighborhood in post-Katrina New Orleans in this Community Close-Up from the Building Healthy Places Network.
Example #7: Mobilizing to Overcome the ‘Geography of Inequality’ in St. Louis: For the Sake of All
In St. Louis, being born in zip code 63105 or zip code 63106 can make all the difference in the path your life takes, including how long you live. That was one of the main findings from the For Sake of All project report released in May 2014. What it highlights is deep structural and systemic changes that need to happen. Learn more about this initiative, and view GIS maps they created to better understand and communicate disparities in place here.

Example #8: The Brandywine Center: In Pennsylvania, Wealthy County’s Poorer Residents Get A Healthy Place To Live
Although Chester County, Pennsylvania, has been considered one of the richest counties in the country, seven percent of its half-million residents live in poverty. Coatesville, a city of 13,000 people, is one such low-income pocket. To combat this problem, the Brandywine Health Foundation (BHF) constructed the Brandywine Center, a community hub. The four-story building houses health and dental services on the first floor, behavioral care on the fourth, and 24 units of affordable senior housing on the two middle floors. The BHF is committed to working toward both improved neighborhood conditions and improved health in this low-income community.

Contributed by Lia Thompson, University of Kansas, Community Tool Box Intern.
Example #9: Community Health And Literacy Center: A Health, Literacy & Recreation Hub
The Community Health and Literacy Center, formed out of a collaboration between the Children’s Hospital of Philadelphia (CHOP) and the City as unexpected partners, worked together to bring a neglected neighborhood both improved access to health care and health, promoting recreation and literacy opportunities.
The center, which opened in the spring of 2016, is a first-of-its-kind hospital-city partnership. The project includes a CHOP pediatric clinic; a full-service community health center run by the city’s department of public health; a branch of the Free Library of Philadelphia; and a modern recreation center with a playground and green space, run by the city’s Department of Parks and Recreation. It offers welcoming outdoor space for the neighborhood and an indoor community meeting space. The location has excellent public transit access, with a subway stop on site. CHOP and the city are working to integrate services and programming as a way to have more of an impact on improving population health.

Contributed by Lia Thompson, University of Kansas, Community Tool Box Intern.
Example #10: Vita Health & Wellness District: Health at the Center of a Neighborhood Transformation
The Vita Health & Wellness District project was established through a partnership between the Stamford housing authority and Stamford hospital to revitalize an impoverished inner city area, in Stamford Connecticut, into a mixed-income community with expanded neighborhood services centered around a sustainable urban farm. Addressing the social determinants of health provide a framework for managing the neighborhood transformation in ways that would support and strengthen the existing community.
The Vita project is a great example of how a hospital can fulfill the Affordable Care Act’s mandate to engage its community by partnering to address the social determinants of health. The project also demonstrates how a forward-thinking community development organization can effectively partner with the health sector to pursue comprehensive community revitalization that could not have been achieved otherwise. These are still early days in what promises to be a fruitful and long-lasting partnership.

Read more about the Vita Health & Wellness District project on the Building Healthy Places Network blog.
Contributed by Lia Thompson, University of Kansas, Community Tool Box Intern.
Example #11: Revitalizing People and Place with a Healthy Food Hub Origin

Following the devastation of Hurricane Katrina in New Orleans, the founders of what became Broad Community Connections (BCC) began to attend community meetings, and investigate with their fellow community members how to rebuild a city in disarray. These discussions highlighted many of the problems that many central New Orleans resident had faced even before the storm, including but not limited to economic disadvantage, community disinvestment, health disparities, and lack of access to many needed goods and services. BCC was designed to revitalize Broad Street, a commercial thoroughfare running through the heart of the city and to connect several of the central city neighborhoods.
Founded in 2008, BCC set its sights on improving health and improving economic vitality in the area. Ultimately, the ReFresh project provided a high-quality grocery store to a low-income food desert and created a multi-faceted hub to improve healthy food access and local food systems, foster community connectivity, support youth development, and anchor economic development.
Read more about the ReFresh project in New Orleans on the Building Healthy Places Network blog.
Contributed by Lia Thompson, University of Kansas, Community Tool Box Intern.
Example #12: Under One Roof: Health Care and Social Services in the Same Place
The Chicanos Por La Causa (CPLC) is the largest community development corporation based in Arizona. CPLC is committed to building stronger, healthier communities as a lead advocate, coalition builder, and direct service provider. CPLC helps more than 200,000 people through programs in four areas–housing, economic development, education, and health and human services. CPLC recognizes that the needs of the families it serves are complex as a family rarely approaches the CDC with only one need. As a result, CPLC sought to establish cross-sector partnerships that would more effectively and holistically meet the needs of families.
Read more about CPLC on Rooflines - The Shelterforce Blog, from the National Housing Institute.
Contributed by Lia Thompson, University of Kansas, Community Tool Box Intern.
Example #13: Boston Children’s Hospital Community Asthma Initiative
The Community Asthma Initiative (CAI), an initiative of Boston Children’s Hospital, began addressing health disparities in Boston neighborhoods impacted by asthma in 2005. CAI provides an enhanced model of care, which includes asthma education and home visits for families with children ages 2–18 living in the Greater Boston area that were previously treated in the Emergency Department (ED) or hospitalized as a result of asthma. CAI works with partners and coalitions to address asthma health disparities by implementing changes in policies at the local and state levels. As of June 2014 there were reductions in the number of children with ED visits, hospitalizations, missed school days, and missed work days for parents.
Read more about the Community Asthma Initiative from the National Forum on Hospitals, Health Systems & Population Health.
Contributed by Lia Thompson, University of Kansas, Community Tool Box Intern.
Example #14: Columbia Gorge Hears From Everyone on Health: A Deeper Look
The Columbia Gorge is a vast rural area characterized by extremes. Near the coffeehouses and boutiques of affluent neighborhoods are remote towns in which residents live in poverty and the nearest doctor’s office may be an hour away. To combat these disparities, the governor of Oregon signed into law a new system for managing federal dollars for the medical needs of low-income residents by dividing and creating action plans for each of the 16 divisions of Oregon, ultimately shaping policy and improving health.
Contributed by Lia Thompson, University of Kansas, Community Tool Box Intern.
Example #15: Louisville’s Focus on Health Equity: A Deeper Look
In Louisville generational disparities are caused by many other systemic issues besides proximity to health care services including education, employment, air quality, housing, access to healthy food and various resources, etc. The city’s efforts in aiming to right historical wrongs and improve the lives of many Louisville families led the Louisville to be recognized as an RWJF Culture of Health Prize winner. Members from all of Louisville’s sectors including but not limited to the arts, business, health, education, law enforcement and social service have come together to lessen health disparities and neighborhood violence and to make the city’s health resources accessible to everyone.
Contributed by Lia Thompson, University of Kansas, Community Tool Box Intern.
Example #16: Manchester’s Weaving Health into the Community’s Fabric: A Deeper Look
Manchester’s community leaders are facing a very tough challenge: Restoring health and well-being throughout Manchester’s neighborhoods, which are plagued by poverty, violence, homelessness and the effects of the opioid epidemic that has brought negative attention to Manchester and other nearby cities. Manchester’s health promotion efforts focus on the creation and restoration of communities with an emphasis on strong support networks.
Contributed by Lia Thompson, University of Kansas, Community Tool Box Intern.
Example #17: Miami’s Goal of Health for All: A Deeper Look
Miami is facing pressing social and health risks, as 20% of Dade County’s residents live below the federal poverty line, including 1 in 3 children. Over 30% of the population is uninsured, 60% of adults are overweight or obese, and many neighborhoods lack access to affordable healthy food or safe parks. In 2003 the Consortium for a Healthier Miami-Dade County was formed to improve the overall health of the county. The consortium partnered with 160 organizations to focus on and target factors that impact health.
Contributed by Lia Thompson, University of Kansas, Community Tool Box Intern.
Example #18: Use of Photovoice by the Roma Community in Seville, Spain
In this interview with Daniela Miranda, doctoral student at the Universidad de Sevilla, we learn about the use of Photovoice among a disenfranchised, marginalized group of Roma neighbors in Seville, Spain. The Roma community comprises the largest ethnic minority in Spain and Europe. The Roma community experiences disproportionate social marginalization and discrimination manifested in high unemployment rates and poor health outcomes. The Roma neighbors used photos as a tool for action to help them communicate poor living conditions.
Example #19: H.E.A.T. Report Solutions: NBC Community Development Corporation - Wyandotte County, Kansas
Example #20: It’s Not Just About the Buildings: How Community Development Organizations are Promoting Residents’ Mental Health

Around the country, housing and community development groups are increasingly stepping up to partner with residents to improve community well-being by proactively strengthening residents’ emotional and mental health. Read more.
Example #21: How communities are addressing the social determinant of access to housing:
The Collective Impact Forum's September 18th, 2023 podcast covers how complex issues such as homelessness can feel unsolvable or intractable, but that through a commitment to a collective approach and strategies, communities can end homelessness.
Speaking with Community Solutions' (a nonprofit that is dedicated to ending homelessness) president Rosanne Haggerty, the program Built for Zero is discussed, which is a program network of more than 100 cities and counties working to ensure that homelessness can be rare or brief in their regions.
Example #22: Pilot Project Directs Healthcare Resources to Rural Missouri

A pilot project has been announced that plans to improve health outcomes in rural Missouri communities. It’s a collaborative effort between the Missouri Department of Social Services and the MO HealthNet Division.
The Transformation of Rural Community Health (ToRCH) project focuses on addressing social care challenges that impact residents’ ability to maintain their health and manage chronic conditions.
“(It’s) a groundbreaking initiative that empowers and encourages rural communities to collaborate to address healthcare-related social needs among their Medicaid population, with a focus on driving better health outcomes,” said Robert Knodell, Missouri Department of Social Services Director.
One key focus of the project is to tackle social determinants of health that influence overall wellbeing – safe housing, transportation, access to healthy foods, and physical activity opportunities. The U.S. Department of Health and Human Services explained that these needs influence the conditions where people are born, grow, learn, work, play, worship, and age.
“For too long, our payment systems have failed to reward hospitals for efforts to address some of the root causes of poor health,” said Kirk Mathews, MHD Chief Transformation Officer, “The ToRCH program allows hospitals to receive payment for proactively addressing issues that contribute to poor health outcomes. Under this model, hospitals are empowered to truly be in the ‘healthcare’ business in addition to the ‘sick care’ business.”
Six rural hospitals were selected last June as part of the pilot project, in Salem, Clinton, Sedalia, Rolla, Bolivar, and Richmond. The funding allows them to act as community hubs.
Click here to read the full article at the MissouriNet website.
Tool #1: Sample Partnership Principles
Within our partnership, we have decided that partners must agree to adhere to the principles outlined below. These principles are based on the premise that all members seek, as a partnership, to create initiatives that build on the unique strengths and assets of the local community. To do so, all partners agree to respect the beliefs and cultural norms of others and to build trust and mutual respect to ensure that programs will be maintained and enhanced over time. The principles that guide our work are as follows:
We are committed to equity, collective decisions, and collective action.
- Knowledge originates and resides in all members of a group.
- All partners are encouraged to participate in all phases of the process.
- Information is shared among all partners.
- Differences in interpretation are addressed with respect for all partners.
- Efforts are made to ensure that the language used is heard and understood by all partners.
- Partners will recognize and honor that each partner brings different assets and different needs to the partnership.
We are committed to high-quality, ethical initiatives.
- We are committed to ensuring that no harm, including emotional and physical harm, is done to anyone affected by the initiative.
- We are committed to full and total disclosure of all information related to risk.
- Informed consent protects the initiative partners and participants as well as the affected community.
- Confidentiality will be maintained.
- Partners agree to act in a manner that is respectful to other partners, to the community, and to the organizations they represent.
- Partners will obtain appropriate human subjects review or approval prior to the collection of qualitative or quantitative data.
- Partners will obtain approval from the partnership to use data or publish findings.
We are committed to addressing social inequities that affect health, including those that constrain the meaningful participation of individuals and communities in the decision-making process.
- We are committed to processes that foster inclusion and will work against all forms of exclusion, such as racism, sexism, or homophobia.
- We are committed to ensuring all partners have an opportunity to participate in local governance, such as membership on city councils or school boards.
We will maximize opportunities for learning within the local community and associated organizations.
- We encourage shared leadership (i.e., decision making, meeting facilitation, direction and management of the partnership).
- We encourage shared input into the development, implementation, evaluation, and dissemination of partnership initiatives.
- We will actively seek financial and other resources that can benefit the community. This includes working with local partners to develop applications for funding.
Tool #2: The Basics of Media Advocacy
The Tool Box includes a whole chapter (Chapter 34) on this topic. The essential strategies of media advocacy include:
- Understand how to work with the media for mutual benefit.
- Get to know and involve media representatives.
- Create your own news stories that the media will want to cover – write them, suggest them, structure events and situations to make them.
- Use advertising to best advantage.
- Understand what to expect, and how to speak, behave, and convey information effectively when you’re being interviewed or otherwise questioned, especially if you’re on camera.
- Inform the media about your issue.
The basic steps of a media campaign:
- Decide on goals of your media campaign. Some possibilities might be public education, generating resources for your initiative, or creating public pressure for policy change.
- Identify your audience. This might be people at risk of certain conditions, potential volunteers, members of a particular community, the general public, etc.
- Involve the media, if they’re not already part of your partnership (they should be), in planning your media campaign.
- Plan your message. It should identify the problem, offer solutions, and tell the public what you want. It might simply convey information, ask for money or other resources, or call for action (votes; attendance at public events, calls, emails, or visits to legislators). The message should be easily understandable by everyone – in simple English and/or other appropriate languages, clear and straightforward.
-
Pick your channel(s) carefully. Concentrate on putting your message where it will reach your intended audience. Think about the medium itself –newspapers and other print, radio, TV, Internet (Within the Internet, you can use e-mail, websites, social media –Facebook, MySpace, Twitter, Flickr, etc.) Then target the area of the medium where you’re likely to find your audience – a Hispanic radio station, local-access cable channel, community newsletter, laundromat bulletin board, word-of-mouth from bartenders, hairdressers, etc.
Tool #3: Priority Populations Framework
Community Commons shares an Introduction to the Priority Populations Framework. This framework supports communities in identifying and prioritizing groups that are disproportionately impacted by inequities. It is organized into five key domains: race and ethnicity; gender and orientation; age and life stage; socioeconomic and legal status; and health, mental health, disability, and neurodiversity. By offering a structured approach to understanding disparities, the framework helps communities engage those most affected and design strategies that promote equity.
-
What is PACE EH?
-
Why use PACE EH?
-
Who should be involved in using PACE EH?
-
When should you use PACE EH?
-
How do you use PACE EH?
At one point or another, nearly every person whose work centers on serving community needs is introduced to a small, but insightful, morality play known as the “tragedy of the commons.” The allegory relates the consequences of uninformed individual consumption of community-held resources. In the tale, a group of herdsmen bring their livestock to a parcel of communally held land at different times throughout the year. Because each herder is selfishly concerned only about the welfare of his livestock, none takes responsibility for the well-being of the land itself. Overgrazing results in the eventual death of all the herders’ livestock. Had the herdsmen worked together and jointly accepted the responsibility for the upkeep of the land, all would have prospered…
The true “tragedy of the commons” has always been how easily such hardship could have, and should have, been avoided. Contemporary environmental health risks, mirroring the subtle yet predictable loss of land in the fable, have the potential to grow destructive through inattention and inaction. Application of the PACE EH methodology is a step towards ensuring that the “tragedy of the commons” remains an instructive fable rather than a glimpse of the future within the field of environmental health.
From PACE EH in Practice: A Compendium of Ten Pilot Communities. NACCHO, 2002.
Community health is more than simple freedom from disease for most individuals in the community. It encompasses the community’s involvement in the promotion of healthy behavior and conditions, in the prevention of disease and injury, and in the provision of health care for all. The World Health Organization (WHO) defines health as “a state of complete physical, mental and social well-being and not merely the absence of disease or infirmity.”
Given this wide-ranging view of health, communities can’t ignore the environments in which their residents live, work, and play. These environments must of course include the natural world, with its geographic features, its climate, and its plants and animals. But they also include the built environment – buildings, roads, and all the other human-created aspects of the modern world that surround us – and the social, political, and economic environments that we, as communities and societies, construct for ourselves.
When you consider health from an environmental perspective, it becomes clear that the issues raised go far beyond the standard concerns of most health providers, and can extend into such areas as community planning, environmental law, ecology, human rights, equity, economic development, construction techniques, climate change…the list can go on and on. Just about any community has a number of environmental concerns of various kinds. How can a community, and/or its health department or public health agency, decide what’s most important to tackle, and what can actually be accomplished?
In this section, we’ll profile the PACE EH process, which can help communities build partnerships to make good decisions about environmental health issues. We’ll explain the process and how it works, when and by whom it can be used, and how a community can use it to plan and implement an environmental health strategy.
What is PACE EH?
PACE EH (Protocol for Assessing Community Excellence in Environmental Health) is a process for assessing and analyzing the environmental health of communities and for creating plans to address threats and create improvements. The process and the partnerships it creates in the community then become the basis for regular reassessment of and attention to environmental health.
PACE EH was developed in partnership by the National Association of County and City Health Officials (NACCHO) and the National Center for Environmental Health (NCEH) of the U.S. Centers for Disease Control and Prevention (CDC), along with representatives of state, local, and federal environmental and health agencies and institutions. Before the PACE EH Guidebook was finalized, ten communities piloted the process, and their experience was used to inform the guidebook. The PACE EH Guidebook remains available through CDC/ATSDR. Much of the material in this section comes, either directly or indirectly, from the guidebook.
While the Guidebook provides a variety of tools and suggestions – many of them included in the Tools for this section – for making the process go smoothly, it emphasizes that these are intended as just those: tools and suggestions. They are meant to be used if they’re helpful, but to be changed or tossed aside in favor of more locally appropriate means when that’s necessary.
PACE EH is based on four underlying principles:
- A community-based environmental health assessment supports the core functions of public health.
The Ten Essential Public Health Services, originally released in 1994 and revised in 2020, describe the public health activities that all communities should undertake:
- Assess and monitor population health status, factors that influence health, and community needs and assets.
- Investigate, diagnose, and address health problems and hazards affecting the population.
- Communicate effectively to inform and educate people about health, factors that influence it, and how to improve it.
- Strengthen, support, and mobilize communities and partnerships to improve health.
- Create, champion, and implement policies, plans, and laws that impact health.
- Utilize legal and regulatory actions designed to improve and protect the public's health.
- Assure an effective system that enables equitable access to the individual services and care needed to be healthy.
- Build and support a diverse and skilled public health workforce.
- Improve and innovate public health functions through ongoing evaluation, research, and continuous quality improvement.
- Build and maintain a strong organizational infrastructure for public health.
- Strengthening leadership abilities in the field of environmental health will make local health officials more effective in ensuring the health of the community.
- Community collaboration is the cornerstone of a useful environmental health assessment process and of effective community planning.
- Principles of environmental justice, whether explicit or implicit, underlie the practice of sound local public health and environmental health.
PACE EH is designed to help communities explore and find the answers to a number of questions about their own environmental health:
- What are the connections between the environment — where people live, work, learn, and play — and human health and wellbeing?
- Are certain groups in the community currently experiencing, or likely to experience, an increased risk or disproportionate share of adverse health effects from environmental hazards?
- What can be done to protect human health and the environment?
- How appropriate and effective are current environmental health protection measures in the community?
- What are some of the key environmental resources in communities that should be preserved or protected?
The process intentionally says little about how to address specific environmental health issues, leaving that to each community. This is in keeping with a basic principle underlying PACE EH: that community members know their community best, and must be involved in the assessment of environmental health issues and in planning the actions designed to address them. The PACE EH process is meant to be inclusive and participatory from the beginning, involving both individuals from the community and organizations and agencies from all sectors.
The assumption is that the lead in assembling a coordinating body will be taken by the local or state public health department or board. While that certainly makes sense, there may be occasions where the process is started by concerned community members, or by another agency. The goal in either case is to form a partnership among a wide range of individuals (including individuals often left out of such discussions: residents with lower incomes and people from underrepresented racial and ethnic groups, people who speak languages other than English, youth), organizations, and institutions.
PACE EH was developed for use in the U.S. by an American government agency and an American NGO. There is no reason, however, why the process can’t be used, with appropriate adaptation where necessary, in other societies. Environmental health is a concern everywhere, and this is a process that doesn’t specifically rely on American resources, laws, or values. In some places, people may need more education and discussion about the meaning of environmental health than in others, but that doesn’t mean that they can’t understand or participate fully in the process.
PACE EH is constructed around 13 tasks
- Determine Community Capacity to Undertake the Assessment
- Define and Characterize the Community
- Assemble Community Environmental Health Assessment Team
- Define the Goals of the Assessment
- Generate the Environmental Health Issue List
- Analyze Issues with a Systems Framework
- Develop Appropriate Community Environmental Health Indicators
- Select Standards
- Create Environmental Health Issue Profiles
- Rank the Environmental Health Issues
- Set Priorities for Action
- Develop an Action Plan
- Evaluate Progress and Plan for the Future
We’ll discuss each of these tasks in more detail in the “how-to” part of this section.
While these tasks are laid out as a sequence, the guidebook emphasizes that each community is different, and that, in some cases, a community may work on more than one task at a time, or switch the order of some. Flexibility, which allows PACE EH to be adapted to the needs and concerns of each community that uses it, is an important element of the protocol.
Why use PACE EH?
- PACE EH is a participatory process. It seeks to involve all stakeholders in the community as much as possible. Participation of this kind is not only fair to those who will be affected by decisions the Community Environmental Health Assessment (CEHA) team makes, but it also has two other great advantages: First, it draws on the experience and knowledge of a broad range of community members, so that the final plan is likely to address the real needs of community members in a way that reflects their concerns. Second, it encourages ownership of the plan, because it was created by a group that represented the whole community and used residents’ ideas and concerns in the process. If community members feel ownership, they’ll support the plan and work to make it successful.
- The process brings together numerous people and organizations from various sectors, many of whom may not usually have contact. This lays the foundation for future collaboration in many areas, and makes coordination of services and efforts much easier.
- PACE EH takes a community perspective on health. The WHO, the CDC, and others have long realized that developing a healthy community depends on looking at the community as a whole. The availability and quality of medical care is only one of many factors that contribute to that development. The PACE EH perspective deals with as many of those factors as possible.
In 1986, WHO, in what has come to be called the Ottawa Charter, stated that a truly healthy community provides residents with peace, shelter, education, food, income, a stable ecosystem, sustainable resources, social justice, and equity.
- PACE EH is flexible. The process not only allows, but requires the community to set its own agenda, decide what it wants to work on, and plan how to reach its goals. The assumption of the process is that communities are different and that each needs to consider its unique character and needs in order to make real and lasting changes.
- The process helps empower communities to identify and use their own resources. It puts communities in control by helping them to understand how many assets they have and can use to address environmental health and other issues. Furthermore, by bringing together so many organizations, individuals, agencies, and institutions, it creates a resource – an interconnected and collaborative network – that can be activated again and again to maintain changes and address a variety of other community concerns as well.
- PACE EH looks at the environment in an inclusive way. It allows the community to define the environment as broadly as it needs to in order to get at the real context of community health issues. Thus, environmental health can include such issues as violence and substance use, which can create health problems directly, or the lack of transportation, which can hinder social connectedness, a proven health benefit.
- PACE EH raises the profile of the environment as the foundation and context of community health. Those involved in the PACE EH process, especially those whose experience has been in narrowly defined areas, can come to view both the term “environment” and the community environment itself in a different way. By the same token, the activities spawned by PACE EH can help to educate the community about the importance of the environment to health and about the concept of environmental health.
- Through the CEHA team and associated work groups, PACE EH builds leadership and connections for other initiatives and issues, health-related or not.
- The process is structured to keep all participants focused on the community and its concerns, rather than their own. It specifically provides suggestions to keep one-issue proponents from pushing their agenda at the expense of issues that are equally or more important to the community.
- PACE EH examines environmental issues in a systems framework. By looking at all the factors involved in an issue and analyzing how they interact, the CEHA team is more likely to get at real causes and effectively deal with problems or make improvements. The systems perspective helps communities find and target the pressure points of the system – the places where the whole system can be changed, sometimes by a relatively simple action – rather than simply treating the symptoms of a problem.
- Because of its structure, the PACE EH process is likely to have a real impact on community health. With its participatory nature, its whole-community and systems perspectives, and its view of the environment as the context of a healthy community, PACE EH is more likely than a more narrowly-focused process to lead to significant improvements in community environmental health.
Who should be involved in PACE EH?
An environmental health assessment is meant to benefit everyone in the community, however community is defined. Depending on the circumstances, the PACE EH process may be aimed at the whole community, at a particular area or neighborhood, at a particular population…there are many possibilities. Whatever the case, all stakeholders should be part of the process in some way – represented on the CEHA team, among workgroups or subcommittees, or consulted as part of data gathering and choosing issues.
Stakeholders include individuals who are or may be directly or indirectly affected by environmental health issues, those who provide services to or depend upon those people, those who might be asked to carry out actions to address environmental issues, concerned community activists and advocates, and policy makers and other officials who have the power to make changes in laws and regulations that can have an effect – positive or negative – on environmental health. Some examples:
People affected by environmental health issues
- Populations experiencing increased risk, particularly those who may face environmental injustice (residents with limited economic resources living in public housing built in an industrial neighborhood, for example)
- People with respiratory diseases or other environmentally-influenced health conditions
- Workers in jobs with dangerous or unhealthy conditions
In reality, everyone is affected by environmental health issues. Some populations, however, generally because of poverty or discrimination, have less control over their exposure to hazards and fewer opportunities for health-promoting activities and behaviors. Communities with limited economic resources and communities with large populations from underrepresented racial and ethnic groups may receive fewer services, and both physical and social environmental issues in those neighborhoods may be overlooked. People with asthma and other respiratory diseases are at the mercy of air quality, which may be bad everywhere, not just in their immediate area. Workers in some industries or facilities may have to endure unhealthy or dangerous conditions for fear of losing their jobs. These and other groups experiencing increased risk may gain a voice and some control over their situations by participating in a PACE EH process.
People indirectly affected by environmental health issues
- Landlords who might be responsible for removing environmental hazards, such as lead paint, from buildings or land
- Business owners who may have to change their use of products or methods
Individuals and organizations that provide services to affected populations
- Health professionals and institutions
- Human service organizations
- Educators and schools
- Public services – police, fire, EMS
Government
- Federal/state/local environmental agencies and officials, including Department of Public Works and similar functions
- Public health agencies – state/federal/county DPH, local boards of health
Advocacy and community groups
- Environmental organizations
- Community activists
- Faith communities
Others with a vested interest
- Business and industry
- Labor
- People with expertise in relevant areas – scientists, university professors, researchers, students, professionals
This is not a complete list, and the implication is not that all of these groups necessarily have to be involved in any given PACE EH process. It depends on the community, on the circumstances, on the issues, and on the population affected. An advantage of PACE EH is that it allows each community to determine who needs to be involved and how.
When should you use PACE EH?
PACE EH is a model that can and should be used at any time. There are, however, some specific situations when it would be particularly appropriate.
- When the community is experiencing rapid growth. Rapid development can have consequences to air and water quality, wildlife habitat, land use, food production, open space, housing cost and availability, the local economy, and many other areas that can affect environmental health. A PACE EH process can help to lessen the impact of fast growth and can lead to the encouragement of healthier building and land use.
- When a new commercial or residential development is being proposed. PACE EH can help the community understand current issues, assess how they will be affected by the proposed development, and help the developer find ways to make the project environmentally friendly.
- When a new industry is moving in. Most industry, even if it’s low-impact, carries environmental consequences. It may create pressure on housing or services by bringing more people into the community, or build in well-used open space. Agriculture can be responsible for major amounts of water pollution, caused by fertilizer runoff from fields and from manure piles and tanks. PACE EH can aid the community in understanding and anticipating possible impacts on environmental health and in planning to counteract them.
- When changes are proposed that will affect the natural environment. The new developments or industry mentioned above may fall into this category, but so do road building and road improvement, lumber operations, mining, dams, and even “green” installations, such as wind farms and solar power arrays.
- When there’s an upsurge in what might be environmentally-caused illness, or when community health seems to be deteriorating. Environmental factors involved in health changes might include the ability of the area to attract medical professionals, economic conditions, pollution, the introduction of new diseases or new vectors, changes in diet, or a host of other factors. PACE EH can help to identify and prioritize causes and lead to action to improve community health.
Vectors are living creatures that spread disease. Mosquitoes are a vector for malaria, for instance, because they can be infected with the parasite that actually causes the disease.
How do you use PACE EH?
Most of this part of the section comes from the PACE EH Guidebook for Local Health Officials, first published in 2000 and reprinted with a new foreword in 2008. The Guidebook is available through CDC Stacks and is also listed as a current environmental health resource by NACCHO and CDC/ATSDR.
The 13 tasks that make up the substance of PACE EH lay out the process. We’ll look at each of them in turn, but first, there are two pre-process considerations: initiating the process and dealing with long-standing distrust or bad feeling.
Initiating the process
One of the core assumptions behind PACE EH, as we’ve discussed, is that the local or state public health agency must be the convener, and that may usually be true. There may, however, be circumstances where the public health agency is unable or unwilling to take the lead. The agency may be hampered by lack of funding, over-commitment, or under-staffing. Public health officials may be unwilling to give up control to the community, may not see environmental health as a priority, or may feel that an environmental health assessment would be too controversial, and might hurt other necessary programs. Public health policy and actions are also sometimes driven by political or economic pressure, which may push against an assessment.
In any of these circumstances, another convener may have to step forward. This might be a community-based organization or coalition, a community health provider (a free clinic, an independent hospital), an environmental group, or even a determined and knowledgeable individual, to name just a few of many possibilities. The only requirements are a commitment to environmental health and the underlying philosophy of PACE EH and the ability to bring together all the necessary stakeholders to participate in the process…which leads us to the second pre-process issue.
Dealing with long-standing distrust or bad feeling
What if there is distrust of the logical convener – the public health agency – or general distrust or bad feeling among some of the organizations and/or individuals who need to be involved? When this is the case, a community PACE EH process is not likely to succeed without a fair amount of groundwork. Relationships need to be established or mended, trust needs to be built. It is far more difficult to convince organizations or individuals that have had a bad history to work together than it is to convince those who don’t know one another at all.
Once a convener has begun the process and has managed, if necessary, to create a climate where collaboration among the stakeholders is possible, work on the 13 tasks can begin.
A question: what should the first task be? The guidebook lists it as determining community capacity, but it seems that it could be instead assembling an inclusive planning team or at least an oversight body for the environmental health assessment process. It would no doubt be more efficient to have the public health agency conduct the first two tasks before starting to assemble a team, but community ownership and trust might be much greater, and therefore make the rest of the process easier, if the community were clearly involved from the onset. That said, we’ll examine the tasks in the order in which they appear in the Guidebook.
Task 1: Determine community capacity to undertake the assessment
The first order of business is to determine what resources are needed in order to carry out the assessment, and whether the community has and/or can reasonably expect to assemble those resources.
Specify the resources, skills, and capacities needed for assessment. The essential resources for any community undertaking are generally money, people, time, and technical skills of various kinds. The amount of funding, the number of people and the kinds of technical skills will vary with the needs of each community. Time refers both to the total amount of time an assessment will take, which may be as much as a year or two; and the amount of time the organizations and individuals involved can give to developing and implementing a plan to improve environmental health.
According to the guidebook, the essential skills and capacities needed include:
- community mobilization
- qualitative data management
- coalition building
- leadership
- communication
- public outreach
- strategic planning
- time management/project management
- survey methodology
- data collection and analysis
- group process
- epidemiology
- access to technical support
- public relations/marketing
- political savvy
Specify the available resources, skills, and capacities. The convener or lead agency, whether the public health agency or another, must have the internal capacity to coordinate and manage the assessment, a willingness to give up control, and the external relationships with other organizations and the community that give it the ability to assemble an inclusive planning group. In addition, community resources should be identified. Buildings, organizations and institutions, people, facilities, media – there are probably assets in all of these and other areas in practically any community. Finding and using them, through asset mapping or other means, is vital.
Review possibilities for collaboration. The next question to ask is whether the lead agency has or can develop the relationships necessary for a true community collaboration. Efforts should be made to understand and address rifts among organizations or within the community, so that a collaborative effort has a good chance of success.
Determine ability to carry out the assessment. At this point, it should be apparent whether or not there exist the local resources to carry out the PACE EH process. If not, engaging in the process can perhaps help to increase and strengthen them, although, in this circumstance, the effort will probably take longer.
Task 2: Define and characterize the community
The next step is to take a close look at the community you’ll be assessing.
Define the community. Community has many meanings. It most often refers to a geographic area with specific boundaries – a city, a town, a neighborhood, a distinct rural area – but it can also refer to any group of people with something important and identifiable in common – culture, race, ethnicity, class, language, occupation, or even ecosystem or watershed. Whom will the PACE EH assessment serve? You have to decide exactly where the borders – geographic, social, economic, and/or political – of your community are, and what and whom they include.
Describe the community’s characteristics, composition, organization and leadership. A community description includes demographics (age, gender, race, etc.), health data, socioeconomic statistics, physical characteristics (built and natural), educational status, language, culture, religion, major employers, and the like. Other key information concerns the history and current state of the community, its formal and informal leaders, its conflicts, and who influences its decision-making and how.
Refine the definition of the community as needed. As conditions change, and as time goes on, you should revisit your definition of community and make sure that it still represents the reality and doesn't define the effort either too broadly or too narrowly.
Task 3: Assemble a Community-based Environmental Health Assessment Team
The information you’ve gathered in the first two tasks should tell you who needs to be part of the CEHA Team.
Clarify expectations of team members. The roles, responsibilities, and rights of team members should be carefully framed. Clarity will help individuals and organizations decide whether to join the team, and will eliminate misunderstandings later.
Identify and invite individuals to help design and carry out the assessment. The team should represent various sectors. (See the “Who…?” part of this section above for examples of individuals and groups that might be included.) Its composition should also reflect the diversity and composition of the community, including, to the extent possible, youth; older adults; women; members of underrepresented racial, ethnic, cultural, and language groups; people from all socioeconomic levels; etc.
Determine a governing structure, decision-making structure, and ground rules. How will the team operate? The best answer to this question is usually developed by the team itself at the very beginning of the process. Whether there will be a chair and who it will be, how the work will be done and who will do it, meeting schedules and agenda-setting, whether there will be subcommittees and how they’ll be filled and structured, where resources will come from and who will be responsible for pursuing them, the ground rules for the work of the team (e.g., participate actively, deal with ideas rather than people, use conflict constructively, listen actively, respect others’ opinions, etc.) – all of these and more are questions that should be addressed at the very beginning by the team, so that work can proceed in an atmosphere of clear expectations and trust.
Task 4: Define the goals, objectives, and scope of the assessment
Involving the community in this task will help cement support for the process.
Establish goals and objectives for the assessment. Goals describe what you hope to ultimately accomplish. Objectives describe what you have to do to achieve your goals, and may often include a deadline.
Describe the vision that will guide the process. To get community ownership, the community should be engaged in helping to define the vision for the process. That may mean being kept up to date while a representative group drafts a vision statement, or it may mean that the community is directly involved (through public meetings, surveys, or other means) in creating the vision or in refining a statement that the CEHA team presents to them.
Describe the scope of issues to be addressed by the assessment. This is the process of deciding what will and won’t be included in “environmental health” for your community. The Guidebook provides a useful diagram to help the group think about this issue:

The size and position of the circle should vary – often greatly – from community to community, depending on how each sees its environmental problems and needs. A rural community may be very concerned with preserving open space and the ecology of the community, while an urban community might be more concerned with specific point sources of pollution or reducing the triggers for asthma. The scope of issues depends on the community’s circumstances, the resources available, and the way the community chooses to define environmental health.
Define key terms. “Health,” “environment,” and “environmental health” may mean different things to different communities. It’s necessary that CEHA team members (and the community) agree on the definitions of these and other relevant terms, not only to mark out the scope of the environmental health assessment, but to proceed in the future to address environmental health needs. The definitions may change as the community and its priorities change, and should probably be revisited at least annually.
Task 5: Generate a list of environmental health issues
With this task, the work starts to become more specific: what is the community actually concerned with, and what will the effort work on?
Evaluate and select data-gathering method(s). In the words of the Guidebook, “Community assessments are simultaneously research projects and efforts to engage the community around environmental health issues. Therefore, the process of gathering information on the community’s concerns needs to do more than build on the existing base of knowledge and gather additional community-specific information. It should also foster the community’s understanding of the project and provide opportunities for community engagement.”
The logical extension of this statement is the creation of a participatory action research project, where some or most of the data is not only supplied, but gathered, by members of the community. There are a number of advantages to this approach, including community participation and ownership; the greater openness of people when approached by those whom they know or can identify with; and the knowledge of community members about the reliability of informants, the community’s history, and the issues that affect the community most deeply.
There are a number of ways to gather data: written or oral surveys, formal or informal individual and/or group interviews, community forums, focus groups, and even direct observation. Data gathering can be structured and formal, or more informal, can focus on quantitative or qualitative methods, or can combine different techniques. What you choose will depend on your resources (formal randomized surveys are usually conducted by consultants, and can be very expensive), the nature of your community, and the preferences of the CEHA team.
Collect data on community concerns. Use the methods and researchers you’ve chosen to gather data about what the community sees as environmental health issues.
Collect data on community knowledge, attitudes, behaviors, and perceptions. To understand community concerns, it’s important to also understand what community members know, don’t know, and would like to know about environmental health conditions; their attitudes about environmental health and health risks; behaviors they engage in that can put them or others at risk for or protect them from environmental health threats; and how they perceive the risk posed by various environmental health issues.
Risk perception is often based on factors that have little to do with actual risk. People often respond to sensational media reports or to spectacular events more strongly than to day-to-day occurrences. Thus, community members may feel that they are at increased risk of experiencing crime, even when crime is dramatically decreasing, because of the way violent crime is reported, or because of an acquaintance’s experiences or fears.
Create a manageable list of issues. Any community might have a host of potential environmental health issues. In order to whittle the list down to a reasonable number, the Guidebook suggests asking some pointed questions of each possibility:
- Does the issue fall within the intended scope of the assessment?
- Does the issue represent a relationship between the environment and human health?
- Is it a local concern?
- Was this an issue identified by a significant majority of the public?
- Can other information from the community support the inclusion of this issue?
Task 6: Analyze the Issues with a Systems Framework.
Systems theory assumes that no issue exists in a vacuum. Each is both caused and structured by a much larger system that includes the context – physical, geographic, social, etc. – in which it exists and the factors and conditions – climate, behaviors and policies that increase or decrease its effects, people who are harmed and benefited by it, community attitudes about it, the science that makes it possible or that can change it, to name just a few – that contribute to it. “In the framework, environmental health status is described by linking contributing factors – public policy decisions and personal behaviors – with exposure factors that describe how and where affected populations are exposed to environmental agents/conditions and the public health protection factors that are implemented by individuals or communities and reflect the collective capacity to address environmental health issues” (Guidebook, p.29):
Name of Issue
Understand the framework. In order to use this framework effectively, it’s important to understand what the elements of it refer to, and how they fit together and affect one another. From the Guidebook:
- Contributing factors are the activities, practices, or behaviors of society or individuals that affect environmental conditions or that place individuals at potential health risk.
- Environmental agents and conditions are chemicals, biologic agents, radiation, and other physical conditions in the built or natural environment that may be connected to human health, environmental quality, or quality of life.
- Exposure factors describe how and where people are exposed to potentially hazardous environmental agents or conditions. These include the place of exposure, activities that can lead to exposure, and route of exposure.
- Affected populations are groups who may be at risk of exposure. They are any segment of the community that is likely to experience the health state of interest or to be affected by the environmental condition.
- Public health protection factors are the personal protection factors (individual behaviors, such as wearing protective gear and getting immunizations) and community protection factors (community actions or systems – pollution control regulations, mosquito control) that can either modify or prevent an environmental health concern, or maintain an area of environmental health quality in the community.
- Environmental health status can be described in terms of an acute or chronic health condition or quality of life concern that is known or suspected to be environmentally related. Issues may reflect existing concerns or potential future concerns if preventive measures are not maintained or initiated.
Identify the connections among health status, affected populations, exposure factors, environmental agents/conditions, contributing factors and behaviors, and public health protection factors for selected environmental health issues. To use the framework, pick a topic, consider why it is a community concern, and plug topic and concerns into the diagram, filling in the various boxes and examining the connecting lines among them. This will give you a graphic description of the system that supports the issue. Tool #1 has an example of a filled-in framework diagram.
Task 7: Develop Locally Appropriate Indicators
The goal here is to take the connections that you mapped in the last task and turn them in to quantitative (i.e., expressed in numbers) indicators (measures) that will make it possible for you to track changes in various contributing factors, in individual issues, and in overall environmental health.
Develop a list of potential indicators. Begin by taking each factor you filled in on the framework diagram and translating it into a measure. If wearing protective gear in a particular job was a contributing factor, for instance, the indicator for it might be the percentage of workers wearing protective gear on the job. Tool #2 has an example of a filled-out framework map translated into indicators.
Depending on the complexity of the issue, you may have a large number of potential indicators. How will you decide which you’ll use?
Identify key indicators based on selected criteria. The indicators you choose should make sense in terms of local conditions, and should meet some other basic criteria. They should be simple, each clearly measuring just one thing. They should be understandable to the team and the public, and should reflect team agreement. Each should be acceptable to the community and address its concerns. Indicators should be measurable – able to be expressed in numbers and to be compared. And finally, indicators should be defensible, clearly showing a relationship between contributing factors and environmental health status.
Another description of good indicators can be found in Creating Objectives. It’s abbreviated SMART + C: Specific, Measurable, Achievable, Relevant, Timed (with a date for completion), and Challenging.
Task 8: Select Standards Against Which Local Status Can be Compared
While indicators allow you to see whether there are changes in the chosen issues over time, the question remains as to what is an acceptable or “good” level to reach for. There are few generally accepted standards that apply to environmental health, but some possibilities exist, and others can be generated locally.
Identify externally driven standards. The Guidebook gives examples of standards available when it was developed, but current users should look to more recent sources. The environmental health objectives of Healthy People 2030 may be helpful. Another possibility is to use for comparison current state or federal standards, levels, or percentages of people affected by the issue, where such measures are available.
Agree upon locally appropriate standards. There may be current data available to provide a starting point (the number of children with elevated blood lead levels, for example, or the percentage of people in the community who have respiratory illnesses). If a goal is to eliminate lead paint and other lead contamination, for instance, it might be reasonable to set a standard of no new cases of children with elevated blood lead levels after a certain date. A more difficult issue – e.g., respiratory illness tied to air quality – might have less ambitious goals, since the community may have less control over its environmental causes. Factories hundreds of miles away or thousands of cars a day traveling on interstate highways that run through the community may be major factors in determining air quality, and are probably beyond the ability of the local PACE EH effort to influence significantly.
Task 9: Create Issue Profiles
The point of this task is to describe all issues in similar terms, so that it will be easier to compare them when prioritizing them as part of the next task.
Adopt a standardized format for organizing information. The Guidebook provides a sample format that organizes each issue around the aspects of it the team has already explored: its scope, its background (local conditions and community input), the external and local standards the team has chosen, its community-specific indicators (including environmental health status, affected populations, exposure factors, environmental agents/conditions, contributing factors and behaviors, and public health protection factors, all from the issue map), sources of data about it, and the team’s analysis of it.
Gather information. Much of the information necessary may already have been gathered. Try to get similar types of information for each issue, so they can be easily compared. Federal, state, and community-by-community statistics; scientific background supplied by members of the team or a local university; local history of the issue related by key informants – all of these and many more types of information may go into the overall package.
Collect data for locally developed indicators. Here again, many sources will probably be needed, and a lot more of them will rely on the team’s own data-gathering. Both archival – federal, state, and local statistics, census data, etc. – and original sources are necessary, so team members may be interviewing and surveying community members, conducting forums and focus groups, and tracking down local organizational and institutional data (police and hospital records, numbers of local people using SNAP benefits, participation in various human service programs) in order to flesh out various issues and develop profiles.
Develop a summary statement. Finally, prepare a description of each issue explaining it and summarizing the data you’ve collected in each category. You’ll use these statements in the next task.
Task 10: Rank issues
Now, it’s time to rank the issues: how do the issues the team has identified stack up in terms of their importance to the health of the community?
Determine the purpose of ranking. What are you trying to accomplish in your ranking? Is it more important that the rankings reflect the perceptions of the community, that they identify the issues associated with the most immediate health problems, that they pinpoint the issues that most seriously affect particular populations (children, people experiencing poverty, people from underrepresented racial and ethnic groups)? Each of these intentions calls for a different emphasis when ranking issues.
Decide on ranking criteria. It’s important, if you’re hoping to rank issues rationally, to compare them according to the same criteria. Tool #3 shows the Guidebook's worksheet to get started, but more discussion and more or different categories are likely to be needed in many communities. Some common criteria might include:
- The importance of the issue to the community
- The seriousness of the issue (Are people likely to die if it isn’t addressed immediately, for instance?)
- Whether it affects a geographically or ecologically sensitive area
- Whether it disproportionately affects a population experiencing increased environmental health risks
- How much real data is available or can be obtained about it
- Whether there are policies in place that relate to it or regulate it
- How well the community at large understands the issue, and how strongly it will support addressing it
Select a method for ranking. This is really an extension of the first two parts of this task. Once you have a set of criteria, you have to decide how you’ll use them. Will you score each with a number, with a value (e.g., 1-5, with 1 being unimportant, 5 being very important; or 1 for a yes, 0 for a no), or simply rank issues in order after considering their positions on each criterion? Will one criterion be worth more than another because of your purpose in ranking? (For example, should the score for importance to the community be multiplied by 2 if you’ve decided that community perception is a deciding factor?)
Rank the issues. Will the team as a group score issues, or should each member score them individually, with the results added or averaged afterwards? In addition to scoring, ranking may require a good deal of discussion and back-and-forth on the part of the team. Ultimately, ranking is a matter of opinion – there are generally no pure right answers – so the process will benefit from team members explaining their reasons for ranking as they do, and factoring those reasons into the final result.
Task 11: Set priorities for action.
Priorities are different from ranking in that they will identify the issues the team will actually adopt to work on. The process is similar to that for ranking.
Determine local priority-setting criteria. The criteria in this case are meant to be practical as well as based on the rank of the issue. They include such categories as political and public support for the issue, the likelihood that the community can have an effect on it, the legal implications of tackling it, the consequences of not addressing it, and the community’s perception of the risk it poses. Tool #4 from the Guidebook provides a worksheet as a starting point.
Select a method for prioritizing. As for the previous task, this is a matter of how the team will score categories, what weight it will give to each, and how it will determine an overall score for each issue.
Determine priorities. Finally, the team will come up with a list of the issues it intends to work on. Again, there have to be decisions about how this will be done – solely by scores, whether averages or totals; through discussion of the scores and the issues; by some agreed-upon voting procedure; etc. How many issues are on this final list depends upon the team and community resources and the ease with which it seems issues can be resolved. The number might be relatively large if the plan is to work on one, then the next, until all have been addressed, with the understanding that such a plan may take several years – even a decade or more – to carry out. If the time line is shorter, the list of issues should be shorter as well – probably no more than two or three.
Task 12: Develop an action plan.
Once the issues to address have been chosen, the CEHA team must plan how that can be done. We’ll look briefly at the Guidebook steps in that process. (See also Chapter 8, Developing a Strategic Plan.)
Develop goals and objectives. For each issue, long-term goals (final outcomes) and shorter-term objectives (what has to be done to accomplish the goals) have to be determined. It’s often helpful to institute a participatory process for this, either by including more community people on various subcommittees or by asking for ideas and opinions from the community and acting on what they say.
Identify contributing factors. The team has already done this in Task 6.
Identify possible interventions and prevention activities. How will you go about changing the situation? Which factors can be affected by what interventions? What can be done with the resources available to the community?
Identify community assets. What institutions, organizations, people, facilities, and skills already exist in the community that can contribute to the effort?
Identify potential barriers. What are the legal, logistical, geographic, social, physical, political, and economic factors that might make addressing a particular issue difficult, and how can they be countered?
Select an intervention(s)/activity(ies). Decide what the team will actually do.
Determine resource needs. What are the funding, personnel, skills, and time needs to carry out the proposed interventions, and where will they come from?
Identify potential partners. Identify and bring in the organizations, individuals, institutions, businesses, and government officials and agencies that are needed or can help the team reach its goals.
Provide training. Determine what training is needed, and for whom, in order to turn the plan into reality, and arrange for that training to take place.
Develop timeframe. This is not just an overall timeframe, although that’s part of it (e.g., the effort will take a total of three years.) There should be a target for each phase of the plan – recruiting of partners, hiring (if necessary), completion of training (if necessary), determination of baseline data for evaluation, start of implementation, etc.
Determine measures of success. What are the specific measures the team will aim at? (By x date, x number of children will receive immunizations. By x date, the prevalence of the issue in the community will have been reduced by 15%.)
The Tool Box would add here the development of an evaluation of the implementation of whatever interventions or other activities are part of the action plan. Monitoring and evaluation of the process, impact, and outcomes of the implementation are an important part of taking action, and they should start at the very beginning of any implementation. They allow you to see where you need to adjust, add, change, or scrap elements of what you’re doing in order to improve effectiveness. Chapters 36, 37, 38, and 39 have more on evaluation.
Task 13: Evaluate progress and plan for the future
As with any process or initiative, it’s crucial to evaluate what you do.
The Community Tool Box would suggest that your evaluation plan be one of the first things you tackle in setting up the PACE EH effort, so that you can monitor your activities and progress from the very beginning.
Agree on the questions to be answered by the evaluation. What do you want to know about the assessment effort? Will you examine the process (the degree of involvement and collaboration among the stakeholder groups and individuals, how well timelines were observed, how work was distributed, how efficient the process was, etc.); the impact (what you actually did – e.g., conducting a certain number of interviews, distributing and receiving back a certain number of surveys); and/or the outcomes of the assessment (how close the effort came to meeting its goals, progress on implementation, other results that are important to the community, such as improved collaboration among various sectors or agreement to continue the assessment effort indefinitely)?
Evaluate the success of the assessment process. How well has the assessment process served the community by making possible the addressing of important environmental health issues? Have structures been created that will help the community continue to improve environmental health? Did the assessment process raise the profile of environmental health in the community and among the organizations, agencies, and officials that make up the public health system?
Begin preparations for ongoing community-based environmental health assessment activities. This is the PACE EH version of advice you’ll see everywhere in the Community Tool Box: keep at it indefinitely. Conditions change, formerly unknown environmental health issues surface, populations shift. Communities have to keep up with these changes, and to continue to plan and to alter their current activities and interventions to match emerging needs. The PACE EH process can and should be conducted on an agreed-upon regular basis, as should monitoring the community’s environmental health status, demographics, and other environmental-health related areas. In that way, communities can see issues developing, and address them before they become problems. Continuing the process can help make yours a healthy community.
In Summary
PACE EH provides a structure for assessing a community’s environmental health and identifying current or emerging issues in that area. Because of its emphasis on collaboration and community involvement, it creates a climate for community problem-solving, not only in relation to environmental issues, but for community issues in general. PACE EH also sets the stage for regular assessments, so that environmental health remains in the community’s consciousness, and doesn’t have to be approached as if it’s new every time there’s an environmental health issue to address. Overall, the use of PACE EH can be a vital part of creating and maintaining a healthy community.
We encourage the reproduction of this material, but ask that you credit the Community Tool Box: /.
Contributor
Phil Rabinowitz
Andrea Glinn, Editor
Resources
Online Resources
Generation tree: Meet the UK’s original green activists from Trees for Life: Breathing Life into Your Neighborhood.
Healthy People 2030. The CDC's objectives.
NACCHO (National Association of County & City Health Officials).
PACE EH on the CDC (Centers for Disease Control) website.
PACE EH Community Environment Health Assessment (CEHA).
PACE EH in Practice: A Compendium of Ten Pilot Communities. NACCHO, 2002. Results of the original ten PACE EH pilot studies. Also available as either a free pdf download or as a for-a-fee hard copy.
PACE EH: Protocol for Assessing Community Excellence in Environmental Health – a Guidebook for Local Health Officials. NACCHO (National Association of County and City Health Officials) and CDC (Centers for Disease Control and Prevention), 2000, reprinted 2008. Available, in English or Spanish, free as a pdf file or for a price as a print document at the NACCHO website.
The Power of PACE EH, a slide and video presentation of a PACE EH process in Wabasso, Florida. Narrated by Julianne Price, the Florida Environmental Health official who oversaw the project.
Print Resources
PACE EH Post Project Assessment of Quality of Life Changes in a Florida Community Related to Infrastructure Improvements. Laurel Harduar-Morano, M.P.H., Julianne R. Price, R.S., Daniel Parker, M.S.P., Carina Blackmore, D.V.M., Ph.D. Journal of Environmental Health, vol.70, #10, June 2008, pp. 40-47. An article about Wabasso.
What is PACE EH?
__ PACE EH is a process for assessing and analyzing the environmental health of communities and for creating plans to address threats and create improvements.
__ It is constructed around 13 tasks:
- Task 1: Determine Community Capacity to Undertake the Assessment
- Task 2: Define and Characterize the Community
- Task 3: Assemble Community Environmental Health Assessment Team
- Task 4: Define the Goals of the Assessment
- Task 5: Generate the Environmental Health Issue List
- Task 6: Analyze Issues with a Systems Framework
- Task 7: Develop Appropriate Community Environmental Health Indicators
- Task 8: Select Standards
- Task 9: Create Environmental Health Issue Profiles
- Task 10: Rank the Environmental Health Issues
- Task 11: Set Priorities for Action
- Task 12: Develop an Action Plan
- Task 13: Evaluate Progress and Plan for the Future
Why use PACE EH?
__ PACE EH is a participatory process.
__ The process brings together numerous people and organizations from various sectors, many of whom may not normally have contact.
__ PACE EH takes a community perspective on health.
__ PACE EH is flexible.
__ The process helps empower communities to identify and use their own resources.
__ PACE EH looks at the environment in an inclusive way
__ PACE EH raises the profile of the environment as the foundation and context of community health.
__ Through the CEHA team and associated work groups, PACE EH builds leadership and connections for other initiatives and issues, health-related or not.
__ The process is structured to keep all participants focused on the community and its concerns, rather than their own.
__ PACE EH examines environmental issues in a systems framework.
__ Because of its structure, the PACE EH process is likely to have a real impact on community health.
Who should be involved in using PACE EH?
__ People affected by environmental health issues, including:
- Vulnerable populations
- People with environmentally-influenced health conditions
- Workers in dangerous or unhealthy jobs
__ People indirectly affected by environmental health issues, including:
- Landlords who might be responsible for removing environmental hazards
- Business owners who may have to change their use of products or methods
__ Individuals and organizations that provide services to affected populations, such as:
- Health professionals and institutions
- Human service organizations
- Educators and schools
- Public services – police, fire, EMS
__ Government
- Federal/state/local environmental agencies and officials
- Public health agencies – state/federal/county DPH, local boards of health
__ Advocacy and community groups
- Environmental organizations
- Community activists
- Faith communities
__ Others with a vested interest, such as:
- Business and industry
- Labor
- People with relevant expertise – scientists, researchers, professionals, etc.
When should you use PACE EH?
__ When the community is experiencing rapid growth.
__ When a new commercial or residential development is being proposed.
__ When a new industry is moving in.
__ When changes are proposed that will affect the natural environment.
__ When there’s an upsurge in what might be environmentally-caused illness, or when community health seems to be deteriorating.
How do you use PACE EH?
__ Choose a convener, whether a public health agency or official or some other trusted entity.
__ Deal with longstanding mistrust, turf issues, and factionalism.
__ Task 1: Determine community capacity to undertake the assessment.
- Specify the resources, skills, and capacities needed for the assessment.
- Specify the available resources, skills, and capacities.
- Review possibilities for collaboration.
- Determine ability to carry out the assessment.
__ Task 2: Define and characterize the community.
- Define the community.
- Describe the community’s characteristics, composition, organization and leadership.
- Refine the definition of the community as needed.
__ Task 3: Assemble a Community-based Environmental Health Assessment Team.
- Clarify expectations of team members.
- Identify and invite individuals to help design and carry out the assessment.
- Determine a governing structure, decision-making structure, and ground rules.
__ Task 4: Define the goals, objectives, and scope of the assessment.
- Establish goals and objectives for the assessment
- Describe the vision that will guide the process.
- Describe the scope of issues to be addressed by the assessment.
- Define key terms.
__ Task 5: Generate a list of environmental health issues.
Evaluate and select data-gathering method(s).
- Collect data on community concerns.
- Collect data on community knowledge, attitudes, behaviors, and perceptions.
- Create a manageable list of issues.
__ Task 6: Analyze the Issues with a Systems Framework.
- Understand the framework.
- Identify the connections among health status, affected populations, exposure factors, environmental agents/conditions, contributing factors and behaviors, and public health protection factors for selected environmental health issues.
__ Task 7: Develop Locally Appropriate Indicators.
- Develop a list of potential indicators.
- Identify key indicators based on selected criteria.
__ Task 8: Select Standards Against Which Local Status Can be Compared.
- Identify externally driven standards.
- Agree upon locally appropriate standards.
__ Task 9: Create Issue Profiles.
- Adopt a standardized format for organizing information.
- Gather information.
- Collect data for locally developed indicators.
- Develop a summary statement.
__ Task 10: Rank issues.
- Determine the purpose of ranking.
- Decide on ranking criteria.
- Select a method for ranking.
- Rank the issues.
__ Task 11: Set priorities for action.
- Determine local priority-setting criteria.
- Select a method for prioritizing.
- Determine priorities.
__ Task 12: Develop an action plan.
- Develop goals and objectives.
- Identify contributing factors.
- Identify possible interventions and prevention activities.
- Identify community assets.
- Identify potential barriers.
- Select an intervention(s)/activity(ies).
- Determine resource needs.
- Identify potential partners.
- Provide training.
- Develop timeframe.
- Determine measures of success.
__ Task 13: Evaluate progress and plan for the future.
- Agree on the questions to be answered by the evaluation.
- Evaluate the success of the assessment process.
- Begin preparations for ongoing community-based environmental health assessment activities.
Example: Julianne Price, West Wabasso, FL
In 2004, Julianne Price took a job administering a new grant for the Environmental Health division of the Indian River County Department of Health in Florida. The grant, from the Centers for Disease Control, was for a PACE EH project in West Wabasso, a small community a couple of miles away. West Wabasso is a suburb of Vero Beach, a city that occupies one of the most affluent zip codes in the state. Price drove the short distance north through acres of golf courses and past the manicured lawns of million-dollar houses. When she came to West Wabasso, however, she found herself in a different world.
“It was like something out of a developing country. There were tiny houses, most – but not all – with electricity, but many without running water. The streets were dirt, there were no sidewalks. There was a park, but it wasn’t in great shape. There was just nothing there…and we were a mile from a wealthy neighborhood of huge homes.”
West Wabasso was a traditionally Black community that had essentially remained unchanged from the days of legal segregation in the 1960’s. There were no city services, no public transportation, no sewage system. Water for most houses came from hand-dug wells or from an antiquated water system that produced brown water…not discolored, not with traces of iron in it, but brown. Septic systems were hand-made tanks (and totally illegal – they had no bottoms.) Price, then in her late 20’s, had never seen anything like it. She set out to get to know the community.
“It was really hard to get people to open up; no one wanted to talk to me. The Health Department had been there before, and had made promises that were never kept. They’d taken information, and then used it to get funding for other projects. People were justifiably suspicious. They just didn’t trust government to do anything to help their situation. Besides, they were afraid I was there to get them in trouble. In their experience, when the government came around, you wanted to be somewhere else, or you’d be cited for something.
“The key was face-to-face time. I just went there every day and talked to people, anyone who’d talk to me. I talked to community leaders and to people out in front of their houses. I went to the churches, to the school, to community events. I was just there all the time, building relationships one person at a time. Eventually, they got the idea I wasn’t going to go away like the others had, and they started telling me what they needed.”
What they needed was what Price wanted to find out, so that she could start putting together a CEHA (Community Environmental Health Assessment) team. It took several months, but she eventually managed to get on the agenda at a meeting of the West Wabasso Civic Progressive League to introduce the PACE EH project and ask for help.
“I stood up to talk, and people just started yelling. They weren’t really yelling at me, but they had so much anger and frustration about the way they’d been treated in the past that they just had to get it out.”
At that first meeting, however, Price did manage to survey the crowd, and found that the number one item on their wish list was streetlights. It stunned her: why streetlights, when they had no clean water and no effective sewage disposal? In talking to people, she found the answer to her question: there were abandoned buildings in town that had been turned into crack houses, and a notorious drug lord lived in the community as well. Residents, many of them elderly, were afraid to go out at night in their own community.
Besides the survey, there were two major consequences of that first meeting: “The Civic League invited me to take over their meetings for several months, to work on the PACE process. And we grabbed the low-hanging fruit: we got the street lights, which was fairly easy. Within seven months, streetlights were in place, and the people were involved in the process. They started believing that something might really happen.”
About five months after coming to West Wabasso, Price was able to put together a Steering Committee (the CEHA team). She emphasizes that it’s important to identify issues before assembling a team, so that you’ll know who you need. “It was obvious that water was an issue, so I got the Director of the County Utilities Department involved. I brought him to a meeting at a church where a man stood up and talked about how embarrassed he was that he and his family had to wash in brown water, how it gave them sores and stained their clothes so that they couldn’t look respectable no matter what they did. The Utilities guy was practically in tears, and I knew we’d get a water system.”
It took time to get to that point, however. From the beginning, Price started calling various county and state agencies, trying to get them involved. “I’d call and explain the situation, and then I wouldn’t ever get called back. I knew how the folks in Wabasso felt.”
Price used the media to help get agencies involved. “I contacted a reporter who came to Wabasso and saw the situation. The issues were so apparent, he latched right on, and wrote a bunch of stories about how the community was ignored. Agencies started coming around at that point.” Price also cultivated personal relationships with people at agencies she worked with. People are much more likely to return phone calls when they know the person on the other end of the line as a human being, rather than as a proverbial faceless bureaucrat.
In addition, the community was becoming empowered. They were learning how to contact their legislators to pressure agency administrators, and how to find their way through the labyrinth of county bureaucracy to reach someone who could get them results.
As agencies became involved, Price conducted tours of West Wabasso for adminstrators that included interviews with residents, demonstrations of the water that came out of their taps, and drives by notorious crack houses. Bringing legislators or their aides along markedly improved attendance by agency administrators.
With the multi-pronged demonstration of need, help was soon forthcoming. West Wabasso, in addition to streetlights and a water system, got sidewalks, park improvements (including a walking trail), and grants for septic system upgrades and home improvements. For a $30,000.00 investment in the PACE EH project by the Health Department, the community received about $1.3 million in services and improvements.
Another positive result of the process was that those crack houses that made residents hesitant to leave their houses at night were knocked down, and three new houses built (each in one day, for residents who had lost homes to weather or decay) with volunteer labor by contractors and donations of building materials by local businesses. Both the knockdowns and the construction were coordinated by the sheriff, who himself had grown up and still lived in West Wabasso. During the first construction day, a man came up to him and said that he had seen the positive changes in the community and wanted to do something to help. It turned out that he was one of the drug lord’s henchmen. He went undercover and helped the sheriff take down his boss, who is now in jail for the next 20 years or so. Thus, an unexpected result of the PACE EH process was that 15 abandoned houses were demolished and hauled away, and a serious crime problem was eliminated.
Julianne Price mentions that 90% of PACE communities around the state have identified substandard and abandoned houses as a serious issue. West Wabasso was clearly not alone in its concerns.
Price is convinced that PACE really does what it’s intended to do. It makes possible developing relationships with community leaders, and facilitates collaboration among agencies. Most important, it makes government an ally, rather than an adversary, of communities in need. “We as government need a vehicle for getting things done in communities that the communities want and need. Without PACE, you have to use enforcement to get things changed. If you cite poor people for illegal septic systems, it doesn’t change anything – they don’t have the money to fix the problem, and the Health Department can’t force anyone… But with PACE, the community can show the problems, and enlist government to help.”
Furthermore, involvement in PACE both taught community members political skills – learning to use the system, establishing relationships with legislators and agency administrators – and developed their administrative and planning capacity as well. PACE funding is long gone from Wabasso, but the West Wabasso Civic Progressive League has taken over its function: it has a five-year development plan, and the community is sustaining its improvements and moving forward without help from the Health Department.
Price still administers local PACE projects directly – three at the moment – but she’s also now the state coordinator for PACE, overseeing more than 45 projects statewide. She’s acutely aware of the need to quantify PACE’s results, and states with pride that the total of $800,000.00 invested in PACE has brought a return of $21 million worth of improvements to Florida communities. That’s about a 2,300% return on investment – somewhat better than Wall St. can promise.
For Julianne Price, the personal rewards of her involvement have been great as well. She still spends time in West Wabasso, because she has people to see there. The minister from one of the churches that helped in the PACE process officiated at her wedding, and she describes the sheriff as her best friend. When a tree fell on her house during a hurricane, five men from West Wabasso were there the next morning with chain saws to repair the damage. It’s clear that the West Wabasso community regards her as family. For someone who cares about community building, it doesn’t get much better than that.
Tool #1: A filled-out framework
Tool #2: A framework map translated into indicators
Tool #3: Environmental Health Issue Ranking Worksheet
Tool #4: Priority-Setting Worksheet: Environmental Health Issue